

Next Lesson - Anxiety and Anxiety Disorders
Core
A subarachnoid haemorrhage (SAH) occurs when there is arterial bleeding into the space surrounding the brain and spinal cord beneath the arachnoid mater. It is a clinical emergency and must be recognised and treated rapidly to prevent irreparable complications and death.
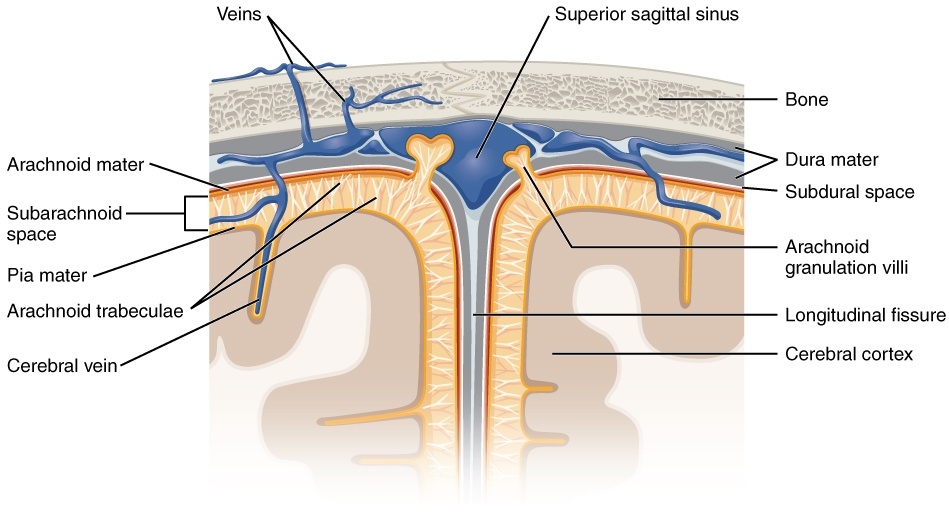
Diagram - The meningeal layers surrounding the brain. The bleed takes place in the subarachnoid space
Source illustration: OpenStax, source, CC BY 4.0.
Overall, the most common cause of a subarachnoid haemorrhage is head trauma; however, in spontaneous (non-traumatic) cases, the usual cause is rupture of a cerebral aneurysm. Examples of trauma could be due to a road traffic accident or due to a fall.
SAH can also occur spontaneously, commonly following rupture of a cerebral aneurysm. Aneurysm formation involves blood-flow forces and multifactorial arterial wall remodelling, including degeneration of the internal elastic lamina and tunica media. It cannot be explained simply by erosion of the intima.
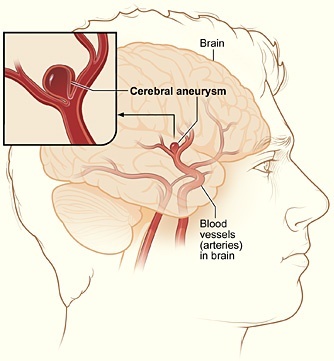
Diagram - A cerebral aneurysm in the brain
Public Domain Source by National Institutes of Health [Public domain]
Non-traumatic causes of an SAH are related to the modifiable and non-modifiable risk factors a patient can present with. These are not direct causes of a haemorrhage but can increase the risk of developing a bleed.
Cerebral aneurysms often arise at arterial branch points, where local flow patterns act on susceptible vessel walls. Common sites include the anterior communicating artery complex, the internal carotid–posterior communicating artery junction and middle cerebral artery bifurcations. These sites are not explained by pressure passing from a large artery into a smaller communicating artery.
Modifiable risk factors are factors that can be reduced through changes to the patient’s lifestyle or medications, and include cigarette smoking, heavy alcohol use and hypertension.
Non-modifiable risk factors are those that cannot be changed through any intervention and include connective tissue disorders, polycystic kidney disease, arteriovenous malformations, and a positive family history of subarachnoid haemorrhage. These risk factors can all perpetuate the formation of aneurysms in the brain, either by increasing the pressure of the blood flowing through the vessels or reducing the integrity of the arterial wall.
When the arterial wall gives way a large volume of arterial blood is released very quickly into the subarachnoid space, found between the pia and arachnoid mater. This event triggers a cascade of complex mechanisms in the brain that can be split into Early Brain Injury and Delayed Cerebral Ischaemia.
This occurs immediately after vessel rupture and encompasses the direct effect of the haemorrhage on the brain tissue and the compensatory mechanisms of the brain. The direct bleeding effects are the most common cause of mortality.
The extravasation of a high volume of blood initially causes a mechanical compression of the brain, resulting in direct damage to the cerebral tissue. Secondary to this, the mixing of the blood with cerebrospinal fluid (CSF) can impede normal CSF clearance, resulting in an acute phase hydrocephalus in approximately 20-30% of patients.
The increased volume in the subarachnoid space causes a rapid rise in the intracranial pressure (ICP) which correspondingly decreases the cerebral perfusion pressure (CPP), resulting in a reduced flow of blood to the brain tissue. (For more information on cerebral autoregulation, see our article on Raised Intracranial Pressure). Arteriolar dilation reduces vascular resistance and attempts to support cerebral blood flow. It does not restore a critically low CPP; severe pressure elevation and impaired autoregulation can overwhelm this compensation, producing acute global ischaemia.
Following this transient period of ischaemia, there is gradual reperfusion of the brain tissue as the blood flow returns which causes the added problem of cerebral reperfusion injury. Oxidative damage occurs in the brain due to the increased production of reactive oxygen species (see our article on Oxidative Stress). These radicals act by directly damaging the neurovascular structures in the brain, increasing inflammation, breaking down the blood-brain barrier and releasing more vasoconstrictors.
Alongside these mechanisms, the extravasated blood itself is an irritant to the brain tissue, resulting in spasming of the arteries, inflammation and cerebral oedema. There is also the inappropriate production of microthrombi, secondary to the activation of platelets which attempt to clot the original haemorrhage, which further blocks the blood supply.
Summary of early brain injury: a big haemorrhage compresses the brain tissue and stops drainage of CSF, both of which raise intracranial pressure. This decreases the cerebral perfusion pressure, cutting off blood supply to the brain and encouraging the formation of radical oxygen species. As reperfusion occurs, oxidative stress further damages the brain, causing oedema and further swelling.
In the days following SAH, some patients develop delayed cerebral ischaemia (DCI), with a new neurological deficit or reduced consciousness. DCI is multifactorial; large-artery vasospasm is only one contributor. Urgent specialist assessment is needed to distinguish it from other causes of deterioration, including rebleeding and hydrocephalus.
A subarachnoid haemorrhage presents with a sudden onset, ‘thunder-clap’ like headache with patients commonly describing it as the worst headache they have ever experienced. This develops over seconds to minutes, reaching peak intensity rapidly, and the headache may then persist for hours.
Other associated signs may include vomiting, seizures, neck stiffness and a decreased or absent level of consciousness, all resulting from the increased intracranial pressure which blocks the normal flow of CSF in the cranium. The patient’s level of consciousness must be monitored carefully, as it directly correlates to the extent of their neurological dysfunction and can be predictive of their outcome. However, none of these signs may be present.
It is very important to differentiate a SAH from meningitis. Both can present similarly, but the rapid identification and treatment of SAHs can help to minimise the risk of mortality and any further complications.
Patients presenting with a suspected SAH should always have an urgent CT scan of the head, without contrast. This helps to identify the presence of subarachnoid blood, which will guide any following management. A positive result is seen when there is an area of increased density around the Circle of Willis, depicting blood in the basal cisterns.
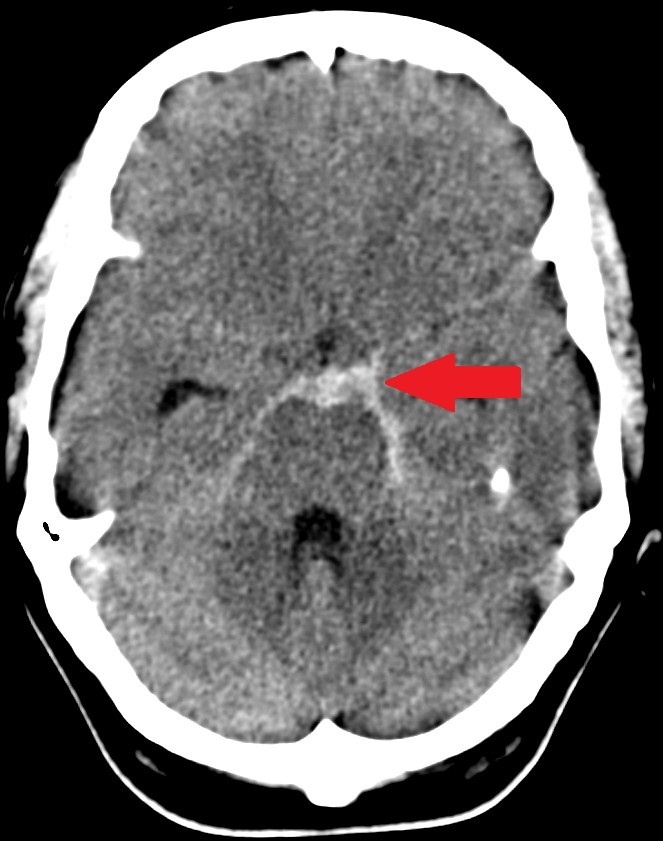
Image - A CT slice of the human brain. In the centre, there are hyper-dense (brighter) areas corresponding to blood in the subarachnoid basal cisterns (area highlighted by red arrow)
Source illustration: Lipothymia, source, CC BY-SA 3.0.
After SAH is confirmed, offer CT angiography promptly to identify the cause and guide specialist treatment.
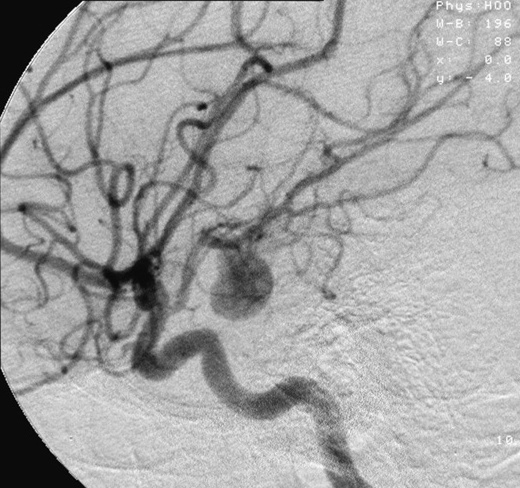
Image - Angiograph of an aneurysm in a cerebral artery
Source illustration: Lucien Monfils, source, CC BY-SA 3.0.
After a radiologist-reported and documented negative CT within six hours of onset, do not routinely offer lumbar puncture; discuss alternative diagnoses with a senior clinician and seek specialist advice. After a negative CT performed more than six hours after onset, consider lumbar puncture, allowing at least 12 hours from onset and checking for contraindications.
When lumbar puncture is indicated, diagnose SAH if CSF shows elevated bilirubin (xanthochromia) on spectrophotometry; visual inspection alone is insufficient.
All patients with a confirmed SAH must be placed under continuous observation, especially monitoring for any further neurological deterioration or systemic side effects of the event, such as a myocardial infarction or pulmonary oedema. Provide effective analgesia, including opioids when needed, and account for sedating effects during neurological assessment. Decisions about antiplatelets or anticoagulants require specialist risk assessment. Once the culprit aneurysm has been secured, do not withhold these drugs solely because of the history of aneurysmal SAH.
There are two main components of managing a patient with a SAH:
- Reducing delayed ischaemic complications. Consider enteral nimodipine after confirmed SAH. Its clinical benefit is not adequately explained by prevention of angiographic vasospasm alone; DCI has multiple mechanisms.
- Prevention of a re-bleed. This is done by repairing the affected blood vessel, so the aneurysm does not burst again. This can be done using one of two surgical techniques.
- Coiling involves a catheter being inserted through an artery in the groin and up to the brain. Small platinum coils are then passed through the tube and into the aneurysm, preventing any further blood from entering it.
- Clipping on the other hand involves the surgeon accessing the aneurysm via a flap of bone in the skull (craniotomy) and securing a small metal slip around the base of the aneurysm. This effectively cuts off the blood supply and prevents the aneurysm from re-growing or re-bleeding.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell
- 799



