

Next Lesson - Diuretics
Core
Micturition is the process of passing urine. It can be split up into storage (filling the bladder) and voiding (emptying the bladder) phases. These phases are antagonistic: the mechanisms that favour storage oppose those that favour voiding.
During the storage phase, the volume of urine in the bladder increases gradually, and initially the pressure inside the bladder (intra-vesical pressure) stays at the same low level. After around 150 ml of urine in the bladder, the brain often becomes aware of bladder filling. Even as filling continues, the intra-vesical pressure normally changes little or not at all, because the bladder wall is compliant (it stretches easily). At volumes of around 400 to 600 ml, the urge to void is usually strong, although this varies between individuals.
During the voiding phase, the detrusor muscle (the smooth muscle of the bladder wall) contracts in a single, continuous contraction. Pressure increases as the contraction builds, and the contraction continues until the full volume of the bladder is voided.
The graph below shows the relationship between intra-vesical pressure and volume.

Diagram - Graph showing the relationship between increasing intra-vesical volume and pressure
SimpleMed original by Dr. Joshua Sturgeon
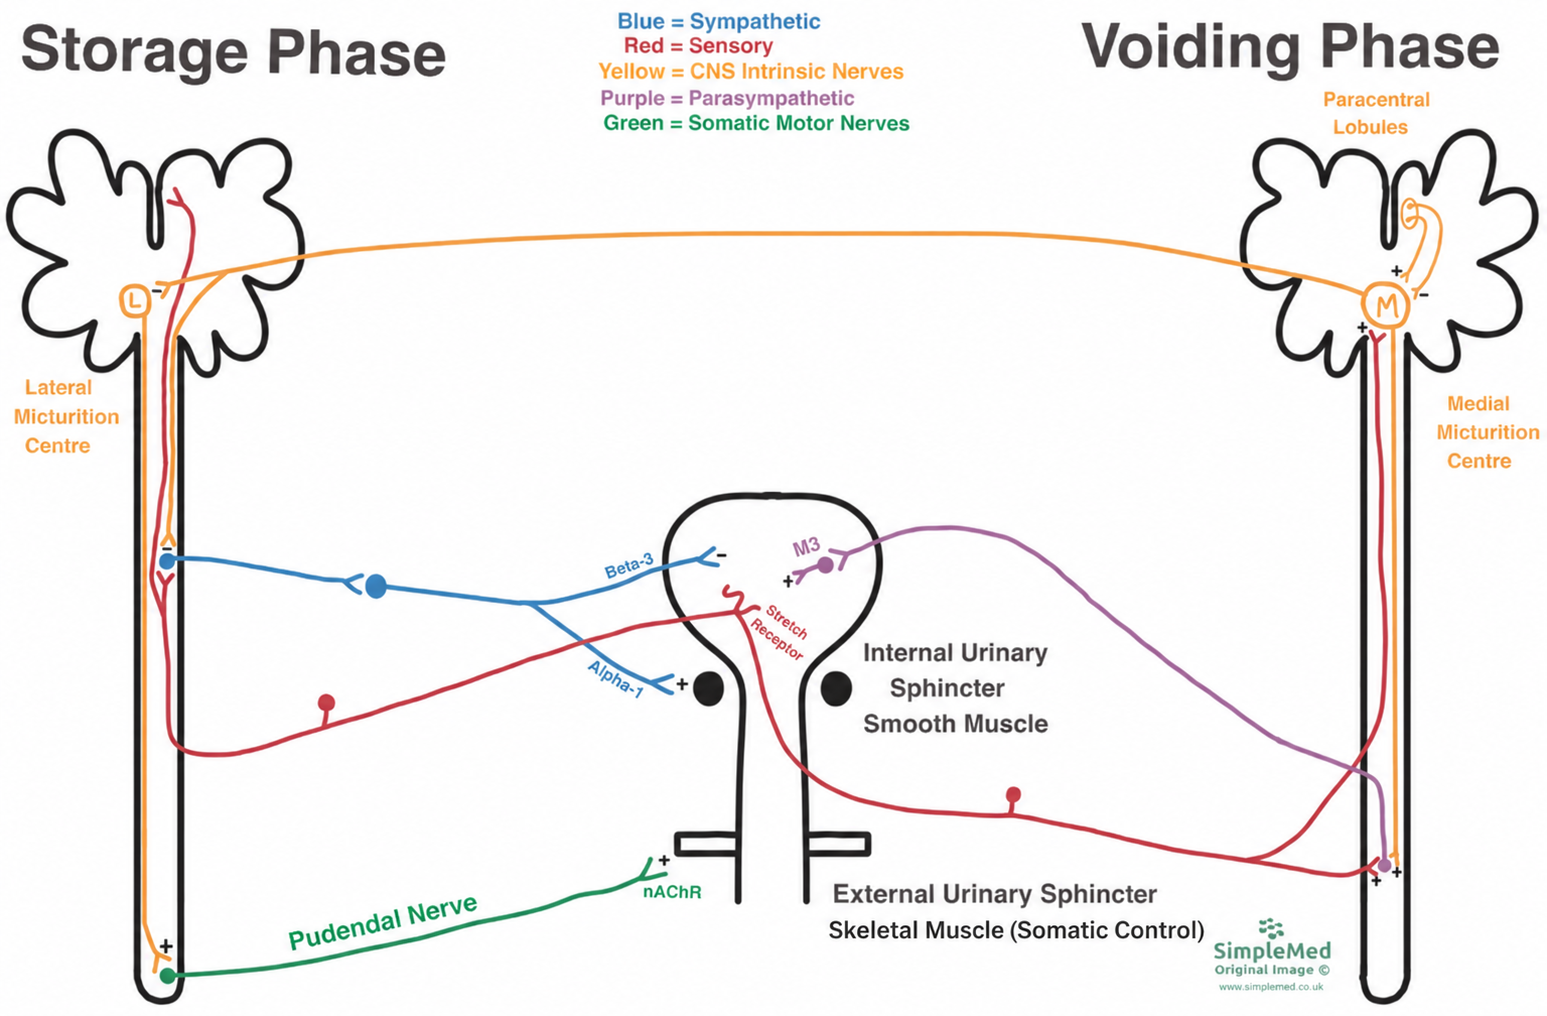
Diagram - Neural control of storage and voiding. The detrusor receives parasympathetic input; the external urethral sphincter is skeletal muscle under somatic control. A minus sign denotes inhibition and a plus sign denotes stimulation.
SimpleMed Original by Dr. Maddie Swannack, with contributions from Dr. Joshua Sturgeon
Stretch receptors in the bladder detect the level of filling. Sensory neurones carry this information to the spinal cord, and it is then relayed up to the cortex, which gives the feeling of the bladder filling.
Sensory neurones also synapse with sympathetic neurones in the spinal cord. The sympathetic neurones act to stimulate the internal urinary sphincter (IUS, also called the internal urethral sphincter) through alpha-1 adrenoceptors (the receptors that sympathetic neurones act on). The sympathetic neurones also help to relax the detrusor muscle through beta-3 adrenoceptors (the receptors that make the bladder muscle relax). How much this relaxation matters in humans is less clear. The bladder wall is also compliant (it stretches easily), so the pressure stays low as the bladder starts to fill.
The lateral micturition centre (often referred to as the pontine storage centre, because it lies in the pons) is located in the brain stem (the pons is its middle part). It continually sends excitatory (stimulating) action potentials down the cord to the neurones of the pudendal nerve. The pudendal nerve carries somatic motor neurones (neurones that supply skeletal muscle) to the pelvic floor and the external sphincter. It arises from the sacral nerve roots S2, S3, and S4. It acts on the external urinary sphincter (EUS, also called the external urethral sphincter) through nicotinic acetylcholine receptors (the type of acetylcholine receptor on skeletal muscle). The pudendal nerve stimulates the EUS to contract, meaning the lateral micturition centre acts to retain urine.
The voiding phase involves a large amount of input from the cerebral cortex. This allows for voluntary control over voiding, but it is important to recognise that in some situations, such as emergencies, voiding cannot always be postponed.
The paracentral lobules are in the cortex, on the inner surface of the frontal and parietal lobes. They send inhibitory (dampening) and excitatory (stimulating) action potentials to the medial micturition centre in the pons of the brain stem. The medial micturition centre sends inhibitory signals to the sympathetic and somatic neurones in the spinal cord, which relaxes the IUS and EUS. It also stimulates parasympathetic neurones in the spinal cord.
Stretch receptors in the bladder also send excitatory action potentials to the parasympathetic neurones as well as directly stimulating the medial micturition centre when the bladder becomes full.
These parasympathetic neurones synapse with other parasympathetic neurones in the bladder. The second set of neurones act via stimulatory M3 muscarinic receptors (acetylcholine receptors on smooth muscle) and cause contraction of the detrusor muscle. So the medial micturition centre and the parasympathetic nervous system act to encourage micturition, but the cerebral cortex can override this drive to void.
Cauda equina syndrome (CES) is a medical emergency which arises due to compression of the spinal nerves in the spinal canal below the end of the spinal cord. The cord usually ends at about the level of the first lumbar vertebra (L1). Symptoms include sciatica (pain spreading down the leg) in both legs, or pain that starts in one leg and spreads to both. They also include perianal anaesthesia (numbness around the anus and genitals, sometimes called saddle numbness), difficulty starting to pass urine, and reduced sensation of urine flowing. Sexual dysfunction can also occur. Urinary retention (being unable to empty the bladder), overflow incontinence (leaking when the bladder is overfull) and faecal incontinence are late signs.
Suspected CES is also a surgical emergency, because the nerves may need urgent decompression (an operation to relieve the pressure on them). It needs urgent MRI scanning, followed by assessment by a spinal or neurosurgical team. The Getting It Right First Time (GIRFT) national pathway advises that an emergency MRI should be done as soon as possible, and certainly within four hours of the request to radiology (the imaging department). The request for the scan should be discussed with a senior decision-maker (a senior doctor, for example a consultant) before it is made. Discussing the patient with the spinal team first is not required and may delay the scan. Best practice is to scan at the hospital where the patient presents, in and out of hours. A catheter (a tube to drain the bladder) may also be needed in urinary retention as a supportive measure.
CES can cause incontinence through several mechanisms:
- Damage to Sacral Parasympathetic Pathways - parasympathetic efferent (outgoing motor) fibres supply the detrusor muscle. Damage to these pathways can impair bladder contraction and emptying, causing urinary retention with possible overflow incontinence.
- Damage to Sensory Neurones - this means patients cannot feel how full the bladder is, again leading to overflow incontinence.
- Pudendal Nerve Damage - the pudendal nerve supplies the external urethral sphincter through somatic motor fibres. Injury can weaken sphincter closure and contribute to leakage. It does not necessarily leave the sphincter permanently open or cause constant leakage; the pattern depends on the combined effects on bladder sensation, detrusor function and outlet (urethral sphincter) control.
Damage to the lowest end of the spinal cord (the conus medullaris) causes conus medullaris syndrome. It overlaps with CES and can look similar, but it is a lesion (area of damage) in the cord itself, known as a central lesion. CES is a lesion of the nerve roots, known as a peripheral lesion.
A complete transection of the mid-spinal cord cuts the pathways between the brain and the sacral spinal cord. The brain therefore loses control of the bladder, because the parasympathetic neurones lose the inhibition that normally comes from above the spinal cord (supraspinal inhibition). At first there is spinal shock, a temporary loss of reflexes below the injury, with urinary retention. As spinal shock settles, a reflex bladder (one that contracts by a spinal reflex, without control from the brain) typically develops, with involuntary detrusor contractions. Coordination with sphincter relaxation is lost, because the detrusor contracts while the sphincter also contracts (detrusor-sphincter dyssynergia), so effective voiding does not occur. High bladder pressures put the upper urinary tract (the ureters and kidneys) at risk. The patient needs to be catheterised to drain the bladder and relieve the pressure. The NICE guideline on urinary incontinence in neurological disease (CG148) advises telling people that indwelling urethral catheters (catheters left in place in the urethra) may carry higher risks of kidney complications, such as kidney stones and scarring, than other forms of bladder management. An example of another form is intermittent self-catheterisation, where the person passes a catheter to empty the bladder and then removes it.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 6386
