

Next Lesson - Pneumothorax and Pleural Effusion
Core
Tuberculosis (TB) is a chronic, communicable (able to spread from person to person) disease, caused by the bacteria Mycobacterium tuberculosis. TB occurs worldwide, but in 2024 most new cases were in South-East Asia, the Western Pacific and Africa (WHO regions). TB is uncommon in the UK (9.4 reported cases per 100,000 people in England in 2024), but about 82% of cases are in people born outside the UK. Rates are also more than 5 times higher in the most deprived areas than in the least deprived, and higher in some social risk groups, such as people who are homeless or who use drugs.
Mycobacterium tuberculosis is an aerobic organism with a lipid-rich cell envelope containing mycolic acids (waxy fatty acids), which makes Gram staining (the standard dye test for most bacteria) unreliable. Ziehl-Neelsen staining is one method of visualising these acid-fast bacilli (rod-shaped bacteria that keep the red dye even after being washed with acid); fluorescent acid-fast stains are also used. Microscopy alone does not identify the mycobacterial species or establish drug susceptibility (which antibiotics the bacteria respond to). Culture can take several weeks, depending on the method.

Image - Mycobacterium tuberculosis as imaged using the Ziehl-Neelsen staining method
Public Domain Source by Public Health Image Library [Public domain]
TB is transmitted by inhaling airborne infectious droplet nuclei (tiny particles left when infected droplets dry out), and only a small number of bacilli may be required to establish infection, depending on host and environmental factors.
Once the bacilli are inhaled by the body, alveolar macrophages engulf the bacterial deposits in alveoli. The bacteria then stop the phagosome (the sac that holds the engulfed bacteria) fusing with lysosomes (sacs of digestive enzymes), partly through their lipid-rich cell wall, so the macrophages are unable to kill them.
The macrophages initiate cell-mediated immunity (the part of the immune system run by T lymphocytes). The release of Interferon-γ (a signalling protein that activates macrophages) by the cell mediated immune system allows further activation of macrophages. These activated macrophages release reactive oxygen species (ROS, chemically aggressive oxygen molecules) to try to kill the bacteria, and cytokines (chemical messengers between immune cells) to promote an inflammatory response. These macrophages are now known as epithelioid macrophages (which are just macrophages that look like epithelial cells on microscopy). Some of the macrophages fuse, to form Langhans giant cells (multiple epithelioid macrophages fused together, with the nuclei arranged in a horseshoe).
The epithelioid macrophages ingest the tuberculosis bacteria but cannot kill them, even with the help of the cell mediated immune system (T lymphocytes). This causes a granulomatous reaction. It forms a tubercle, a spherical granuloma (a ball of immune cells walling off the bacteria) with central caseation (cheese-like dead tissue). Under the microscope you are able to see caseous necrosis, epithelioid macrophages, Langhans giant cells and lymphocytes in a TB granuloma.

Image - Two Langhans giant cells marked by the green arrows. Note the horseshoe of nuclei
Creative commons source by Humpath, edited by Dr. Maddie Swannack [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The initial TB infection with creation of the tubercle occurs on the first exposure to Mycobacterium tuberculosis. The bacilli then deposit in the alveoli. This usually forms a primary or Ghon’s focus, a sub-pleural group of these tubercles (just under the pleura, the lining of the lung), which can occur in any lung zone.
The bacilli then drain from the primary focus into the hilar lymph nodes (the lymph nodes at the root of each lung). The combination of the hilar lymph nodes and the primary focus is together known as the primary complex.
To recap:
- Tubercle - a spherical granuloma with central caseation, caused by the macrophages ingesting Mycobacterium tuberculosis.
- Primary/Ghon’s Focus - a sub-pleural collection of tubercles, which can occur in any lung field after initial TB exposure.
- Primary Complex - the primary focus plus the hilar lymph nodes into which the bacilli drain.
Most TB infections at this stage will heal, either with or without calcification (the scar hardening with calcium) of the primary complex.
Before containment, TB bacilli may enter the bloodstream via lymphatic drainage, resulting in haematogenous spread (spread through the blood) to other parts of the lung and other organs. Cell-mediated immunity may contain the infection, allowing latent tuberculosis without symptoms of active disease, but containment is not guaranteed: primary infection can progress directly to active TB. Granulomas occur in both latent and active infection and do not by themselves establish latency.
In latent tuberculosis, the patient has the infection present but no symptoms of active disease. The person will remain well, but the potential for reactivation at any site is always present. Reactivation usually occurs when the host’s immune response is impaired, for example by infection with HIV, a haematological malignancy (a blood cancer), long-term immunosuppressive treatment (high-dose corticosteroids, chemotherapy or biologic drugs such as infliximab, an anti-TNF-alpha drug), or substance misuse (for example excessive alcohol or injecting drug use). At this point, the epithelioid macrophages containing the bacilli will fail, and the bacilli will spread, causing active infection again.
Latent TB: About 5 to 10% (up to 1 in 10) of people infected with TB go on to develop active disease at some point in their life. This can happen either through the development of primary TB at the initial time of infection, or due to reactivation of latent TB following initial infection. The risk is higher in babies, children and people with a weakened immune system.
Primary TB occurs when the primary complex doesn’t heal, but instead progresses to active TB. The pathology seen in primary TB is similar to the pathology in reactivation of latent TB.
Reactivation of latent TB occurs most often in the lungs, most commonly in the upper lung zones. The reason is not fully settled: the higher pO2 (partial pressure of oxygen) there suits the aerobic bacteria, and poorer lymph drainage of the upper zones may also contribute.
The following sequelae (complications) can occur after activation through either mechanism:
- Cavity Formation - the caseous material undergoes liquefaction (turns to liquid), and is then discharged into a bronchus. This causes the patient to cough up the material as thick phlegm. Fibrous tissue forms around the necrotic tubercle in an attempt to limit the rupture of tubercles and spread of bacilli, but isn’t usually successful.
- Haemorrhage - the necrosis spreads into vessels in the cavity walls, causing haemorrhage into the tubercle.
- Involvement of the Rest of the Lung - once a tubercle ruptures into the bronchi, infected material spreads the infection through the bronchial tree and into other lung zones.
- Pleural Effusion - a collection of fluid in the pleural space caused by either the presence of bacilli in the pleura or a hypersensitivity reaction, both of which cause inflammation.
- Miliary Tuberculosis - a focus ruptures into a blood vessel, and the bacilli spread throughout the body. Many tiny ‘miliary’ foci (nodules the size of millet seeds) form in the lungs and other organs, such as the brain (causing TB meningitis, infection of the membranes around the brain), spleen, liver or bone marrow.
Extra-pulmonary tuberculosis is active TB in sites other than the lungs, for example after reactivation of latent TB. Note the difference from miliary TB, in which the bacilli spread through the blood to the lungs and other organs. Common sites include lymph nodes, bones, joints, the central nervous system, GI tract and urinary tract. This can cause a wide variety of symptoms depending on which organ systems are affected.
TB has a gradual onset, and symptoms of pulmonary TB include:
- Tiredness
- Weight loss
- Fever (possibly with sweats)
- Cough - dry or productive, often lasting more than 3 weeks
There may also be haemoptysis (coughing up blood) due to the haemorrhage discussed earlier, but this will not happen in every patient and is usually a late feature.
There may be crackles (crackling breath sounds) on auscultation, but there may also be no clinical signs present, so a chest radiograph (chest X-ray) is an important first investigation. It cannot establish the diagnosis alone, because samples must be tested for the bacteria. If there is fibrosis or a pleural effusion present, then clinical signs of these may be apparent.
TB is more likely, and should therefore be considered, in people who were born outside of the UK, have lived in an area where TB is common, are immunocompromised (have a weakened immune system), or have been in close contact with someone with TB.
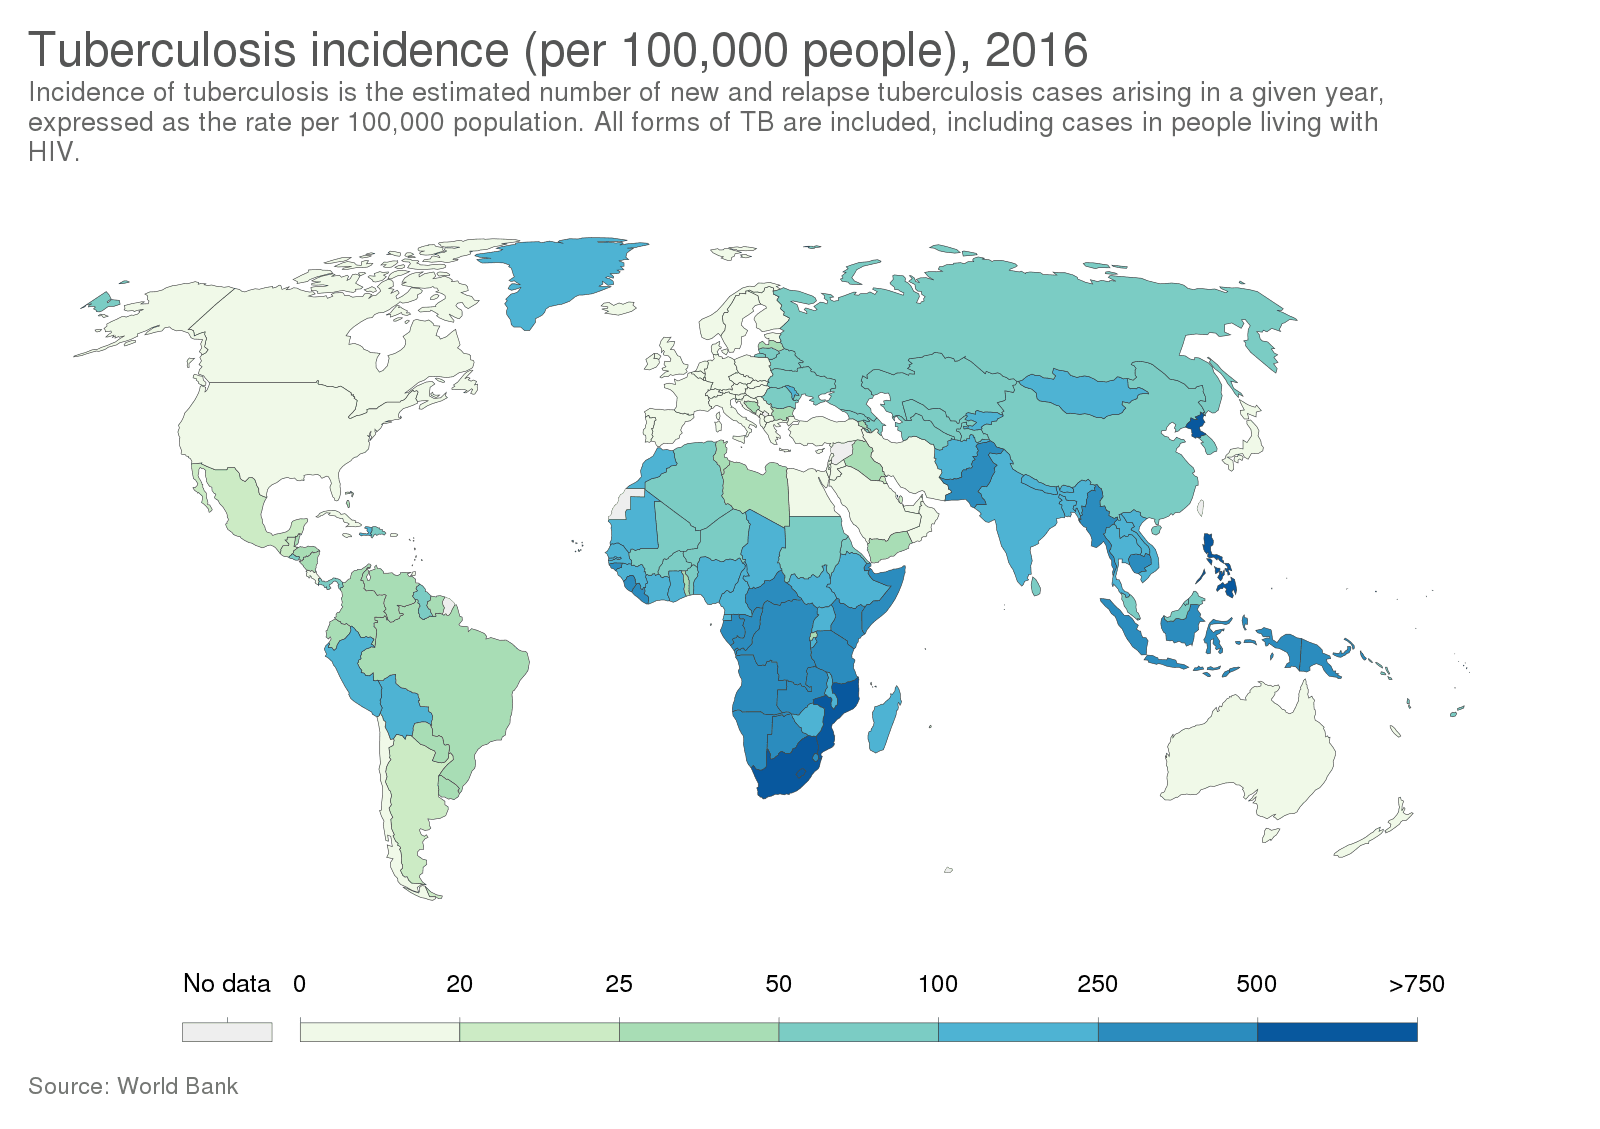
Diagram - The incidence (new cases in a year) of tuberculosis in 2016. The darker the blue, the more cases in that region. This information can be helpful when determining if a patient is at high risk of contact with TB
Creative commons source by Our World In Data [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Two tests used to assess TB infection are the QuantiFERON blood test (an interferon-gamma release assay, IGRA) and the Tuberculin (Mantoux) skin test. Neither IGRA nor Mantoux distinguishes active from latent infection. Assess for active disease before treating infection as latent, because treating active TB as if it were latent TB (too few drugs for too short a time) can lead to drug resistance.
- The QuantiFERON test is based on the ability of Mycobacterium tuberculosis antigens to stimulate the host production of interferon gamma from T Lymphocytes.
- A blood sample is taken from the patient, and their lymphocytes are then cultured with antigens of Mycobacterium tuberculosis. If a patient has been exposed to TB before, T lymphocytes will produce interferon gamma in response.
- The antigens used in this test are absent from BCG (Bacillus Calmette-Guérin, the TB vaccine) and most non-tuberculous mycobacteria. Prior BCG vaccination therefore does not usually cause a positive IGRA, unlike the Mantoux test. A positive IGRA supports TB infection but does not establish whether it is active or latent.
- In the Tuberculin or Mantoux skin test, tuberculin, a protein derived from mycobacteria, is injected intradermally (into the skin).
- If the patient has been previously exposed to TB there is usually a type IV hypersensitivity reaction (a delayed reaction driven by T lymphocytes) at the injection site between 48-72 hours after the injection. The result is read as the width of the firm raised area (induration) in millimetres, and NICE treats 5 mm or more as a positive result.
- However, this test can give false results. False positives can occur if the patient has had a previous BCG vaccine or if they have been infected with a non-tuberculous mycobacterium in the past (an atypical organism).
- False negatives can also occur if a patient is immunocompromised, as this may affect their ability to mount the hypersensitivity response.

Image - Administration of the tuberculin skin test
Public Domain Source by Centers for Disease Control and Prevention, Greg Knobloch [Public domain]
On a chest radiograph there may be shadowing (areas that look whiter than normal lung). This may take the form of patchy solid lesions, cavitated solid lesions, or streaky fibrotic flecks of calcification.

Image - Chest radiograph showing the shadowing seen in primary pulmonary TB. It shows the inflammation contained to one area (the right lower and middle lobes)
Creative commons source by "The Radiological Diagnosis of Pulmonary Tuberculosis (TB) in Primary Care". Journal of Family Medicine and Disease Prevention 4, Basem Abbas Al Ubaidi [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]

Image - Miliary TB, when the Mycobacterium tuberculosis has spread throughout the lungs (shown by the hazy appearance across all lung fields) due to spread through a blood vessel
Creative commons source by James Heilman, MD [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
However, a definitive diagnosis is established by identifying the bacillus in culture, usually of a sputum (coughed-up mucus) sample. NICE advises sending 3 deep cough sputum samples, preferably including 1 early morning sample, for microscopy and culture. If the signs and symptoms fit TB, treatment is started without waiting for the culture result. In extra-pulmonary TB, the tests depend on the site. They can include a biopsy or needle aspiration (taking a sample of tissue or fluid), a lumbar puncture (a needle sample of spinal fluid) for central nervous system TB, and a CT or MRI scan if the central nervous system may be involved.
Tuberculosis is treated through a long course of several antibiotics. NICE guideline NG33 recommends this starting antibiotic treatment for active TB that does not involve the central nervous system. A clinician with training and experience in TB leads treatment, and the regimen is modified according to drug susceptibility testing:
- Rifampicin (6 months)
- Isoniazid (6 months)
- Pyrazinamide (2 months)
- Ethambutol (2 months)
The four drugs should be taken at the same time. Take all four for the first two months, then take only rifampicin and isoniazid for a further four months. For TB of the central nervous system, treatment is longer: after the first two months, rifampicin and isoniazid continue for a further ten months, and a corticosteroid (dexamethasone or prednisolone) is added at the start. This combination therapy is used to prevent the increase of antibiotic-resistant strains, and to negate the effect of already resistant strains, as it is unlikely that the infection will be resistant to all four drugs.
These drugs can cause a wide range of side effects, some of them serious (this is just a selection):
- Rifampicin can cause hepatitis, orange colouring to the secretions (e.g. urine, tears), thrombocytopenia (a low platelet count, which can cause a purpuric rash from bleeding into the skin), and failure of the COCP due to induction of the liver enzymes that normally metabolise it.
- Isoniazid can cause hepatitis, peripheral neuropathy (damage to the nerves of the hands and feet) and psychosis (losing touch with reality).
- Pyrazinamide can cause hepatitis, gout (painful joint inflammation from uric acid crystals) and arthralgia (pain in the joints).
- Ethambutol can cause optic neuritis (inflammation of the optic nerve) and loss of vision. Early stopping of the drug is almost always followed by recovery of eyesight, so visual acuity is tested before treatment and patients should report any change in vision.
Because of these side effects, extra medicines are often given alongside TB treatment: for example, vitamin B6 (pyridoxine) should be taken with isoniazid to prevent peripheral nerve damage.
The infectivity of sputum often becomes minimal after two weeks of commencing effective treatment in drug-susceptible pulmonary TB, meaning the patient is usually less infective to others, but the course must be finished to eradicate the disease in infected people.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 7249



