

Next Lesson - Hepatic, Biliary and Pancreatic Pathology
Core
Sialolithiasis is the medical term for stones in the salivary glands or the salivary ducts that pass saliva from the glands into the mouth. The calculi (stones) are mainly composed of calcium phosphate but can contain a variety of other compounds such as urate (a salt of uric acid). The calculi can form in any salivary gland: the submandibular gland (under the jaw, the most common site), the parotid gland (in front of the ear) or the sublingual gland (under the tongue).
The causes of salivary stones are not fully understood, and the evidence for some risk factors is weak. Factors that are often listed include:
- Dehydration - lower water content in saliva increases concentration which predisposes to stones
- Gout - high uric acid levels may predispose to urate stones
- Smoking
- Hyperparathyroidism (overactive parathyroid glands in the neck) - hypercalcaemia (high blood calcium) may predispose to calcium phosphate stones
- Anti-cholinergic medications - these drugs can cause a dry mouth (less saliva)
The evidence is mixed. A recent US case-control study (a study that compares people who have a condition with matched people who do not) found links with Sjögren’s syndrome (an autoimmune condition that reduces saliva) and obesity. It found no significant link with dehydration, hyperparathyroidism, smoking or gout.
This condition can be asymptomatic (without symptoms) or may present with intermittent pain (often when eating as this is when saliva is released) or intermittent facial swelling. Symptoms are usually unilateral.
Diagnosis of this condition is usually made based on history and examination. If further investigation is needed, it usually begins with an ultrasound scan or a plain X-ray. Most salivary calculi are radio-opaque (they show up on X-ray). This applies to about 80% of submandibular stones and about 60% of parotid stones, so a normal X-ray does not rule out a stone. A sialogram (an X-ray taken after contrast dye is injected into the duct) can show stones and strictures (narrowings).
Conservative management is to increase salivation with citrus fruit consumption to dislodge the stone alongside analgesia to manage the pain. If this is unsuccessful a minor operation to remove the stone may be required. In cases of recurrent sialolithiasis, the salivary gland producing the calculi may have to be removed but this is uncommon.
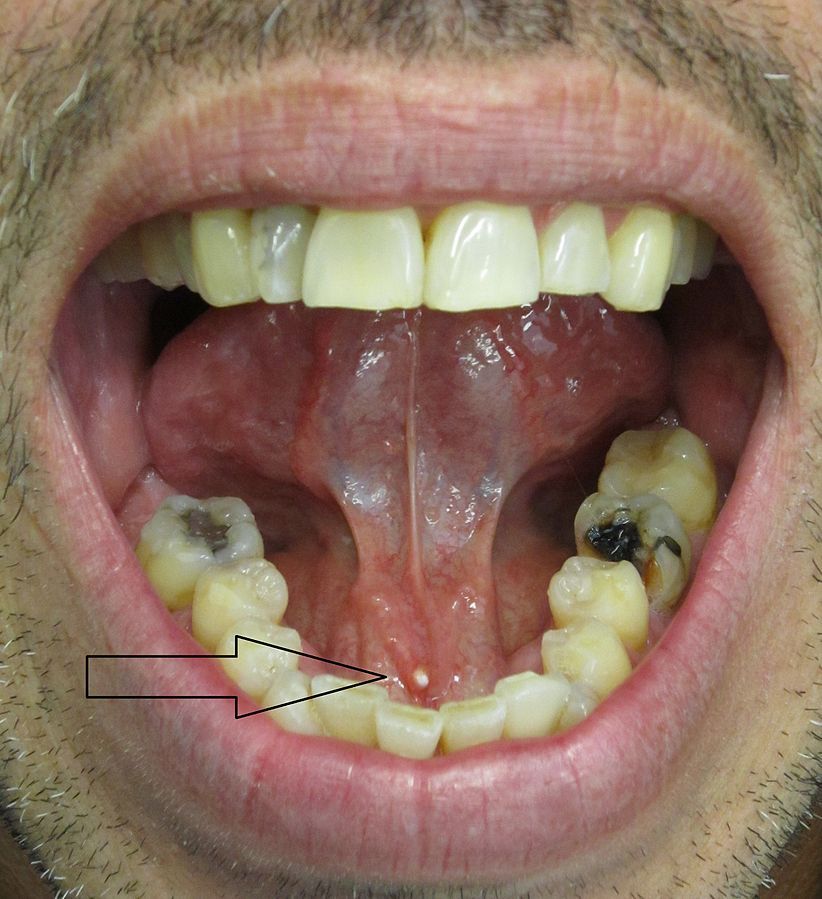
Image - Patient with submandibular sialolithiasis
Creative commons source by James Heilman, MD [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Oesophageal varices are dilated veins in the wall of the distal third of the oesophagus. They lie in the lamina propria and the submucosa (the layers just beneath the surface lining). They are a complication of portal hypertension (high pressure in the portal vein, which carries blood from the gut to the liver) and therefore risk factors are the same as those for liver disease and cirrhosis. Oesophageal varices usually cause no symptoms until they bleed. They are usually diagnosed by oesophagogastroduodenoscopy (OGD, a camera test of the oesophagus, stomach and duodenum). NICE advises offering this test to most people after a diagnosis of cirrhosis, to look for varices.
Varices that are not found by screening may only be identified when the patient presents with an upper gastrointestinal (GI) bleed. If the patient has medium or large varices, NICE advises offering carvedilol or propranolol (non-selective beta-blockers, drugs that lower the pressure in the portal vein) to reduce the chance of a bleed. Endoscopic variceal band ligation (rubber bands are placed around the varices through the endoscope) is offered instead if the tablets are not tolerated or are unsuitable, or if the patient cannot take tablets regularly.
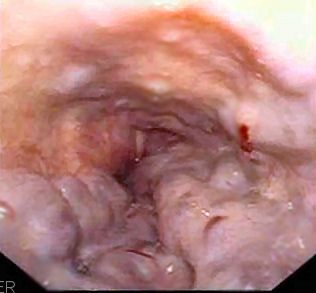
Image - View of oesophageal varices via oesophagogastroduodenoscopy
Creative commons source by Samir [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
For more information on Portal hypertension, please see the Hepatic, Biliary and Pancreatic Pathology article.
For more information on Upper GI bleeds, please see the Gastrointestinal Emergencies article.
A Mallory-Weiss tear is a tear of the mucous membrane at the gastro-oesophageal junction. It is not a full rupture of the oesophagus, that is a different condition known as Boerhaave’s syndrome.
Risk factors for a Mallory-Weiss tear are binge drinking, chronic alcoholism, and bulimia (an eating disorder with binge eating followed by purging, for example by making yourself sick). This is because these tears are most commonly caused by severe retching (dry heaving) and/or vomiting. There are other causes that also increase the intra-oesophageal pressure such as chronic hiccups, severe coughing, straining etc. However, these are much less common.
Patients typically present with haematemesis (vomiting blood), often after severe vomiting or retching. Some also have epigastric (upper central abdomen) or retrosternal (behind the breastbone) pain. Some patients have no such history: in one case series of 66 patients, 41% had no retching, vomiting, nausea or abdominal pain before the bleed. The haematemesis may be bright red blood, or partially digested blood known as coffee-ground vomiting, depending on how long the blood was present in the digestive tract. They may also have associated melaena (the passage of digested blood through the rectum).
Oesophagogastroduodenoscopy (OGD) is used to diagnose the Mallory-Weiss tear. NICE advises OGD straight after resuscitation for unstable patients with severe bleeding, and within 24 hours of admission for all other patients. Management ranges from supportive treatment until bleeding resolves to endoscopic haemostasis (stopping the bleeding through the endoscope), depending on the extent of the bleeding. NICE advises that adrenaline injection is not used on its own. NICE lists these options: a clip (with or without adrenaline), cauterisation (sealing the vessel with heat) with adrenaline, or fibrin or thrombin (clotting agents) with adrenaline.
Gastro-oesophageal Reflux Disease (GORD)
Gastro-oesophageal reflux disease (GORD) is also known as acid reflux. It is a condition where stomach acid rises up into the oesophagus.
Risk factors include:
- Hiatus hernia (part of the stomach pushes up through the diaphragm into the chest)
- Smoking
- High alcohol intake
- Obesity
- Pregnancy
- Family history
- High fatty food intake
- Stress/anxiety
- Some medicines, such as NSAIDs (non-steroidal anti-inflammatory drugs, e.g. ibuprofen)
Patients typically present with retrosternal pain (heartburn), metallic taste in the back of the throat and halitosis. Less commonly they may have an associated cough, wheeze, or hoarse voice. Diagnosis is based on history usually but OGD may be used if conservative management does not improve symptoms or complications are suspected.
Management of GORD is lifestyle advice (for example weight loss, stopping smoking, and avoiding foods and drinks that trigger symptoms) alongside a full-dose proton pump inhibitor (PPI, a drug that reduces stomach acid), e.g. omeprazole, for 4 or 8 weeks (8 weeks for severe oesophagitis). If symptoms come back, the lowest dose of PPI that controls them is used.
Oesophagitis is a complication of GORD where the oesophagus becomes inflamed. Oesophagitis can also have other causes. These include infection (for example with Candida, a yeast, or with a virus) and eosinophilic oesophagitis (inflammation involving eosinophils, a type of white blood cell). Eosinophilic oesophagitis is an increasingly common cause of dysphagia (difficulty swallowing).
Oesophagitis can be asymptomatic, but may cause epigastric/retrosternal pain or dysphagia. Initial management is the same as for GORD. In severe oesophagitis, NICE advises a full-dose PPI for 8 weeks, then a full-dose PPI long term to keep the oesophagus healed. Laparoscopic fundoplication (keyhole surgery that tightens the lower end of the oesophagus) can be considered for some people with confirmed acid reflux.
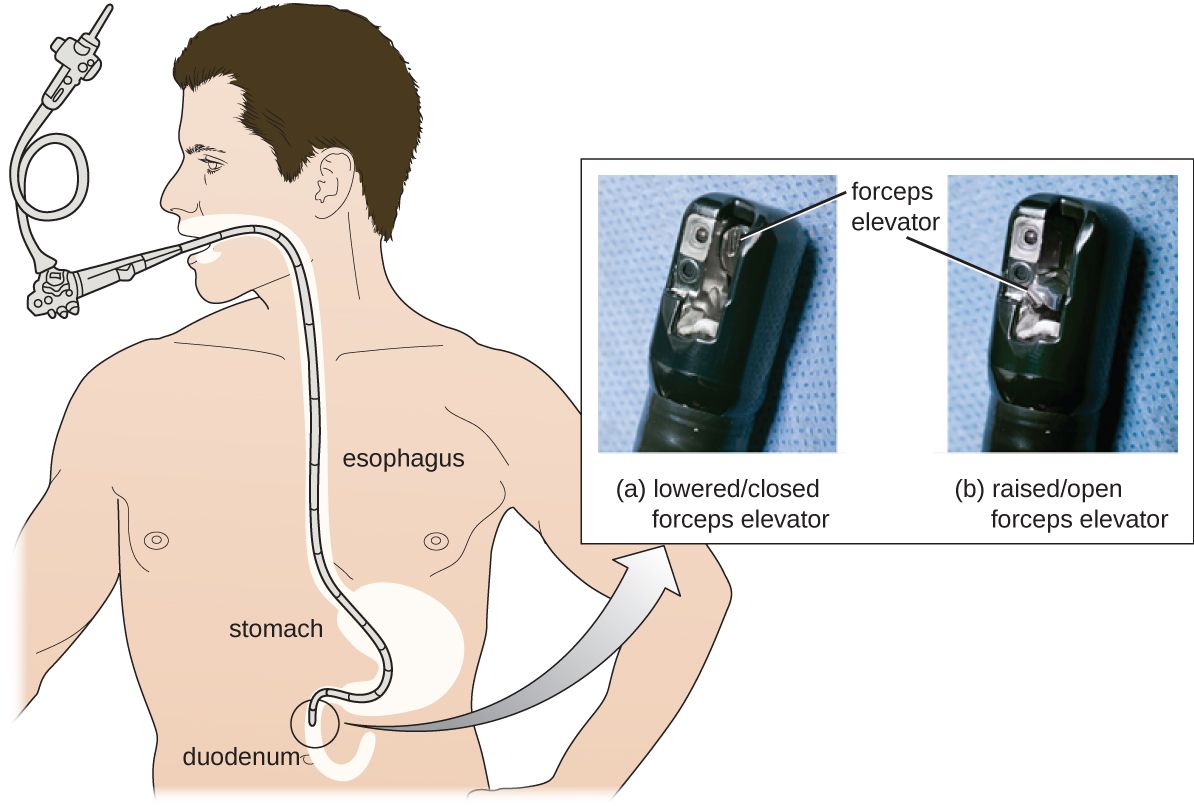
Diagram - The process of oesophagogastroduodenoscopy
Creative commons source by CNX OpenStax [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
An oesophageal stricture is a narrowing of the oesophagus most commonly linked to GORD, oesophagitis and hiatus hernias. It can present with symptoms similar to GORD as well as dysphagia (difficulty swallowing), odynophagia (painful swallowing), choking, coughing, burping and weight loss. Dysphagia and weight loss can also be signs of oesophageal cancer, so cancer must be excluded. NICE advises a suspected cancer pathway referral for anyone with dysphagia. A stricture is investigated by OGD with biopsies (small tissue samples) or by a barium swallow x-ray (an X-ray taken after drinking a liquid that shows up on X-ray).
Management involves treating the cause (e.g. GORD management). The narrowing itself is usually treated with endoscopic dilation (stretching the oesophagus with a balloon or a bougie, a rigid tapered tube) to relieve dysphagia. People who have had a stricture dilated should stay on a full-dose PPI long term. Stenting (placing a tube to hold the oesophagus open) is an option for strictures that keep coming back or do not respond to dilation alone.
Barrett’s oesophagus is a complication of oesophagitis caused by GORD. The cells lining the lower end of the oesophagus undergo a metaplastic change. Stratified squamous epithelium (flat, layered cells, the normal lining of the oesophagus) is replaced by columnar epithelium (tall, column-shaped cells). The columnar cells are often intestinal-type and include goblet cells (mucus-producing cells). The change is an adaptive (protective) response to the acid that is refluxing into the oesophagus.
The main risk factors are a history of reflux symptoms and obesity. Men, smokers and people with a family history are also at increased risk. Symptoms are the same as those of oesophagitis caused by GORD. Barrett’s oesophagus is diagnosed by OGD, where a change in the appearance of the oesophagus can be seen. The diagnosis is confirmed by biopsies (small tissue samples) examined under the microscope.
Barrett’s oesophagus is metaplasia not neoplasia (a new, abnormal growth of cells), but it is considered a pre-malignant condition (one that can turn into cancer) because it can be a precursor to adenocarcinoma (a cancer of gland-type cells) of the oesophagus. The risk is low: fewer than 1% of people with Barrett’s oesophagus develop oesophageal adenocarcinoma each year. Progression to cancer happens through an intermediate stage called dysplasia (abnormal-looking cells), which usually develops without clinical signs. For this reason, most patients are offered OGD surveillance (repeat OGD with biopsies) to identify changes early. NICE advises surveillance every 2 to 3 years for a long segment (3 cm or longer), and every 3 to 5 years for a short segment (under 3 cm) with intestinal metaplasia. Surveillance is not offered for a short segment without intestinal metaplasia once the diagnosis has been confirmed at two endoscopies.
Gastritis is the inflammation of the lining of the stomach and may be acute or chronic.
Patients often present with stomach pain, nausea, acid reflux/associated GORD or in more severe cases there can be melaena or haematemesis if a peptic ulcer has formed and/or perforated. Perforated ulcers are discussed further in the ‘Gastrointestinal Emergencies’ article.
Gastritis can be caused by:
- Helicobacter pylori - causes persistent gastric (stomach) inflammation. Its urease (an enzyme) converts urea to ammonia, which buffers acid around the organism, helping it survive in the gastric mucus. Acid output depends on the distribution of infection: antral-predominant infection (mainly in the lower stomach) can increase gastrin (a hormone that stimulates acid release) and acid secretion, whereas body-predominant infection (mainly in the body, the main part of the stomach) can cause gastric atrophy (thinning and loss of the stomach lining) and reduce acid secretion. MSD H. pylori pathophysiology; urease-mediated survival.
- NSAIDs - inhibit the prostaglandins (chemicals that help to protect the stomach lining) which would normally maintain blood flow to the mucosa of the stomach, leading to reduced perfusion.
- Heavy alcohol use - disrupts the protective barrier of the stomach lining, which includes its mucous layer.
- Autoimmune conditions - the immune system attacks the lining of the stomach.
A definite diagnosis of gastritis combines the appearance of the stomach lining at endoscopy with histology (examining biopsies under a microscope). To find out whether H. pylori infection is the cause, NICE advises testing with a ‘urea breath test’ (the patient drinks a special liquid and their breath is checked afterwards) or a stool antigen test. NICE advises offering this ‘test and treat’ approach to people with dyspepsia (indigestion). NICE advises leaving a 2-week gap after the last dose of a proton pump inhibitor (PPI) before the test.
Treatment for gastritis involves removal of risk factors (e.g. stop drinking alcohol, stop using NSAIDs etc.), and, if H. pylori is found, triple therapy (three drugs given together) to eradicate (clear) it. NICE advises a 7-day, twice-daily course of a PPI plus amoxicillin plus either clarithromycin or metronidazole. Amoxicillin, clarithromycin and metronidazole are antibiotics. People who are allergic to penicillin are given a different combination of drugs. If medical treatment is unsuccessful, further investigation with endoscopy will likely be required. NICE advises seeking advice from a gastroenterologist (a digestive system specialist) if eradication fails after second-line treatment.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 1692



