

By Dr. Ben Appleby and Dr. Ethan Kavanagh
Next Lesson - Bacterial Structure, Classification and Growth
Core
“Infection models” are usually complex mathematical models used in epidemiology. They use equations to predict outbreaks of disease and to work out ways of limiting damage and exposure. For anyone who is not an epidemiologist (a specialist in how diseases spread through populations), and for this article, the infection model is simpler. It describes the way in which a patient interacts with a pathogen. The article then looks at each stage of the model in turn.
The basic infection model illustrates the pathway a patient travels down, from pre-presentation (before they seek medical help) through to treatment and outcome.
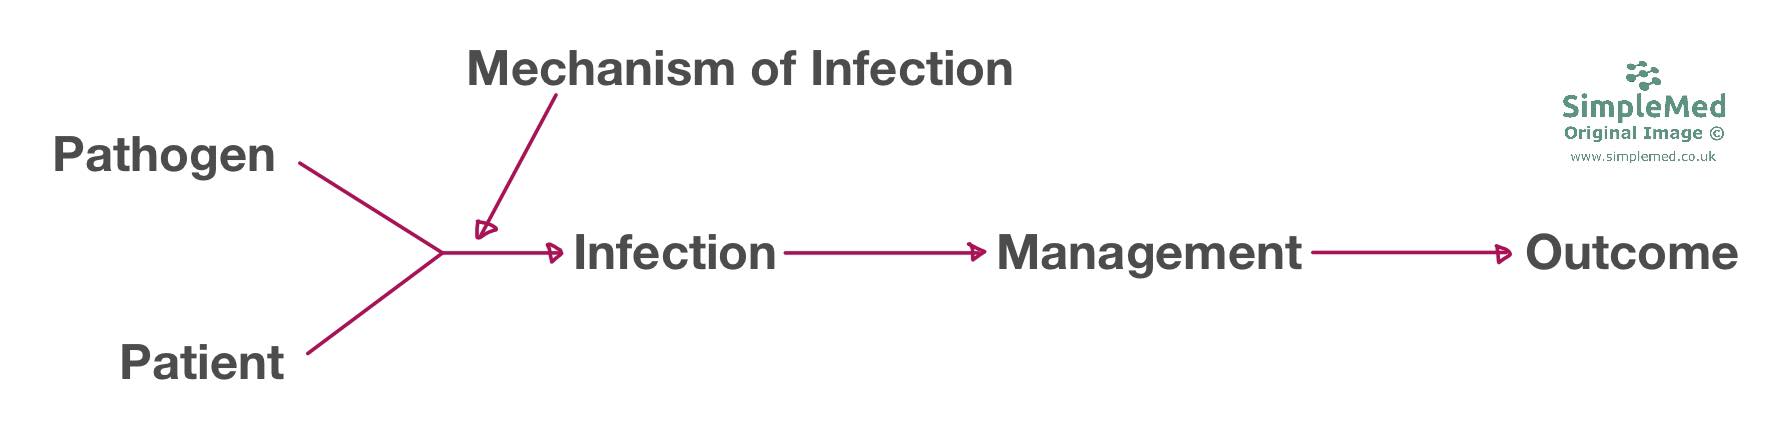
Diagram: The basic infection model, describing the pathway from a healthy patient being infected with a pathogen to their treatment and outcome
SimpleMed original by Dr. Maddie Swannack
Here is a step-by-step run-through of the basic model shown above.
Please note, the rest of the images in this article are courtesy of Dr. D Heney at the University of Leicester Medical School.

The pathogen is the agent that is causing the infection; this could be a virus, bacteria, fungus or parasite. Pathogenicity is the ability of a microorganism to cause disease. Virulence is the degree to which an organism is pathogenic. Pathogenesis is the process by which a pathogen causes disease. It has four stages. In exposure, the patient comes into contact with the pathogen. In adhesion, the pathogen attaches to the body and begins to colonise it (to settle and grow there). In invasion, the pathogen spreads through local tissues or the body. In infection, the pathogen multiplies successfully and causes damage.
Viruses - two categories, based on their genetic material: DNA viruses and RNA viruses
Bacteria - categorised by structure and Gram stain (a staining test that sorts bacteria into Gram-positive and Gram-negative groups). See our Gram staining and infection investigations article for a full run down.
Fungi:
Yeasts (single cells) e.g. Candida albicans, Cryptococcus neoformans, Pneumocystis jirovecii
Moulds (multicellular) e.g. Aspergillus, dermatophytes (fungi that infect the skin, hair and nails)
Parasites:
Protozoa (single-celled parasites) - e.g. Giardia lamblia, Plasmodium falciparum, Trypanosoma cruzi
Helminths (parasitic worms) - roundworms (nematodes) and flatworms (platyhelminths), which include tapeworms (cestodes) and flukes (trematodes)

The Patient is the uninfected individual who encounters the pathogen and may become infected (also referred to as the susceptible). Their likelihood of infection (their susceptibility) depends on factors about themselves, including:
- Age
- Sex (UTIs are commoner in females because the female urethra is shorter, so bacteria are more likely to reach the bladder and cause an infection)
- Physiological state (overall physical fitness and whether pregnant)
- Pathological state (what current diseases the patient has, and any comorbidities, which are other diseases they have at the same time. For example, people with AIDS are immunocompromised, meaning their immune system is weakened. They are therefore susceptible to opportunistic infections, which mainly affect people with a weakened immune system)
- Social factors (quality of housing, food and water quality/safety, IV drug use, sexual partners, proximity of living e.g. Meningitis spreading in university halls previous to the ACWY vaccine.)
Time matters in two ways:
- Calendar time is important as it is helpful in narrowing down the possible microorganisms the patient has been exposed to at a certain time of the year (seasonal organisms). For example, the influenza virus can be caught at any time of year, including the summer. However, it is much less likely to be a differential in summer when a patient presents with respiratory distress. A differential (or differential diagnosis or DDx) is a list of possible conditions which could explain a patient’s condition.
- Relative time is the time between exposure and development of symptoms (incubation period) or the time between the development of additional symptoms.
Place
- Current location: hospital, or the community (that is, with little or no contact with healthcare). This is again relevant in predicting exposure.
- Recent travel history (especially relevant in tropical diseases).

The mechanisms by which a pathogen can infect the patient are many, and they are covered in the Introduction to Infection.
How a pathogen spreads helps to determine how quickly it can pass through a population. The potential for spread can be estimated using the R0 of a pathogen, also known as the basic reproduction number. This figure measures how easily a disease spreads. It is the average number of secondary infections (new cases) produced by one typical case in a population where nobody is immune (a totally susceptible population). Put simply, it describes how many additional people are infected by each infected patient. For example, if R0=2, each infected patient will pass the infection on to two other people on average. At the start of an outbreak, an R0 above 1 means the outbreak is expected to grow, and an R0 below 1 means it is expected to die out. Later, as more people become immune or control measures are introduced, the number of new cases per case changes. This current reproduction number (R) is what decides whether the outbreak keeps growing or ends. The figure depends on the pathogen, including its mechanism of infection and how long the patient stays infectious. It also depends on the population and setting, such as how much people mix, population density and behaviour. R0 is not a fixed biological constant for a pathogen, and it is not a measure of how severe a disease is.

Management is usually the first step in which a medical professional is involved. It starts with a diagnosis where possible, using the history, examination and investigations. Treatment for the infection then follows. Treatment is usually empirical - targeting the most likely cause of infection even if it has not been confirmed via bacteriology i.e. microscopy, culture and susceptibility testing (MC&S).

There are two broad types of treatment: specific and supportive
Specific treatment focuses on treating the underlying cause of a disease. For an infectious disease this involves giving antimicrobials (antibiotics, antivirals, antifungals or antiparasitic drugs) that the pathogen is known to be susceptible to. Empirical treatment (see Management) is usually started first, while the cause is still unknown. Once the cause has been identified, for example from culture results, treatment is tailored to it. NICE advises considering a review of intravenous antimicrobial prescriptions at 48 to 72 hours, looking at the response to treatment and the microbiological results, to decide whether the antimicrobial needs to continue and, if so, whether it can be switched to an oral one.
Alongside antimicrobials, in some cases surgery can also be used to treat an infection:
- Drainage is used when there is a large collection of pus (an abscess), e.g. under the skin. Draining the pus reduces the bacterial load (the amount of bacteria present) and gives the patient’s immune system a better chance of clearing the infection.
- Debridement refers to the removal of infected/damaged/dead tissue. This helps the surrounding healthy tissue to heal by reducing the bacterial load and removing tissue that cannot be saved. If this tissue is left in place, it may lead to further complications. Debridement may be carried out by surgical excision (cutting the tissue out) or by other means, including maggot therapy.
- Dead space removal means closing or filling an empty space that infection could move into (possibly created by debridement), so that the infection cannot spread. In bone infection, for example, surgeons may use a tissue flap (a section of the patient's own tissue moved into the gap) or fill the space with beads or pellets, which can be loaded with antibiotics.
Supportive treatment is aimed at treating the symptoms of a disease, lessening the impact of the side effects of treatment and overall improving patient comfort.

Infection prevention involves stopping an infection spreading from one patient to another in a clinical or community setting. The 4 main areas of infection prevention can be remembered as the 4 P’s:
- Patient- minimise patients' risk factors for infection by optimising health and controlling interaction with visitors and other patients e.g. by isolating infectious patients in side rooms. Patients with airborne infections, such as tuberculosis (TB), measles or chickenpox, are nursed in a single room with the door kept closed, as a minimum. Negative pressure rooms (specially ventilated isolation rooms that stop infected air escaping) are used for the highest-risk patients, for example those with suspected or known multidrug-resistant TB (TB that is resistant to several of the usual TB drugs). Prophylactic antibiotics (antibiotics given to prevent infection) may also be used in patients at high risk of serious infection. Examples are immunosuppressed patients (patients with a weakened immune system) and asplenic patients (people with no working spleen). In asplenia, daily antibiotics are often recommended to protect against serious infection. This is essential in the first few years after the spleen is lost, and some patients need to take them for longer. Phenoxymethylpenicillin (penicillin V) is used to prevent pneumococcal infection (infection with Streptococcus pneumoniae) in asplenia.
- Pathogen - prevent the pathogen from causing infections. This can be achieved by minimising inappropriate antibiotic use to limit resistance (when bacteria are no longer killed by an antibiotic) and ensuring good levels of vaccination within the general population. Healthcare workers should also be up to date with their routine vaccines (for example MMR, which protects against measles, mumps and rubella). They should also have any extra vaccines their role needs, such as hepatitis B for staff who may come into contact with patients' blood. Staff must not provide care while they could pass an infection on to others.
- Practice- modify healthcare worker activity to prevent iatrogenic spread of disease (spread caused by healthcare itself). This includes effective hand hygiene and professional dress standards including the policy ‘bare below the elbow’ preventing long sleeves, watches, jewellery etc from harbouring and spreading germs. This is also supported by the infection prevention and control (IPC) team, which advises on local policies and is told about any possible outbreaks. In NHS trusts, a director of infection prevention and control (DIPC) leads this work and reports to the trust board. The Health and Social Care Act 2008 code of practice on the prevention and control of infections sets out the infection control standards that NHS bodies and other registered providers, including GP practices, are expected to meet. Providers must have regard to it, but it is not mandatory. It replaces the earlier 2015 edition.
- Place- this covers the environment the patient is in and the equipment used. It includes sterilisation and disinfection of equipment and the ward environment to eliminate reservoirs of infection (places where pathogens live and multiply).
In the community, the main ways to prevent infections are avoiding risk factors, immunisation, and prophylaxis (preventative treatment) together with contact tracing. Contact tracing means finding and advising the people who have been in contact with an infected person.
An example of avoiding risk factors would be a child with chickenpox (caused by the varicella zoster virus). The child would stay off school or nursery until all the spots have formed a scab. They would also stay away from susceptible people (those who are not immune) who are at risk of serious illness, such as newborn babies, pregnant women and people with a weakened immune system. People who have already had chickenpox are usually immune, so they are no longer susceptible. In England, since January 2026, chickenpox vaccination has also been part of the routine NHS childhood schedule, as the MMRV vaccine (measles, mumps, rubella and varicella).
Contact tracing and prophylaxis are used for some infections, including some notifiable diseases. Notifiable diseases are diseases that doctors must report when they suspect them, without waiting for laboratory confirmation. In England the report goes to the UK Health Security Agency (UKHSA), to help prevent outbreaks and further spread. Contact tracing involves finding out who the patient has recently been in contact with. Where prophylaxis is recommended, those contacts are then given treatment (such as antibiotics or a vaccine) to prevent them from developing and spreading the disease.
The main aim of vaccination is to protect the person who is vaccinated. Vaccines can also protect the wider population through herd immunity (also called population immunity). Immunising one individual removes them from the pool of susceptible individuals who may catch the pathogen. If enough people are vaccinated ("the herd"), then there are too few susceptible people for the microorganism to spread to while an infected person is infectious. This concept also helps protect those who cannot be immunised, including immunosuppressed individuals and children who are too young to be immunised. The NHS in the UK runs a full immunisation programme. The NHS vaccination schedule lists the vaccines offered and when to have them.
Healthcare-associated infection (HAI)
For an infection to be classed as healthcare-associated rather than community-acquired, it must not have been present or incubating (developing, but not yet causing symptoms) when the patient was admitted. In practice, infections that develop more than 48 hours after admission are commonly classed as HAIs. Surveillance (the routine monitoring and counting of infections) definitions often word this as onset on day 3 or later of the stay, counting the day of admission as day 1. HAIs can also develop in other healthcare settings, such as long-term care facilities, or after the patient has gone home. HAIs should be avoided because they can worsen the patient’s condition, cause complications, and add to the cost of a longer stay and use of a bed.

Outcome describes the final condition of the patient post-infection. Outcome is a spectrum ranging from complete cure to death with chronic infection/long-term morbidity/disability in between.
Edited by: Dr. Marcus Judge and Dr. Ben Appleby
- 11184
