

Next Lesson - Labour and Delivery
Core
The placenta is the organ that facilitates the survival and growth of the fetus in the uterus. The placenta acts as the source of oxygen and nutrients (in place of the lungs and gastrointestinal tract) for the growing fetus. It is also the route for the excretion of waste (in place of the gastrointestinal tract and kidneys).
Implantation begins with attachment of the blastocyst to the endometrial lining, usually about six days after fertilisation. The blastocyst (the early ball of cells) must first hatch from the zona pellucida (its protective shell). This allows trophoblast cells (the outer cells, which form the placenta) to contact the endometrium (the lining of the uterus). Invasion and embedding follow over the next few days, and the blastocyst is completely embedded in the endometrium by about day 11. Around day 9, spaces called lacunae (small gaps) form in the syncytiotrophoblast (the outer layer of the trophoblast). Maternal blood later fills these spaces, which lays the foundation for exchange between mother and embryo.
The aim of implantation is to establish a unit of exchange between the mother and fetus by anchoring the embryo in the endometrium and creating the placenta.
The placenta begins to form in the second week after fertilisation. It develops from the trophoblast, the first cell type to specialise in the embryo, and is needed to provide nutrients and oxygen to the growing embryo. If a healthy placenta does not form, the pregnancy cannot continue, because no fetus can grow without this supply from the placenta. A diseased placenta can lead to miscarriage, and also to other problems such as poor fetal growth (fetal growth restriction) or pre-eclampsia. If implantation fails, the pregnancy cannot continue.
The placenta is a specialised structure with a fetal part and a maternal part. The fetal part develops from the chorion (the outer membrane around the fetus), and the maternal part is formed by the decidua basalis (the part of the decidua beneath the embryo). The trophoblast cells that have developed as part of the outer cell mass of the embryo will become the placenta (‘tropho’ means to feed). In the diagram below, the trophoblast is shown in pale blue. The trophoblast layer differentiates and can be separated into the outer syncytiotrophoblast and the inner cytotrophoblast layers. This is shown in the fourth image below, with the syncytiotrophoblast being shown in pale blue and the cytotrophoblast being shown in darker blue.
Following implantation, the amniotic membrane (the inner membrane, which surrounds the fluid-filled amniotic sac that holds the fetus) is separate from the chorionic membrane (the outer membrane, which contributes to the placenta). As the amniotic cavity enlarges, the two membranes fuse by 17 to 20 weeks of gestation to form the amniochorionic membrane, which lines the amniotic sac until birth. The diagram below does not show this fusion, as the chorionic sac is very tiny.

Diagram - How the embryo attaches to the endometrium. It is important to note that the trophoblast differentiates into the cytotrophoblast and the syncytiotrophoblast in the fourth image
SimpleMed original by Dr. Maddie Swannack
The chorionic villi are structures within the placenta which maximise the exchange of nutrients, gases, and waste products between the mother and the fetus.
Villi are finger-like projections which act to increase the surface area of a membrane to facilitate diffusion. They are found at multiple sites in the body including the small intestine.
In the placenta, the chorionic villi are the site at which substances are exchanged between mother and fetus. The villi are arranged in groups of ‘villous trees’ (so called as they look like small trees) to further increase surface area.
The chorionic villi are made up of 3 layers. The outer layer is made of syncytiotrophoblast cells, which cover a layer of cytotrophoblast cells. At the centre is a core of connective tissue, where fetal blood vessels later develop.
The villi are bathed in maternal blood supplied by spiral arteries (the coiled arteries of the uterine lining that supply the placenta; they carry blood at high flow and low resistance). The membrane of the villi separates the maternal and fetal blood, and prevents them from mixing. Therefore the transfer of gases, nutrients, and waste products occurs across the membrane. At the start of the pregnancy, this membrane is very thick but as the pregnancy progresses it begins to thin. The cytotrophoblast layer reduces as pregnancy progresses, so the exchange barrier becomes much thinner and is dominated by the syncytiotrophoblast, closely associated with fetal capillary endothelium.
The placenta has three adaptations that make diffusion as efficient as possible. The surface area is maximised by the chorionic villi. A constant diffusion gradient is maintained by rich blood flow from endometrial vessels and from fetal vessels within the villi. The diffusion membrane is as thin as possible: in specialised regions of the villi, the syncytiotrophoblast (a fused sheet of cells) lies very close to the lining of a fetal capillary.
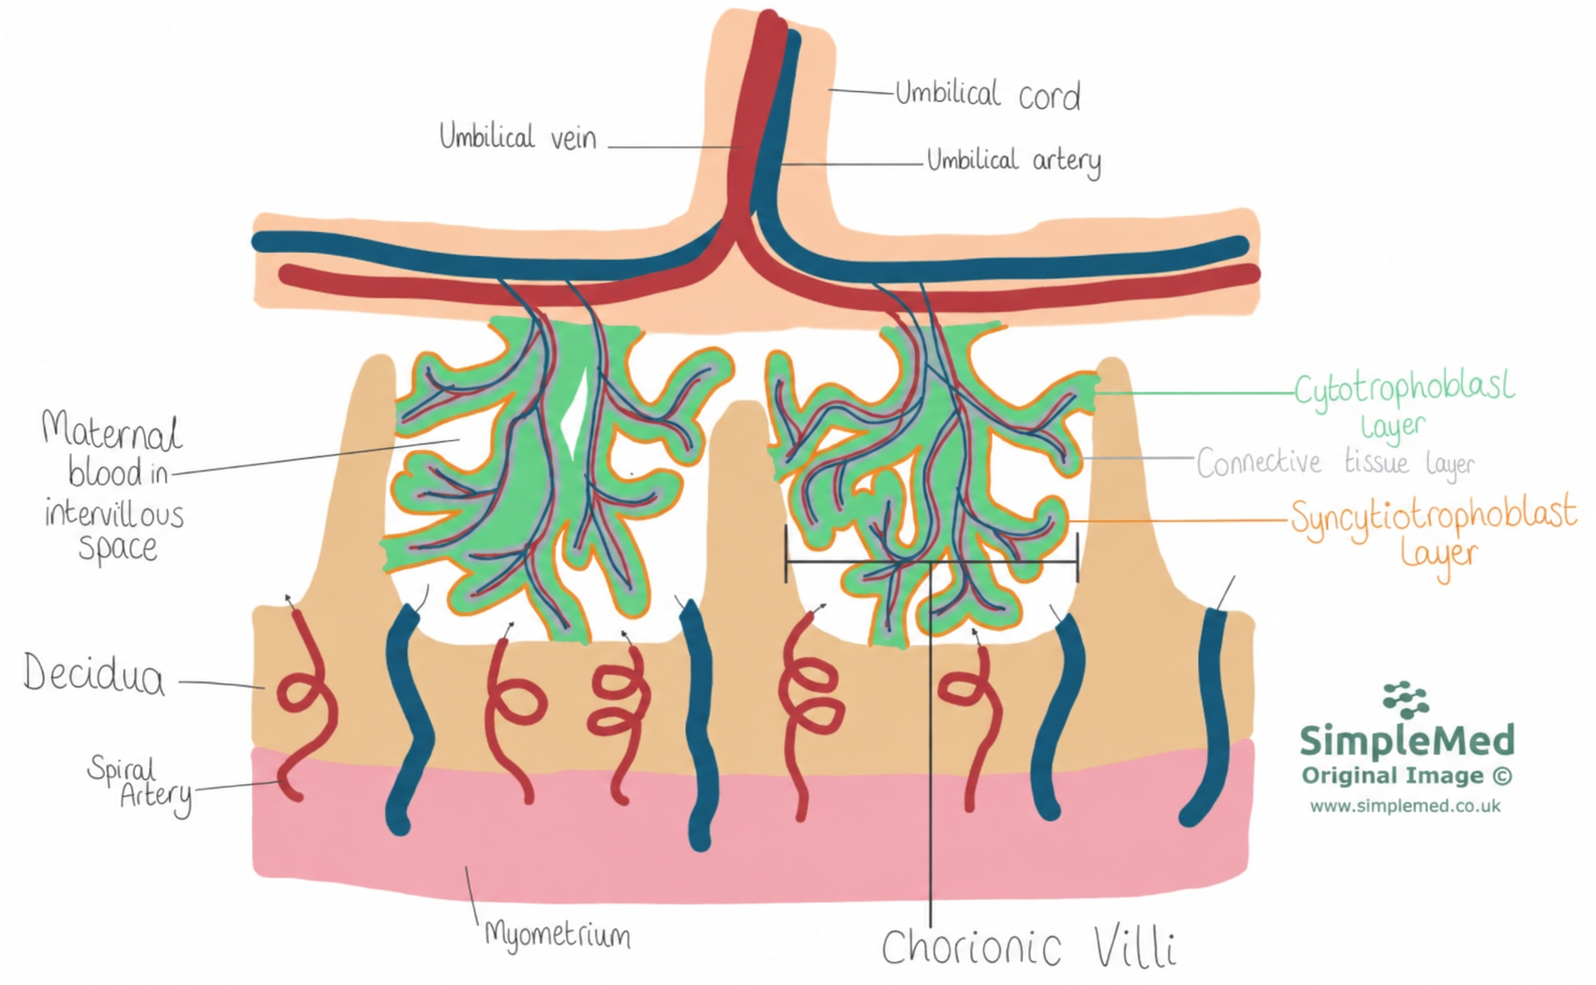
Diagram - The relationship between the maternal and fetal circulations in the placenta
SimpleMed original by Dr. Maddie Swannack
The decidua is the modified endometrium (the lining of the uterus) that forms under the influence of progesterone. In humans, decidualisation (the change of endometrial cells into decidual cells) begins in each menstrual cycle after ovulation and does not need an embryo. Without a pregnancy, the decidualised lining is shed at menstruation. With a pregnancy, the decidua is maintained and supports implantation and placental development.
The decidua of pregnancy modulates the degree of invasion into the endometrium that the embryo can achieve. This occurs through a process called ‘decidualisation’ and is controlled by factors that promote or inhibit this reaction.
Control of invasion by the decidua is important. Sometimes the embryo implants in an area where there is no decidua, for example in an ectopic pregnancy in a fallopian tube (the tube that carries the egg from the ovary to the uterus). There is then nothing to regulate invasion and therefore no control of the depth of invasion. If implantation occurs in the correct place but the decidual reaction (decidualisation) is not completed properly, it can lead to a range of complications where pregnancy is not maintained (e.g. causing miscarriage). Another result of the decidual reaction not occurring properly is that the invasion is not the correct depth. Invasion that is too shallow can lead to pre-eclampsia, and invasion that is too deep can lead to placenta accreta.
Implantation usually occurs on the anterior or posterior wall of the body of the uterus. This is a suitable place for implantation, as it allows the uterus to expand with the growth of the fetus and allows for vaginal delivery. However, implantation can occur elsewhere, which can cause serious problems.
If implantation occurs outside the uterus (usually in a fallopian tube), this is termed an ‘ectopic pregnancy’.
The most common site of ectopic pregnancy is in the ampulla (the widest, middle part) of the fallopian tube. Ectopic pregnancies can be life-threatening if they split open the fallopian tube (ruptured ectopic). If the fetus does not have enough space to grow, or invades tissue without decidua, it can damage nearby structures and cause massive haemorrhage. Haemorrhage from a ruptured ectopic pregnancy can become rapidly life-threatening due to rich blood supply to the uterus and fallopian tubes. A ruptured ectopic pregnancy can be life-threatening, so it should be ruled out as a matter of urgency in any woman of childbearing age who presents with abdominal pain. A pregnancy test is an important initial investigation, but further assessment is usually required to exclude an ectopic pregnancy.
If implantation occurs in the inferior portion of the endometrium, the growing placenta can block the internal os (the inner opening) of the cervix (the neck of the uterus). This means that the birth canal is blocked and that the baby cannot be born vaginally without tearing through the placenta and causing massive haemorrhage. This condition is called placenta previa (or ‘placenta first’) and is managed through delivery of the baby by Caesarean section.
Pre-eclampsia is new high blood pressure after 20 weeks of pregnancy, together with at least one other new problem such as proteinuria (protein in the urine) or organ dysfunction. It involves placental stress and maternal endothelial dysfunction, meaning impaired function of the cells lining maternal blood vessels. Inadequate trophoblast invasion and spiral artery remodelling (the normal widening of the uterine spiral arteries so that they carry more blood to the placenta) can impair placental perfusion. Placental release of factors that inhibit blood-vessel growth contributes to widespread endothelial dysfunction, raised maternal blood pressure and organ injury. The hypertension is part of this disease process, rather than a compensatory response intended to improve placental blood flow. Pre-eclampsia can progress to eclampsia, with seizures requiring emergency care.
Abnormal attachment of the placenta to the uterine wall can also cause problems. This is called placenta accreta. It belongs to the placenta accreta spectrum (PAS), in which the placenta attaches or invades abnormally deeply into the uterine wall. Important risk factors include a previous caesarean birth and placenta praevia. In accreta, it can be difficult for the placenta to detach from the uterine wall following the delivery of the fetus. This can lead to post-partum haemorrhage (bleeding after birth) as the blood supply to the placenta is not cut off.
There are a number of blood vessels which contribute to the placenta. On the maternal side the vessels are the spiral arteries and veins of the endometrium. Blood from these vessels spills out into blood lakes (pools of maternal blood, also called the intervillous space) which bathe the outside of the villi in maternal blood for exchange to occur.
On the fetal side, the paired umbilical arteries bring waste products and deoxygenated blood from the fetus towards the villi. This naming may seem slightly counter-intuitive, but they are arteries because they travel away from the fetal heart. The umbilical vein takes oxygenated blood and nutrients to the fetus. It is a vein because it travels towards the fetal heart.
The main aim of the placenta is to support the normal growth and development of the fetus.
The placenta produces protein-based hormones such as human chorionic gonadotrophin (hCG). In pregnancy this hormone is made by the syncytiotrophoblast, so it can be analysed as a positive sign of pregnancy in urinary and serum pregnancy testing. It is not completely specific to pregnancy: levels are also raised in molar pregnancy (an abnormal pregnancy in which a baby and placenta do not develop properly), and some tumours can make it, so a positive result needs clinical context. hCG is the hormone that sustains the corpus luteum (the structure left in the ovary after ovulation, which makes progesterone) in early pregnancy, until the placenta takes over.
The placenta also produces steroid hormones when it is sufficiently mature (at about 7 to 8 weeks of pregnancy, which is within the first trimester, the first 12 weeks or so). This handover from the corpus luteum to the placenta is called the luteo-placental shift. After this point, the placenta takes over the role of the corpus luteum. It makes progesterone itself, and it makes oestrogen partly from precursor steroids (starting molecules) made by the fetal adrenal gland, so the fetus and placenta work together as the feto-placental unit. These hormones keep the HPG axis (the hypothalamic-pituitary-gonadal axis, the hormonal link between the hypothalamus, pituitary gland and ovaries) in a ‘pregnant state’. This prevents ovulation and menstruation.
Placental hormones have an impact on maternal metabolism. Progesterone is thought to increase appetite, which may allow increased fat deposition in the mother. This could help support the later development of the fetus and breastfeeding following birth.
Other hormones such as human placental lactogen (hPL) create a diabetogenic state (a state that tends to raise blood glucose) by causing insulin resistance in the mother. This increases the amount of glucose available in the blood to the fetus, but can play a role in the development of gestational diabetes (diabetes that first appears in pregnancy).
Substances cross the placenta in several ways, depending on what is being moved:
- Simple diffusion across a concentration gradient, e.g. water, electrolytes, and gases.
- Facilitated diffusion (down a concentration gradient through carrier proteins), e.g. glucose.
- Active transport (using energy to move a substance against its concentration gradient), e.g. amino acids.
- Receptor-mediated transport (a receptor on the cell surface carries a molecule across the cell), e.g. IgG antibodies, which cross the placenta using a receptor called FcRn.
The limiting factor for gas exchange in the placenta is maternal blood flow. As a result, maintaining adequate blood flow is key. A marked or sustained fall in flow can leave the fetus short of oxygen, which can lead to fetal compromise (older texts call this ‘fetal distress’). Reduced blood flow can occur during labour due to the mechanical pressure on the vessels.
As the immune system of the fetus is very immature, it is at risk of infection in the neonatal period (the first 28 days after birth) after leaving the sterile uterus. However, passive immunity from antibodies transported across the placenta into the fetal circulation in utero (in the womb) helps reduce this risk. As a result, the fetus has some immunity against infections at birth. Only IgG (immunoglobulin G, a type of antibody) can be transferred across the placental membrane. This means that the baby has some temporary protection from infections that the mother has experienced because the mother has made the relevant IgG. However, this also means that the baby can show some autoimmune conditions of the mother when these are mediated by IgG. An example is neonatal lupus, which is caused by maternal anti-Ro or anti-La antibodies (autoantibodies against the body's own proteins). These are found in systemic lupus erythematosus (an autoimmune disease) and in some other conditions, and the mother may not yet have a diagnosis. The most serious feature, congenital heart block (explained below), affects about 1 to 2 in 100 pregnancies exposed to these antibodies, and about 15 to 20 in 100 pregnancies after a baby has already been affected.
Most of these effects are temporary, as the baby is not producing these immunoglobulins themselves. Once the baby's body has broken down the maternal IgG, no more is present. The rash and blood count changes of neonatal lupus usually settle by 6 to 8 months of age. Congenital heart block (a fault in the heart's electrical conduction, present from birth) is permanent.
See our immunity section for more details.
Pregnancy is associated with significant immune modulation in the mother, which helps her body tolerate the fetus. This is not the same as a general immunocompromised state (a weakened immune system). The altered immune response can make some infections more serious, such as influenza. Cytomegalovirus (CMV, a common virus) and toxoplasmosis (an infection caused by a parasite) are usually harmless or symptom-free in the mother. They matter in pregnancy because they can pass to the baby and cause serious problems.
Teratogens (substances that can cause birth defects) have their greatest effects in early pregnancy, particularly in the embryonic stage. This stage is weeks 3 to 8 after fertilisation, or about weeks 5 to 10 if counted from the last menstrual period. This is when organ systems are starting to be formed and are at most risk of damage. In the first 2 weeks after fertilisation, exposure either causes loss of the pregnancy or has no effect (the ‘all-or-none’ period).
In the fetal period (from week 9 after fertilisation until birth), most of the systems have already developed and only need to mature. They are therefore at less risk of major malformations (structural birth defects). Drugs can still harm the fetus in this period by affecting growth or organ function. For example, ACE inhibitors (a type of blood pressure drug) should be avoided in pregnancy. They can reduce fetal kidney function in the second and third trimesters (the later part of pregnancy), and a risk of birth defects in the first trimester cannot be excluded. The central nervous system also continues to be at risk of teratogenic damage throughout the pregnancy due to its long development.
Many teratogens can be transferred across the placenta during pregnancy. Teratogens can be found in many drugs, both illicit and pharmaceutical. As a result, extra attention should be given to the medications a pregnant woman is prescribed to prevent harm to the developing fetus. The British National Formulary (BNF) gives pregnancy and breastfeeding advice in its drug entries. This is not a simple safe or unsafe label, and the BNF states that absence of information does not imply safety. The UK Teratology Information Service (UKTIS) also gives advice on drugs in pregnancy.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 7483
