

Next Lesson - The Thyroid Gland
Core
Note that this article discusses the pathology of the pituitary gland. To learn about the normal functions of the pituitary gland, and the hypothalamic-pituitary axis (how the hypothalamus controls the pituitary gland), read the article on the hypothalamus, pituitary gland and growth hormone. For how the pituitary gland controls the release of cortisol from the adrenal glands, see the article on the adrenal glands and adrenal disorders.
Disorders of the pituitary gland are relatively rare and can manifest themselves as either an over- or under-secretion of pituitary hormone.
Pituitary disorders are most commonly caused by a pituitary adenoma, a benign pituitary tumour. About 3 in 10 of these tumours are non-functioning, meaning that they do not produce any hormone themselves. They can still cause an inadequate production of one or more pituitary hormones, due to the physical pressure of the growing tumour on the glandular tissue. Symptoms of a pituitary adenoma include headaches and visual problems (such as loss of part of the field of vision). These are also caused by the adenoma putting pressure on the surrounding structures. Sudden severe headache with vomiting and worsening vision can mean bleeding into the tumour (pituitary apoplexy), which is a medical emergency.
Functioning tumours, also known as hypersecreting tumours, make too much of one or more pituitary hormones, and their clinical symptoms are dependent on which pituitary hormone they are over-secreting and its systemic effects. Tumours are investigated by an MRI scan, assessment of the visual fields (a test of how much you can see without moving your eyes), and blood tests measuring hormone levels.
Hypopituitarism is most commonly caused by a pituitary adenoma putting pressure on the pituitary glandular tissue. There is typically progressive loss of anterior pituitary function, with growth hormone (GH) and the gonadotrophins (luteinising hormone (LH) and follicle stimulating hormone (FSH)) often affected early, although the pattern can vary depending on the underlying cause. Loss of GH can cause poor growth and short stature in children (an older term is pituitary dwarfism), and loss of the gonadotrophins can cause problems with the menstrual cycle in females. The posterior pituitary is normally only affected if the tumour also affects hypothalamic function, or if an inflammatory process is involved. This means that the secretion of oxytocin (which makes the uterus contract and milk be released) and anti-diuretic hormone (ADH, which helps the kidneys hold on to water) is normally unaffected.
The symptoms of GH deficiency are subtle, and consist of decreased exercise tolerance, reduced muscle mass and strength, increased body fat, and a reduced sense of well-being. Because the symptoms are subtle and GH is released in a pulsatile fashion (in bursts rather than steadily), GH deficiency can be very hard to diagnose. Whilst in adults the cause is most commonly a pituitary adenoma, in children it is idiopathic (of unknown cause, although specific genetic mutations and autoimmune inflammation may be linked). GH deficiency has little effect on growth in the womb, because other growth factors dominate growth before birth. However, babies born with several pituitary hormones missing (congenital combined pituitary hormone deficiency) can have recurrent low blood glucose (hypoglycaemia) and prolonged jaundice. From the age of one to the mid-teens, GH deficiency results in poor growth and short stature. This can be treated with GH (somatropin), which is made in a laboratory using genetically engineered cells (recombinant DNA technology).
Gonadotrophin (LH and FSH) deficiency can result in lack of libido, infertility, and oligomenorrhoea (infrequent periods) or amenorrhoea (no periods) in women of reproductive age. In men, it can also decrease libido and cause erectile dysfunction (difficulty getting or keeping an erection).
Thyroid stimulating hormone deficiency can be caused by a pituitary adenoma and can lead to hypothyroidism (an underactive thyroid gland) with symptoms that include feeling cold, weight gain and bradycardia (a slow heart rate). This will be discussed further in the article on the thyroid gland and thyroid disorders.
Adrenocorticotropic hormone (ACTH) deficiency can be caused by a pituitary adenoma, and symptoms include tiredness, dizziness and low blood pressure. This is discussed further in the article on the adrenal gland and adrenal disorders.
ADH deficiency may result from a hypothalamic tumour, or a pituitary tumour that has extended up into the hypothalamus. Other causes include cranial radiotherapy, pituitary surgery, head injury, autoimmune infiltration (immune cells invading the pituitary gland) and infections such as meningitis. It results in excess secretion of dilute urine, resulting in dehydration and an increased sensation of thirst. The condition represents the cranial form of diabetes insipidus, now also called arginine vasopressin deficiency (AVP-D), as arginine vasopressin is another name for ADH.
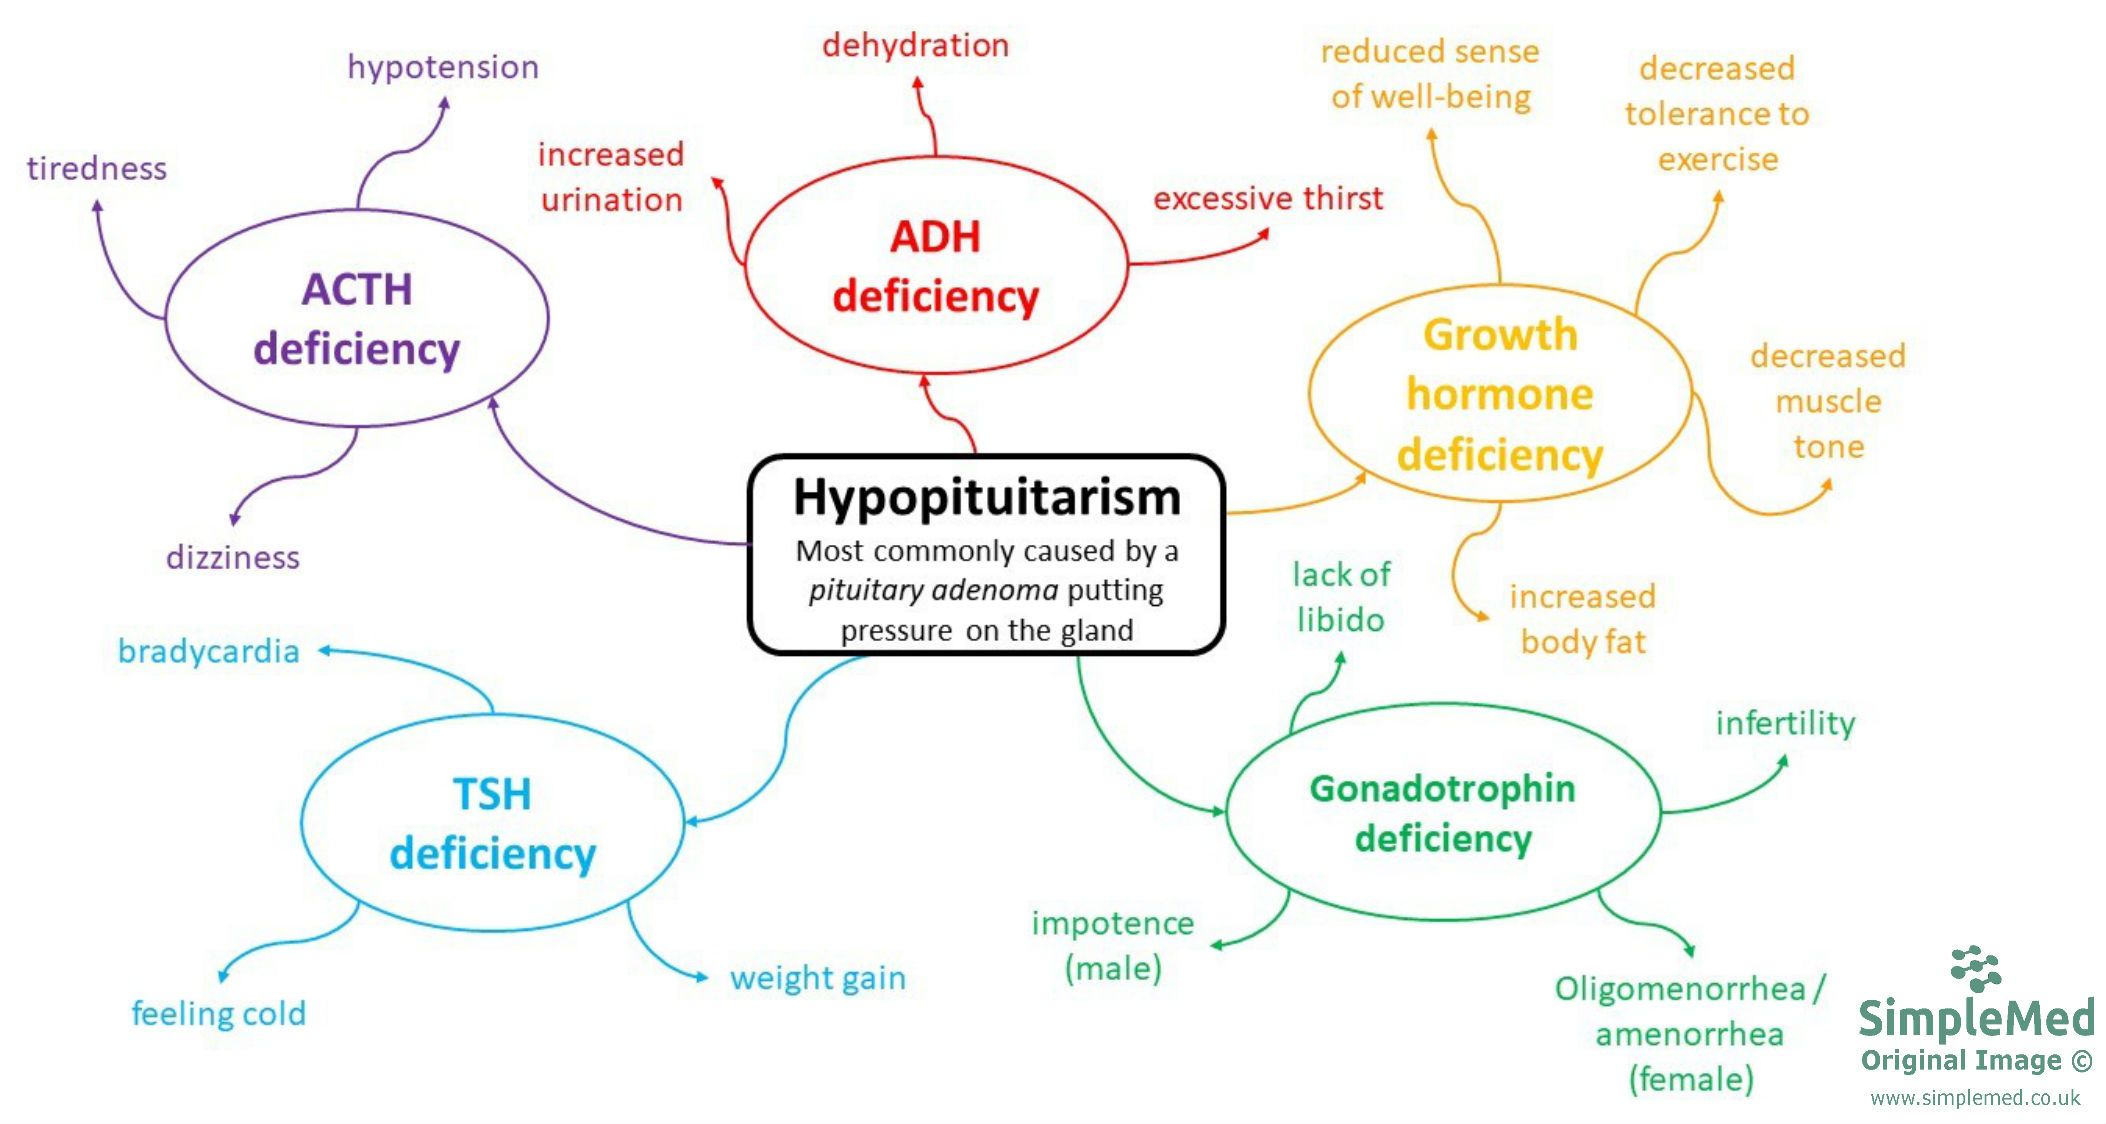
Diagram: A mind-map outlining the most common symptoms of the different forms of hypopituitarism
SimpleMed original by Dr. Jenny Hubball
Hyperpituitarism is usually caused by a hypersecreting pituitary adenoma. The three hormones most commonly affected are prolactin, GH and ACTH.
Hyperprolactinaemia is a condition involving the presence of excess amounts of prolactin in the body. It is the most common form of hyperpituitarism, and the most common pituitary cause is a prolactinoma (a pituitary adenoma that secretes prolactin). Other causes include pregnancy, suckling during breastfeeding, stress, exercise, an underactive thyroid gland (hypothyroidism), pressure on the pituitary stalk (the link between the hypothalamus and the pituitary) from other tumours, and medicines that block dopamine, such as antipsychotic drugs. Symptoms include galactorrhoea (milk production when not breastfeeding), gynaecomastia (breast enlargement in men), hypogonadism (low sex hormone production), amenorrhoea and erectile dysfunction. The increased concentration of plasma prolactin exerts negative feedback at the hypothalamus, leading to increased dopamine release (dopamine is also known as prolactin inhibiting hormone, because it reduces prolactin secretion). Raised prolactin also suppresses the release of gonadotrophin-releasing hormone (GnRH), the hypothalamic hormone that drives LH and FSH release, resulting in reduced sex hormone production. The first line of treatment is usually a dopamine receptor agonist (a drug that acts like dopamine, for example cabergoline). This is enough for most people. Trans-sphenoidal surgery (removal of the tumour through the nose) or radiotherapy may be needed if the drug does not work well enough or causes side effects.
GH excess is usually caused by growth-hormone secreting pituitary adenomas. Larger tumours are associated with local mass effects (symptoms from the tumour pressing on nearby structures) such as headaches, visual field defects (loss of part of the field of vision) and other cranial nerve palsies (weakness of the nerves that leave the brain). The systemic effects are through both the direct actions of GH, and through the stimulation of IGF-1 production (insulin-like growth factor 1, made mainly by the liver). The effects often take several years to develop, so it can take a while for a diagnosis to be made. Changes to the patient include broad nose, coarse facial features, thick lips, a prominent supraorbital ridge (the bony brow above the eyes), enlarged hands and feet, greasy skin, excessive sweating and deepening of the voice. In childhood, excess GH can result in gigantism (abnormally tall stature). This is because the epiphyseal growth plates (the areas near the ends of long bones where growth happens) have not yet fused, so the excess growth hormone increases growth of the body. In adults it results in acromegaly (enlargement of the hands, feet and face), as the growth plates have fused, so height is not affected.
GH antagonises insulin, meaning metabolic conditions such as diabetes mellitus can occur, and the increased IGF-1 levels have been associated with some forms of cancer. Three types of treatment are available for patients with acromegaly: surgery to remove the adenoma, which is usually the first choice, drug therapy and radiation therapy. Drug therapy is often needed as well as surgery. Examples are somatostatin analogues (drugs that mimic the hormone that switches off GH release, so they lower GH secretion) and GH receptor antagonists (drugs that block the action of GH).
ACTH excess is one of the causes of Cushing’s syndrome (a condition caused by too much cortisol). Cushing’s syndrome is covered in the article on the adrenal glands and adrenal disorders.
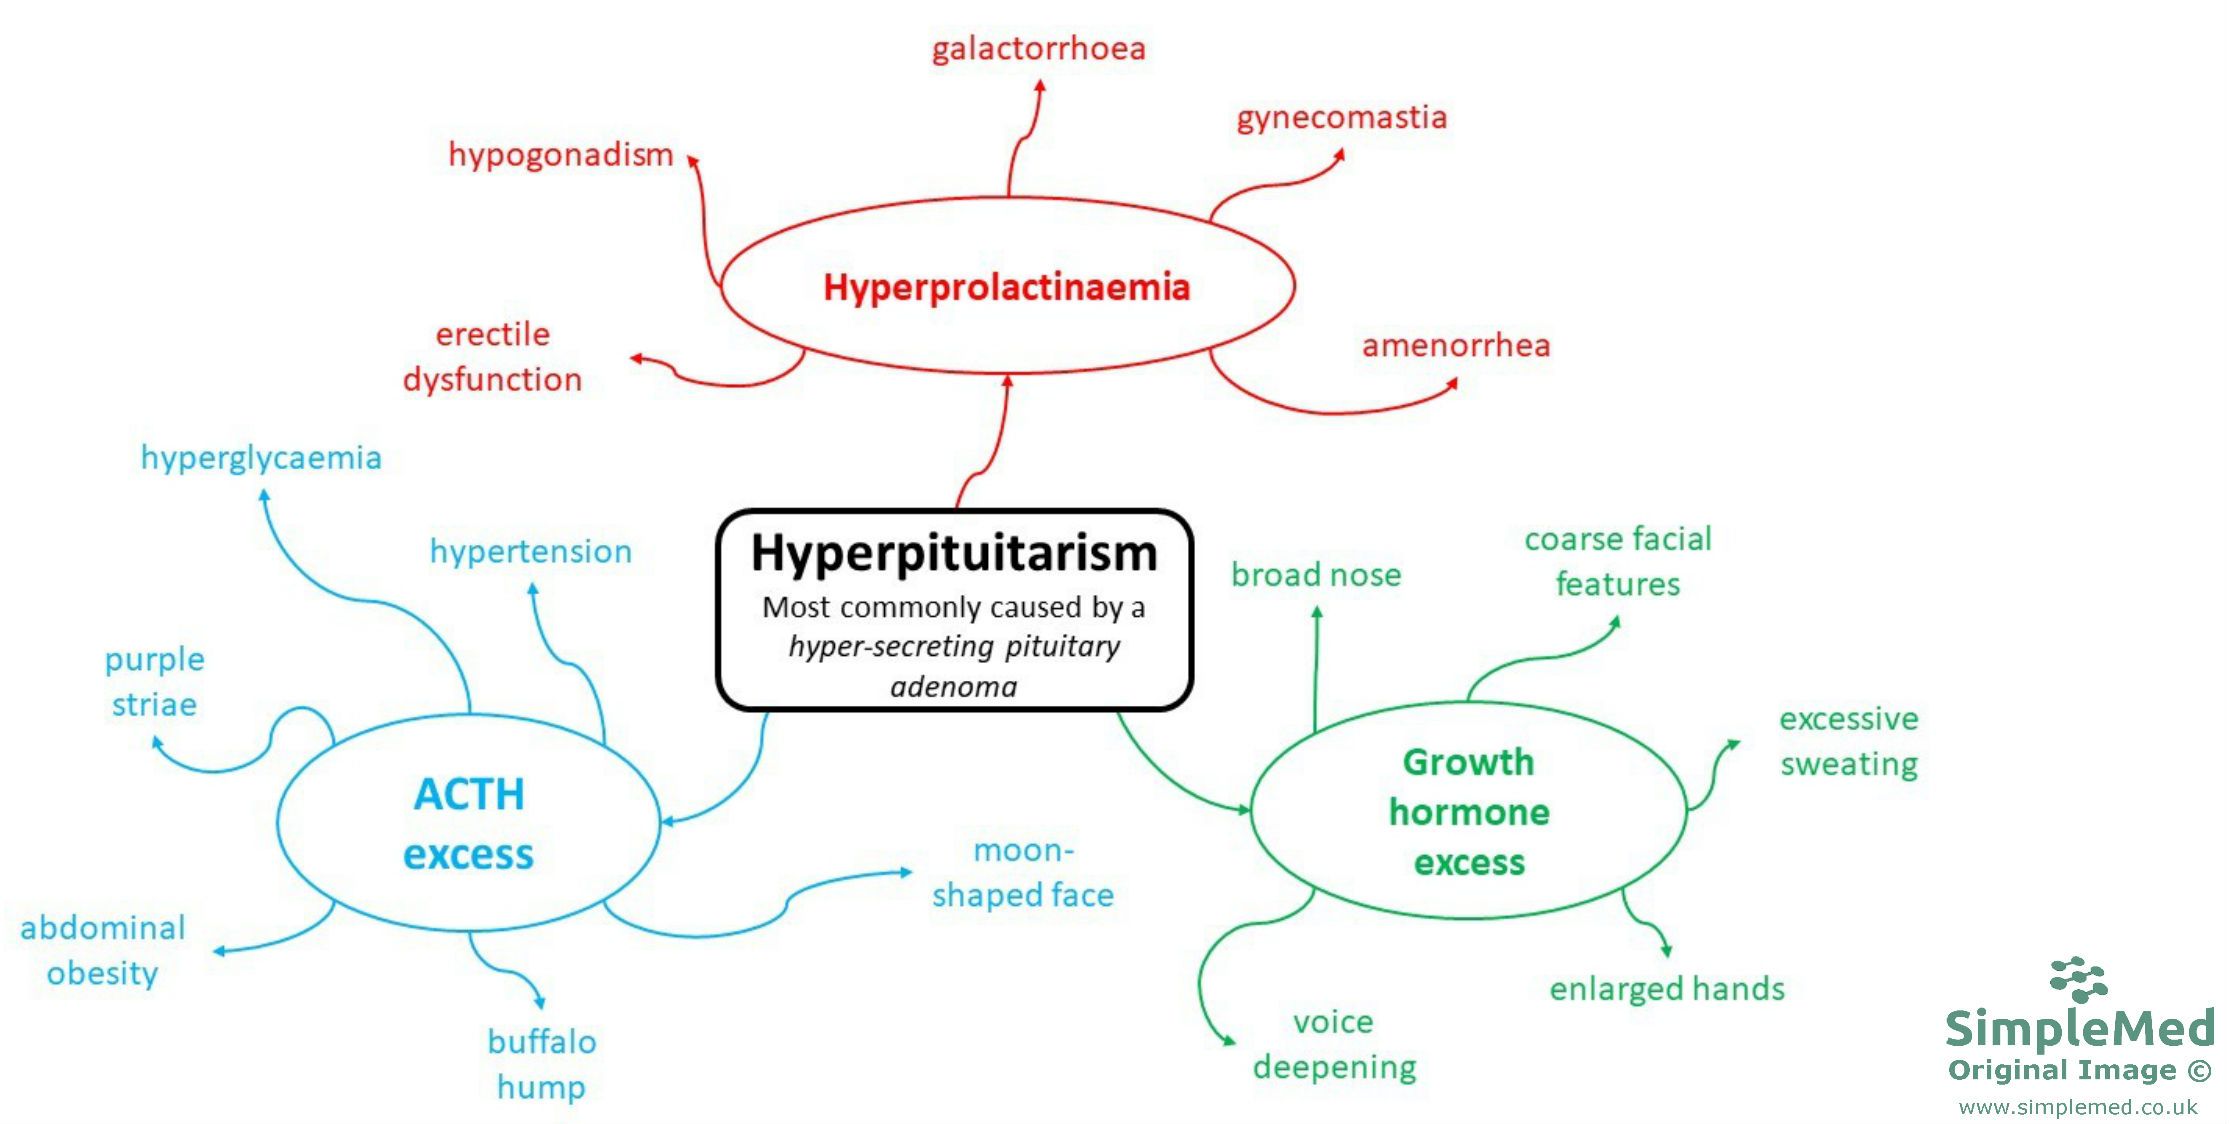
Diagram: A mind-map outlining the most common symptoms of the different forms of hyperpituitarism
SimpleMed original by Dr. Jenny Hubball
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
Edited by: Dr. Maddie Swannack
- 10504
