

Next Lesson - Anatomy of the Woman
Core

Diagram - Anatomy of the male reproductive system
Creative commons source by alt.sex FAQ, © Elf Sternberg [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The function of the penis includes:
- Expulsion of urine through the urethra
- Deposition of sperm
The penis is made up of two key erectile tissues.

Diagram - Cross section of the penis showing the erectile tissue
Creative commons source by Mcstrother [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The corpus cavernosum is the main erectile tissue of the penis. There are two columns of this tissue type in the penis, and they are anchored to the ischiopubic rami (the bony arms of the pubis and ischium in the pelvis). The corpus spongiosum is an expandable tissue which surrounds the urethra; it is of lesser importance in producing an erection.
An erection is stimulated by the parasympathetic nervous system. The parasympathetic system causes vasodilation of arterioles and relaxation of the sinusoids (the blood-filled spaces) of the corpora cavernosa.
Ejaculation has two phases. In emission, the sympathetic nervous system causes contraction of glands and ducts of the male reproductive system, which moves sperm and fluid into the urethra. It also causes the closing of the internal urethral sphincter to prevent retrograde ejaculation (semen flowing backwards into the bladder). In expulsion, striated muscles around the base of the penis (such as the bulbospongiosus) contract rhythmically and force the semen out through the urethra. These muscles are supplied by the somatic pudendal nerve.
The roles of the two systems can be remembered by the rather crude ‘Point and Shoot’. Erection is achieved by the parasympathetic system (P for point). Ejaculation is started by the sympathetic system (S for shoot), although the somatic nerves are also needed for the final expulsion.
Erectile dysfunction is the persistent inability to attain and maintain an erection that is firm enough for satisfactory sexual activity. Its causes can be classified as organic (a physical cause), psychosexual (a psychological cause), or mixed. The most common organic cause is vascular: reduced blood flow caused by cardiovascular disease, hypertension, diabetes mellitus, or smoking. Erectile dysfunction can also be a side effect of some medications, for example beta-blockers, thiazide diuretics and some antidepressants.
The tunica albuginea (a tough fibrous sheath) surrounds each of the corpora cavernosa and gives the penis its cylindrical shape on erection. A tear (rupture) of this sheath, usually caused by blunt trauma to an erect penis, is known as a penile fracture. It is not a broken bone. It leads to deformation of the penis and is a urological surgical emergency.
The clitoris is the embryological equivalent to the penis in females.
Blood supply to the penis is from the internal pudendal artery which is a branch of the internal iliac artery.
In the embryo, the testes begin their development at the posterior abdominal wall and descend to their position in the scrotum (the skin sac that holds the testes). This allows spermatogenesis (sperm production) to occur at the optimum temperature, which is lower than core body temperature.
The descent of the testes creates the inguinal canal (the passage through the lower abdominal wall) as it brings down the layers of the abdominal wall. The testes also bring down the peritoneum (the membrane that lines the abdominal cavity), which surrounds the testes forming the tunica vaginalis (a double-layered sac around each testis). The tunica vaginalis has a parietal and visceral layer as it is formed from the peritoneum, and it allows for friction-free movement of the testes. The space between the two layers can fill with excess fluid, forming a hydrocele (a collection of fluid around the testis).
The tunica albuginea is a fibrous capsule surrounding the testes which divides the parenchyma (the working tissue of the testis) into lobules (small compartments).
The seminiferous tubules (the coiled tubes in which sperm are made) are lined with Sertoli cells, which help the developing sperm to mature. The tubules are the site of spermatogenesis. The sperm travel to the rete testis (a network of small channels at the back of the testis) and then to the epididymis (the coiled tube on the back of the testis), where the maturation of sperm occurs. The epididymis then goes on to form the vas deferens (or ductus deferens), a muscular tube that carries sperm towards the urethra and travels through the spermatic cord.
The Leydig cells lie in the tissue between the seminiferous tubules, outside the tubules themselves, and they produce testosterone.

Diagram - The anatomy of the testis
Public Domain Source by Henry Gray (1918) Anatomy of the Human Body [Public domain]
The testes receive their blood supply from the testicular arteries, which arise directly from the abdominal aorta. These arteries are long due to the descent of the testes.
The venous drainage is by the pampiniform plexus (a network of veins around the testicular artery), which then forms the testicular vein. On the right, the blood drains directly from the pampiniform plexus into the inferior vena cava, whereas the left drains into the left renal vein. These veins also surround the testicular arteries. Heat passes from the arterial blood to the cooler venous blood, so the blood entering the testes is cooled. This helps to keep the testes at the cooler temperature required for spermatogenesis.

Diagram - The arterial supply to the testes
SimpleMed original by Dr. Emily Smith

Diagram - The venous drainage of the testes. Note that the left pampiniform plexus drains into the left renal vein, and the right pampiniform plexus drains straight into the inferior vena cava
SimpleMed original by Dr. Emily Smith
A varicocele is a swelling of the scrotum made up of dilated (widened) veins of the pampiniform plexus. It is due to increased hydrostatic pressure (the pressure of the blood inside the veins). The usual cause is incompetent or absent valves in the testicular veins (valves that do not close properly, or are missing). Rarely, a varicocele is secondary to obstruction of the veins, for example by a tumour or other renal pathology (kidney disease) compressing them. Varicoceles most commonly occur on the left side (about 90%) because of the route taken by the veins. The left testicular vein drains into the left renal vein at a right angle, so the pressure in the column of blood can build up. The right testicular vein drains at an oblique angle into the inferior vena cava, which gives it some protection. Varicoceles are typically painless. The diagnosis is clinical (made from the history and examination): the dilated veins feel like a ‘bag of worms’ above the testis and are more obvious when the man stands. An ultrasound scan can also be carried out to help with diagnosis. Small varicoceles (those found only on ultrasound, or felt only when the man strains) need no treatment. A man with a larger varicocele that is painful, or who has abnormal semen results, is referred to a urologist for possible surgery. Boys are also referred if the testis on the affected side is smaller. A varicocele that appears suddenly and is painful, or that does not drain when the man lies down, needs urgent referral.
The spermatic cord provides the neurovascular supply (the nerve and blood supply) to the testes. It begins its course at the deep inguinal ring (an opening in the abdominal wall at the start of the inguinal canal), then passes through the inguinal canal and enters the scrotum through the superficial inguinal ring (the opening at the far end of the canal).
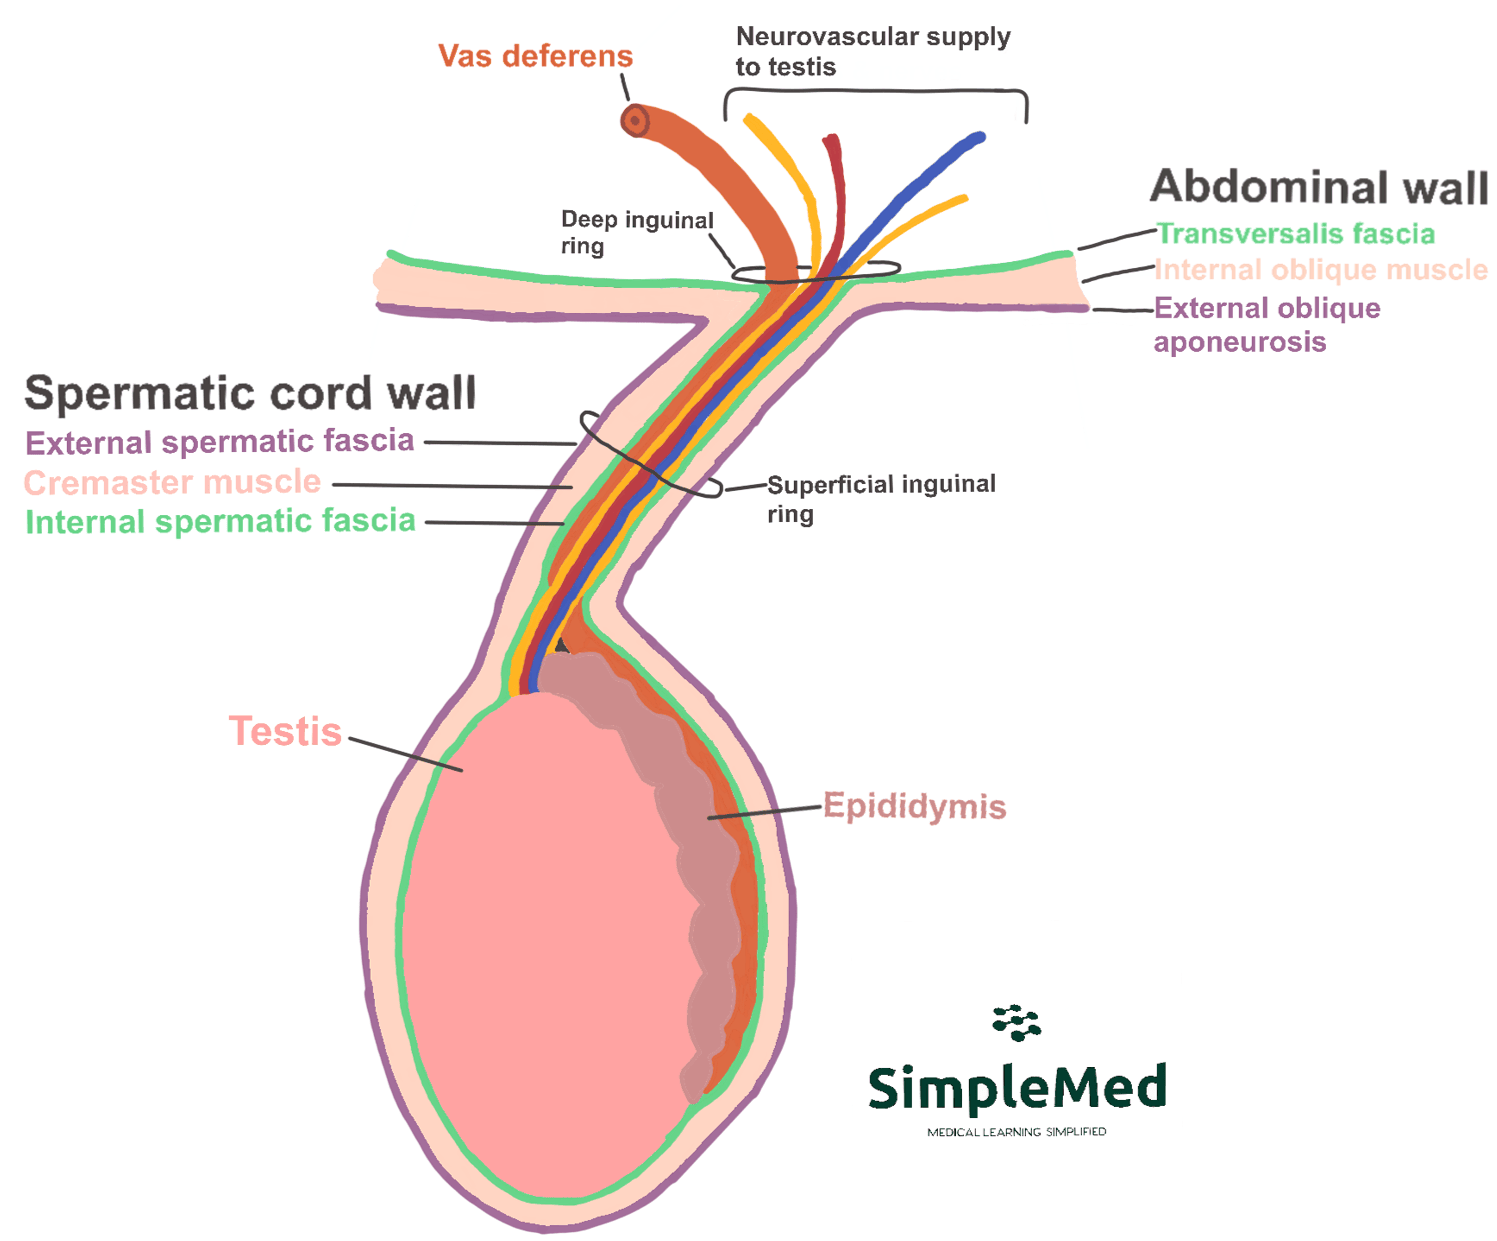
Diagram - The structure of the spermatic cord
SimpleMed original by Dr. Emily Smith
The spermatic cord carries structures that matter clinically, because twisting of the cord (testicular torsion) cuts off the blood supply to the testis. Its contents include:
- 3 Fascial Layers (sheets of connective tissue)
- External spermatic fascia
- Cremaster muscle (the muscle that raises the testis) and fascia
- Internal spermatic fascia
- 3 Arteries
- Testicular artery
- Artery to vas deferens
- Cremasteric artery
- 3 Veins
- Pampiniform plexus
- Vein to vas deferens
- Cremasteric vein
- Nerves
- Genital branch of the genitofemoral nerve (cremasteric nerve), which supplies the cremaster muscle
- Sympathetic fibres to the vas deferens
- Vas Deferens
- Lymphatics (lymph vessels): these drain the testes to the para-aortic lymph nodes, which lie beside the aorta in the lumbar region.
- Processus Vaginalis: the pouch of peritoneum that guided the descent of the testes in the embryo. It normally fuses shut after the testes have descended. If it stays open, peritoneal fluid can pass into the scrotum (a communicating hydrocele) or abdominal contents can pass down it (an indirect inguinal hernia).
The spermatic cord can become twisted on itself resulting in testicular torsion. This is a surgical emergency. The testis needs immediate surgical exploration, ideally within 6 hours of the start of symptoms, so a suspected case is sent straight to hospital without waiting for a scan. There is a risk of necrosis (death) of the testis if the blood supply is not restored quickly. Torsion is most common in males aged 12 to 18 years. A risk factor for this is a ‘bell clapper deformity’, where the testis is abnormally attached to the tunica vaginalis, which allows it to swing and move within the sac. Patients with torsion present with sudden onset, severe pain in one testis. The pain may spread to the groin or lower abdomen. They often also have nausea and vomiting. Pain that changes, or eases for a short time, does not reliably mean that the testis has recovered, and torsion remains a surgical emergency due to the risk of testicular ischaemia and necrosis.
These glands produce the majority of the ejaculate (the semen), approximately 65 to 70%. The fluid produced is alkaline to neutralise the acidic environment of the vagina, and provides nutrition to sperm.
This gland produces about 25% of the ejaculate. This secretion contains proteolytic enzymes (enzymes that break down proteins) and is mildly acidic.
The prostate wraps around the urethra, so enlargement such as in benign prostatic hyperplasia (a non-cancerous overgrowth of prostate tissue) can lead to urinary symptoms. Voiding symptoms (problems passing urine) include hesitancy (difficulty starting), a slow or weak stream, straining and dribbling at the end of urination. Storage symptoms include frequency (passing urine often), urgency (needing to go suddenly), nocturia (passing urine at night) and incontinence (leaking urine). The prostate also sits just anterior to the rectum. This means that the doctor can feel the gland through the rectal wall in a digital rectal examination (DRE, also called a PR or per rectum exam). A hard gland with nodules can suggest prostate cancer, and a smooth, firm, enlarged gland suggests benign enlargement. However, the examination alone is poor at detecting prostate cancer, so it is combined with a PSA (prostate-specific antigen) blood test.
These glands (also called Cowper’s glands) only produce a small amount of the ejaculate. During sexual arousal, their alkaline mucus secretion lubricates the urethra, which reduces friction, and it helps to neutralise any acidic urine left in the urethra.
Edited by: Dr. Ben Applebyand Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 10583



