

Next Lesson - Haematology in Systemic Disease
Core
To better understand this topic, have a read of our article on Haematopoiesis and the Spleen.
As previously mentioned, haematopoiesis is the formation of the cellular components of blood. A healthy adult makes about 200,000,000,000 red cells and about 100,000,000,000 platelets per day. The usual estimate for neutrophils (a type of white cell) alone is about 100,000,000,000 per day, although this figure is debated.
A deviation from the norm (i.e. too many or too few cells are produced) can produce life-threatening complications. This deviation can be caused by infections, certain medications or malignancy.
The overproduction of blood cells has two main causes: a disease of the bone marrow itself or abnormalities in hormonal signalling.
Diseases of the bone marrow that cause overproduction are called myeloproliferative neoplasms (cancers of the bone marrow that make too many blood cells). These arise from a genetic mutation in a haematopoietic stem cell (a bone marrow cell that can develop into any type of blood cell). The cells that descend from it multiply and increase levels of various blood cells, including platelets, erythrocytes (red blood cells) and white blood cells, in the body.
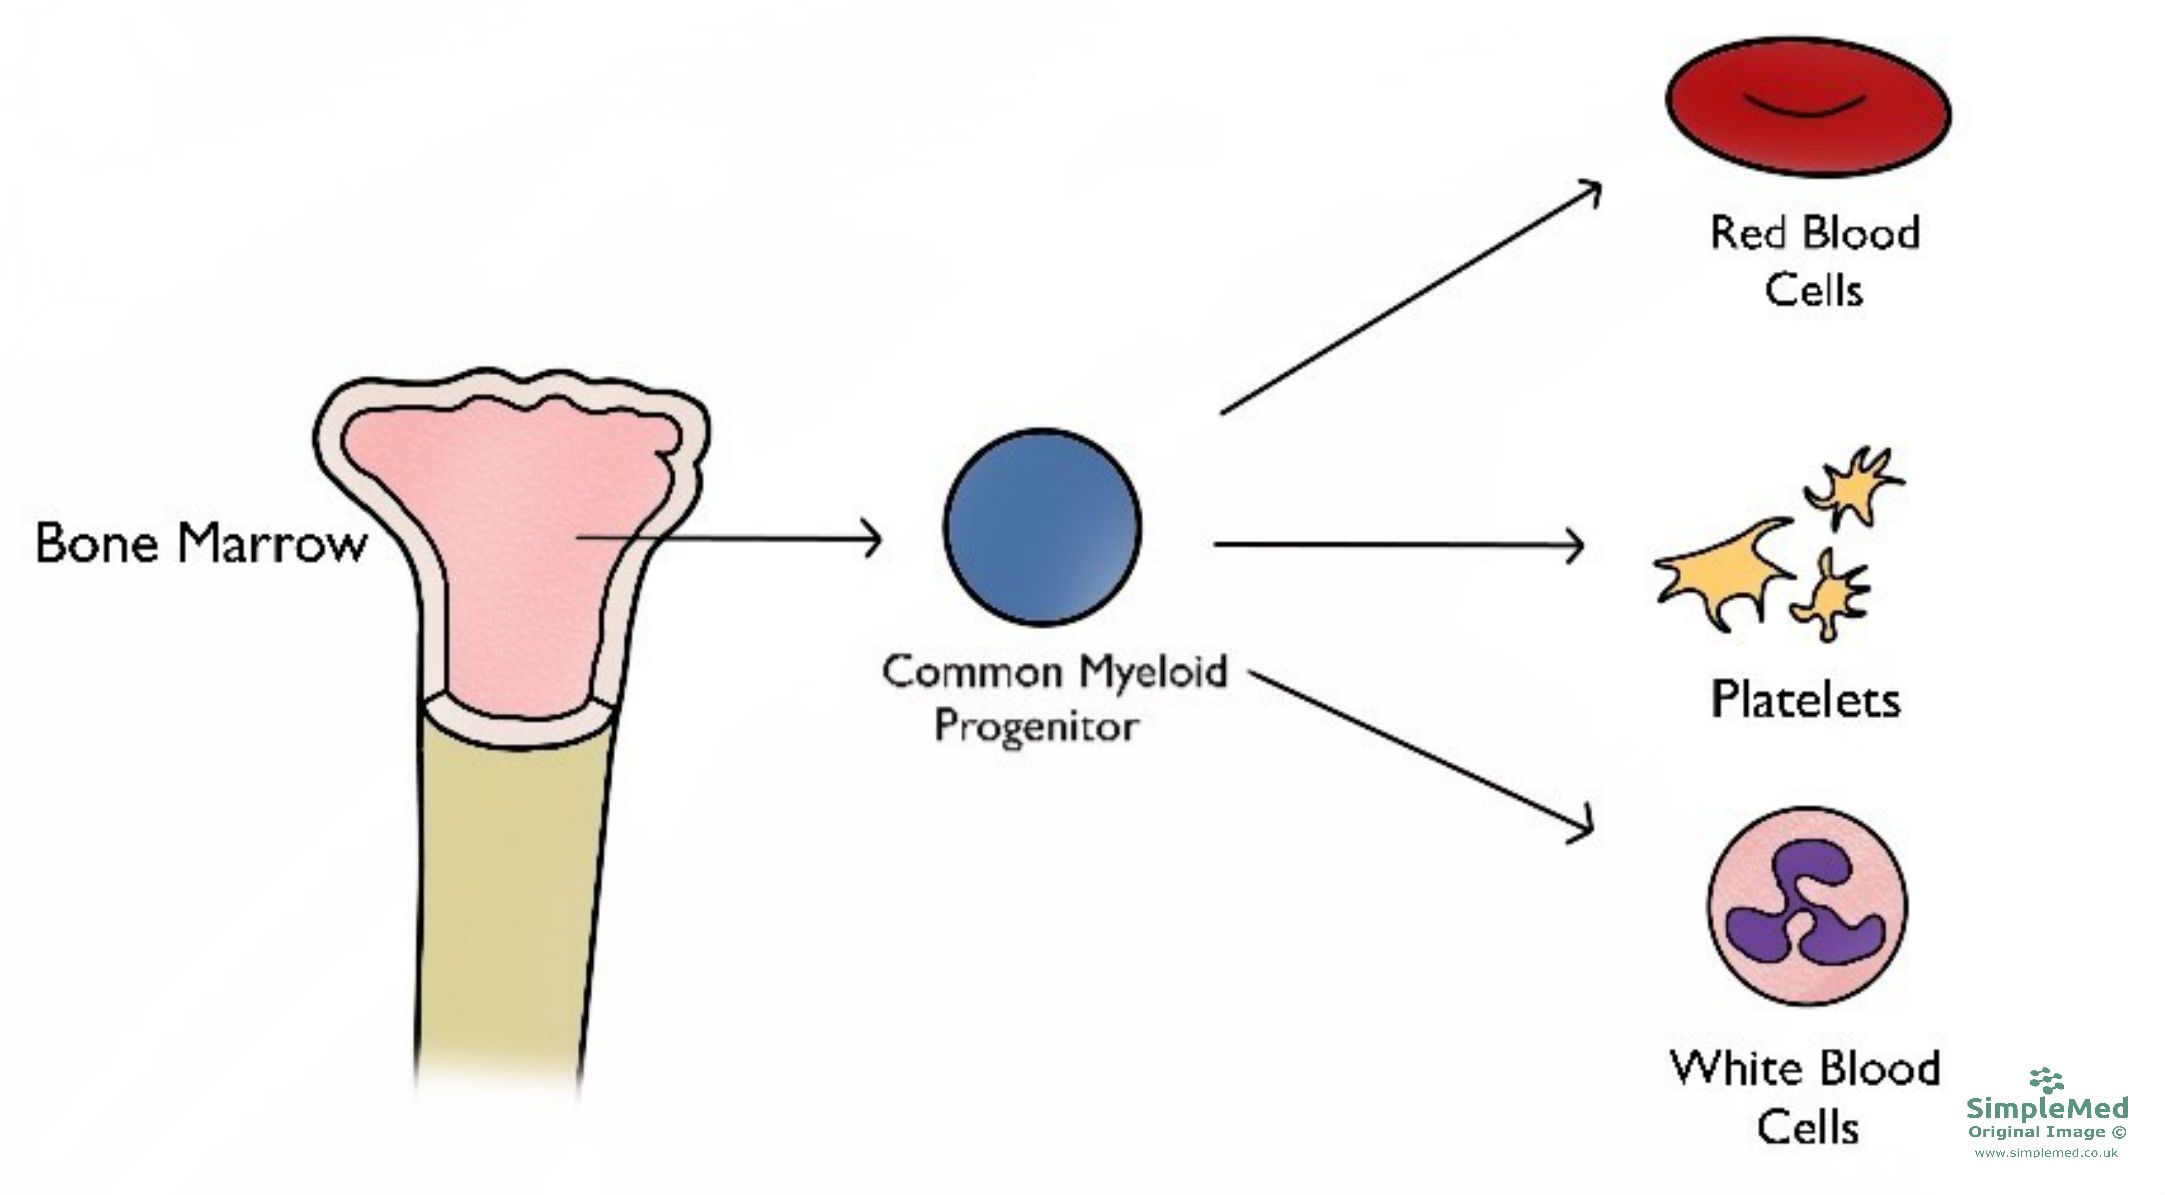 Figure 1 - The types of cells that arise from the bone marrow, specifically the myeloid lineage (the family of cells that includes red cells, platelets and most white cells)
SimpleMed original by Dr. Keertana Anne
Polycythaemia is a disease state where the haematocrit is raised (greater than 52% in males and over 48% in females).
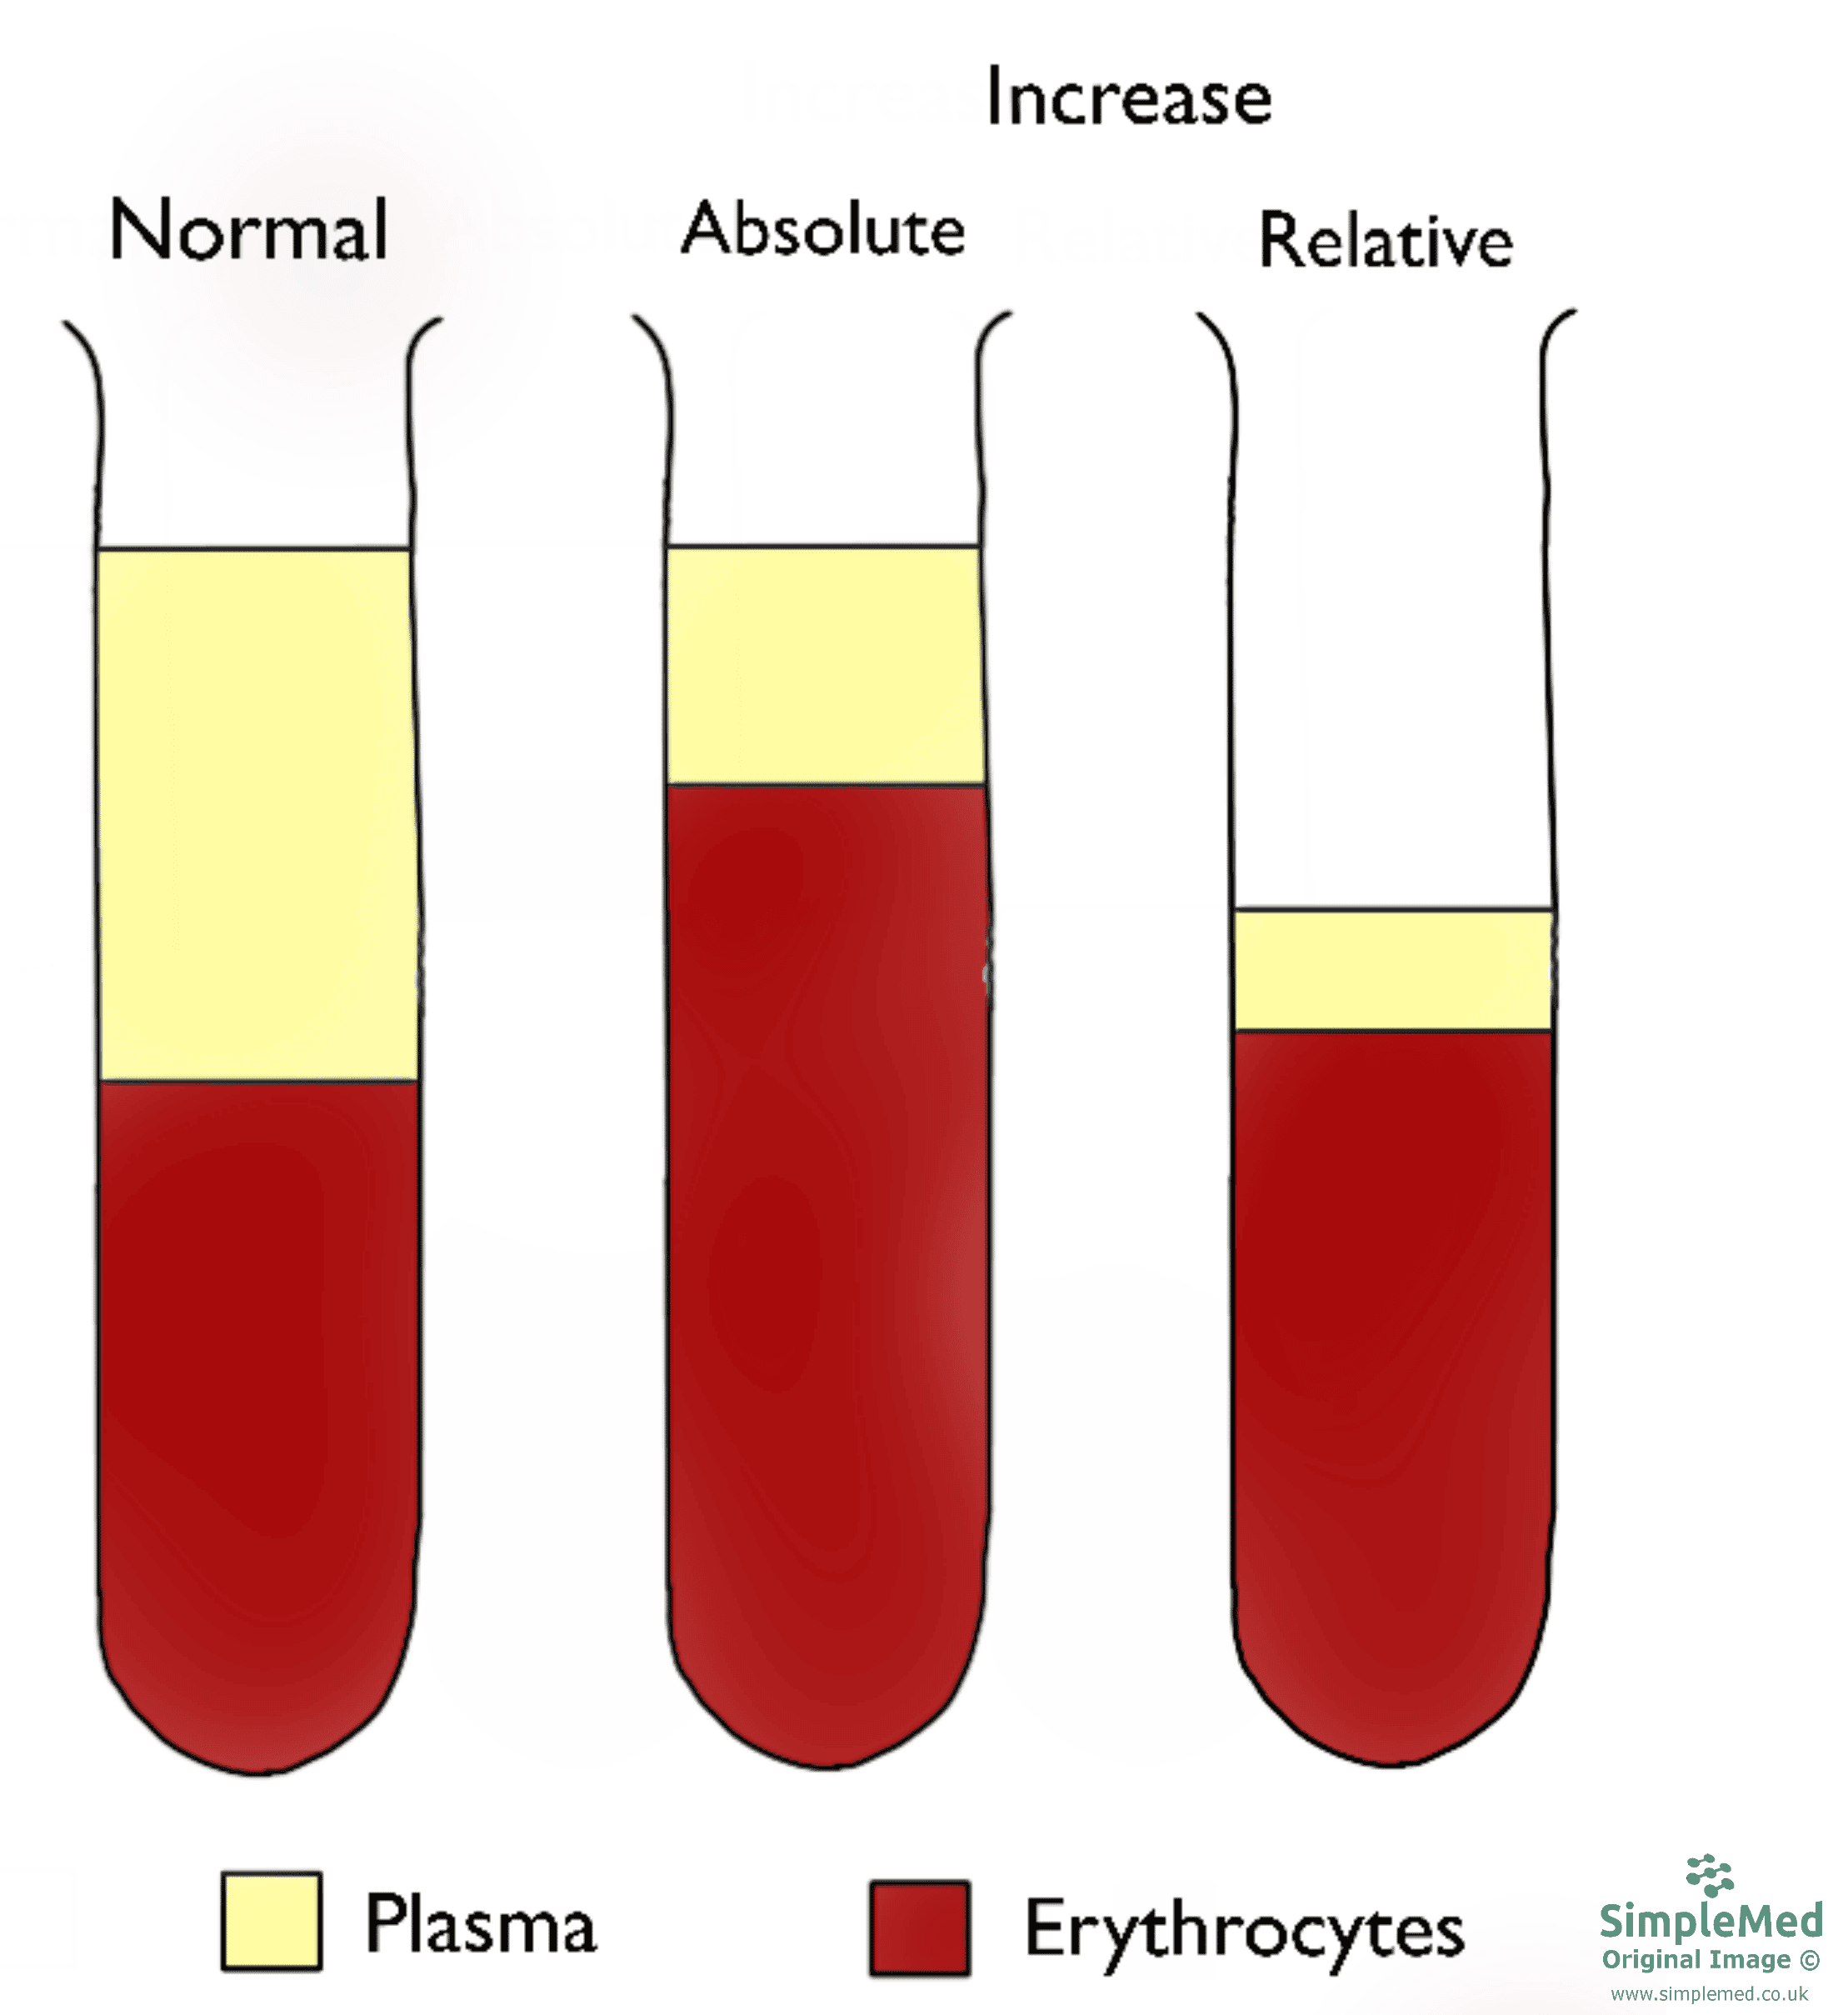
Figure 2 - The difference between an absolute and a relative increase in the haematocrit level
SimpleMed original by Dr. Keertana Anne
An absolute increase in haematocrit is due to increased erythrocytes, while a relative increase is due to a decrease in plasma volume (note how volume of erythrocytes remains the same).
An increase in erythrocytes (absolute increase in haematocrit) can happen for a number of reasons:
- Primary causes - When there is an abnormality in the bone marrow, known as polycythaemia vera.
- Secondary causes - There are increased levels of erythropoietin (a hormone, made mainly by the kidneys, that stimulates red cell production):
- Physiological, as a response to low oxygen levels in the tissues (hypoxia), e.g. high altitude or chronic lung conditions.
- Pathological due to abnormal production from the kidneys or from a secreting tumour (e.g. renal cell carcinoma or hepatocellular carcinoma).
- Self-administered human erythropoietin (EPO) is used by some members of the sporting community to increase performance. EPO is banned by the World Anti-Doping Agency (WADA).
A relative increase is a common cause of a raised haematocrit. It happens when the plasma volume is low, for example in dehydration, which can be resolved by replenishing fluids. Other causes include diuretics, a high body mass index, heavy smoking and heavy alcohol use.
Polycythaemia vera is a specific type of polycythaemia. It is a myeloproliferative neoplasm (a bone marrow disorder). It is usually caused by a mutation in the gene coding for the enzyme Janus Kinase 2 (JAK2). The mutation causes abnormal signalling within bone marrow cells. They keep making blood cells, even without the normal signals that control cell production. Polycythaemia vera mainly increases erythrocyte production, but can also increase levels of white blood cells and platelets.
The signs and symptoms of polycythaemia are generally non-specific and may include dizziness, headaches and tinnitus (ringing in the ears). Pruritus (itching), especially after contact with warm water, is a common feature of polycythaemia vera. Erythromelalgia (a burning sensation in the fingers and toes with associated erythema, meaning redness of the skin) is also characteristic. Erythromelalgia is less common than itching: one review of polycythaemia vera reported it in about 5% of patients and itching in about 33%. Many cases are asymptomatic.
Polycythaemia vera is treated by therapeutic phlebotomy (bleeding the patient, also called venesection), which keeps the haematocrit below 0.45. Low-dose aspirin (75 mg daily) is also given, unless it is contraindicated. Drugs that reduce blood cell production (cytoreductive drugs) are added for people at high risk of thrombosis (over 60 years old, or with any history of thrombosis). They can also be used if phlebotomy is not tolerated. The usual first-line cytoreductive drug is hydroxycarbamide. Other causes of a raised haematocrit are managed by treating the underlying cause.
When presented with a high haematocrit it is helpful to consider the more common causes first. First ask whether the change is relative. If not, ask whether it has a secondary cause. A primary cause (the least common) can then be considered.
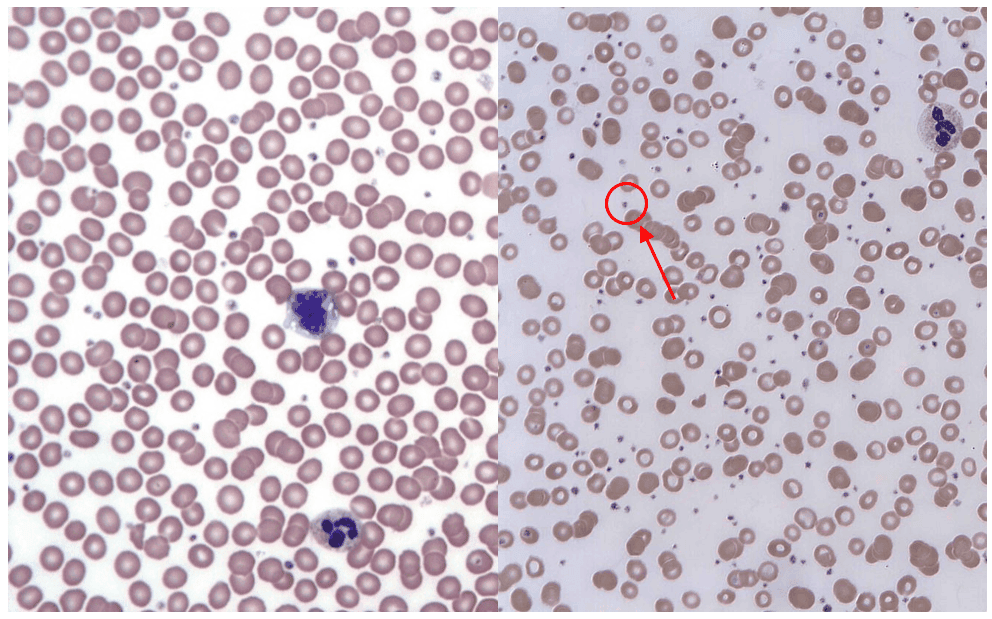
Figure 3 - A normal blood film vs the blood film of a patient with thrombocytosis. The small dots (circled) are platelets
Creative commons source by Keith Chambers [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)] - Left Image
Creative commons source by Erhabor Osaro (Associate Professor), edited by Dr. Keertana Anne [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)] - Right Image
Thrombocytosis is an increase in the platelet count of the blood above the normal range (more than 450 × 10⁹/L). A raised platelet count is commonly seen in hospitalised patients, due to a higher risk of infection and inflammation. This is a reactive rise, not a physiological one. Thrombocytosis has two main causes: reactive (secondary) and primary.
Reactive thrombocytosis is the more common pathological cause, and develops secondary to another cause. These causes include iron deficiency, chronic inflammatory disorders, acute infections and cancers. The platelet count also rises when the spleen has been removed (splenectomy) or is not working properly. Platelets usually work normally in reactive thrombocytosis. The risk of thrombosis is generally much lower than in primary causes, but it depends on the underlying condition.
Primary thrombocytosis (also known as Essential Thrombocythaemia), on the other hand, is a myeloproliferative neoplasm. This is a rare blood cancer that starts in the bone marrow. It causes an overproduction of megakaryocytes (the bone marrow cells that make platelets). A JAK2 mutation is seen in about 50 to 60% of these patients. Others have a mutation in the CALR gene (about 15 to 24% of patients) or the MPL gene (about 4%). CALR codes for the protein calreticulin. MPL codes for the thrombopoietin receptor (the receptor for thrombopoietin, a hormone that stimulates platelet production). A minority of patients have none of these mutations. The symptoms relate to the increase in platelets. Many patients (about 40 to 50%) have no symptoms at diagnosis. When symptoms occur, they include erythromelalgia (burning pain and redness in the hands and feet), migraine, paraesthesia (tingling or numbness in the extremities), and complications from thrombosis and bleeding.
Leukaemia is a group of blood cancers that start in the bone marrow. They produce increased numbers of abnormal white blood cells. These cells are unable to perform their normal function, often because they are immature.
Leukaemia is categorised in two ways: whether it is acute or chronic; and whether it is myeloid or lymphoid.
Acute leukaemia results from a rapid increase in the number of immature blood cells, and these overwhelm the ability of the bone marrow to produce mature blood cells. This rapidly produces the symptoms of leukaemia. Chronic leukaemias on the other hand are slower to produce the symptoms (may take months to years), as the blood cells that are produced are relatively mature, but still abnormal.
Myeloid leukaemias originate from the myeloid lineage, and so affect erythrocytes, granulocytes (neutrophils, eosinophils and basophils) and platelets. Lymphoid (lymphocytic) leukaemias originate from the lymphoid lineage, and so affect lymphocytes and natural killer cells (lymphocytes that kill virus-infected and cancer cells).
It is important to remember that lymphoid leukaemias are usually distinguished from lymphomas (which are classified into Hodgkin and non-Hodgkin lymphoma) by where the cancer cells mainly sit. In leukaemia the cancer cells mainly sit in the bone marrow and blood. In lymphoma they mainly sit in lymph nodes and other tissues. The line between the two is not sharp. For example, chronic lymphocytic leukaemia and small lymphocytic lymphoma are classified as the same disease.
Frequent infections are a key complication of leukaemias. This is because the abnormal white blood cells cannot remove pathogens properly, and the bone marrow makes fewer healthy white cells. Previously common infections can then become life-threatening. Other signs and symptoms come from the bone marrow being replaced by leukaemia cells. Too few normal platelets are made, which leads to increased bleeding and bruising. Too few red blood cells are made, so the blood cannot carry enough oxygen to the tissues, causing anaemia (see our article on anaemia).
| Acute | Chronic |
Myeloid | Acute Myeloid Leukaemia | Chronic Myeloid Leukaemia |
Lymphoid | Acute Lymphoblastic Leukaemia | Chronic Lymphocytic Leukaemia |
Insufficient numbers of blood cells can also be produced when the bone marrow is damaged, and these changes can be either benign or malignant. Low counts can also be due to cells being used up or destroyed faster than they are made (see thrombocytopenia below).
Thrombocytopenia is characterised by an abnormally low level of platelets, the causes of which can either be inherited or acquired. The lack of platelets means that the body is no longer able to form blood clots easily which increases the risk of bleeding.
There are many different types of inherited thrombocytopenias, and all of them are very rare. Some examples include MYH9-related disease (which includes the May-Hegglin anomaly, and the Epstein and Fechtner syndromes that were once described as variants of Alport syndrome), Wiskott-Aldrich syndrome and Fanconi anaemia (an inherited bone marrow failure that affects all three blood cell types). These are easily misdiagnosed due to their rarity.
Acquired thrombocytopenias are a lot more common. Patients with these disorders experience symptoms such as bleeding gums, nosebleeds and petechiae (tiny pinpoint spots on the skin, under 2 mm across, that do not fade when pressed) on their feet, shins and forearms. Women may experience heavier and longer menstrual periods. The following three things can cause acquired thrombocytopenia:
- Decreased platelet production: lack of vitamin B12 or folate, also called vitamin B9 (unable to form megakaryocytes); liver failure (decreased production of thrombopoietin).
- Increased platelet consumption: massive haemorrhage; disseminated intravascular coagulation (condition where blood clots form throughout the body, blocking small vessels and using up platelets); thrombotic thrombocytopenic purpura.
- Increased platelet destruction: hypersplenism (there is a greater destruction of platelets and increased splenic pooling of platelets, thereby removing them from circulation); drug-induced; immune thrombocytopenia (ITP).
Thrombotic Thrombocytopenic Purpura (TTP)
TTP is a blood disorder characterised by widespread microthrombi (tiny clots) forming in small blood vessels, leading to a reduced platelet count. Although it shares some features with disseminated intravascular coagulation (DIC), TTP is not caused by excess thrombin (the enzyme that makes fibrin). Instead, TTP is caused by a severe deficiency of ADAMTS13 (an enzyme that cuts von Willebrand factor, a protein that helps platelets stick together). As a result, ultra large von Willebrand factor multimers (long chains of the protein) build up. This causes inappropriate platelet aggregation (platelets clumping together).
Most TTP is immune-mediated: the body makes autoantibodies (antibodies against its own tissues) against ADAMTS13. TTP can also follow systemic diseases such as HIV or systemic lupus erythematosus (SLE), and is associated with the use of certain drugs and chemotherapy (cancer drugs), whereas DIC is triggered by head trauma or sepsis. Blood films in TTP typically show an increased number of schistocytes (fragmented red blood cells). DIC may also show schistocytes, although this finding can be variable.
Immune Thrombocytopenia (ITP)
ITP (formerly called idiopathic or immune thrombocytopenic purpura) is an autoimmune disease that is caused by anti-platelet auto-antibodies and T-cell activity against platelets and megakaryocytes. T-cells are a type of lymphocyte. ITP can be triggered by infections and other associated autoimmune diseases, such as rheumatoid arthritis or systemic lupus erythematosus, however, the cause is unknown in 80% of the cases.
The symptoms of ITP are due to the low platelet count, e.g. excessive bruising, bleeding gums, etc. Treatment of ITP is needed when thrombocytopenia is severe (for example, a platelet count below 20,000 per microlitre), and it depends on the bleeding risk. It uses immunosuppressive therapies (treatments that dampen the immune system), most commonly corticosteroids.
Myelodysplastic syndromes (MDS) are a rare group of cancers that affect the blood-forming cells of the bone marrow. The immature blood cells that are produced are defective, and many of them die inside the bone marrow before they can be released (this is called ineffective haematopoiesis), so the blood counts are low. Over time, there are more immature and defective cells than healthy ones. Different cell lineages can be affected, however, the most common finding is a shortage of red blood cells (therefore the patient presents with anaemia).
Some MDS are idiopathic (no known cause), while others have factors that contribute to the risk (such as: chemotherapy or radiotherapy [treatment with radiation]; certain chemicals [tobacco, pesticides] and certain heavy metals).
Myelodysplastic syndromes are split into subtypes. These depend on the number and type of blood cells that are affected, the percentage of immature cells (blasts) in the bone marrow, and the genetic changes found in the cells. Many patients don’t exhibit any symptoms, but the signs produced are non-specific and related to the blood cytopenias (low blood cell counts): anaemia (low red blood cells - fatigue, dyspnoea [breathlessness] and tachycardia [fast heart rate]); neutropenia (low neutrophils - increased infection risk); thrombocytopenia (low platelets - increased bleeding risk).
About 1 in 3 patients with myelodysplastic syndromes might eventually develop leukaemia (specifically acute myeloid leukaemia). Infection and bleeding are also important causes of death. In one large registry of patients with MDS, they accounted for about 37% of deaths with a known cause (infection about 27% and bleeding about 10%).
Aplastic anaemia is a rare condition in which the body stops producing sufficient new blood cells of all three types (pancytopenia). It is usually autoimmune: the immune system attacks the stem cells in the bone marrow. This causes bone marrow damage (either aplasia or hypoplasia - a complete or partial reduction in the stem cells available).
Aplastic anaemia is often confused with myelodysplastic syndrome (MDS). MDS can also cause a low count of more than one type of blood cell. The key difference is in the bone marrow. In aplastic anaemia the marrow is hypocellular (it contains few cells). In MDS it is often hypercellular (it contains many cells) and the cells look dysplastic (abnormal), although a hypocellular form of MDS also exists. The symptoms that are produced are very similar to MDS.
Aplastic anaemia can be caused by immune disorders or exposure to chemicals, radiation or drugs, but most cases are idiopathic (no cause is found).
Treating aplastic anaemia depends on the severity of the disease, the patient’s age and whether a matched donor is available. The standard first-line treatment for severe disease is immunosuppressive therapy (medication that suppresses the immune system) with horse anti-thymocyte globulin and ciclosporin, together with eltrombopag (a drug that boosts blood cell production). Alternatively, a bone marrow transplant (an allogeneic haemopoietic stem cell transplant, using stem cells from a matched sibling donor) can be used. Risks with transplants include ‘graft-vs-host disease’, in which the newly created white blood cells may attack the rest of the body. In one Dutch registry of 127 adults given standard immunosuppressive therapy as first-line treatment, 79% were alive at five years.
Myelofibrosis is classified as a type of myeloproliferative neoplasm in which the excessive multiplication of abnormal haematopoietic stem cells in the bone marrow causes fibrosis. The abnormal cells produce cytokines (signalling proteins released by cells), which eventually cause the marrow to be replaced with scar tissue. The decrease in functioning tissue means the patients have a reduced ability to produce new blood cells, and progress to pancytopenia. The cause of this disease is usually associated with JAK2 mutations, but patients can also have mutations in the CALR gene (which codes for the protein calreticulin) or the MPL gene (which codes for the thrombopoietin receptor). About 90% of cases carry at least one of these three mutations.
The progressive replacement of healthy bone marrow with scar tissue causes the progenitor cells (early blood cell precursors) to begin to colonise the liver and spleen. This leads to extramedullary haematopoiesis (the production of blood cells outside the bone marrow medulla). It can present with hepatomegaly and splenomegaly (an enlarged liver and spleen). Symptoms are diverse. They include constitutional symptoms (night sweats, fever and weight loss), spleen-related symptoms (abdominal pain and early satiety, meaning feeling full after eating very little) and systemic symptoms (fatigue and itching). Anaemia and thrombocytopenia (a low platelet count) are also features, so some patients bruise easily. Up to 30% of patients have no symptoms at diagnosis.
Myelofibrosis is described as primary if the disease arises on its own (idiopathic), and secondary if it is a consequence of polycythaemia vera or essential thrombocythaemia.
There is currently no definitive cure for most patients, and prognosis varies depending on disease severity and risk factors. The only potentially curative treatment is allogeneic stem cell transplantation (a transplant of blood-forming stem cells from a donor), which is suitable only for selected patients. Otherwise, treatment is largely supportive and may include blood transfusions, symptom control with targeted therapies, and splenectomy (removal of the spleen) in selected cases. The targeted therapies include JAK inhibitors (drugs that block Janus kinase enzymes) such as ruxolitinib. NICE recommends ruxolitinib for disease-related splenomegaly or symptoms in adults with intermediate-2 or high-risk myelofibrosis.
Edited by: Dr. Ben Appleby and Dr. Thomas Burnell
Reviewed by: Dr. Marcus Judge
- 8773

