

SimpleMedSimpleMed
Hit enter to search or ESC to close

Get in Touch

Contact Us

Use our contact form.

The Nose

Share:

By Dr. Joshua Bray

Next Lesson - The Oral Cavity and Pharynx

  Head & Neck


Contents

  1. External Nose
  2. Nasal Cavity
  3. Paranasal Sinuses
  4. Vasculature of the Nose
  5. Epistaxis
  6. Innervation of the Nose
  7. Conditions Affecting the Nose and Sinuses
  8. Quiz

Abstract

  • The nose has many functions: these include olfaction (the sense of smell), filtering, humidifying and warming inspired air, speech and drainage.
  • The nasal skeleton is predominantly hyaline cartilage (smooth, glassy-looking cartilage) with a proximal bony root.
  • The nasal septum is cartilaginous anteriorly and bony posteriorly.
  • Septal haematomas need urgent drainage: if left untreated they can become infected (a septal abscess) and lead to saddle-nose deformity (the bridge of the nose collapses inwards) or a hole in the septum.
  • The nasal cavity is lined with olfactory mucosa and respiratory mucosa.
  • There are 3 pairs of conchae (bony shelves inside the nose), which increase the opportunity for air humidification and warming.
  • There are 4 pairs of paranasal sinuses (air-filled spaces in the skull around the nose): frontal, ethmoidal (in the bone between the eyes), maxillary, and sphenoidal (in the central bone at the base of the skull).
  • There is a rich anastomosis (a network where blood vessels join up) in the anterior nasal septum (Kiesselbach’s area), which is a common source of epistaxis (nosebleeds).
  • The nasal cavity is supplied with nerves by the olfactory nerve (for smell) and the trigeminal nerve (cranial nerve V, for ordinary sensation).
  • Rhinitis is inflammation of the nasal mucosa and includes both the common cold and hay fever.
  • Viral infection of the nose can spread to the paranasal sinuses, resulting in sinusitis (inflammation of the sinuses).
  • Nasal polyps are soft benign growths of the nasal mucosa and are usually bilateral.
  • Persistent unilateral (one-sided) nasal symptoms in an adult, such as blockage, discharge or nosebleeds, should raise suspicion of a tumour of the nose or sinuses and need urgent specialist referral. A foreign body is another cause, especially in children.
 

Core

The nose is the uppermost part of the respiratory tract (the airways) and lies immediately superior to the hard palate (the bony roof of the mouth).

Functions of the nose include:

  • Olfaction (smell)
  • Conduction of inspired air
  • Filtration of inspired air
  • Humidification and warming of inspired air
  • Resonance chamber for speech
  • Drainage of secretions from the paranasal sinuses and nasolacrimal ducts (the tubes that drain tears from the eyes into the nose)


External Nose

The external nose is the visible portion of the nose which protrudes from the face. Its prominent nature makes it particularly easy to injure in facial trauma (injury).

The nose has two external openings called the nares (or nostrils). Via the nares, inspired air immediately enters the vestibule of the nose (the entrance chamber just inside the nostril). The vestibule is lined with skin containing sebaceous glands (oil-producing glands) and hairs. The hairs assist in trapping unwanted particles from the air.

The skeleton of the nose is predominantly hyaline cartilage with a proximal bony root.

The bony part of the nose consists of the nasal bones, frontal processes (bony projections) of the maxillae, nasal part of the frontal bone and the bony part of the nasal septum.

There are 5 main nasal cartilages (a few smaller alar cartilages are also present):

  • 2 Lateral Cartilages - situated just inferior to the nasal bones. They are flattened and triangular in shape.
  • 2 Alar Cartilages (alar means wing-shaped) - the soft, flexible part of the external nose. These cartilages are mobile and can dilate with contraction of the nasalis muscle.
  • 1 Septal Cartilage - the cartilaginous part of the nasal septum.
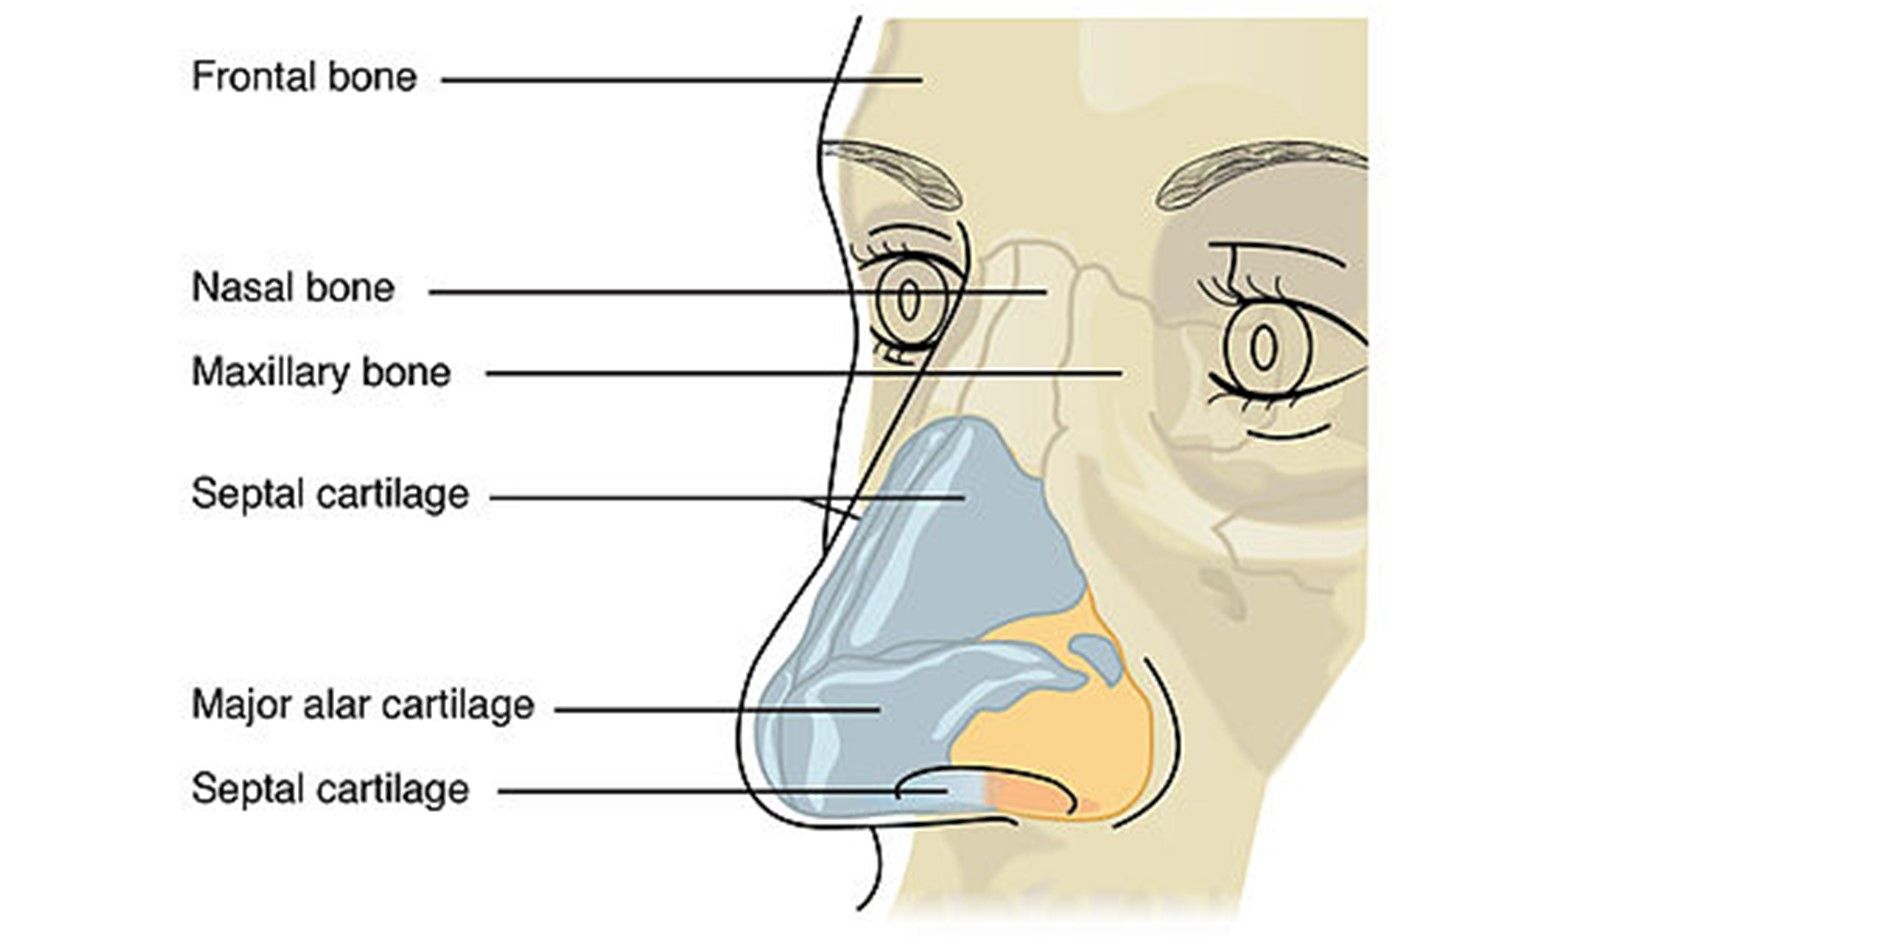
 

The Nasal Skeleton SimpleMed

Diagram - The nasal skeleton

Creative commons source by OpenStax College, edited by Dr. Joshua Bray [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]


Nasal Cavity

The nasal cavity is the internal space of the nose, which extends from the vestibule to the nasopharynx (the part of the throat behind the nose). It lies in an approximately horizontal plane.

The boundaries of the nasal cavity are:

  • Roof - cribriform plate of the ethmoid (the thin, perforated part of the ethmoid bone that the nerves of smell pass through), with contributions from the nasal bone anteriorly
  • Floor - hard palate
  • Lateral Walls - maxilla (mainly)
  • Medial Wall - nasal septum

The nasal septum separates the left and right nasal cavities. It has 2 parts:

  • Cartilaginous (anteriorly)
  • Bony (posteriorly) - consisting of the perpendicular portion of the ethmoid bone and the vomer bone (a thin, flat bone forming the lower back part of the septum)
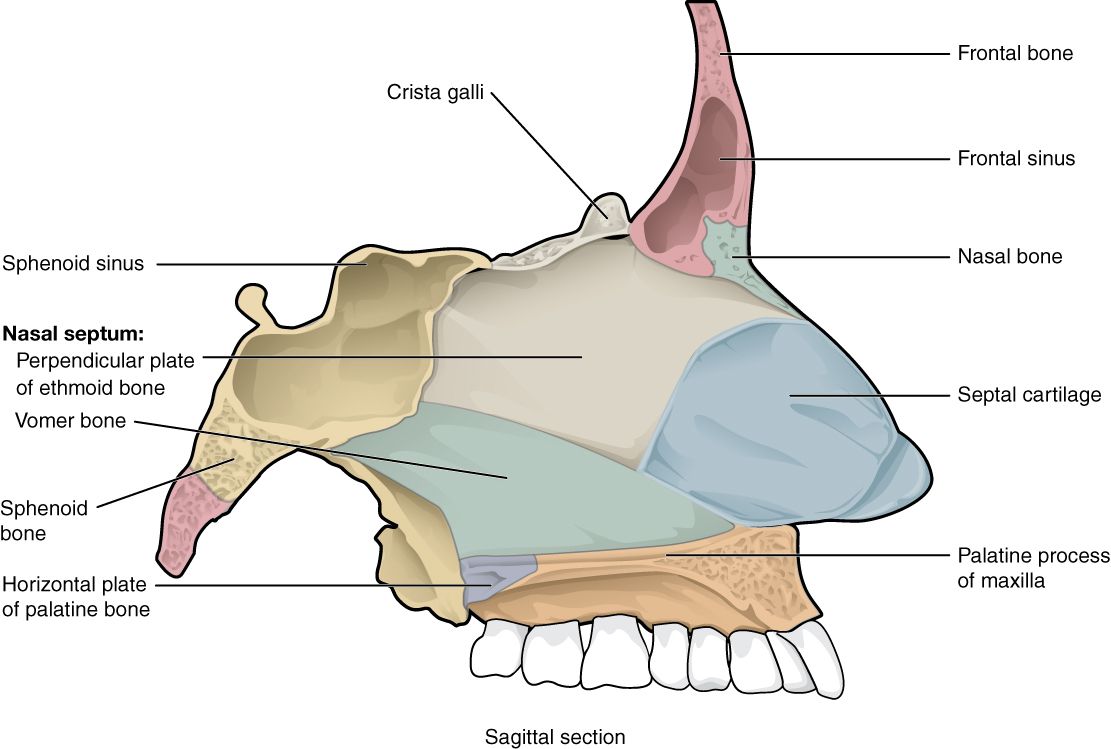
The Nasal Septum SimpleMed

Diagram - The nasal septum

Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]


Trauma to the nose could shear blood vessels in the nasal septum, causing a septal haematoma. This haematoma separates the cartilage from its overlying perichondrium (the membrane that covers cartilage and supplies it with blood), depriving the cartilage of its blood supply. If left untreated, the septal cartilage undergoes avascular necrosis (tissue death from loss of blood supply) and remodelling, resulting in a saddle-nose deformity (the bridge of the nose collapses inwards). The collection of blood can also become infected (a septal abscess), which can destroy the cartilage, make a hole in the septum (perforation) and lead to serious complications, including infection inside the skull. A septal haematoma is therefore an emergency and needs urgent drainage by a specialist in ear, nose and throat (ENT) surgery.

The nasal cavity is lined with mucosa and is highly vascular.

The olfactory mucosa lines the roof of the nasal cavity and houses olfactory neurones, which are responsible for our sense of smell. The neurones respond to chemicals in the air (aromas) by producing action potentials. These signals travel along the olfactory nerve (cranial nerve I, or CN I).

The rest of the nasal cavity is lined with respiratory mucosa. The respiratory mucosa is composed of pseudostratified columnar epithelium (tall cells in a single layer that looks layered) and houses cilia (tiny hair-like projections that sweep mucus along) and mucous glands. It acts to warm, humidify and filter inspired air.

The nasal conchae (or turbinates) are bony shelf-like projections from the lateral walls of the nasal cavity. There are 3 pairs of conchae: superior, middle and inferior. Each concha has a respective meatus, which is a gap underneath the curve of the concha. The function of the conchae is to induce turbulent air flow, thereby slowing air flow and increasing the opportunity for humidification and warming.
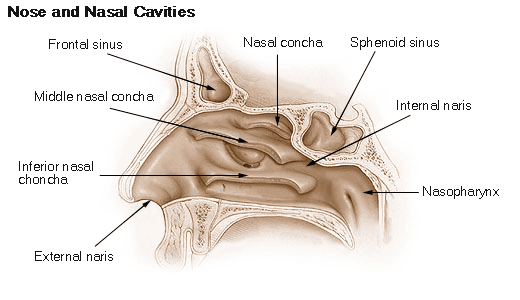
 

The Nasal Cavity and Conchae SimpleMed

Diagram - The nasal cavity and conchae

Public Domain Source (NIH) [Public domain]


Paranasal Sinuses

The paranasal sinuses are air-filled extensions of the nasal cavity. They are lined with respiratory mucosa. Their function is still debated. Suggested roles include lightening the weight of the head, supporting immune defence of the nasal cavity, humidifying inspired air and adding resonance to the voice.

There are 4 pairs of sinuses:

  • Frontal - situated between the outer and inner layers (tables) of the frontal bone.
  • Ethmoidal - otherwise termed ‘ethmoidal air cells’. They are small invaginations (inward pockets) of mucosa into the ethmoid bone (the bone between the eyes).
  • Maxillary - the largest of the paranasal sinuses, located within the body of the maxilla, just inferior to the orbit (eye socket).
  • Sphenoidal - located within the body of the sphenoid bone (the central bone at the base of the skull).
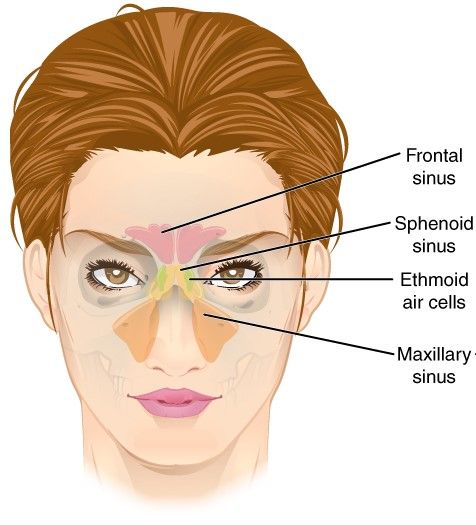
 

Paranasal Air Sinuses SimpleMed

Diagram -  Paranasal air sinuses

Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]


The paranasal sinuses have important anatomical relations with the structures below. These matter because infection or injury can spread between the sinuses and their neighbours:

  • Nasal Cavity - the sinuses drain directly into the nasal cavity.
  • Orbit - the maxillary sinus is situated immediately inferior to the orbit. Fractures to the floor of the orbit (‘orbital blow-out’ fracture) can cause the contents of the orbit to prolapse (drop down) into the maxillary sinus.
  • Anterior Cranial Fossa (the hollow in the floor of the skull that holds the front of the brain) - the frontal, ethmoidal and sphenoidal sinuses are in close proximity to the anterior cranial fossa.
  • Roots of Upper Teeth - these can sometimes project into the maxillary sinuses.


Vasculature of the Nose

The nasal cavity is supplied by branches of the ophthalmic (eye), maxillary, and facial arteries:

  • Anterior ethmoidal artery (ophthalmic a.)
  • Posterior ethmoidal artery (ophthalmic a.)
  • Sphenopalatine artery (maxillary a.)
  • Greater palatine artery (maxillary a.)
  • Superior labial artery (facial a.)

These arteries anastomose (join up to form a network) in the anterior nasal septum. This anastomosis is named Kiesselbach’s plexus or Little’s area and is a common source of epistaxis.
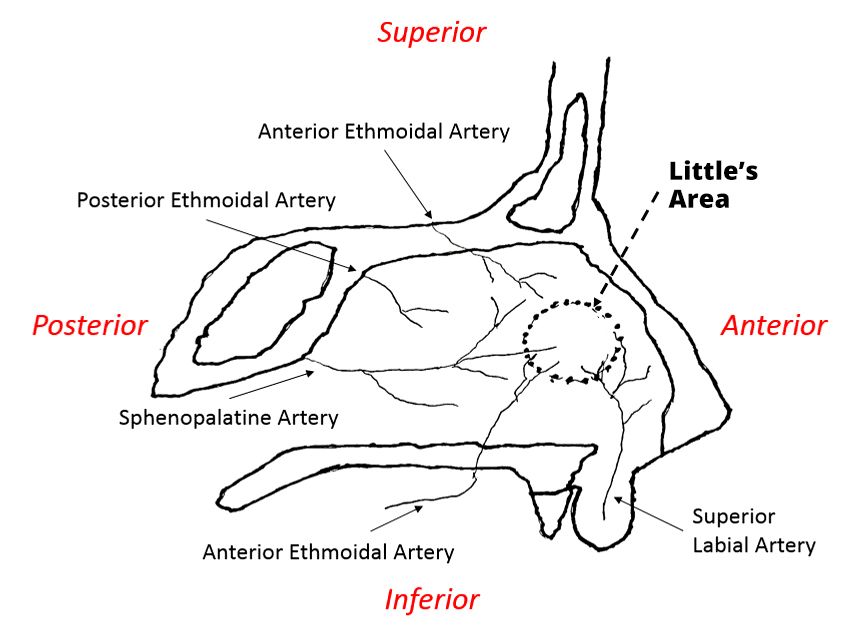
 

Arterial Supply of the Nasal Cavity SimpleMed

Diagram - Arterial supply of the nasal cavity

Creative commons source by Mbuchko3 [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]


Venous blood is drained via the sphenopalatine, facial, and ophthalmic veins. There is also a communication with the cavernous sinus (a large venous channel inside the skull, beside the pituitary gland), hence the nose is part of the ‘danger triangle’ of the face, where infections can potentially spread intracranially (into the skull).


Epistaxis

Epistaxis (a nosebleed) is often a minor and self-limiting (settles on its own) problem. However, persistent bleeds can be serious and lead to hypovolaemia (low blood volume).

In most cases the cause of the damage to the blood vessels is not identified. Known causes include minor trauma to the nose (for example nose-picking), inflammation of the nasal lining (for example from infection or allergy), medicines that thin the blood (anticoagulants and antiplatelet drugs such as aspirin), coagulopathies (blood clotting disorders), hereditary haemorrhagic telangiectasia (an inherited condition of fragile blood vessels) and tumours.

Epistaxis can be anterior or posterior in origin:

  • Anterior - this is the most common source, arising from Kiesselbach’s area.
  • Posterior - arising from the sphenopalatine artery. These bleeds are less common and more difficult to treat.

The management steps for epistaxis usually follow the order below, stopping once the bleeding is controlled. Urgent assessment is needed for anyone whose circulation is unstable (for example, a low blood pressure or fast pulse), whose bleeding does not stop after first aid, or who may have a posterior bleed:

  • First Aid - sit up with the head tilted forward and the mouth open, then pinch the soft part of the nose (the alar cartilages) firmly, without letting go, for 10 to 15 minutes.
  • Cautery (sealing the bleeding vessel, usually with a silver nitrate stick) - used if the bleeding point can be seen.
  • Anterior packing (a pack placed in the front of the nose) - used if cautery does not work or the bleeding point cannot be seen, using nasal tampons or an inflatable nasal pack.
  • Posterior packing - using a balloon catheter.
  • Surgical Intervention (last resort) - either embolisation (blocking the vessel from inside, guided by X-ray imaging) or ligation (tying off the vessel).


Innervation of the Nose

Special sensory innervation (the nerve supply for the sense of smell, or olfaction) is via the olfactory nerve (cranial nerve I, or CN I).

The somatosensory innervation (the nerve supply for ordinary sensation, such as touch and pain) of the nasal cavity is via branches of the trigeminal nerve (cranial nerve V, or CN V):

  • Anterosuperiorly (front and top) - via the ophthalmic division (CN V1)
  • Posteroinferiorly (back and bottom) - via the maxillary division (CN V2)


Conditions Affecting the Nose and Sinuses

Rhinitis is an umbrella term for inflammation of the nasal mucosa. It encompasses both the common cold (coryza) and allergic rhinitis (hay fever). Typical symptoms include nasal irritation, sneezing, nasal discharge and congestion.

The common cold is caused by a range of respiratory viruses, including rhinoviruses, adenoviruses and coronaviruses. It is transmitted via droplet spread and is highly contagious. However, the disease is often mild and self-limiting. In addition to nasal symptoms, individuals may experience fever, fatigue, malaise (a general feeling of being unwell) and sore throat.

Sometimes viral infection can spread from the nose to the paranasal sinuses, resulting in sinusitis (inflammation of the sinuses). About 0.5 to 2% of cases of viral sinusitis develop a bacterial infection (most often with Streptococcus pneumoniae, Haemophilus influenzae or Moraxella catarrhalis). Clinical features include frontal headache, purulent (pus-containing) nasal discharge, facial pain and tenderness, and fever. Sinusitis is normally self-limiting. Bacterial sinusitis is also usually self-limiting, so antibiotics are not routinely needed. NICE advises no antibiotic prescription for symptoms of around 10 days or less. If symptoms last longer without improving, the options are no antibiotic or a back-up prescription (one the patient uses only if symptoms do not improve within 7 days or get rapidly worse). An immediate antibiotic is for people who are very unwell, have signs of a more serious illness or are at high risk of complications. Bacterial sinusitis is more likely if several of these are present: symptoms for more than 10 days, discoloured or purulent nasal discharge, severe pain on one side of the face (especially over the teeth and jaw), fever, and a marked worsening after an initial milder phase. Swelling around the eye, double vision, swelling over the forehead or a severe frontal headache suggest a complication and need referral to hospital.

Hay fever is a manifestation of a Type I hypersensitivity reaction (allergy). B cells (a type of white blood cell) recognise allergens and produce IgE (immunoglobulin E, an antibody), which binds to mast cells (immune cells that store histamine). When the same allergen is met again, the mast cells release histamine and other inflammatory substances, resulting in local inflammation. Common allergens include pollen, dust mites, animal dander (tiny flakes of skin and fur) and mould. Hay fever also commonly affects the eyes and is associated with other atopic (allergy-prone) illness such as asthma and eczema. Avoiding the allergen helps where this is possible. First-line drug treatment is an intranasal corticosteroid (a steroid spray used in the nose), an antihistamine (a non-sedating tablet or a nasal spray), or both together. Intranasal corticosteroids are the most effective treatment and are suggested first for moderate to severe or persistent symptoms.

Nasal polyps are fleshy benign growths of the nasal mucosa. Affected individuals may complain of nasal discharge (with or without blood), blocked nose, loss of smell or taste, cough (due to post-nasal drip, which is mucus running down the back of the throat) and snoring. Nasal polyps are usually bilateral. Persistent unilateral symptoms, such as nasal obstruction, discharge or nosebleeds, should raise suspicion of a sinonasal tumour (a tumour of the nose and sinuses) and need an urgent suspected cancer pathway referral.

In children, another important differential for nasal discharge is a foreign body (an object pushed into the nose), which typically causes a unilateral discharge or blockage.


Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge

Free account

Keep reading for free

Create a free account to continue reading The Nose.

Your account includes:

  • Thousands of free practice questions
  • Tools to track your revision progress
Sign up free Already have an account? Log in

No payment. No spam. Just free medical revision.

Quiz

Preview the The Nose quiz

Practice this topic

Free single best answer questions written by UK doctors, with an explanation after every answer.
  • The Nose: free SBA questionsQuestions on this article→
  • Head and Neck question bankEvery question in this subject→
  • Free medical question bankAll subjects, with full explanations→
SimpleMed+ EncyclopaediaShort and simple explanations of hard topics, with memory aids→
SimpleMed+

Want More?

Access more on SimpleMed+

Lock it in with practice questions, the full question bank and revision tools that track what you know.

Practice now
6236

Free medical encyclopaedia

Concise concepts, mechanisms and exam traps for medical students. Free to read, no account needed.
Head and Neck concepts →All encyclopaedia subjects
simplemedlonglogo.png
  • Home
  • Terms & Conditions
  • Privacy Policy
  • Contact

The medical information on this site is provided as an information resource only, and is not to be used or relied on for any diagnostic or treatment purposes. This information is intended for medical education, specifically to biological/medical learning inclined individuals, and does not create any doctor-patient relationship, and should not be used as a substitute for professional diagnosis and treatment.

©2026 Lili's Ark Limited, UK Company #15424953
S+

Search

  • Pre-Clinical
    • Cardiovascular System
      • 1. Anatomy of the Cardiovascular System
      • 2. The Cardiac Cycle
      • 3. Pulses and Pressures
      • 4. Control of Cardiac Output
      • 5. Cardiac Conduction and Contraction
      • 6. Embryology of the CVS
      • 7. Congenital Heart Defects
      • 8. Hypertension
      • 9. Electrocardiograms
      • 10. Electrocardiogram Pathology
      • 11. Cardiovascular Drugs
      • 12. Murmurs
      • 13. Special Circulations
      • 14. Heart Failure
      • 15. Artery and Vein Disease
      • 16. Acute Coronary Syndromes
      • 17. Haemodynamic Shock
    • Musculoskeletal System
      • The Human Body
        • 1. Anatomical Terms
        • 2. Structure of the Muscles
        • 3. Muscles in Action
        • 4. Connective Tissue
        • 5. Cartilage: Structure, Growth and Repair
        • 6. Structure of Bones
        • 7. Basics of Bone Anatomy
        • 8. Joints
        • 9. The Spine
        • 10. Dermatomes and Myotomes
        • 11. The Brachial Plexus
        • 12. The Lumbar Plexus
        • 13. The Sacral Plexus
      • Clinical Conditions
        • 1. Conditions of the Foot
        • 2. Conditions of the Ankle
        • 3. Conditions of the Lower Leg
        • 4. Conditions of the Knee
        • 5. Conditions of the Thigh
        • 6. Conditions of the Hip
        • 7. Conditions of the Lower Back
        • 8. Conditions of the Back and Neck
        • 9. Conditions of the Shoulder and Clavicle
        • 10. Conditions of the Arm
        • 11. Conditions of the Elbow
        • 12. Conditions of the Forearm and Wrist
        • 13. Conditions of the Hand
      • Musculoskeletal Anatomy
        • 1. Muscles of the Gluteal Region
        • 2. Muscles of the Thigh
        • 3. Key Areas of the Lower Limb
        • 4. Bones of the Lower Limb
        • 5. Bones of the Foot
        • 6. Muscles of the Lower Leg
        • 7. Bones of the Upper Limb
        • 8. Muscles of the Shoulder
        • 9. Muscles of the Upper Arm
        • 10. Bones of the Hand
        • 11. Muscles of the Forearm
        • 12. Key Areas of the Upper Limb
    • Cell Physiology & Biology
      • 1. An Introduction to the Cell
      • 2. Introduction to DNA
      • 3. The Cell Cycle, Checkpoints and Apoptosis
      • 4. Structure of Proteins
      • 5. Protein Function in Oxygen Transport
      • 6. Enzymes and Regulation of Protein Function
      • 7. Molecular Techniques for Medics
      • 8. Post-translational Modification and Collagen Biosynthesis
      • 9. Protein Targeting
      • 10. Biological Membranes
      • 11. G-Protein Coupled Receptor
      • 12. Enzyme-linked and Intracellular Receptor Signalling
      • 13. Membrane Transport and Intracellular Calcium Regulation
      • 14. Membrane Potentials
      • 15. Action Potentials
      • 16. Autonomic Nervous System Introduction
    • Metabolism
      • 1. Nutrition, Diet and Body Weight
      • 2. Energy Reactions in Cells
      • 3. Dietary Energy Production
      • 4. Vitamins, Cofactors, Minerals and Trace Elements
      • 5. Glycolysis
      • 6. Oxygen-dependent Pathway
      • 7. Lipid Metabolism and Transport
      • 8. Protein and amino acid metabolism
      • 9. Purine and Pyrimidine Metabolism
      • 10. Inborn Errors of Metabolism and Newborn Screening
      • 11. Alcohol Metabolism
      • 12. Oxidative Stress
      • 13. Energy Storage
      • 14. Temperature Regulation
      • 15. Metabolic and Endocrine Regulation
    • Endocrinology
      • 1. An Introduction to Endocrinology
      • 2. Control of Appetite
      • 3. The Adrenal Glands and Adrenal Disorders
      • 4. HPA and Growth Hormone
      • 5. Pituitary Disorders
      • 6. The Thyroid Gland
      • 7. The Endocrine Pancreas
      • 8. Diabetes Mellitus
      • 9. Calcium Metabolism
    • Haematology
      • 1. Haematopoiesis and the Spleen
      • 2. Full Blood Count
      • 3. Blood Groups, Crossmatching and Transfusion Reactions
      • 4. Anaemia
      • 5. Vitamin B12 and Folate
      • 6. Iron Metabolism
      • 7. Haemoglobinopathies
      • 8. When Haematopoiesis goes wrong
      • 9. Haematology in Systemic Disease
    • Genetics
      • 1. Mitosis and Meiosis
      • 2. Genotype, Phenotype and Inheritance
      • 3. Gene Expression
      • 4. Epigenetics, Genomic Imprinting and Mitochondrial Inheritance
      • 5. Introduction to Gene Mutation
      • 6. DNA Repair and Cancer
      • 7. Genetic Testing and Counselling
    • Infection
      • 1. An Introduction To Infection
      • 2. The Infection Model
      • 3. Bacterial Structure, Classification and Growth
      • 4. Biofilms
      • 5. Innate Immunity
      • 6. Adaptive Immunity
      • 7. Gram Staining and Infection Investigations
      • 8. Staphylococci and Other Gram-positive Bacteria
      • 9. Streptococci
      • 10. Gram-negative Bacteria: Structure, Entry Routes and Endotoxin
      • 11. The Organisms Gram Staining Misses
      • 12. Sepsis
      • 13. Antibiotics
      • 14. Principles of Medical Virology
      • 15. Hepatitis
      • 16. Human Immunodeficiency Virus
      • 17. Fungi and Parasites: The Eukaryotic Pathogens
      • 18. The Immunocompromised Host
      • 19. Travel-related Infections
    • Pathology
      • 1. An Introduction to Pathology
      • 2. How to Read a Histology Slide
      • 3. The Basics of Pathology
      • 4. Epithelium, Skin and Exocrine Glands
      • 5. Acute Inflammation
      • 6. Chronic Inflammation
      • 7. Regeneration and Repair of Tissues
      • 8. The Lymphatic System
      • 9. Haemostasis and Clotting
      • 10. Thrombosis and Embolism
      • 11. Atherosclerosis
      • 12. Cellular Adaptations
      • 13. Introduction to Neoplasia
      • 14. Pathogenesis of Neoplasms
      • 15. Behaviour of Neoplasms
    • Population & Social Science
      • 1. Introduction to Population Science
      • 2. Describing Data and Testing Hypotheses
      • 3. Epidemiological Studies
      • 4. Models of Health
      • 5. Beliefs of the Public
      • 6. Health Economics
      • 7. Evidence-Based Practice
      • 8. Patient Safety and Quality Control
      • 9. Summary and Glossary
    • Patient-Centred Care
      • 1. Lifestyle Medicine
      • 2. Childhood Immunisations
      • 3. Sepsis in Paediatrics
      • 4. Child Safeguarding
      • 5. Ageing
      • 6. Falls
      • 7. Men's Health
      • 8. Palliative Care
    • Reproductive System
      • 1. Anatomy of the Man
      • 2. Anatomy of the Woman
      • 3. The Pelvic Floor
      • 4. Development of the Reproductive System
      • 5. Puberty
      • 6. The Menstrual Cycle and Menstrual Abnormalities
      • 7. Gametogenesis
      • 8. Sex, Infertility and Contraception
      • 9. Physiology of the Mother
      • 10. Diseases of the Mother in Pregnancy
      • 11. Physiology of the Fetus
      • 12. The Placenta
      • 13. Labour and Delivery
      • 14. The Postpartum Period
      • 15. Infections of the Reproductive Tract
      • 16. Pelvic Inflammatory Disease
      • 17. The Menopause
      • 18. Malignancies of the Reproductive Tract
      • 19. Introduction to the Breast
      • 20. Benign Conditions of the Breast
      • 21. Malignant Breast Disease
    • Respiratory System
      • 1. Anatomy of the Respiratory System
      • 2. Development of the Respiratory System
      • 3. Ventilation and Lung Mechanics
      • 4. Properties of Gas Exchange
      • 5. Carbon Dioxide Transport
      • 6. Chemical Control of Breathing and Plasma pH
      • 7. Lung Function Testing
      • 8. Pulmonary Embolism
      • 9. Asthma
      • 10. Chronic Obstructive Pulmonary Disease
      • 11. Pneumonia and other Lower Respiratory Tract Infections
      • 12. Bronchiectasis and Cystic Fibrosis
      • 13. Tuberculosis
      • 14. Pneumothorax and Pleural Effusion
      • 15. Lung Cancer
      • 16. Respiratory Failure
    • Urinary System
      • 1. Anatomy of the Kidneys, Bladder and Urethra
      • 2. Development of the Urinary System
      • 3. The Nephron
      • 4. The Glomerulus – Tubular Reabsorption and Secretion
      • 5. Control of Plasma Volume
      • 6. Control of Plasma Osmolarity
      • 7. Control of Potassium
      • 8. Micturition
      • 9. Diuretics
      • 10. Glomerular Filtration Rate and the Measurement of Kidney Function
      • 11. Hyponatraemia
      • 12. Urinary Incontinence
      • 13. Glomerular Disease
      • 14. Diabetic Nephropathy
      • 15. Acute Kidney Injury
      • 16. Chronic Kidney Disease
      • 17. Urinary Tract Obstruction
      • 18. Urinary Tract Infections
      • 19. Prostate Pathology
      • 20. Male Urological Conditions
      • 21. Urological Malignancy
    • Gastrointestinal System
      • 1. Development of the Gastrointestinal Tract
      • 2. Abdominal Wall and Inguinal Canal
      • 3. Anatomy and Physiology of the Foregut
      • 4. Anatomy and Physiology of the Midgut
      • 5. Anatomy and Physiology of the Hindgut
      • 6. Gastrointestinal Motility and the Enteric Nervous System
      • 7. Liver, Biliary and Exocrine Pancreatic Physiology
      • 8. Gastrointestinal Secretion, Digestion and Absorption
      • 9. Upper Gastrointestinal Pathology
      • 10. Hepatic, Biliary and Pancreatic Pathology
      • 11. Intestinal Pathology
      • 12. Distal Gastrointestinal Tract Pathology
      • 13. Gastrointestinal Malignancy
      • 14. Gastroenteritis and Enterocolitis
      • 15. Gastrointestinal Emergencies
    • Head & Neck
      • 1. Introduction to Head & Neck Anatomy
      • 2. Blood Supply of the Head and Neck
      • 3. Lymph Nodes and Neck Lumps
      • 4. The Skull
      • 5. The Temporomandibular Joint
      • 6. The Meninges
      • 7. Cranial Nerves I-VI
      • 8. Cranial Nerves VII-XII
      • 9. Development of the Head and Neck
      • 10. Autonomics in the Head and Neck
      • 11. Anatomy of the Ear
      • 12. Ear Pathology
      • 13. The Nose
      • 14. The Oral Cavity and Pharynx
      • 15. The Eye
      • 16. The Larynx
      • 17. Head and Neck Cancers
      • 18. Imaging of the Head and Neck
      • 19. Fascial Planes, Muscles and Triangles
    • Immunology
      • 1. An Introduction to Hypersensitivity
      • 2. Type 1 Hypersensitivity
      • 3. Food Allergy
      • 4. Introduction to Autoimmunity
      • 5. Rheumatoid Arthritis
      • 6. Systemic Lupus Erythematosus (SLE)
      • 7. Immunological Therapies | Monoclonal Antibodies
    • Neuroanatomy & Psychiatry
      • 1. Basics of Neuroanatomy
      • 2. Cells and Components of the Nervous System
      • 3. Arterial Supply to the Brain
      • 4. Development of the Nervous System
      • 5. Production and Circulation of CSF and Related Disorders
      • 6. Somatosensory System
      • 7. Motor System
      • 8. The Cerebellum: Circuits, Coordination and Clinical Signs
      • 9. Visual System
      • 10. Auditory and Vestibular Systems
      • 11. The Hypothalamus and Limbic System
      • 12. Higher Cortical Function
      • 13. Reticular Formation
      • 14. Movement Disorders
      • 15. Infections of the Central Nervous System
      • 16. Dementia
      • 17. Delirium
      • 18. Headaches
      • 19. Stroke
      • 20. Raised Intracranial Pressure (ICP)
      • 21. Subarachnoid Haemorrhage
      • 22. Anxiety
      • 23. Mood Disorders
      • 24. Psychosis
    • Embryology
      • 1. The Basics of Embryology
      • 2. Development of the Limbs and Body Wall
      • 3. Teratology and Congenital Malformations
      • 4. Development of the Gastrointestinal Tract
      • 5. Development of the Reproductive Systems
      • 6. Development of the Urinary System
      • 7. Development of the Respiratory System
      • 8. Development of the Head and Neck
      • 9. Development of the Nervous System
      • 10. Embryology of the Cardiovascular System
    • Pharmacology
      • 1. Research Methods in Pharmacology
      • 2. Pharmacokinetics
      • 3. Pharmacodynamics
      • 4. Pharmacovigilance and Pharmacogenetics
      • 5. Safe Prescribing
      • 6. Cholinergic Pharmacology
      • 7. Adrenergic Pharmacology
      • 8. Hypertension and Heart Failure
      • 9. Cardiac Arrhythmias
      • 10. Antiplatelets, Anticoagulants and Thrombolysis
      • 11. Hyperlipidaemias
      • 12. Diuretics and Renal Pharmacology
      • 13. Pharmacology of Insulin
      • 14. Reproductive and Post-reproductive Health
      • 15. Antibiotics
      • 16. Antivirals
      • 17. Cancer Chemotherapy
      • 18. Anaesthetics
      • 19. Opioids
      • 20. Introduction to Psychopharmacology
      • 21. Epilepsy and Anti-epileptic Drugs
      • 22. Parkinson's Disease and Myasthenia Gravis
      • 23. NSAIDs
      • 24. Immunosuppression and Disease-modifying Therapy
      • 25. Pharmacology of Airway Control
      • 26. Drugs Affecting Acid Secretion
      • 27. Antiemetics and Laxatives
      • 28. Poisoning and STOPP/START
  • OSCE
    • Index Conditions for OSCE exams
    • Cardiovascular System Examination
    • Shoulder Examination
    • Hand Examination
    • Venepuncture
    • Blood Pressure
    • Respiratory System OSCE Examination
    • Peripheral Vascular OSCE Examination
    • Varicose Vein OSCE Examination
    • Deep Vein Thrombosis (DVT) OSCE Examination
    • Abdominal OSCE Examination
    • Rectal (PR) OSCE Examination
    • Stoma OSCE Examination
    • Hernia OSCE Examination
    • Upper Limb Neurological OSCE Examination
    • Lower Limb Neurological OSCE Examination
    • Cranial Nerve OSCE Examination
    • Cerebellar OSCE Examination
    • GALS Screening OSCE Examination
    • Elbow OSCE Examination
    • Hip OSCE Examination
    • Knee OSCE Examination
    • Ankle and Foot OSCE Examination
    • Spine OSCE Examination
    • Thyroid Status OSCE Examination
    • Diabetic Foot OSCE Examination
    • Cushing's Syndrome OSCE Examination
    • Acromegaly OSCE Examination
    • Ear, Otoscopy and Hearing OSCE Examination
    • Nasal OSCE Examination
    • Eye and Vision OSCE Examination
    • Fundoscopy (Ophthalmoscopy) OSCE Examination
    • Visual Acuity OSCE Assessment
    • Anterior Segment Eye OSCE Examination
    • Pigmented Skin Lesion OSCE Examination
    • Rash and Non-Pigmented Skin Lesion OSCE Examination
    • Breast OSCE Examination
    • Testicular OSCE Examination
    • Neck Lump OSCE Examination
    • Lymphoreticular OSCE Examination
  • Question Bank
  • About
  • How to Use SimpleMed
  • SimpleMed Lecture Series
  • DON'T PANIC - Guide to the Wards
  • SimpleMed Plus
Your privacy We use optional analytics cookies (Google) and advertising measurement cookies (Google and Meta) to understand how SimpleMed is used and to measure our adverts. Privacy policy
