

Next Lesson - Abdominal Wall and Inguinal Canal
Core
This article covers the development of the gastrointestinal system.
In the fourth week of embryonic development, the trilaminar disc (the flat, three-layered early embryo) folds in two ways:
It folds laterally (the sides of the embryo fold in towards the middle) to create a ventral body wall and a tubular primitive gut.
It also folds craniocaudally (along the head-to-tail axis) to form the cranial and caudal blind end pouches from endoderm (the innermost layer of the embryo) of the yolk sac (the early food store attached to the embryo).
The gut tube is an endoderm-lined tube that runs the length of the body with blind pouches at the head and tail ends. It opens at the umbilicus (belly button) via the vitelline duct (the narrow tube joining the midgut to the yolk sac).
The foregut and hindgut develop from the head and tail blind pouches, and the midgut develops from the portion that is continuous with the yolk sac via the vitelline duct.
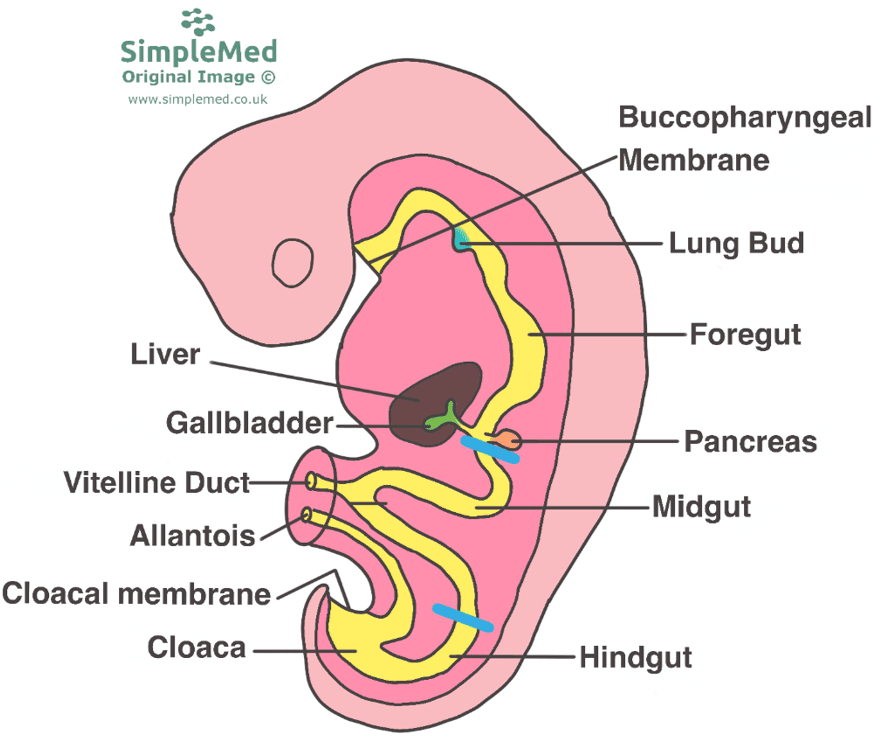
Diagram - The gut tube in the developing embryo. The blind pouches that form the foregut and the hindgut are prevented from being open by the buccopharyngeal membrane (closing the mouth end) and the cloacal membrane (closing the anal end)
SimpleMed original by Dr. Maddie Swannack
The intraembryonic coelom is a structure that forms from mesoderm (the middle layer of the embryo) during the third week of embryonic development. It is a cavity in the centre of the embryo that, when separated by the developing diaphragm, goes on to form the thoracic and abdominal cavities. One membrane lines the whole intraembryonic coelom. As the cavities separate, this membrane specialises to form the pleural and peritoneal membranes (the linings of the chest and abdominal cavities). A number of key organ systems develop within the coelom.
A mesentery is a double fold of the peritoneal membrane that suspends the gut tube within the intraembryonic coelom away from the abdominal wall. The mesentery allows the gut tube to move (motility) and provides a path for the blood and nerve supply from the abdominal wall to the suspended gut tube.
They form from splanchnic mesoderm (mesoderm around the gut tube) as a double layer of peritoneum associated with the intraembryonic coelom.
There are two mesenteries attached to the gut tube:
- The dorsal mesentery attaches the ‘back’ of the gut tube to the posterior abdominal wall. It runs the whole length of the gut tube.
- The ventral mesentery attaches the ‘front’ of the gut tube to the anterior abdominal wall. It only attaches the foregut, ending at the distal foregut and leaving a free edge.

Diagram - The rotation of the foregut. Notice that the gut tube has dorsal and ventral mesenteries, and that the right sac becomes the lesser sac and the left sac becomes the greater sac. The development of the liver and the spleen is more complex than shown, but it is a good representation of their location
SimpleMed original by Dr. Maddie Swannack
This means that at the foregut, the two mesenteries (dorsal and ventral) divide the cavity (intraembryonic coelom) into two sections, the left and right sacs. Distal to the foregut, however, there is only the dorsal mesentery. This single cavity is the continuation of the left sac.
With further folding and development of the organs, the left sac develops into the greater sac, and the right sac develops into the lesser sac.
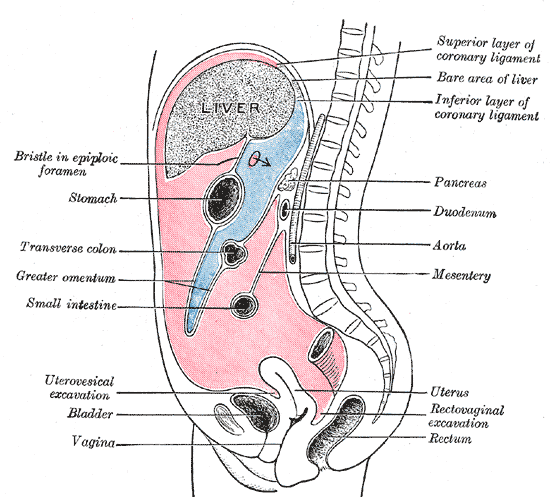
Diagram - The greater sac (in pink) and the lesser sac (in blue) in the sagittal plane. Remember the lesser omentum runs between the liver and the stomach, with the epiploic foramen connecting the greater and lesser sacs. The greater omentum (labelled) is the ‘flap’ with four layers of visceral peritoneum
Public Domain Source Anatomy of the Human Body, by Henry Gray [Public domain]
Omenta are sheets of visceral peritoneum (peritoneum that covers organs lying inside the abdominal cavity, known as intraperitoneal organs) extending from the stomach and duodenum to other organs. They form the boundary of the lesser and greater sacs.
The greater omentum is made up of four layers of visceral peritoneum, and attaches to the greater curvature of the stomach and to the transverse colon. It lies like an apron over the front of the intestines in the adult. It has roles in preventing adhesion of organs to the parietal peritoneum (the peritoneum lining the abdominal wall) and in covering inflamed organs to protect nearby structures which is why it is referred to as the ‘policeman of the abdomen’.
The lesser omentum is made up of only two layers of visceral peritoneum, and attaches to the lesser curvature of the stomach and to the liver. The lesser omentum has a free edge (a rim that is not attached to another structure) because the ventral mesentery ends at the foregut. This edge contains the bile duct, portal vein and hepatic artery on their way to the liver.
The epiploic foramen (foramen of Winslow) is the connection between the lesser and greater sacs.

Diagram - The greater (in red) and lesser (in blue) sacs in the transverse plane. It shows the epiploic foramen very clearly
Public Domain Source Anatomy of the Human Body, by Henry Gray [Public domain]
When there is no mesentery, organs are not suspended in the abdominal cavity but are attached to the abdominal wall. This means that they are covered only by parietal peritoneum (the peritoneal layer lining the abdominal wall). These organs can be:
- Primarily Retroperitoneal - these organs were never covered by visceral peritoneum or had a mesentery. These organs developed and stayed behind the peritoneum (in the retroperitoneal space), like the kidneys.
- Secondarily Retroperitoneal - these organs did have a mesentery, but as they grew, the mesentery fused with the posterior abdominal wall, causing the organ to become retroperitoneal. The structure formed by the fusion of the parietal and visceral peritoneum is known as a fusion fascia. Examples of this are the ascending and descending colons.

Diagram - The difference between primarily retroperitoneal, secondarily retroperitoneal and intraperitoneal organs. In the image, the abdomen shown on the left is earlier in development than the one on the right
SimpleMed original by Dr. Maddie Swannack
Each region of the gut develops from the foregut, midgut or hindgut. The principal abdominal arterial pattern is the coeliac trunk (a large branch of the abdominal aorta) for the foregut, the superior mesenteric artery for the midgut and the inferior mesenteric artery for the hindgut. This is not an exclusive supply to every structure that develops from that region. The oesophagus has segmental arterial supply (it is supplied by different arteries along its length). The duodenum and pancreatic head receive pancreaticoduodenal branches (small arteries supplying the pancreas and duodenum) from both the coeliac and superior mesenteric territories (the areas each artery supplies). Each region also has a pattern of visceral innervation (nerve supply to the internal organs) relevant to localisation of pain.
Visceral pain is caused by pathology in visceral organs, often due to stretch, ischaemia or inflammation, and may involve the visceral peritoneum. It is poorly localised, and is generally referred to the dermatome (the area of skin supplied by one spinal nerve) of the nerve that supplies the affected organ. If inflammation of the viscera (internal organs) becomes bad enough to irritate the parietal peritoneum, pain is localised much more accurately, directly over the organ itself. This is because the parietal peritoneum receives somatic innervation (nerve supply that senses touch and pain, as the skin does).
Some structures that develop on the border between divisions receive blood from the arteries of both. For example, the duodenum develops from the foregut and the midgut, so it is supplied by both the coeliac trunk and the superior mesenteric artery. Bleeding duodenal ulcers (sores in the lining) can be difficult to control and are prone to bleed again. Most duodenal ulcers occur in the first part of the duodenum (the duodenal bulb). This part is supplied by the gastroduodenal artery (a branch of the coeliac trunk), and an ulcer that erodes this artery can cause serious bleeding.
The coeliac trunk is the principal arterial trunk for the abdominal foregut, rather than the exclusive supply to every foregut derivative. The oesophagus has segmental arterial supply, while the duodenum and pancreatic head have overlapping coeliac and superior mesenteric supply. Foregut visceral pain is generally referred to the epigastric region (the upper central abdomen). The sympathetic pathways are associated with the greater splanchnic nerve (a nerve carrying autonomic fibres to the abdominal organs, from spinal levels T5-9). Organs that develop from the foregut are:
- Oesophagus
- Stomach
- Pancreas
- Liver
- Gallbladder
- Portion of the duodenum that is proximal to the entrance of the bile duct
The lung bud also develops from an outpouching of the gut tube. See our article on respiratory embryology for more information.
The stomach starts off as a long tube, connected to the abdominal wall by the dorsal and ventral mesenteries. The tube begins by rotating longitudinally (along its long axis). The ventral edge swings around to the right and becomes the lesser curve of the stomach. The dorsal edge swings around to the left and becomes the greater curve of the stomach. When viewed from below (the way a CT scanner displays an image), the stomach has gone through a 90 degree rotation anticlockwise. Seen from above, the same movement is a 90 degree clockwise rotation, which is how it is often described.
The curves are of different sizes due to the asymmetrical growth of the stomach. The new greater curve which is lying on the left side grows faster than the lesser curve which is to the right. This uneven growth is known as anteroposterior rotation. It creates a bulge in the stomach and causes the duodenal end of the stomach tube to be pulled up, creating the classic stomach shape.
The lungs develop from an outpouching of the foregut called the respiratory diverticulum. At around week 4 of development, the tracheo-oesophageal septum develops, separating the gastrointestinal and respiratory tracts.
Abnormal positioning of this septum can lead to a tracheo-oesophageal fistula - an abnormal connection between the gastrointestinal and respiratory tracts.
For more information on the development of the lungs, please see our article on the development of the respiratory system.
Development of Other Foregut Structures
The development of the pancreas, liver and duodenum is closely linked.
The liver and biliary system (the bile ducts and gallbladder) develop in the ventral mesentery of the foregut, and the pancreas develops partially in the ventral and partially in the dorsal mesenteries.

Diagram - The development of the pancreas. It begins in both the ventral and dorsal mesenteries of the foregut, and through rotation and fusion it becomes one gland. This creates the classical ‘C’ shape of the duodenum
SimpleMed original by Dr. Maddie Swannack
The duodenum sits in a ‘C’ shape around the pancreas. The pancreas pushes the duodenum against the posterior abdominal wall, which causes most of it (all except the first part) to become secondarily retroperitoneal (it ends up behind the peritoneum). The first part is the exception and stays covered by peritoneum.
The midgut is supplied by the superior mesenteric artery (SMA) and lesser splanchnic nerve (a nerve carrying autonomic fibres to the abdominal organs, from spinal levels T10-11). The organs that develop from the midgut therefore get their main blood supply from the SMA. Pain from these organs is felt in the periumbilical region (around the belly button; T10-11 dermatomes). Organs that develop from the midgut are:
- Portion of the duodenum that is distal to the entrance of the bile duct (ampulla of Vater)
- Jejunum
- Ileum
- Caecum (the pouch at the start of the large intestine) and appendix
- Ascending colon
- Proximal 2/3 of the transverse colon
The midgut elongates rapidly during development to form the small intestine. However, the abdominal cavity does not grow at the same rate and also contains the rapidly enlarging liver. This means that the growing intestine runs out of space to grow inside the abdominal cavity. As a result it forms a loop that grows outside of the abdominal cavity. This forms a physiological hernia (a normal, temporary bulge of bowel into the umbilical cord) through the umbilicus (belly button).
This loop has the superior mesenteric artery as its axis. This artery supplies blood to the midgut, and the loop is connected to the yolk sac by the vitelline duct. The primary intestinal loop can be described as having cranial and caudal limbs divided by the SMA.
The gut loop turns anticlockwise around its axis by a total of 270 degrees. It makes a 90 degree turn while it is outside the abdomen, and a further 180 degrees as it returns into the abdominal cavity. The turns produce the normal adult arrangement of the organs. As a result of these turns, the cranial limb (more proximal) lies posterior to the caudal limb. This mimics adult anatomy where the more proximal duodenum lies posterior to the transverse colon. The cranial limb ends up on the left side of the abdomen once it has returned into the cavity. The jejunum (the part of the small intestine after the duodenum) returns first, followed by the rest of the bowel. The caecum starts in the upper right of the abdomen.
Much later in development, the caecal bud (the early caecum) descends into the right iliac fossa (the lower right of the abdomen), forming the classical shape of the intestines in adults.
In about week 6 of development, the cells lining the gut multiply and temporarily block the lumen (the central channel of the gut). This has been described most clearly in the duodenum. Recanalisation is the process of reopening this lumen.
If recanalisation is unsuccessful, atresia (complete closure) or stenosis (narrowing) can occur and lead to complications. Failure of recanalisation is most likely to happen in the duodenum, where it is the classical explanation for duodenal atresia, although this explanation has been challenged. Other theories exist: some atresias are thought to follow a vascular accident, when part of the bowel loses its blood supply before birth.
It is important to note that failure of recanalisation is not implicated in pyloric stenosis (narrowing of the outlet of the stomach). In patients with pyloric stenosis, the lumen develops normally, but the muscle of the pylorus (the stomach outlet) thickens after birth, usually around six weeks of age, and narrows the outlet.
If the gut does not rotate a full 270 degrees anticlockwise or if the loop rotates the wrong way this can lead to an abnormal anatomical configuration. Known as malrotation, this condition can increase the risk of volvulus (twisting of the bowel on itself) and bowel obstruction. Midgut volvulus is a surgical emergency. It classically presents in a newborn or young infant with bilious (green) vomiting, but malrotation can also cause symptoms in older children and adults. Specific abnormalities include:
- Incomplete Rotation - if only one 90 degree turn occurs, all the colon ends up on the left side, instead of framing the small intestine on all sides.
- Reversed Rotation - if the midgut loop makes one 90 degree turn clockwise, the transverse colon ends up posterior to the duodenum.
There are two key abdominal wall defects in which bowel lies outside the abdomen at birth.
- Omphalocele - caused by persisting herniation. The intestine herniates through the abdominal wall but is covered in a layer of peritoneum. Intestinal function may be preserved, but feeding depends on the size of the defect and on associated anomalies (other birth defects). Omphalocele is associated with other birth defects and with genetic conditions such as trisomy 13, 18 or 21 (an extra copy of that chromosome) and Beckwith-Wiedemann syndrome. Overall it has a worse prognosis than gastroschisis.
- Gastroschisis - a full-thickness defect (a gap through every layer) in the abdominal wall, beside the umbilicus, where the wall does not form completely. The exact cause is not known. The intestine and other organs herniate through the abdominal wall but do not have any peritoneal covering. As a result, they are open to the amniotic fluid (the fluid around the baby in the womb). The fluid can damage them, so it often takes a while to establish feeds after surgery.
If the vitelline duct which connects the midgut with the yolk sac does not fully close up and disappear (obliterate), it can cause various pathologies.
- Vitelline Cysts/Fistulas - a fluid-filled remnant of the duct. If the duct stays open to both the gut and the skin, it forms a fistula (an abnormal connection).
- Meckel’s Diverticulum - an outpouching of the gut where the duct has not fully obliterated. It is not open to the skin and is a blind ending (a closed pouch). As it tethers the gut to the abdominal wall it can cause volvulus. It may also contain ectopic glandular tissue (gland tissue in the wrong place, most often stomach lining). Acid from ectopic stomach lining can cause bleeding, and the diverticulum can become inflamed, with pain imitating appendicitis.
- Meckel’s diverticulum is known for its rule of 2’s, a memory aid for how common it is and where it lies. It is found in 2% of the population, about 2 feet (roughly 60 cm) from the ileocaecal valve (the valve between the ileum and the caecum), is most often symptomatic in children under 2 years old, and affects males twice as often as females.
The hindgut is supplied by the inferior mesenteric artery (IMA) and lumbar splanchnic nerves (L1-2 nerve roots). The organs that develop from the hindgut therefore get their main blood supply from the IMA. Some also receive branches from other arteries. For example, the anal canal also receives median sacral and middle rectal branches. Pain from these organs is felt in the suprapubic region (the lower central abdomen, above the pubic bone; L1-2 dermatomes). Organs that develop from the hindgut are:
- Distal 1/3 of the transverse colon
- Descending colon
- Sigmoid colon
- Rectum
- Structures of cloacal origin:
- Upper 2/3rds of the anal canal (superior to the pectinate line, the line in the anal canal where the lining changes)
- Bladder
- Urethra
The hindgut during development is covered by the cloacal membrane. Its end opens into the cloaca (the shared end chamber of the gut and urinary tract), a structure that communicates with the developing genitourinary tract (the urinary and reproductive organs). The cloacal membrane is an interesting area embryologically as it is one of the few areas where ectoderm (the outer embryonic layer) meets endoderm without any dividing mesoderm.
Differentiation of the cloaca into the gastrointestinal and genitourinary systems occurs when the urorectal septum descends to divide the two. The cloacal membrane then ruptures, giving a separate outlet for the hindgut (the anus) and for the urinary tract.
The anal canal is divided into sections that look different under the microscope (histologically distinct) by the pectinate line. The pectinate line is the point of demarcation at which the ectoderm and endoderm met during development. The two sections have separate arterial, venous, lymphatic and nervous supplies.
Above the pectinate line, the anal canal is developed from the endoderm. As a result, it is supplied like the rest of the hindgut. Its arterial supply is mainly the superior rectal artery, a branch of the inferior mesenteric artery. Its nerve supply is autonomic (visceral): sympathetic fibres from the lumbar splanchnic nerves (L1-2) and parasympathetic fibres from the pelvic splanchnic nerves (roots S2, S3 and S4). The internal anal sphincter (smooth muscle, not under voluntary control) has the same autonomic supply. The external anal sphincter (skeletal muscle, under voluntary control) is supplied instead by the inferior anal nerve, a branch of the pudendal nerve. This part of the anal canal is lined with columnar epithelium (tall, column-shaped cells) and is drained mainly by the internal iliac lymph nodes. Because it has only visceral nerve supply, only stretch can be sensed in this region, a visceral sensation.
Below the pectinate line, the anal canal is developed from the ectoderm. As a result of this differing embryological origin it has a separate neurovascular supply and lymphatics. The canal at this point is supplied by the pudendal artery and the pudendal nerve (spinal nerve root S2, S3 and S4). As this area is ectoderm derived, somatic sensations of temperature, touch and pain can be detected. It is lined with stratified squamous epithelium (flat cells in layers) and drains to the superficial inguinal (groin) lymph nodes.
If there are issues in septation (division by a septum, a thin dividing wall) of the cloaca or rupture of the membrane this can cause abnormalities in the adult anatomy.
- Imperforate Anus (an anus with no opening, also called anal atresia; it is one type of anorectal malformation, a birth defect of the anus and rectum) - in the simplest form, the anal part of the cloacal membrane does not rupture and so persists meaning there is no outlet from the gastrointestinal tract and therefore no anus. Many cases are more complex, with the bowel ending in an abnormal connection (a fistula). This will need surgical repair.
- Fistulae - if there are holes in the septum there can be abnormal connections between the anus and the bladder as they are not properly separated in development.
- Anorectal Agenesis - a severe defect where there is no development of the anus or rectum rather than simply no outlet.
Development explains the peritoneal relationships and congenital abnormalities described here. Continue with Abdominal Wall and Inguinal Canal for the adult layers, inguinal canal and the anatomical routes taken by direct and indirect inguinal hernias.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 15552


