

Next Lesson - Haemoglobinopathies
Core
Iron is an element that is used in the body for a variety of functions. Its most important use is for carrying oxygen as a component of haemoglobin (the oxygen-carrying pigment in red blood cells) and myoglobin (the oxygen-carrying pigment in muscle cells). It is also a key co-factor in many enzymes involved in detoxification and the Krebs cycle.
In the body, iron is mostly found in one of two oxidation states: ferrous (Fe2+) and ferric (Fe3+) iron.
Iron is taken in through the diet in two forms: haem and non-haem. Haem iron is in the Fe2+ form and is found in meat such as beef, liver and chicken. Non-haem iron is a mixture of Fe2+ and Fe3+ and is found in raisins, oats, spinach and fortified cereals. Iron must be in the ferrous form to be absorbed in the duodenum and upper jejunum.
Iron absorption is inhibited by some chemicals found in everyday food items, e.g. tannins in tea and red wine, or phytates found in chapattis. These chemicals work by binding non-haem iron in the intestine so that it cannot be absorbed. Note that antacids (medicines that reduce stomach acid) can also reduce iron absorption. On the other hand, vitamin C found in citrus fruits can help increase the absorption of iron from food by reducing ferric to ferrous iron. This is why patients on iron supplements are often encouraged to drink orange juice with their tablets. However, in a trial in which 440 patients were randomly given iron tablets with or without vitamin C, the vitamin C did not improve the response to treatment, and the British Society of Gastroenterology (2021) does not recommend taking it with iron tablets.
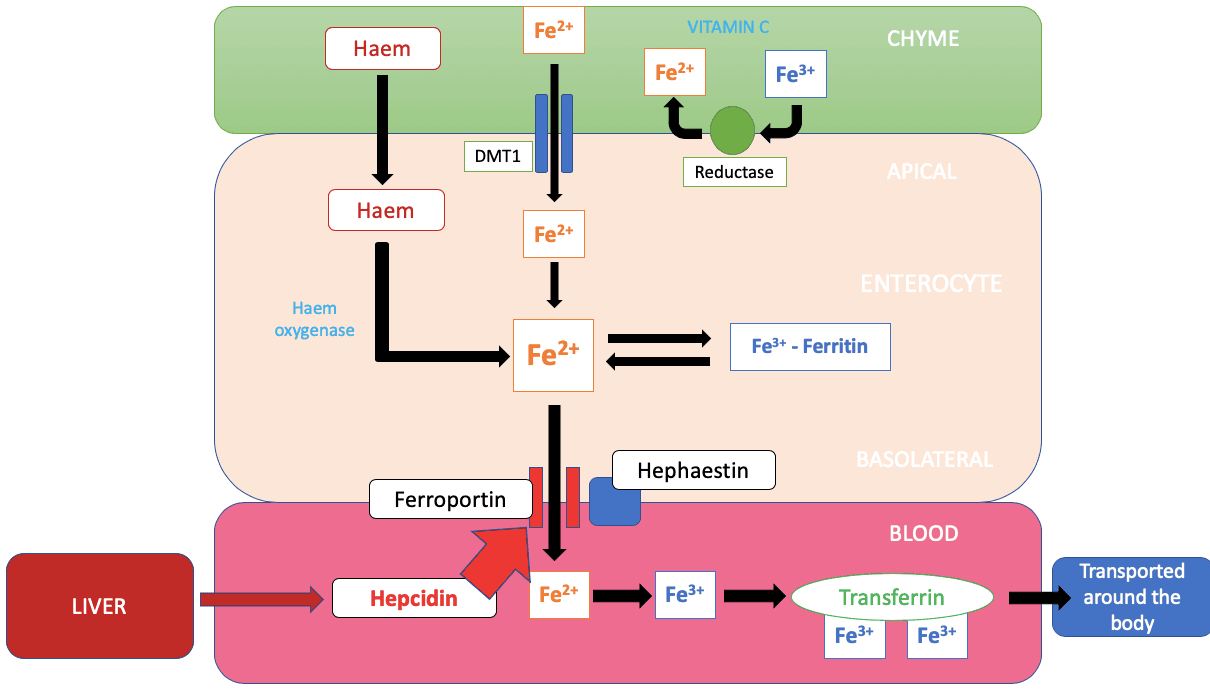
Diagram: Shows the absorption of non-haem iron in the duodenum and jejunum. Fe2+ and haem iron can be absorbed easily, while Fe3+ has to be reduced before being absorbed. Iron can be stored in the enterocytes (the cells lining the bowel) as ferritin (the main iron storage protein). It can also be released into the blood bound to transferrin (the main iron transport protein in the blood).
SimpleMed Original by Dr. Tom Bradley
The conversion into the ferrous form of iron happens via the reductase enzyme on the apical surface (the side facing into the bowel) of the enterocytes. The Fe2+ ions are taken up by a transporter protein called DMT1 (divalent metal transporter 1) into the enterocyte. Haem iron is taken up by a separate process that is still not fully understood.
Once the Fe2+ is inside the enterocyte it has two possible fates. It can be stored as ferritin (a soluble complex of iron and protein), in which the iron is in the form of Fe3+. Alternatively, it can be transported into the bloodstream by the protein ferroportin. As it leaves the enterocyte, the Fe2+ needs to be oxidised back into ferric (Fe3+) iron by an enzyme called hephaestin. Now in the correct form, the ferric iron is bound by transferrin and is carried around the body to the sites where it is needed. The main site is the bone marrow, where erythropoiesis (the production of red blood cells) takes place. (See haematopoiesis and the spleen article).
When the Fe3+ iron bound to transferrin reaches the target cell, the complex binds to a transferrin receptor on the cell surface membrane. The cell then takes it in by receptor-mediated endocytosis, in which the membrane folds inwards to enclose the complex in a small bubble called an endosome. The Fe3+ is reduced to Fe2+ inside the endosome. Following this, the Fe2+ is transported into the cytoplasm through the same DMT1 transporter as on the enterocytes in the gut. Once in the cytoplasm, mitochondria can use it to produce cytochrome enzymes (iron-containing proteins that carry electrons when cells make energy). Unused iron is stored in cells inside the protein ferritin, in the Fe3+ form. Ferritin is able to release iron in a controlled manner when needed, after which the iron can leave the cell as Fe2+ via the transporter ferroportin.
Iron is stored in two different forms. The first is the ferritin mentioned above, which is soluble, usable and found within cells. Iron can enter and leave ferritin through pores in the iron-protein complex. The second form is the insoluble haemosiderin, which consists of ferritin complexes clumped together and often accumulates in macrophages in the liver, bone marrow and spleen.
Most of the iron in the body is obtained from recycling old erythrocytes (red blood cells), which explains the limited requirement of iron in our diet. The old erythrocytes are engulfed (phagocytosed) by macrophages in the reticuloendothelial system (the network of macrophages in the liver, spleen and bone marrow). The macrophages then return the iron to the blood via transferrin, or store it within the macrophage as ferritin.
Iron absorption needs to be regulated carefully as both a deficiency and an excess of iron can be harmful to the body. The balance is maintained through regulation of absorption, bodily stores of iron and the rate of erythropoiesis. Note there is no active mechanism for the excretion of iron from the body. The enterocytes also sense the body's iron levels and adjust how much of the iron transport proteins (such as DMT1 and ferroportin) they make.
Absorption of iron is regulated by hepcidin, a small protein made by the liver. Hepcidin binds to ferroportin and causes the ferroportin to be broken down. This blocks iron from leaving the enterocyte and entering the blood. In laboratory studies it also lowers the amount of DMT1 protein in enterocytes. Overall, hepcidin inhibits dietary iron from entering the bloodstream. The synthesis of hepcidin is increased during iron overload to reduce the levels taken in. Conversely, hepcidin synthesis is decreased when there is an increased rate of erythropoiesis. This enables the bone marrow to be supplied with enough iron to produce new erythrocytes.
Excess dietary absorption of iron can occur in conditions such as hereditary haemochromatosis. This is usually an autosomal recessive condition (the gene is not on a sex chromosome, and two faulty copies, one from each parent, are needed). It causes accumulation of iron in tissues and organs such as the liver, heart and endocrine glands. This accumulation of iron can promote the formation of reactive oxygen species (highly reactive molecules). This happens through the Fenton reaction, a chemical reaction in which iron acts as a catalyst to produce free radicals (unstable molecules that react readily with other molecules). These free radicals can cause damage to proteins and DNA within cells. Most cases are caused by a mutation in the HFE gene (the gene that codes for the HFE protein), and this protein normally plays a role in regulating hepcidin and iron absorption. Mutations impair this regulation, leading to inappropriately increased intestinal iron absorption and progressive iron accumulation in tissues. Rarer forms are caused by mutations in other genes that help to control iron levels. In some people the accumulation of iron makes the skin look tanned and causes secondary conditions such as cardiomyopathy (disease of the heart muscle) and diabetes mellitus. These are later features: early symptoms are more often tiredness and joint pain, and some people have no symptoms. The combination of tanned skin and diabetes gave the condition its older name, bronze diabetes.
Hereditary haemochromatosis is suspected when blood tests show a raised transferrin saturation (how much of the transferrin is carrying iron) and ferritin, and genetic testing for HFE can confirm it. The main treatment is regular venesection (removing blood, in a similar way to giving blood), which removes iron from the body. Early treatment can prevent complications such as cirrhosis (scarring of the liver) and diabetes. Chelation therapy (medicines that bind iron so that it can be removed from the body) is used only if regular venesection is not possible.
Another way in which iron can accumulate is transfusion associated haemosiderosis. This is a condition that occurs when a patient is given repeated blood transfusions. It is seen in transfusion dependent anaemias, such as thalassaemia major (an inherited condition in which too little normal haemoglobin is made) and in some people with sickle cell disease. Each unit of transfused blood contains roughly 200 to 250 mg of iron, far more than the 1 to 2 mg the body can lose in a day. With repeated transfusions, iron therefore builds up in the body, putting the patient at risk of the same secondary conditions, such as cardiomyopathy and diabetes. Haemosiderin deposition can lead to characteristic slate grey colouring of the skin. Iron chelating agents are medicines that bind iron so that it can be removed from the body. They are used to reduce iron overload in transfusion dependent patients. Examples are desferrioxamine (given by a slow infusion under the skin) and the oral drugs deferiprone and deferasirox. Chelation therapy is the mainstay of treatment for transfusional iron overload. Therapeutic phlebotomy (removing blood) would remove red cells and worsen the anaemia, so phlebotomy is generally not appropriate in patients who are anaemic. Hereditary haemochromatosis differs in this respect, because regular venesection is its main treatment.
Iron deficiency is a very common disorder and the most common cause of anaemia. It is a sign of an underlying cause rather than a diagnosis in itself, so the cause must always be sought. In men and postmenopausal women, newly diagnosed iron deficiency anaemia needs investigation of the gastrointestinal (GI) tract. About a third of these patients have an underlying abnormality, most often in the GI tract (for example a bleeding cancer). There are many possible causes of iron deficiency, which fall into four groups:
- Insufficient intake or absorption of iron - this can be due to too little iron in the diet (for example a vegan or vegetarian diet, although a poor diet is rarely the only cause in adults). Absorption of dietary iron can also be poor, for example in Crohn’s disease (a long-term inflammatory bowel condition) or after a gastrectomy (the surgical removal of part or all of the stomach).
- Increased requirements for iron - this could be during pregnancy or during rapid growth in puberty.
- Bleeding - bleeding can result in loss of iron, e.g. from a gastric ulcer or menorrhagia (heavy periods).
- Anaemia of chronic disease - this is a functional iron deficiency. Iron is present in the body but is locked away in stores. Inflammation from long-term conditions stimulates the production of hepcidin, which decreases the amount of iron available to make red blood cells. Ferritin is therefore often normal or raised.
Groups at higher risk of iron deficiency include menorrhagic (heavily menstruating) women and infants who are being weaned off the breast onto solid foods.
Most of the signs and symptoms of iron deficiency relate to the decreased ability to carry oxygen around the body. See anaemia article for the presentation of anaemias. Some more specific changes can occur with chronic iron deficiency. These are epithelial changes (changes to the skin, nails and the lining of the mouth), such as koilonychia (spoon-shaped nails) and angular cheilitis (sores at the corners of the mouth):
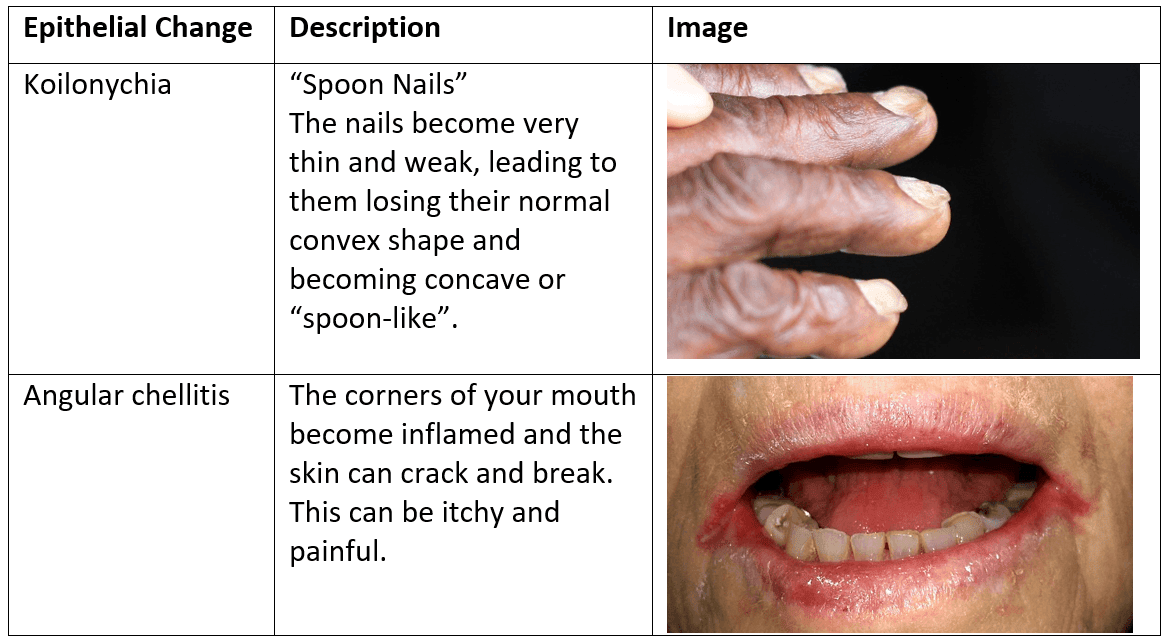
Table: Shows the different epithelial changes associated with iron deficiency anaemia
Creative commons source by "koilonychia" CHeitz [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)] - 1st image
Creative commons source by Matthew Ferguson 57 [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)] - 2nd image
Iron deficiency anaemia is diagnosed from a full blood count (FBC) and a serum ferritin level: a ferritin below 30 micrograms/L confirms iron deficiency. A blood film (a sample of blood examined under a microscope) can support the diagnosis but is not essential. The MCV (mean cell volume, the average size of the red cells) and MCH (mean corpuscular haemoglobin, the average amount of haemoglobin in each red cell) are typically low. Transferrin saturation (a measure of how much transferrin is bound to iron), plasma ferritin and plasma iron levels are also typically low. An elevated platelet count and TIBC (total iron-binding capacity) may also be seen. Note that iron deficiency can still be present when ferritin is normal or raised. This is because ferritin levels increase in infections, inflammation and other co-morbidities (long-term conditions that exist alongside the main illness). On a blood film you would see microcytic (small) and hypochromic (pale) cells with evidence of anisopoikilocytosis (irregularly sized and shaped cells). (See full blood count and blood films article for definitions of these terms).
Oral iron replacement, such as ferrous sulfate or ferrous fumarate (two iron salts), is usually given alongside dietary advice. One tablet once daily is advised. A ferrous sulfate 200 mg tablet, for example, contains 65 mg of elemental iron (the iron itself, rather than the whole salt). Treatment is continued for about 3 months after the haemoglobin has returned to normal, so that the iron stores are replenished. If oral iron is not tolerated, the dose can be reduced to one tablet on alternate days, or another oral preparation can be tried. Parenteral (intravenous) iron is considered if oral iron is unsuitable (contraindicated), ineffective or not tolerated. Treatment aims to increase the body’s iron stores back to a normal level. Transfusions are only given in the most severe cases of anaemia.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Bethany Turner and Dr. Marcus Judge
- 13603

