

Next Lesson - Pituitary Disorders
Core
The hypothalamus and pituitary gland form a complex functional unit, called the hypothalamic-pituitary axis (HPA in the title of this article; not to be confused with the hypothalamic-pituitary-adrenal axis, which has the same abbreviation), that serves as the major link between the endocrine and nervous systems. The pituitary gland can be found within the sella turcica (a socket of bone on the base of the skull, meaning ‘Turkish saddle’), with the hypothalamus sitting above it. A network of capillaries called the hypophyseal portal system links the hypothalamus to the anterior pituitary. Hypothalamic hormones enter these blood vessels and are carried directly to the anterior pituitary. The functions of the hypothalamic-pituitary axis include body growth, reproduction, adrenal gland function, water homeostasis, lactation, thyroid gland function, and puberty.
The pituitary gland consists of two parts: the anterior and posterior pituitary glands. The posterior pituitary gland itself is not technically a gland as it does not produce the hormones that it secretes. The hormones secreted by the posterior pituitary are produced by the hypothalamus.
The pituitary glands have distinct embryological origins. The anterior arises from an evagination of oral ectoderm (an upward pouch of the lining of the primitive mouth, called Rathke’s pouch), and the posterior from neuroectoderm (primitive brain tissue).
The posterior pituitary gland is physically connected to the hypothalamus by the pituitary stalk, which begins embryologically as the infundibulum (a funnel-shaped downgrowth of the hypothalamus). The posterior pituitary gland secretes two hormones:
- Oxytocin, involved in the milk let-down reflex during breastfeeding and uterine contractions during birth.
- Antidiuretic hormone (ADH), which is involved in the reabsorption of water in the nephron of the kidney, at the distal convoluted tubule and collecting duct.
Both of these hormones are produced by neurosecretory cells (nerve cells that release hormones) in the supraoptic and paraventricular nuclei of the hypothalamus (two clusters of nerve cell bodies). They are then transported down nerve cell axons to the posterior pituitary, where they are stored. They are released from the posterior pituitary into the general circulation when stimulated. The hormones then travel round the circulation to act at distant targets.
The other hormones synthesised in the hypothalamus are transported down axons and released at the median eminence (a part of the hypothalamus) into the hypophyseal portal system. When released, these hormones act on target endocrine cells in the anterior pituitary to either increase or decrease the release of their hormones.
Endocrine cells of the anterior pituitary secrete a variety of hormones into the bloodstream to act on distant target cells. Anterior pituitary hormones can also affect the cells that released them and neighbouring cells (meaning the anterior pituitary also has autocrine and paracrine functions).
Tropic hormones are hormones that affect the release of secondary hormones in the target tissue. Many hypothalamic hormones regulate anterior pituitary hormone release, although some act mainly as inhibitory regulators rather than tropic hormones. Six hormones produced in the hypothalamus have direct effects on the release of anterior pituitary hormones. Four are releasing hormones, which stimulate release: thyrotropin releasing hormone (TRH), corticotropin releasing hormone (CRH), gonadotropin releasing hormone (GnRH) and growth hormone releasing hormone (GHRH). Two are inhibiting hormones, which suppress release: somatostatin (also called growth hormone inhibiting hormone, GHIH) and dopamine (also called prolactin release-inhibiting hormone). The pathways to produce hypothalamic and anterior pituitary hormones are often regulated by negative feedback, and many of these pathways will be discussed in other articles in the endocrinology series.

Diagram: Shows the different hormones released from the hypothalamus and which hormones are released from the pituitary glands in response
SimpleMed original by Dr. Jenny Hubball
The image above gives an overview of the hormones released from the hypothalamus and anterior pituitary, and what they do. Note these additional points:
- Prolactin (the hormone that stimulates milk production) is mainly controlled by its inhibition and not its stimulation. Dopamine from the hypothalamus continually suppresses prolactin release. The stimulatory effect of thyrotropin releasing hormone (TRH) is very minor. Prolactin release rises during pregnancy (oestrogen increases it) and when a baby suckles during breastfeeding.
- Prolactin Release-Inhibiting Hormone, or dopamine, can act as both a hormone and a neurotransmitter.
- Thyroid stimulating hormone (TSH) causes release of the thyroid hormones T3 (triiodothyronine) and T4 (thyroxine), and these are the hormones which have the metabolic functions.
- A good example of a hormone secreted by the anterior pituitary is growth hormone, which will now be discussed in further detail below.
The main function of growth hormone is somatic growth (growth of the body). Growth hormone, together with thyroid hormone, is the main hormonal regulator of growth in childhood (from about 3 years of age until puberty). In the first year of life, nutrition is the main influence on growth and growth hormone plays a smaller role. Growth is also influenced by factors such as genetics, nutrition, and environment. Some other hormones also influence growth. They are listed below.

Table: Shows the hormones other than growth hormone that have an effect on somatic growth
SimpleMed original by Dr. Jenny Hubball
Growth hormone is a 191 amino acid protein hormone that has a signal peptide (a short leader chain of amino acids) which must be cleaved (cut off) before proper folding of the hormone can occur. Its growth-promoting effects are mainly exerted indirectly via insulin-like growth factors (IGFs), but it can also have direct effects on the body. In response to growth hormone, liver cells (the main source of IGF1 in the blood) and many other tissues, including skeletal muscle, can produce and secrete IGFs.
Growth hormone receptors are cytokine receptors (a family of receptors with no enzyme activity of their own) that signal via associated Janus kinases (JAKs, enzymes inside the cell that switch other proteins on). Once growth hormone has attached to the receptors on the cells, it causes the cells to activate Janus kinases, so the kinases are phosphorylated (have a phosphate group added, which switches them on). This in turn causes the activation of signalling pathways causing transcription factor activation (transcription factors are proteins that switch genes on) and IGF production.
There are two IGFs that exist in mammals:
- IGF1 - the most important IGF, a major growth factor in children and adults.
- IGF2 - mainly involved in fetal growth.
Binding proteins modulate the availability of IGFs. The IGFs can act as hormones in the blood (endocrine), on the cell that made them (autocrine) and on neighbouring cells (paracrine). The IGFs act through IGF receptors to modulate hypertrophy, hyperplasia, and an increase in protein synthesis rate, with insulin-like metabolic effects in adipose tissue (body fat). Growth hormone itself also has direct metabolic effects: it breaks down fat (lipolysis) and raises blood glucose (a diabetogenic effect).
Growth hormone and IGFs have different functions in children and adults:

Table: Shows the effects of growth hormone on the body
SimpleMed original by Dr. Jenny Hubball
The secretion of growth hormone is regulated by growth hormone releasing hormone (GHRH) and growth hormone inhibiting hormone (GHIH or somatostatin) released from the hypothalamus. These two hormones are in turn regulated by the central nervous system, which controls secretion through inputs to the hypothalamus. Growth hormone secretion can also be regulated by short loop and long loop negative feedback.
- Long Loop: The production of IGFs inhibits the release of GHRH from the hypothalamus, and stimulates the release of GHIH from the hypothalamus. Together, these reduce the release of growth hormone from the anterior pituitary.
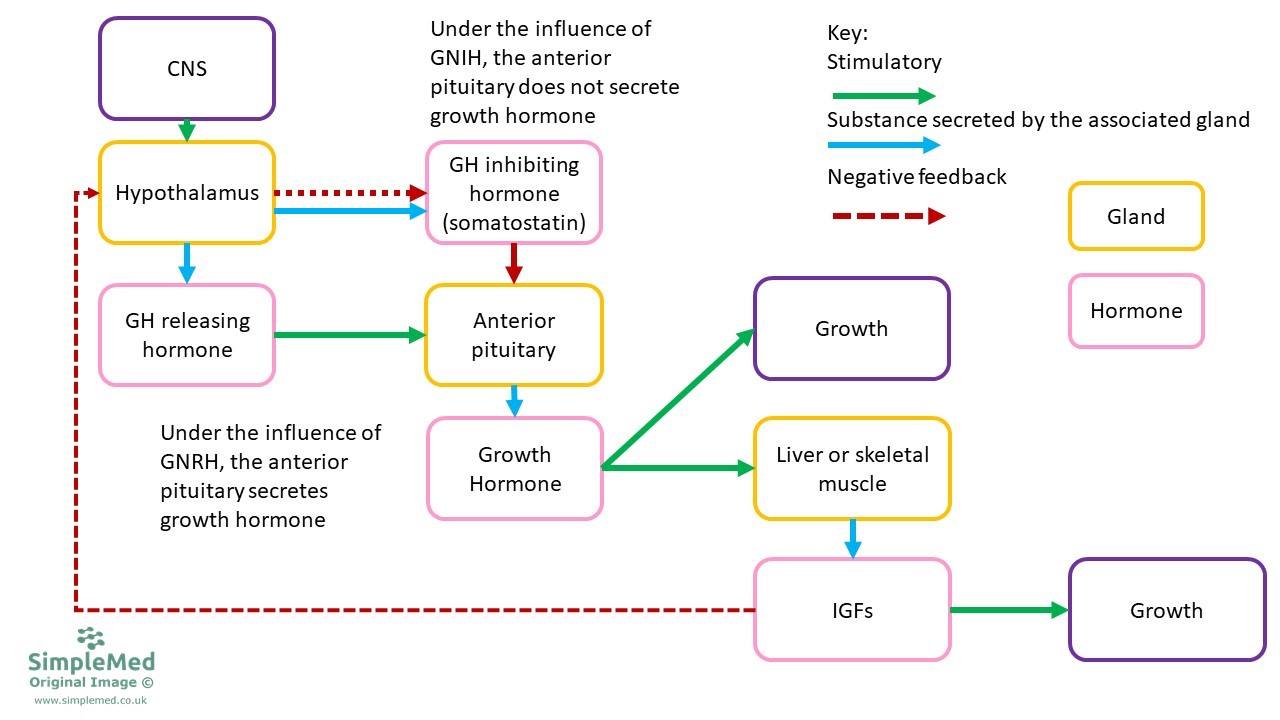
Diagram: Shows the long negative feedback loop controlling growth hormone release. Note: in this diagram, GNIH should read GHIH (growth hormone inhibiting hormone, also called somatostatin) and GNRH should read GHRH (growth hormone releasing hormone). GnRH is a different hormone, gonadotropin releasing hormone.
SimpleMed original by Dr. Jenny Hubball
- Short Loop: The production of growth hormone stimulates the release of GHIH from the hypothalamus, inhibiting the release of growth hormone from the anterior pituitary.

Diagram: Shows the short negative feedback loop controlling growth hormone release
SimpleMed original by Dr. Jenny Hubball
Many different factors act through the central nervous system to either increase or decrease growth hormone secretion. These factors can be seen below.

Table: Shows the different factors that affect the secretion of growth hormone
SimpleMed original by Dr. Jenny Hubball
Pituitary dwarfism is a condition caused by growth hormone deficiency in childhood. It is a proportionate type of dwarfism: the arms and legs are the expected size compared with the rest of the body. This condition responds to growth hormone therapy (injections of somatropin, started and monitored by a paediatrician with specialist expertise). Treatment usually continues until the child stops growing or reaches their target height. Signs of pituitary dwarfism include the following. They are not specific, because short stature has many other causes (for example Turner syndrome), so a specialist assesses the cause:
- Growth rate slower than expected for age.
- Height below the 3rd percentile on standard growth charts.
- Absent or delayed sexual development (puberty) during the teenage years.
Gigantism is a condition caused by growth hormone excess in childhood, where the excess hormone encourages growth of the whole body. It is extremely rare and is usually caused by a pituitary adenoma (a non-cancerous tumour of the pituitary gland that makes too much growth hormone).
Acromegaly is a condition caused by growth hormone excess in adulthood. In this condition, the patient has large extremities (e.g. hands, feet, lower jaw), as the epiphyseal growth plates of the bones (the areas near the ends of long bones where lengthening occurs) have already fused, so growth hormone cannot increase somatic height. The face also becomes coarse (for example, a wide nose and rounded face). Acromegaly is also usually caused by a pituitary adenoma.

Diagram: Shows the facial features of acromegaly
Creative commons source by Philippe Chanson and Sylvie Salenave [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
Edited by:Dr. Maddie Swannack
- 13838

