

Next Lesson - Enzymes and Regulation of Protein Function
Core
In this article, we are going to discuss the function of two important proteins that exist within the human body: haemoglobin and myoglobin.
Haemoglobin is the well-known haem protein (a protein that contains haem, an iron-containing group). It is found in red blood cells (RBCs) and carries oxygen from the lungs to the tissues. It also carries some of the carbon dioxide from the tissues back to the lungs. Myoglobin is found mainly in muscle tissue and serves as an oxygen store inside muscle cells (an intracellular storage site).
Myoglobin is a haem protein and is a monomeric protein (single polypeptide chain). The protein molecule has a globular structure (compact and rounded). It is made of eight separate right-handed alpha helices (coiled stretches of the polypeptide chain) that are connected by short non-helical regions.
Each myoglobin molecule contains a haem group containing an iron ion (Fe2+), which binds one oxygen molecule. When a myoglobin molecule is saturated (its haem group is carrying an oxygen molecule), it can be called oxymyoglobin. When it is unsaturated (its haem group is empty), it can be called deoxymyoglobin.

Image - The structure of myoglobin with the haem group surrounded by the rest of the protein
Public Domain source by AzaToth
Myoglobin is found mainly in muscle tissues and acts as a storage molecule for oxygen. Because of its high affinity for oxygen, it loads oxygen readily in normal conditions. It releases this oxygen mainly when the oxygen level in the muscle falls, for example during strenuous exercise. The oxygen released from myoglobin can then allow the muscle cells to carry on generating energy to contract.
Each myoglobin molecule has only one haem group, so it binds only one oxygen molecule. Binding is not cooperative (each oxygen molecule binds independently of the others). As a result, plotting saturation against the partial pressure of oxygen gives a hyperbolic curve for myoglobin. Saturation is the percentage of binding sites that are holding oxygen. Partial pressure is the pressure that oxygen alone exerts in a mixture of gases. A hyperbolic curve rises steeply and then flattens off. Myoglobin’s high affinity means that the curve rises steeply at low partial pressures of oxygen.

Diagram - Graph of the hyperbolic curve when plotting the saturation of myoglobin against increasing partial pressures of oxygen. A low P50 (the low partial pressure of oxygen needed to give 50% saturation) shows that myoglobin has a high affinity for oxygen
SimpleMed original by Dr. Peter Parkinson
Haemoglobin is a tetrameric haem protein (four polypeptide chains) found in red blood cells (RBCs) and carries oxygen from the lungs to the tissues. It also carries some of the carbon dioxide from the tissues back to the lungs, to be breathed out.
Haemoglobin has a globular structure, with adult haemoglobin (HbA) being composed of two alpha polypeptide chains and two beta polypeptide chains forming a molecule of four subunits (each subunit is one polypeptide chain).

Image - The structure of haemoglobin
Creative commons source by Zephyris [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Within each subunit (each polypeptide chain) there is a prosthetic haem group (a non-protein part permanently attached to the protein) containing an Fe2+, which binds one oxygen molecule. This means that each haemoglobin molecule can bind with a maximum of four oxygen molecules.
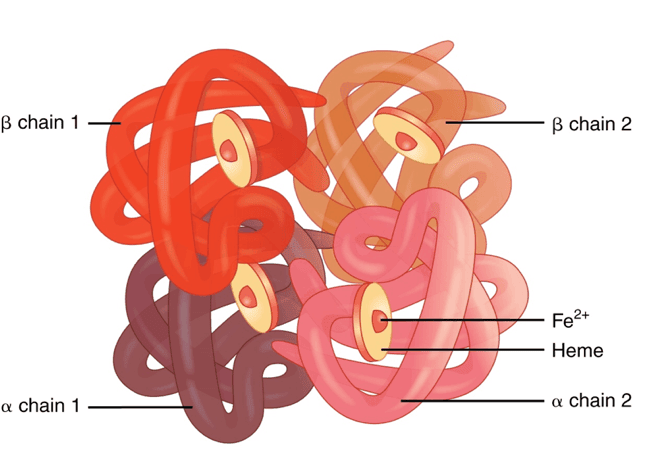
Diagram - The different chains that make up haemoglobin along with the haem groups
Creative commons source by OpenStax College, edited by Dr. Peter Parkinson [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
When haemoglobin is bound to oxygen it is called oxyhaemoglobin, and when it is not bound to oxygen it is called deoxyhaemoglobin. Haemoglobin can exist in two states. The T (tense) state has low affinity for oxygen and is the usual form when no oxygen is bound. The R (relaxed) state has high affinity for oxygen and is the usual form when oxygen is bound. When Fe2+ binds with an oxygen molecule, this promotes the stabilisation of the R state. This leads to a change in the conformation (three-dimensional shape) of haemoglobin.
The oxygen dissociation curve is a graph of the saturation of haemoglobin against the partial pressure of oxygen. For haemoglobin, this curve is sigmoidal (S-shaped) because of cooperative binding of oxygen. In cooperative binding, each oxygen molecule that binds makes it easier for the next one to bind. At low partial pressures of oxygen, haemoglobin is mostly in the T state, which has low affinity, so it is difficult for the first oxygen molecule to bind. After the first molecule of oxygen binds, the shape of haemoglobin changes (a conformational change). This makes it easier for the next oxygen molecules to bind.

Diagram - Graph showing the oxygen dissociation curves for haemoglobin and myoglobin
SimpleMed original by Dr. Peter Parkinson
The sigmoidal shape of the oxygen dissociation curve of haemoglobin shows that oxygen can be transported around the body efficiently from the lungs to the tissues. When in the lungs, where the partial pressure of oxygen is high, haemoglobin molecules will be near 100% saturated due to the high affinity for oxygen at this partial pressure. As the partial pressure of oxygen decreases, the oxygen molecules are unloaded as haemoglobin’s affinity for oxygen decreases. This process occurs at peripheral tissues and allows for the oxygen to be offloaded to the tissues that have the highest requirement.
The P50 (partial pressure of oxygen to give 50% saturation) of haemoglobin is higher than that of myoglobin. A higher P50 means a lower affinity, so haemoglobin has a lower affinity for oxygen than myoglobin. This difference suits the job that each protein does. Myoglobin holds on to its oxygen until the oxygen level in the muscle is very low. Haemoglobin unloads its oxygen at a higher partial pressure than myoglobin does, which allows the tissues to continue to respire. This also means that haemoglobin will give up oxygen to myoglobin.

Diagram - Graph showing how the partial pressure of oxygen required for 50% saturation differs between myoglobin and haemoglobin
SimpleMed original by Dr. Peter Parkinson
Several factors affect how haemoglobin binds oxygen. They change haemoglobin’s affinity for oxygen and shift the position of the oxygen dissociation curve.
2,3-Bisphosphoglycerate (2,3-BPG)
2,3-BPG is made from 1,3-bisphosphoglycerate (1,3-BPG), an intermediate of glycolysis (the pathway that breaks down glucose). This reaction is a side branch of glycolysis and is catalysed by the enzyme BPG mutase (bisphosphoglycerate mutase).
2,3-BPG acts on haemoglobin as an allosteric effector (a molecule that binds away from the oxygen-binding site and changes how the protein behaves). It binds to the positively charged amino acid residues (the individual amino acids in the chain) in the central cavity between the two beta chains of the haemoglobin molecule. Put simply, in the presence of 2,3-BPG, haemoglobin stays in the T state. As a result, 2,3-BPG lowers the affinity of haemoglobin for oxygen. The overall effect is that 2,3-BPG shifts the oxygen dissociation curve to the right. This increases the percentage of oxygen molecules unloaded at peripheral tissues.
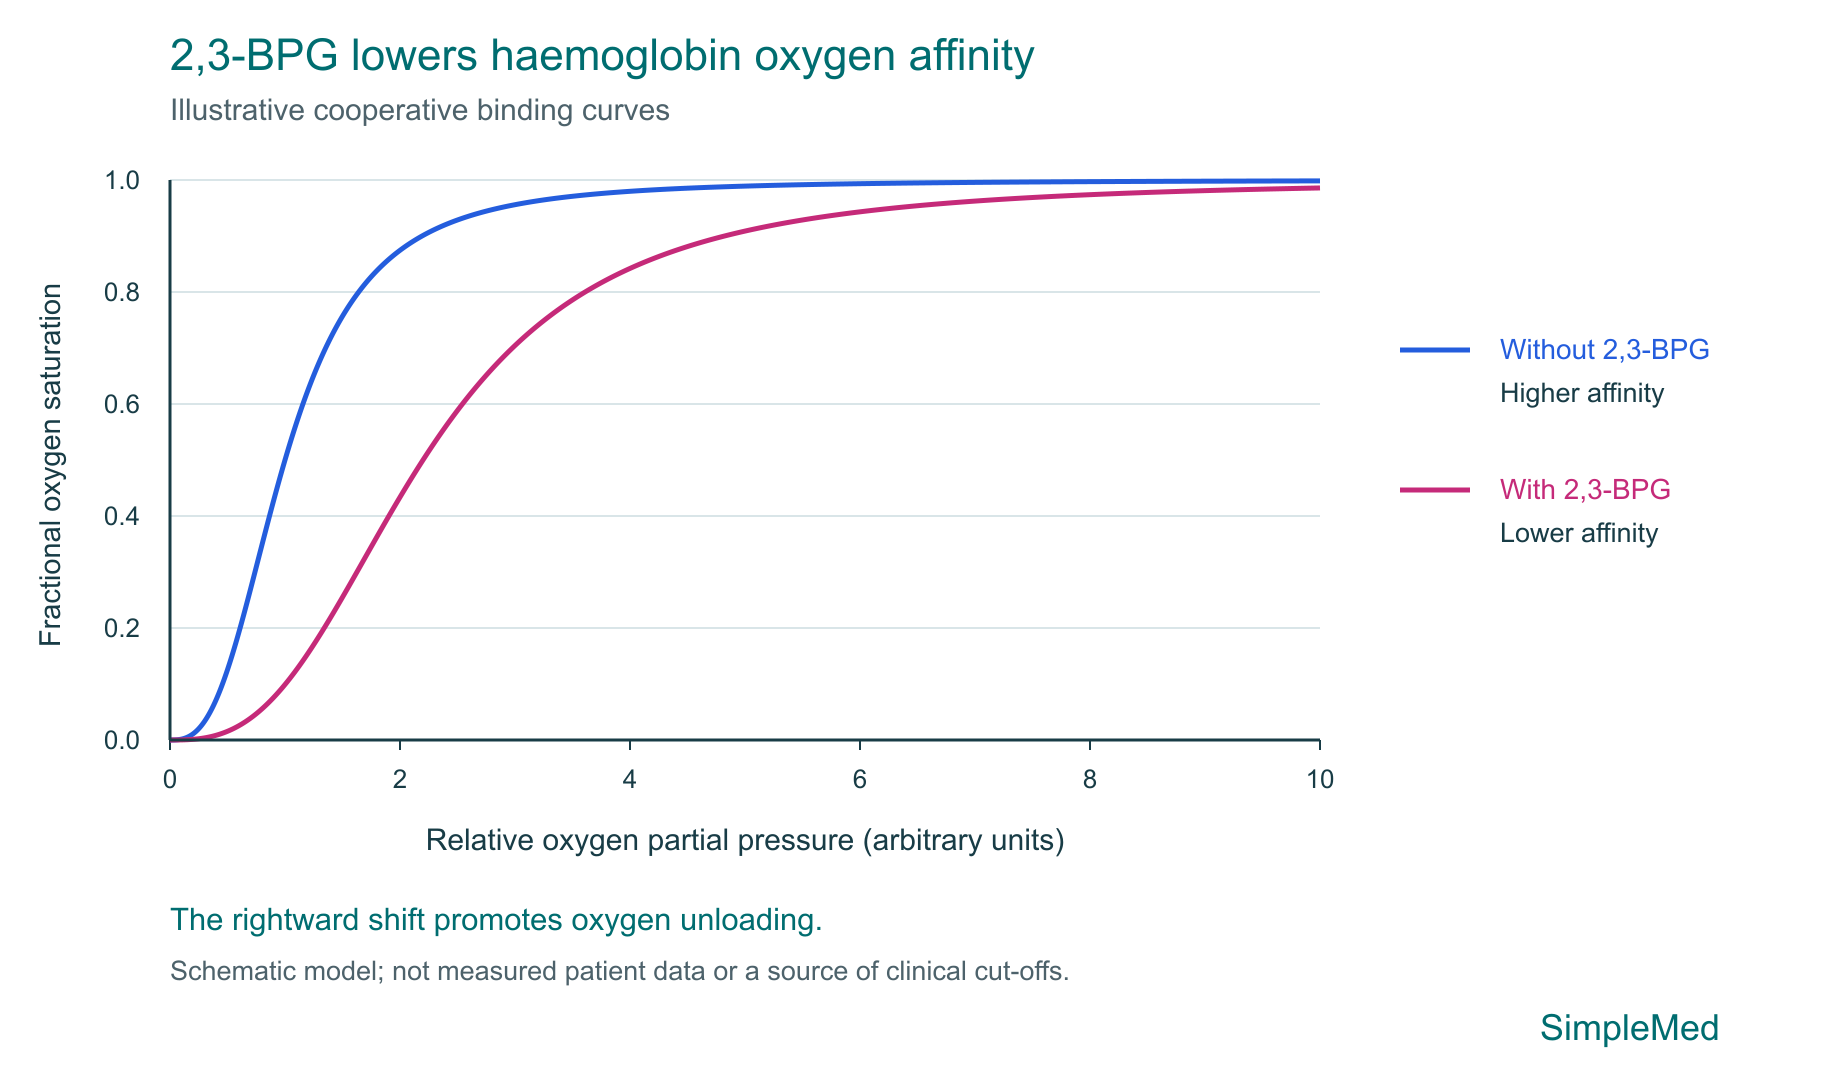
Diagram - Illustrative cooperative oxygen-binding curves. 2,3-BPG lowers haemoglobin oxygen affinity, shifting the curve to the right and promoting oxygen unloading. Pressure is shown in arbitrary relative units; this schematic is not measured patient data and provides no clinical cut-offs.
New illustrative schematic drawn for SimpleMed (2026); independently generated cooperative binding curves in arbitrary units.
There are situations where a person may have higher than expected 2,3-BPG levels because of low oxygen concentrations in the tissues. These include people who have acclimatised (adapted over time) to living at higher altitudes and people with congestive heart failure (CHF). In CHF, the RBCs are stimulated to make more 2,3-BPG. Changes in pH and oxygen levels alter the activity of the enzymes that make and break down 2,3-BPG. At high altitudes there is less oxygen, so the increased level of 2,3-BPG means the RBCs can release more oxygen at lower partial pressures of oxygen.
Carbon Dioxide and Hydrogen Ions
Carbon dioxide and hydrogen ions can both bind to haemoglobin. By binding, they lower haemoglobin’s affinity for oxygen therefore increasing the unloading of oxygen molecules.
There is a relationship between the pH of the blood and the partial pressure of carbon dioxide, which is mediated by the enzyme carbonic anhydrase. This enzyme combines carbon dioxide with water to form carbonic acid, which then splits (dissociates) into bicarbonate and a H+ ion. The extra H+ lowers the pH of the surrounding blood.
In actively respiring tissues, there is a large amount of carbon dioxide produced through increased metabolism. As a result of the action of carbonic anhydrase, this leads to a lowered pH of the local blood. This causes haemoglobin’s affinity for oxygen to decrease, hence a greater amount of oxygen will be provided to actively respiring tissues through increased unloading.
When pH falls and carbon dioxide concentration rises, haemoglobin’s affinity for oxygen decreases. This overall effect is called the Bohr effect. This effect enhances the unloading of oxygen in metabolically active tissues and ensures the delivery of oxygen meets the demands of the tissues.
The Bohr effect shifts the oxygen dissociation curve to the right. This increases the P50 of haemoglobin and so reduces the affinity of haemoglobin for oxygen. Other factors that shift the oxygen dissociation curve to the right are increased temperature (which also rises when cells respire more, for example in exercising muscle) and increased 2,3-BPG concentration. The shift to the right can be remembered by saying that 'BohR is Right'.

Diagram - Shows the Bohr effect for haemoglobin. The green line shows the change when the factors listed on the left of the curve are true. The red line shows the same for the factors listed on the right.
Creative commons source by Ratznium at English Wikipedia Later versions were uploaded by Aaronsharpe at en.wikipedia, edited by Dr. Peter Parkinson [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Carbon monoxide acts as a poison as it combines with myoglobin and haemoglobin, blocking the transport of oxygen. Carbon monoxide binds at the same sites as oxygen does, but binds more tightly: its affinity for haemoglobin is about 240 times that of oxygen. It forms carboxyhaemoglobin (COHb), which is haemoglobin with carbon monoxide bound. Because of this, carbon monoxide cannot be easily released and as a result the subunit of haemoglobin that has bound carbon monoxide cannot transport oxygen. After carbon monoxide binds to a subunit of a haemoglobin molecule, the affinity of the unaffected subunits for oxygen increases. Oxygen bound to these subunits is retained within the molecule.
As a result, an accumulation of carbon monoxide-bound haemoglobin molecules can occur which leads to fewer haemoglobin molecules being able to bind and deliver oxygen to tissues.
The oxygen dissociation curve of haemoglobin shifts to the left when carbon monoxide is present. This shows the increased affinity of the remaining haemoglobin for oxygen, seen as a reduced P50 value. Together with the loss of haemoglobin that can bind oxygen, this means less oxygen is delivered to the tissues.
Carbon monoxide poisoning can cause headache (the most common symptom), dizziness, feeling sick, tiredness, confusion and unconsciousness. These symptoms are mainly due to oxygen deprivation in the tissues. Carbon monoxide poisoning can be fatal, mainly because of severe oxygen deprivation. A carboxyhaemoglobin (COHb) level of 30% or more indicates severe exposure. However, the blood COHb level is not a reliable guide to how severe the poisoning is, and significant poisoning cannot be excluded at lower levels.

Diagram - Graph showing the oxygen dissociation curve for haemoglobin when carbon monoxide is present
SimpleMed original by Dr. Peter Parkinson
During development, the haemoglobin present in a fetus (HbF) is different from that present in an adult. This is due to the regulation of the genes that produce the haemoglobin chains. In a fetus, the haemoglobin molecule is made up of two alpha chains and two gamma chains. The switch from making gamma chains to making beta chains is gradual. It begins before birth, and adult haemoglobin (HbA) becomes the main type by about six months after birth. The switch is largely complete by 6 to 12 months of age. Alpha chains are made throughout fetal and adult life, so they are never replaced.
HbF has a greater affinity for oxygen than adult haemoglobin (HbA). This allows HbF to bind with oxygen from the maternal oxyhaemoglobin in the placenta. The increased affinity is due partly to reduced binding of 2,3-BPG to fetal haemoglobin. The gamma chains in HbF do not bind 2,3-BPG as efficiently as the beta chains of HbA. This greater affinity for oxygen within HbF allows the transfer of oxygen from the mother to the fetus. It also shifts the oxygen dissociation curve to the left.

Diagram - Graph showing the oxygen dissociation curve for fetal haemoglobin compared to adult haemoglobin
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Sickle cell anaemia is the most common type of sickle cell disease. It has an autosomal recessive inheritance pattern. This means a person has the condition only if they inherit the altered gene from both parents, and the gene is not on a sex chromosome. There are around 12,500 to 15,000 people with sickle cell disease in England. Sickle cell disease is most common in people whose families come from Africa or the Caribbean. It also affects people whose families come from the Mediterranean, south and southeast Asia and the Middle East.
A single nucleotide mutation (a change in one DNA base) results in the amino acid glutamate being replaced with valine in the beta globin chain of haemoglobin. The haemoglobin present in patients suffering from sickle cell anaemia is called haemoglobin S (HbS), whereas normal adult haemoglobin is HbA. Glutamate in HbA has hydrophilic (water-loving) properties, whereas valine in HbS has hydrophobic (water-repelling) properties.
At normal oxygen partial pressures, HbS has the same secondary, tertiary and quaternary structure as HbA. These terms mean the folding of the chain, its overall three-dimensional shape and how the four chains fit together. However, at low oxygen partial pressures, the valine amino acid residues cause the haemoglobin molecules to become sticky before polymerising (joining into long chains). The affected RBCs can then form a sickle or crescent shape.

Image - Blood smear of a patient with sickle cell anaemia. The sickle cells have a sickle or crescent shape
Creative commons source by scooterdmu [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Red blood cells with HbS are more likely to lyse (burst). This causes a haemolytic anaemia (anaemia caused by red blood cells being destroyed). The affected RBCs are also more rigid and less flexible than normal RBCs, so they can block small blood vessels, partly because of their shape. This leads to pain and organ damage due to reduced tissue perfusion.

Diagram - How sickle cells can block small blood vessels leading to organ damage
Creative commons source by Diana grib, edited by Dr. Peter Parkinson [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Stem cell transplants and gene therapy are sometimes used to cure sickle cell disease. Gene therapy treats the person's own blood cells so that they work properly. In England, NICE recommends one gene therapy, exagamglogene autotemcel (exa-cel), as an option for people aged 5 years and over who have repeated painful crises (sudden episodes of severe pain when sickled red blood cells block small blood vessels). It is for people who could have a stem cell transplant but have no matched related donor (a relative whose tissue type matches). It is used under a managed access agreement, which means more evidence is being collected. Other treatments reduce symptoms and prevent complications. They include painkillers, hydroxycarbamide (a medicine that can help to reduce painful crises), blood transfusions and red cell exchange (replacing damaged red blood cells with healthy donor cells). People with sickle cell disease are more likely to get serious bacterial infections. This is related to splenic dysfunction (a spleen that does not work properly), which weakens defence against infection. Invasive pneumococcal disease (a serious infection with Streptococcus pneumoniae, such as meningitis or infection of the blood) is the most significant cause of illness and death from infection. The risk is especially high from encapsulated bacteria (bacteria with a protective outer coat), including Streptococcus pneumoniae and Neisseria meningitidis. To reduce this risk, children are offered penicillin to prevent infection, started by 3 months of age and continued until they are 5 years old. Erythromycin is used instead if a child is allergic to penicillin. People who stay at high risk of pneumococcal infection are offered antibiotics for life. Everyone with sickle cell disease should also be fully vaccinated, including vaccines against pneumococcus, meningococcus (the MenACWY vaccine, which covers four groups of this bacterium, and the MenB vaccine, which covers group B) and influenza.
Thalassaemias are a group of inherited blood disorders. There is an imbalance between the number of alpha and beta globin chains due to an abnormal production of the affected globin chain. There are two types of thalassaemia: alpha-thalassaemia and beta-thalassaemia.
In alpha thalassaemia, the severity depends on how many of the four alpha-globin genes are missing or faulty. In beta thalassaemia, a person with one faulty beta-globin gene is a carrier (someone who carries a faulty gene but usually has no symptoms), and a person with two faulty genes has thalassaemia. The severity then depends on how much beta globin can still be made. The words trait, minor, intermedia and major are also used to describe severity. Trait (also called minor) is a carrier state with no symptoms or only very mild anaemia. Intermedia is in between: the anaemia is milder than in major, and regular blood transfusions are not needed from early childhood. Major means severe symptoms and dependence on regular blood transfusions as treatment.
Signs and symptoms of thalassaemia include weakness, fatigue, slow growth and pale/yellowish skin. Weakness, fatigue and pale skin are caused by anaemia (too little working haemoglobin to carry oxygen around the body).
Alpha-thalassaemia reduces or abolishes alpha-globin chain production. After birth, excess beta chains can form haemoglobin H (HbH; β4), a tetramer (a molecule made of four chains) of four beta chains. HbH has high oxygen affinity, which impairs oxygen delivery to tissues. It is also unstable: it precipitates (clumps and falls out of solution) within red cells, which contributes to haemolysis (breakdown of red blood cells) and anaemia. In the fetus, excess gamma chains form haemoglobin Bart (γ4), a tetramer of four gamma chains. Severe deficiency of all four alpha-globin genes causes Hb Bart hydrops fetalis (severe fluid build-up in the fetus). Hb Bart (in the fetus) and HbH (after birth) are different molecules and cause different conditions.
There are several levels of severity because there are four genes that produce alpha chains, and the severity of the symptoms depends on how many genes are missing or faulty. If one or two genes are affected, the person is a carrier (alpha thalassaemia trait). If three genes are affected, the person has haemoglobin H disease. If all four genes are missing, the fetus develops hydrops fetalis. This is usually fatal before birth or in the newborn period. Some babies have survived with blood transfusions given before birth (intrauterine transfusion) and lifelong treatment after birth.
There is decreased or absent beta-globin chain production. In beta-thalassaemia, the alpha chains that are made have too few beta chains to pair with, so they cannot form stable haemoglobin tetramers (molecules of four chains). The unpaired alpha chains build up in developing red blood cells and are toxic to them. Beta-thalassaemia is caused by faulty beta-globin genes. A person with one faulty gene is a carrier and usually has no symptoms. A person with two faulty genes has thalassaemia, and it is more severe the less beta globin can still be made. In the most severe form, beta-thalassaemia major, symptoms usually start from a few months after birth, when fetal haemoglobin (which has no beta chains) is being replaced by adult haemoglobin. Less severe forms may not cause noticeable problems until later in childhood or even adulthood.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 13338



