

Next Lesson - Vitamin B12 and Folate
Core
Anaemia is defined as the condition in which your body has insufficient haemoglobin to meet its needs. Without the correct levels, the body is unable to carry enough oxygen to its cells for them to carry out their normal function.
The World Health Organisation (WHO) defines anaemia in adults aged over 15 years as a haemoglobin level below 130 g/L in men and below 120 g/L in non-pregnant women. UK laboratories use their own reference range (the range of values seen in healthy people), so check the range on the report. The cut-offs are different in pregnancy and in children. The WHO cut-offs came from studies of mainly White adults, and researchers have called for them to be re-examined for other populations.
Anaemia is not a standalone diagnosis, but a sign of underlying pathology.
Anaemia can take place due to a variety of disruptions to the life cycle of a RBC. The life cycle of a RBC has three stages: production (in the bone marrow), circulation (in the blood) and removal (by macrophages in organs such as the spleen). The diagram shows each stage:

Diagram: Shows the lifecycle of a red blood cell and where they are found during each stage
SimpleMed original by Dr. Keertana Anne
Abnormalities during production:
Dyserythropoiesis
This is the abnormal development of RBCs in the bone marrow, also called ineffective erythropoiesis (erythropoiesis is the making of RBCs). The young red cell precursors die or fail to mature. It can be congenital, inherited or acquired. An inherited example is congenital dyserythropoietic anaemia (CDA), a group of conditions that are present from birth.
Acquired problems with RBC production can happen when the bone marrow cannot make enough healthy RBCs. This can be due to damaged bone marrow from chemotherapy (anti-cancer) drugs or infection. Another cause is chronic disease and inflammation, called anaemia of chronic disease (or anaemia of inflammation). It is the second most common anaemia worldwide, after iron deficiency. Long-term inflammation, for example in rheumatoid arthritis (an autoimmune disease that inflames the joints), raises the level of hepcidin, a hormone that controls iron. Hepcidin blocks iron absorption from the gut and traps iron inside macrophages. Less iron is then available to make RBCs. In renal disease, the kidneys make less erythropoietin, the hormone that tells the bone marrow to make RBCs.
[Further discussed in Iron Metabolism, Vitamin B12 and Folate]
Defects in haemoglobin synthesis
RBC production can fail in two main ways. The first is a lack of essential nutrients: iron, vitamin B12 and folate (another B vitamin). Iron is needed to make haemoglobin, so iron deficiency gives small, pale RBCs. Vitamin B12 and folate are needed to make DNA. Without them the cells in the bone marrow cannot divide properly (megaloblastic anaemia, see below). The second cause is mutations in the genes for the globin chains, the protein parts of haemoglobin. These are seen in thalassaemias (inherited conditions in which a globin chain is made in reduced amounts) and sickle cell disease.
[Further discussed in Haemoglobinopathies]
Abnormalities during circulation:
Damage to red cells - Haemolytic anaemia
Haemolysis is the destruction (lysis) of RBCs. It can occur inside the blood vessels (intravascular haemolysis). It can also occur outside them, when macrophages in the reticuloendothelial system (RES), for example in the spleen, remove the cells (extravascular haemolysis). RBCs are damaged due to shear stress, a form of mechanical damage to the cells. This occurs when they are forced through small gaps in vessels or valves. Examples include damaged heart valves, vasculitis (inflammation of the blood vessel walls) and microangiopathic haemolytic anaemia (MAHA). In MAHA, RBCs are torn apart as they squeeze through small vessels partly blocked by clots. A common cause is disseminated intravascular coagulation (DIC), in which clots form throughout the small vessels. A blood film (a drop of blood spread thinly on a glass slide and examined under a microscope) shows the remnants of lysed cells as schistocytes (fragmented RBCs; see article on Full Blood Count and Blood Films).
Both heat damage and osmotic changes can also cause damage to the structure of RBCs. These all come under acquired causes of haemolytic anaemias.
There are also inherited causes of RBC damage. These include hereditary spherocytosis, glucose-6-phosphate dehydrogenase deficiency (G6PD deficiency) and pyruvate kinase deficiency. In hereditary spherocytosis, defective cell membrane proteins make the RBCs spherical instead of biconcave (a disc that is dented on both sides). This makes them more fragile. G6PD deficiency is the most common human enzyme defect. RBCs break down when an infection, certain drugs or fava beans put them under oxidative stress (damage caused by reactive forms of oxygen). Pyruvate kinase deficiency is rare, affecting about 1 in 100,000 to 1 in 300,000 people. It causes long-term haemolytic anaemia. Abnormal cells like these are often removed early by macrophages in the spleen, which is known as extravascular haemolysis.
The body can also attack its own RBCs, in a condition known as autoimmune haemolytic anaemia. Autoantibodies produced by your immune system bind to the proteins on the RBC membrane, causing the RBCs to be targeted and destroyed. This can be caused by other diseases (lupus, lymphomas, certain viruses like EBV/HIV) and some types of medications (e.g. penicillin).
Macrophages in the red pulp of the spleen (the part that filters the blood) remove damaged RBCs from the circulation. If this keeps happening, the bone marrow cannot keep up. RBCs are destroyed faster than they can be replaced.
Excessive bleeding
Anaemia can also develop in situations of blood loss (seen in injury, surgery or childbirth). When there is a large loss of blood, there is a reduced level of iron in the body, so the bone marrow is unable to increase the production of new cells to replace those that were lost. A common cause of this is menorrhagia, heavy blood loss during menstruation. Therefore it is imperative to take a full bleeding history when assessing a patient for anaemia.
Removal by Reticuloendothelial System (RES)
The reticuloendothelial system (RES) is a network of macrophages (cells that engulf and digest old or damaged cells) in organs such as the spleen. It removes damaged RBCs from the circulation. This can become a problem when RBCs are destroyed faster than they can be replaced. An overactive RES speeds up red cell destruction. This is seen in hypersplenism, where an overactive spleen (usually enlarged) removes blood cells too quickly.
Anaemia can be classified by the size of RBCs (part of their morphology, meaning their shape and size). It can also be classified by how the bone marrow responds. This is shown by the reticulocyte count. Reticulocytes are young RBCs that have just left the bone marrow. A raised count means the marrow is making more RBCs to counter the loss. The following flow diagram can help to narrow down the causes:
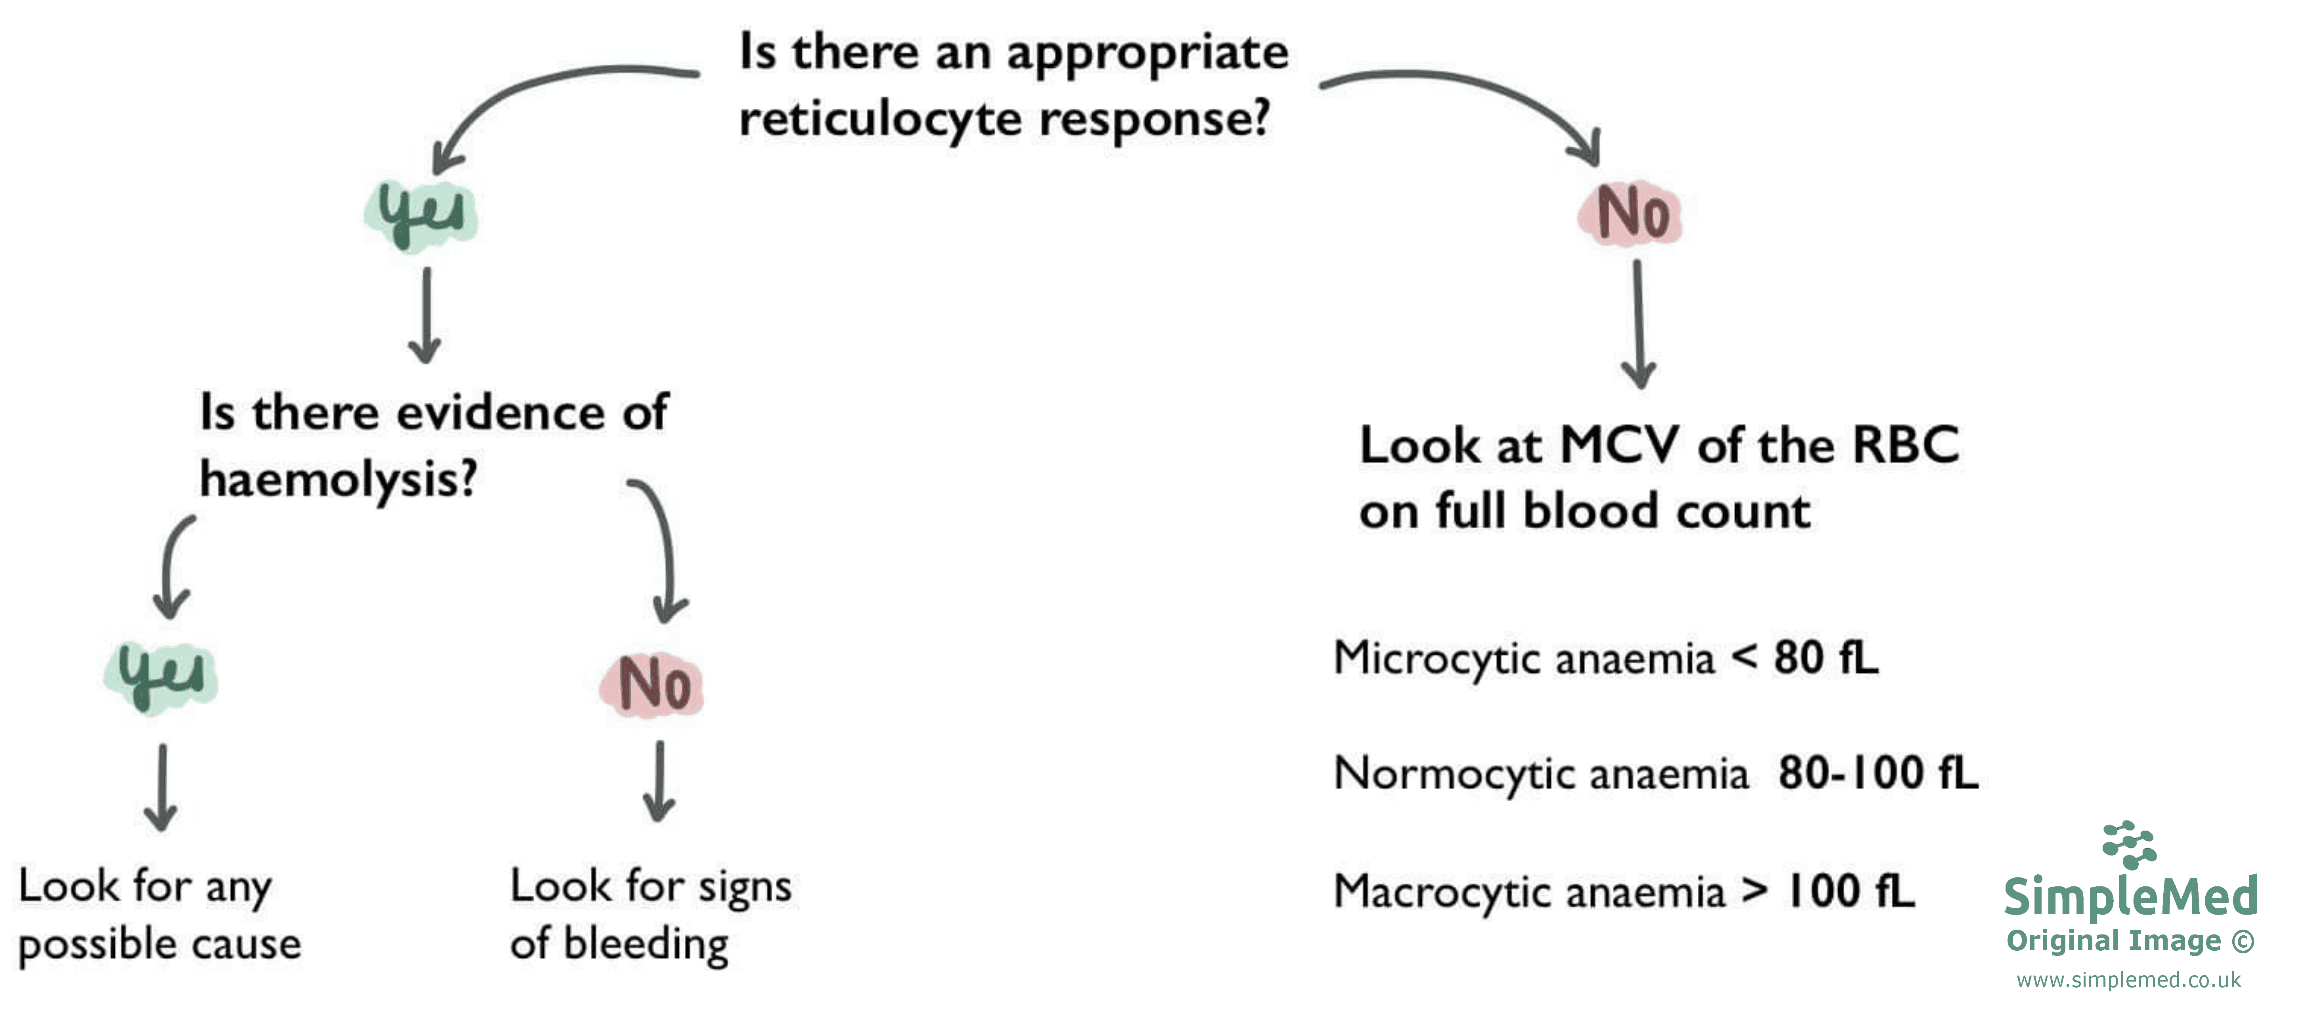
Diagram: A flow diagram showing the classification of anaemia based on reticulocytes and mean corpuscular volume
SimpleMed original by Dr. Keertana Anne
If the bone marrow is responding appropriately, the reticulocyte count is raised (reticulocytosis, found with a blood test; see article on Full Blood Count and Blood Films). This shows an active bone marrow trying to replace lost RBCs rapidly. It is seen in excessive bleeding, splenic sequestration of RBCs (RBCs trapped in the spleen) and haemolysis.
However, a low reticulocyte count, or one lower than expected for the degree of anaemia, means the bone marrow is not making enough RBCs. You would then look at the mean corpuscular volume (MCV), which is the average size (volume) of the RBCs. The blood count analyser measures it.
Microcytic anaemia (Low MCV)
This is characterised by small RBCs. Some causes of this anaemia can be summarised by the mnemonic (memory aid) TAILS:
- Thalassaemia
- Anaemia of Chronic Disease (normocytic in about 80% of cases and microcytic in about 20%)
- Iron Deficiency Anaemia
- Lead Poisoning
- Sideroblastic Anaemia (a very rare condition in which the body has iron but cannot incorporate it into haemoglobin)
Normocytic anaemia (Normal MCV)
In normocytic anaemia, the size of RBCs is normal, however, the haematocrit and haemoglobin levels are reduced. This can occur due to multiple reasons - the most common being anaemia of chronic disease, associated with chronic infection, inflammatory and malignant disease. In anaemia of chronic disease, serum iron levels fall because iron is trapped inside cells (macrophages) and is not available to make RBCs. Other causes of normocytic anaemia include: early stage microcytic anaemia (some normal-sized cells remain); a mix of microcytic and macrocytic anaemias (the red cell distribution width, RDW, shows how much RBC size varies, so it is increased, but the average size looks normal); renal failure, bone marrow failure and acute blood loss.
Normocytic anaemia is very common, especially in hospital patients, because anaemia of chronic disease is usually normocytic. Worldwide, however, iron deficiency (usually microcytic) is the most common cause of anaemia overall.
Macrocytic anaemia (High MCV)
In macrocytic anaemia, the RBCs are larger than normal (a high MCV), but there are too few of them and the haemoglobin is low. Causes include alcohol excess, vitamin B12 or folate deficiency, liver disease, some medications and some types of haemolytic anaemias.
One of the most common types of macrocytic anaemia is megaloblastic macrocytic anaemia. This takes place when DNA is made too slowly or in too small amounts. The young RBCs in the bone marrow (megaloblasts) grow large but cannot divide normally, and their nuclei stay immature. It is most commonly caused by vitamin B12 or folate deficiency, which are both needed to make DNA (see above).
Anaemia that develops over time may not present with any symptoms as the body can begin to adjust to reduced haemoglobin levels. A rapid decline however can produce more significant symptoms:
- Symptoms - fatigue and lack of energy, pale skin, headache, shortness of breath, palpitations (being aware of your heartbeat) and feeling light-headed or faint. Most of these come from the tissues receiving less oxygen.
- Signs - pallor (looking pale, which may be seen even with mild anaemia), bounding pulse (a strong, forceful pulse), postural hypotension (blood pressure that falls on standing up) and tachycardia (a fast heart rate). Signs may be absent, even when anaemia is severe.
The way to treat anaemia is by focusing on the underlying cause of it:
- Iron deficiency is treated with oral iron, for example one tablet a day of ferrous sulfate, ferrous fumarate or ferrous gluconate. Advice on iron-rich foods is given alongside the tablets. Parenteral iron (iron given by injection or infusion) is considered if oral iron is not tolerated, does not work or cannot be used. It is also used if blood loss continues or if iron is not absorbed well (malabsorption).
- Vitamin B12 deficiency is treated with B12 replacement. This is either hydroxocobalamin (a form of B12) injected into a muscle, or oral B12 tablets. The choice depends on the cause. If there are neurological (nerve) symptoms, injections are used first.
- Folate deficiency is treated with oral folic acid (the supplement form of folate). Vitamin B12 levels should be checked before starting it, because folic acid can mask a B12 deficiency and allow nerve disease to develop.
- Find and stop the cause of bleeding - the bleeding may be obvious, for example heavy periods, or hidden inside the body, for example from a peptic ulcer (a sore in the lining of the stomach or duodenum).
- If the patient has anaemia of chronic kidney disease, they may be offered an erythropoiesis stimulating agent (ESA). This is a drug, given by injection, that acts like the hormone erythropoietin and so makes the bone marrow produce more RBCs. Iron deficiency needs to be treated first or at the same time.
- Blood transfusions can be given in extreme cases.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 9943
