

By Dr. Ben Applebyand Dr. Maddie Swannack
Next Lesson - Population and Social Science Summary
Core
Patient safety and quality in the NHS
Quality and safety have not always been well managed in the NHS. A series of scandals and new research have brought the importance of patient safety and quality healthcare to the fore.
Issues have been identified through:
- Evidence of substandard care in some areas.
- Wide variations in healthcare outcomes and decisions between different areas of the country.
- Direct cost of litigation (legal claims for compensation) on already limited NHS resources.
Safety and quality are closely linked: safety is one of the six aims of high quality healthcare listed below. Hospitals which prioritise quality perform better than those which simply try to achieve a minimum of safe treatment.
High quality healthcare is characterised by:
- Safety - no needless deaths.
- Effectiveness - no needless pain or suffering.
- Patient-centredness - focussed on the patient’s needs and priorities.
- Timeliness - no unwanted waiting.
- Efficiency - no waste.
- Equitability - no one left out.
This is obviously difficult to achieve, especially with limited resources. Variations in healthcare across the country suggest that not everyone receives the same quality of care. Variation is not always a bad thing as the different populations that make up the UK have different needs to be met. However, this alone does not account for the presence of waste or inequity.
A good example of this variation is seen in the requirements to receive IVF (in vitro fertilisation) funded by the NHS in England. This variation has been called the ‘postcode lottery’: local integrated care boards (ICBs, the NHS organisations that plan health services for their area) decide who can have NHS-funded IVF and how many cycles they will fund. Depending on the area, the NHS may fund one, two or three cycles, or none. There are many mechanisms in place to try to improve care quality in the NHS:
- Use of standard setting with NICE quality standards of what high quality evidence based care should look like.
- Use of commissioning to drive improvement. Commissioning is the continual process of planning, agreeing and monitoring services, from assessing a population’s health needs to agreeing contracts and checking their quality.
- Use of financial incentives through things like the Quality and Outcomes Framework (QOF), which rewards GP practices in England for the quality of care they provide. Commissioning for Quality and Innovation (CQUIN) was used in a similar way, but NHS England has paused the mandatory CQUIN scheme.
- Increasing emphasis on disclosing information by making it easier to blow the whistle on safety issues and introducing duty of candour where clinicians are obliged to speak up.
- Use of regulation and inspection by the Care Quality Commission (CQC), the independent regulator of health and adult social care in England, which inspects and rates services.
- Use of clinical audits (measuring care against agreed standards, making changes where it falls short, then checking again).
- Feedback from patients such as the ‘friends and family test’.
- Revalidation of doctors as a GMC requirement, normally every 5 years. Revalidation is based on a yearly appraisal (a structured review of the doctor’s work) and checks that doctors are fit to practise and are keeping up to date with medical advances.
An adverse event is an injury caused by medical management (rather than underlying pathology) that causes prolonged hospitalisation, disability, or both. A preventable adverse event is one that is predictable and avoidable.
Some adverse events are unpredictable, e.g. a first time adverse drug reaction (an allergic reaction to penicillin in a patient who has never reacted to it before). This harm came from medical management, so it is an adverse event, but at the moment there is no way to predict it. Should a method come about to reliably predict this event then it would be reclassified as a preventable adverse event.
Some adverse events are preventable. Never Events are a specific subset of patient safety incidents covered by the NHS Never Events list. They are considered wholly preventable because nationally available guidance or safety recommendations provide strong systemic protective barriers (reliable safeguards built into the system, for example a uniquely designed connector that stops a medicine being given by the wrong route) that healthcare providers should have implemented. Classification depends on the listed incident’s criteria, not simply on the severity of injury: actual serious harm is not required. NHS England’s existing Never Events framework remains active while a replacement is developed. Examples of preventable adverse events include:
- Operations being performed on the wrong patient or on the wrong site. This would be classed as a never event.
- Retained objects like surgical swabs. This is a never event.
- Wrong dose or type of medication given. Some specific medication errors meet the criteria for a never event.
- Some infections, like line infections (infections linked to a thin tube placed in a vein, such as a cannula).
All humans are fallible, meaning mistakes can sometimes just happen. Many errors are highly predictable therefore good systems design should anticipate human error and support individuals within the system.
There are four main types of human failure. Slips, lapses and mistakes are errors (actions or decisions that were not intended). Violations are deliberate.
- Slips - failure of attention (misreading the operating proforma, a standard printed form, and operating on the wrong site).
- Lapses - failure of memory (forgetting to fill in a referral form for a patient so they don’t receive the care they need).
- Mistakes - errors of judgement or decision-making, where you do the wrong thing believing it to be right. They can be rule based (using a remembered rule that does not fit the situation, for example wrongly assuming that a policy from another hospital applies here) or knowledge based (not knowing the correct way to do a new or unfamiliar task).
- Intentional violations - deliberate deviations from rules or procedures, such as knowingly skipping a required check to save time. The deviation is intentional, but there is often no intention to cause harm. Malicious acts are one possible category of violation; they do not define all violations.
The state of a healthcare system can sometimes make human errors more likely: inadequate training, understaffing, long hours, drugs that look the same, poorly designed equipment, lack of checks before procedures are done, different methods of doing the same task in different places.
Sometimes failures can be the fault of an individual (incompetence, negligence, malign behaviour), but more often the system has failed, and the same circumstances could lead anyone to make a similar error. Systems and processes not designed for safety are more likely to fail and to need workarounds (quick fixes that get round a problem) which don’t solve the root issue. This common systems failure leads to:
- Short term workarounds instead of long term changes to the system (called 1st order problem solving - see below).
- The tendency to rely on people to put more work in to overcome the problem.
- The need for people to be vigilant all the time.
- A tolerance for poor quality care.
The James Reason Framework for Error 'The Swiss Cheese Model'
This model attempts to explain why errors occur despite normally effective systems being put in place. Reason’s framework is most famously explained as the Swiss cheese model.
The Swiss Cheese model imagines a system as a number of slices of Swiss cheese (see below). Each slice represents a defence (safeguard) that protects patients from harm. However, each slice has holes, which are weaknesses in that defence. The holes come from two sources: pre-existing flaws in the system (latent failures) and the unsafe acts of staff (active failures). A hole in one slice does not normally cause harm, because the next slice stops the error. Harm usually happens only when the holes in many slices line up at the same moment, letting an error pass through every defence to the patient. Examples of ‘holes’ could be things like flawed protocols, time pressures, understaffing, uncommunicative patients and illegible notes to name just a few factors.
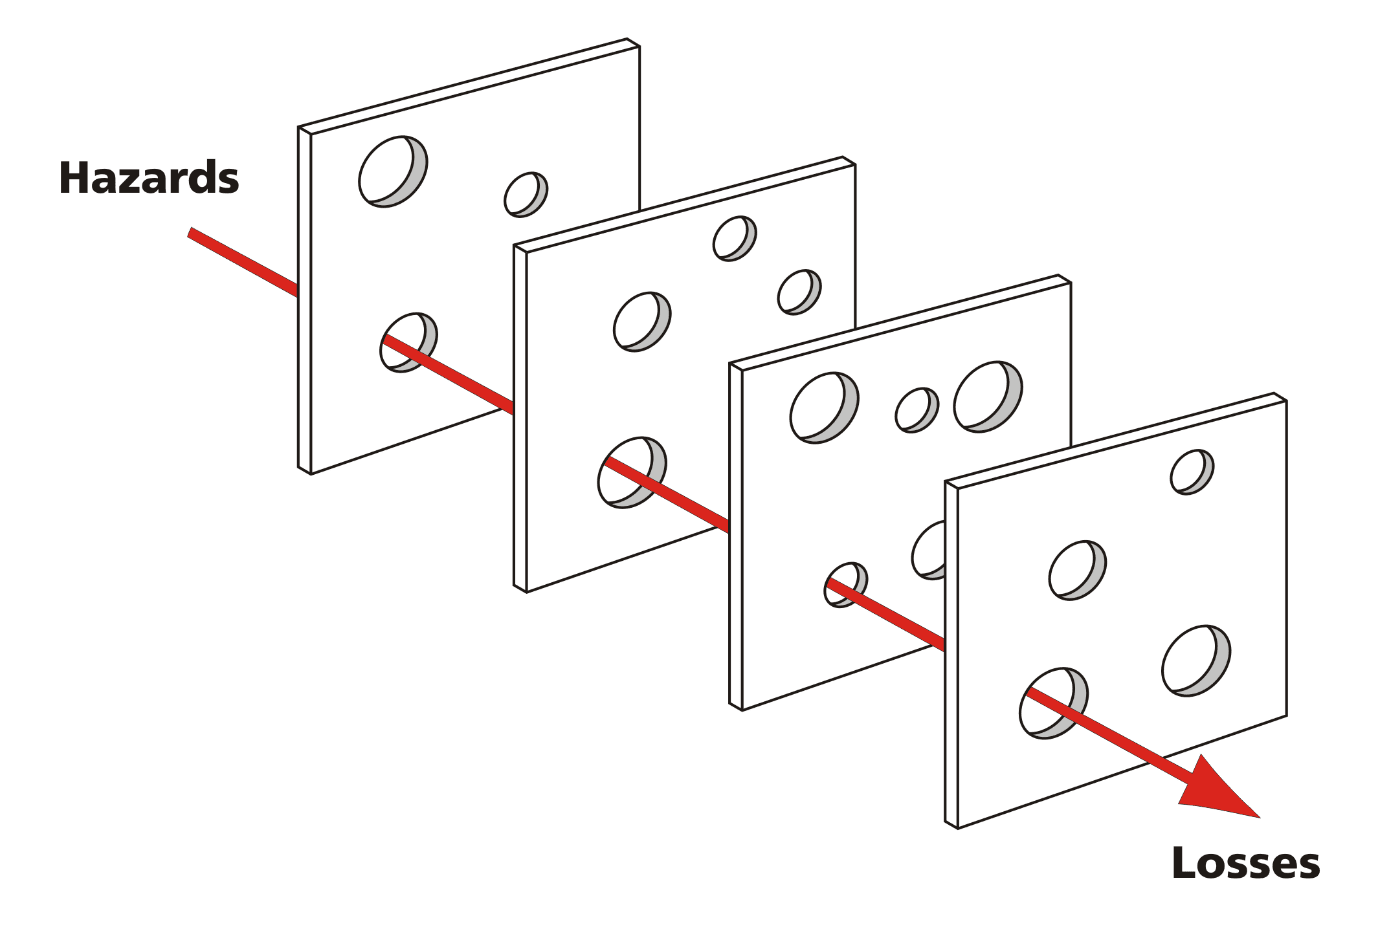
Diagram showing the Swiss Cheese model, showing how different flaws in the systems and human error can line up to cause harm or loss.
Creative Commons Image Source Davidmack [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
In a nutshell, the James Reason Framework for Error is therefore composed of two parts:
- Latent failures are the predisposing conditions of the system that encourage active failures and create holes in its defences e.g. short staffing and similar looking drugs.
- Active failures are the unsafe acts of staff in direct contact with the patient e.g. administration of the incorrect drug. Latent failures make active failures more likely e.g. the wrong drug is selected by the tired, overworked staff member as it is easily confused with another similar looking drug. A more distinctive drug or a better rested clinician would have made the active failure less likely.
There are two orders of problem solving:
First Order Problem Solving - a basic form of problem solving consisting of doing exactly what it takes to complete the task (no more and no less) e.g. if the drip stand is broken, using some surgical tape to fix it. The stand will of course break again in future. This means the problem has only been temporarily and poorly solved, leaving it up to the next user of the faulty stand to fix it again.
Second Order Problem Solving - a more advanced form, where the problem is stripped back to its root (using forms of analysis seen below). A solution is then worked upwards from there. This can take a lot longer (which is why it is often not completed) but reduces the chances of the errors happening again. In the example above, it would involve asking why the drip stand is broken and why it hasn’t been replaced. ‘The department won’t supply any more drip stands as they keep being damaged by door frames’. The second order solution would be to transport the stands collapsed so that they fit through the doors. The department can then be asked to supply new stands, now that this change is in place. The new stands are not broken, as they aren’t damaged by doors. Barriers to second order problem solving include: busy doctors ‘I don’t have the time to collapse the stand’, too new/uncomfortable/alien an idea ‘I’m not sure I’m comfortable with collapsing the stand’, traditional standards and beliefs ‘I was told that a doctor who collapses their drip stand is no true doctor at all!’ or ‘Adjusting drip stands? We don’t do that around here.’
Root Cause Analysis/Systems Analysis
These interchangeable terms both refer to analysis that aims to identify the underlying causes of failure while looking at the whole picture. In August 2022, NHS England published the Patient Safety Incident Response Framework (PSIRF) to replace the older Serious Incident Framework. PSIRF uses a range of system-based approaches to learning from patient safety incidents, focusing on understanding how incidents happen rather than on blame. Some helpful tools when considering a root cause analysis:
- The 5 Whys - basically asking why until it can’t be answered anymore. e.g. Patient died (why?) because they were given a drug that they were allergic to (why?) because it wasn’t written in their file that they were allergic to it (why?) because it was written in the wrong patient file (why?) because the file was kept in the wrong place (why?) because the current filing system doesn’t work with this many patients. This then finds the root issue which can then be amended to prevent further harms.
- Timelines - two timelines are drawn, one of what happened and one of what should have happened as per guidelines or best practice. They are then compared to see where the timeline which resulted in harm deviated from best practice.
- Fishbone diagrams (also called cause and effect diagrams) - the problem is written at the ‘head’ of the fish, and the possible causes are grouped along the ‘bones’ (see diagram below).
- Plan-Do-Study-Act Cycles - a cycle that takes place around an intervention. Plan what the intervention should be. Do (carry out) the intervention. Study the results to see where it did well and where it went wrong. Act on those findings to plan new improvements. The cycle then repeats, improving the intervention each time.
These are all examples of techniques that could be used in the analysis of failure.
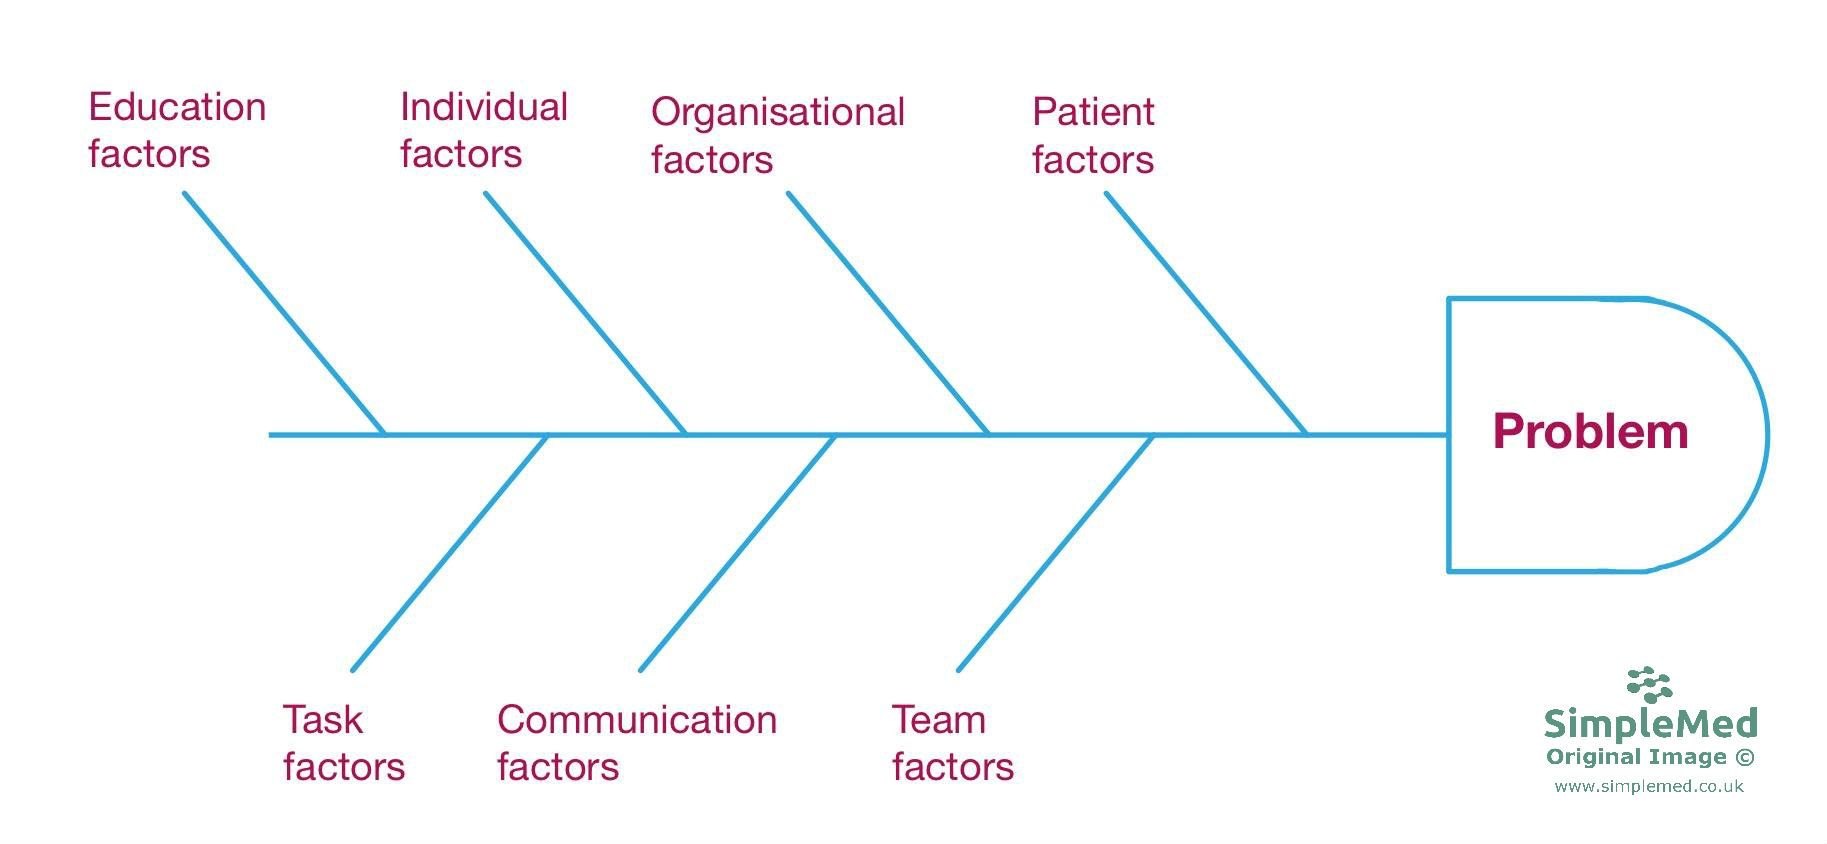
An example of a Fishbone Diagram - it helps to explain the different things that can contribute to the problem and prompts discussion on which areas might have contributed.
SimpleMed Original by Dr. Maddie Swannack
Negligence is a legal term. Not all harm from healthcare is due to negligence. In one large US study of hospital records (the Harvard Medical Practice Study), 27.6% of adverse events were due to negligence. For a negligence claim to succeed, four criteria must be met:
• The defendant (the healthcare worker) owed a duty of care - by definition all healthcare workers have a duty of care to their patient.
• The defendant was in breach of that duty - their care fell below the standard of accepted practice (judged using the Bolam test).
• The breach of duty caused damage - it must have caused harm.
• The damage was foreseeable and not too remote from the breach - if the clinician was simply ‘unlucky’ and the harm was unforeseeable this would not count as negligence.
Note: please refer to our disclaimer. The authors of this article are not lawyers and this article does not constitute legal advice.
Speaking up when witnessing a failure in healthcare is important because it highlights where harm to patients could (or has already) occurred. Speaking up can prevent further harm to patients. It can be difficult to speak up for a number of reasons:
- Loss of situational awareness - you might not realise that a situation has become dangerous even if it originally wasn’t.
- Authority gradients - differences in seniority make it harder to question a more senior person, for example when they say that it is safe.
- Too much deference to others - thinking that senior individuals always know better.
- Fear of future hostility - co-workers might be unpleasant towards you after their actions are reviewed, and there may be unspoken punishment (tacit retribution) in the workplace.
- Not certain it’ll make a difference - colleagues might not listen or change their behaviour. Colleagues might only change their opinion about you.
The NHS encourages speaking up through a number of methods including:
A duty of candour (a duty to be open and honest with patients). Healthcare organisations in England that are registered with the CQC have a statutory (legal) duty of candour. Individual professionals also have a professional duty of candour, overseen by their regulator, such as the GMC. The duty sets out specific steps after a notifiable safety incident. For an NHS body, this is an unintended or unexpected incident that could result in, or appears to have resulted in, death, severe harm, moderate harm or prolonged psychological harm. After such an incident, the organisation must:
- Tell the person affected, in person, giving a true account of all the facts it knows, and offer them reasonable support.
- Advise them what further enquiries into the incident are appropriate.
- Follow this with a written notification, including the results of any further enquiries.
- Apologise to the person affected.
Freedom to Speak Up Guardians: staff in NHS and independent sector healthcare organisations in England who make sure workers are supported in speaking up and that barriers to speaking up are addressed.
Stop the line - (in some trusts) if any member of the team says the phrase ‘stop the line’ this highlights that there is a possible patient safety issue and that the procedure or intervention should be stopped immediately.
SBAR (Situation, Background, Assessment, Recommendation) is a useful tool used to pass information from one clinician to another in a way that is clear. This helps to avoid situations where information is missed in handover.
Situation - Who am I? Who is the patient? Where are they? What is going on with the patient (key points of history and key concerns)?
Background - What is the patient’s clinical background or context?
Assessment - What do I think the problem is?
Recommendation - What do I need to do next? What do I need from you?
Reviewed by: Dr. Marcus Judge
- 6227

