

SimpleMedSimpleMed
Hit enter to search or ESC to close

Get in Touch

Contact Us

Use our contact form.

Infections of the Reproductive Tract

Share:

By Dr. Maddie Swannack

Next Lesson - Pelvic Inflammatory Disease

Reproductive System


Contents

  1. Sexually Transmitted Infections
    • Contact Tracing
    • Chlamydia
    • Gonorrhoea
    • Syphilis
    • Anogenital Warts
    • Herpes
    • Trichomonas Vaginalis
  2. Non-sexually Transmitted Infections
    • Scabies and Pubic Lice
    • Bacterial Vaginosis
    • Vulvovaginal Candidiasis
  3. Vaginal Discharge
  4. Quiz

Abstract

  • In England, new STI diagnoses fell by 8.3% between 2024 and 2025, but diagnosis rates remain relatively high in young people aged 15 to 24 years, in gay, bisexual and other men who have sex with men, and in people of some minority ethnic groups. STIs place demand on sexual health services, including genitourinary medicine (GUM) clinics.
  • STIs are passed on by direct contact with an infected person. This includes contact between mucous membranes (the moist lining of the genitals, mouth and anus) and skin-to-skin contact. Risk factors include young adult age, an increased number of sexual partners, young age at first intercourse, excessive alcohol or recreational drug use, lack of education, and lack of access to condoms and sexual health services.
  • Chlamydia infection is caused by Chlamydia trachomatis. Infection can be asymptomatic (without symptoms). Men may have urethritis (inflammation of the urethra) and dysuria (pain on passing urine). Women may have discharge and dyspareunia (pain during sex). If untreated, it can lead to pelvic inflammatory disease (PID) or to problems outside the genitals, such as conjunctivitis and reactive arthritis (joint inflammation triggered by an infection elsewhere in the body). It is tested for with a swab or urine sample and a nucleic acid amplification test (NAAT, which detects the genetic material of the bacteria). It is treated with doxycycline (an antibiotic).
  • Gonorrhoea is caused by the Neisseria gonorrhoeae bacteria, a Gram negative diplococcus. It commonly can be asymptomatic, but can present with discharge, dysuria or lower abdominal pain in both sexes. If untreated, it can progress to PID. Tested for with swabs/urine samples and NAAT. Treated with IM Ceftriaxone.
  • Syphilis is caused by the Treponema pallidum bacterium. It has four stages. Primary syphilis presents with a chancre (a painless ulcer). Secondary syphilis presents with a rash. Latent syphilis causes no symptoms. Tertiary syphilis presents with gummata (large sores) and cardiovascular problems. Neurosyphilis (nervous system damage) can occur at any stage. Syphilis is treated with penicillin.
  • Anogenital warts (warts around the anus and genitals) are most often caused by HPV (human papillomavirus) strains 6 and 11 (these strains are vaccinated against). The warts can be treated with topical creams or cryotherapy (freezing them off), but HPV infection can persist, leading to recurrence of the warts.
  • Genital herpes is caused by herpes simplex virus (HSV-1 or HSV-2), and presents with painful sores. Aciclovir (an antiviral drug) is the treatment. It suppresses symptoms but does not eradicate the virus. Recurrences are common, particularly in the early years after infection.
  • Trichomonas vaginalis is a sexually transmitted protozoan (a single-celled parasite) which can cause trichomoniasis infection. It is often asymptomatic in men. In women it typically presents with a yellow, foul-smelling discharge that irritates the vulva (the external female genitals) and vagina. It is treated with metronidazole (an antibiotic).
  • Scabies (caused by a mite, a tiny skin parasite) and pubic lice (tiny insects that live on body hair) are parasites that can affect the genital region. They are spread mainly by close body contact, which is often sexual contact.
  • Bacterial vaginosis is associated with an imbalance of the normal vaginal flora (the normal bacteria of the vagina), often involving overgrowth of Gardnerella vaginalis and other anaerobic bacteria. The exact cause is unknown. Risk factors include douching (washing inside the vagina), smoking, and a new or multiple sexual partners. It presents with an offensive ‘fishy smelling’ grey discharge. Bacterial vaginosis without symptoms usually needs no treatment. When there are symptoms, it is treated with metronidazole (an antibiotic) and by avoiding contributing factors such as douching.
  • Candidiasis or thrush is caused by an overgrowth of the fungus Candida albicans. Risk factors include immunosuppression (a weakened immune system), diabetes, pregnancy, recent antibiotics and possibly the combined oral contraceptive pill (COCP). It presents with white, thick discharge and intense itchiness. Management can be difficult because risk factors such as diabetes or immunosuppression cannot always be removed. Antifungal azoles such as fluconazole can help, but oral fluconazole is not used in pregnancy.
  • Vaginal discharge is an important symptom of many of these diseases. Some discharge is normal. A change from the patient’s own normal discharge is what helps with diagnosis.

Core

Infections of the reproductive tract are common in both men and women and have many different causes. Some of these infections can be sexually transmitted.

The sexually transmitted infections HIV and Hepatitis have their own dedicated articles in our Infection unit (see HIV and Hepatitis), and so will not be discussed in this article.


Sexually Transmitted Infections (STIs)

In England, the number of new STI diagnoses fell by 8.3% between 2024 and 2025 (source). Diagnosis rates remain relatively high in young people aged 15 to 24 years, in gay, bisexual and other men who have sex with men, and in people of some minority ethnic groups. STIs still place demand on primary care services, including GPs, and on sexual health services, including Genitourinary Medicine (GUM) clinics.

STIs are passed on by direct contact with an infected person. This includes contact between mucosal membranes (the moist lining of the genitals, mouth and anus) during vaginal, anal or oral sex. Some STIs, such as herpes, can also be passed on by skin-to-skin contact with the infected area. As a result sites of infection include the vagina, penis, anus or pharynx.

STIs are most commonly passed on through unprotected sex, which is the performance of sexual acts or sexual intercourse without a barrier method of contraception (e.g. a condom). Condoms (both external and internal) are the only form of contraception that both helps to prevent pregnancy and reduces the risk of STIs, but they do not give complete protection.

Risk Factors:

  • Age - diagnosis rates remain relatively high in young people aged 15 to 24 years.
  • Increased Number of Sexual Partners - more chances to come into contact with STIs.
  • Lack of Education - individuals who are less well informed may be unaware of the risks of STIs or be unfamiliar with contraception.
  • Excessive use of Alcohol or Recreational Drugs - alcohol and recreational drugs are known to impair judgement and lead to more high risk behaviours.
  • Lack of Access to Contraception - in the UK, condoms are free from sexual health clinics and some GP surgeries, pharmacies and young people’s services, but some people are unable to access these.
    • Geographic - the clinic might be inaccessible to the individual.
    • Stigma - the individual might not want to be seen to attend the clinic due to the stigma sometimes attached to having an STI.
    • Education - some people may not know that condoms are provided free.

In the UK, STIs can be managed and treated through a GUM clinic or another specialist sexual health service.

With all STIs, the patient should be advised to take part in a thorough screening programme, which checks for other infections. They should avoid all sexual contact (including oral sex) until they and their partners have finished treatment. For some infections they must wait a further 7 days after treatment (for example gonorrhoea, or chlamydia treated with azithromycin, an antibiotic). They should also take part in contact tracing.


Contact Tracing

As chlamydia and gonorrhoea are STIs that can be passed very easily between partners who are not using barrier contraception, any patient diagnosed should have their previous partners contacted. In the UK, the patient can tell their partners themselves, or a sexual health clinic may be able to contact them for the patient without giving the patient’s name (an anonymous service). At-risk parties are contacted, for example by text message, and advised to seek screening.

As seen in the table below, asymptomatic infections (infections without symptoms) require a longer period of contact tracing, because with asymptomatic infections, the origin is much harder to establish. The shorter periods in the table apply only to men with urethral symptoms (such as discharge or pain on passing urine). The longer periods apply to everyone else: all women, men with no symptoms, and anyone with symptoms at other sites (the rectum, throat or eye).

One of the difficulties with contact tracing stems from the fact that not all patients are willing or able to provide the contact information of their sexual partners. Patients may not have contact details for all of their past partners, and they cannot be forced to give up information they do not have.

 

Contact Tracing SimpleMed

Table - Period of contact tracing. In this table, ‘symptomatic’ means a man with urethral symptoms (such as discharge or pain on passing urine). Everyone else, including all women, follows the ‘asymptomatic’ row.

SimpleMed original by Dr. Maddie Swannack


Chlamydia

Chlamydia infection is caused by the Chlamydia trachomatis, an obligate intracellular bacterium (meaning it must be inside the cell to replicate). It is classified as a Gram negative bacterium, although in practice it is difficult to Gram stain (a laboratory stain used to see bacteria under a microscope). Unlike most bacteria, its cell wall contains very little peptidoglycan (the strong mesh that gives most bacterial walls their rigidity). Chlamydia is the most commonly diagnosed STI in England (source).


Symptoms

Can be asymptomatic (without symptoms) in both sexes, but more likely to be asymptomatic in women.

Men - mild urethritis (inflammation of the urethra, the tube that carries urine out of the body), dysuria (pain on passing urine), and local inflammation such as epididymitis (inflammation of the epididymis, the coiled tube behind the testis) or prostatitis (inflammation of the prostate).

Women - vaginal discharge, dyspareunia (pain on vaginal penetration) or post-coital bleeding (bleeding after sex).


Complications

If untreated, chlamydia infection can progress to Pelvic Inflammatory Disease (PID) and infertility.

Chlamydia can also lead to complications outside of the genitals, such as reactive arthritis (joint inflammation triggered by an infection elsewhere in the body) and eye inflammation (conjunctivitis or uveitis, which is inflammation inside the eye that causes sore, red eyes sensitive to light). The classic triad of reactive arthritis is urethritis, conjunctivitis and arthritis. This can be remembered with the phrase ‘can’t pee, can’t see, can’t climb a tree’ (urethritis, conjunctivitis, arthritis respectively). Chlamydia is also an important differential diagnosis (a possible cause to consider) in a neonate (newborn baby) presenting with conjunctivitis. The bacteria can pass to the baby during vaginal birth from an infected mother.


Investigations

As Chlamydia trachomatis cannot be seen on Gram staining, Nucleic Acid Amplification Tests (NAAT, which detect the genetic material of the bacteria) are used to identify it.

The samples are obtained by a vulvovaginal swab (a swab of the vulva, the external female genitals, and the vagina) in women, and a urine sample in men. Extragenital sites (sites outside the genitals) including conjunctiva, pharynx and anus are swabbed if symptomatic or if other non vaginal sex has occurred.


Treatment

The current recommended treatment for chlamydia infection is doxycycline (an antibiotic) 100 mg twice daily for 7 days. It cannot be used in pregnancy or breastfeeding, and azithromycin (another antibiotic) is an alternative if doxycycline is unsuitable or not tolerated.

The current recommended treatment pathway can be found here.


Gonorrhoea 

Gonorrhoea infection is caused by the bacteria Neisseria gonorrhoeae, a Gram negative, intracellular diplococcus. This means that on Gram staining, it is seen inside the cell as pink circles, arranged in pairs.


Symptoms

Can be asymptomatic in both sexes, but more likely to be asymptomatic in women.

Men - discharge and dysuria.

Women - vaginal discharge and lower abdominal pain.

Due to the similar symptoms to chlamydia differentiation of cause is usually only achieved after NAAT.


Complications

If untreated, gonorrhoea infection can lead to PID, which occurs in up to 33% of women with gonorrhoea, and to epididymo-orchitis (inflammation of the testes and epididymis). Chlamydia can also cause PID, in up to 16% of women with untreated infection.


Investigations

While Neisseria gonorrhoeae does appear on Gram staining, the culturing required takes time. For this reason, NAAT is used, with vulvovaginal or endocervical (from the neck of the womb) swabs in women and a urine sample in men. A culture is still taken before treatment in people with a positive NAAT, to test which antibiotics the bacteria are sensitive to and to identify resistant strains.


Treatment

The treatment for gonorrhoea infection is a single 1 g intramuscular (IM) injection of ceftriaxone (an antibiotic). Other antibiotics are used if ceftriaxone cannot be used, for example because of an allergy. The MenB vaccine (a vaccine against meningococcal group B bacteria) can give some protection against gonorrhoea. It may be offered to men who have sex with men who are at higher risk of gonorrhoea.

The current recommended treatment pathway can be found here.


Syphilis

Syphilis infection is caused by the spirochete (spiral-shaped) Treponema pallidum bacterium. It has a characteristic four stage development if left untreated.


Primary Syphilis

This is the initial stage of a syphilis infection, presenting with a painless ulcer called a chancre at the site of sexual contact. Over the next few weeks, this ulcer will disappear, but during that time the patient is very infectious.


Secondary Syphilis

The secondary stage of a syphilis infection marks the dissemination (spread) of the bacteria around the body. It is characterised by systemic effects (effects on the whole body). A rash may appear on the body, with a fever, sores on the mucous membranes (the moist lining of the mouth and genitals), weight loss and general malaise (feeling unwell).

The patient is still very infectious at this stage. Secondary syphilis typically develops about 3 months after infection. It usually resolves on its own within 3 to 12 weeks, but without treatment the infection stays in the body.


Latent Syphilis

Following the secondary stage, the body pushes the disease into latency. At this point, the patient will have no symptoms, so latent syphilis is found by a blood test (serology, which detects antibodies) rather than by symptoms. Tests done for other reasons, such as antenatal screening (screening in pregnancy), sexual health screening or blood donation, may find it. If it is missed, it may only be found when a baby is born with congenital syphilis.


Tertiary Syphilis

This is the most severe stage of syphilis. It develops in about one third of untreated people, usually around 20 to 40 years after the initial infection, when the latent disease reactivates. Gummata can appear earlier, on average after about 15 years and sometimes within 2 years.

The symptoms of this stage of syphilis are severe:

  • Gummata - large sores that occur on the skin or on the internal organs.
  • Cardiovascular Effects - damage to the heart and blood vessels.
  • Neurosyphilis - nervous system damage. It can occur at any stage of syphilis, not only in the tertiary stage.


Investigation

Syphilis can be diagnosed either through a blood test or a swab of the primary ulcer if the patient presents at this early stage.


Treatment

The treatment of syphilis is with benzathine benzylpenicillin, given as a single intramuscular dose in early syphilis (primary, secondary and early latent) and as three weekly doses in late latent, cardiovascular and gummatous syphilis. Neurosyphilis needs treatment that reaches the cerebrospinal fluid (the fluid around the brain and spinal cord), such as procaine penicillin with probenecid for 14 days.

The current recommended treatment pathway can be found here.


Anogenital Warts

Anogenital warts (warts around the anus and genitals) are a very common viral STI, and are most often caused by Human papillomavirus (HPV) strains 6 and 11. The current vaccine used for HPV protects against these strains of HPV as well as HPV 16 and 18, which are the main causes of cervical cancer.

Anogenital warts typically present as painless warts on the penis or vulva (the external female genitals). They can also appear in the vagina, cervix (the neck of the womb) and perianal skin (the skin around the anus).


Treatment

There are many treatment options for the appearance of warts.

The first option is to leave them alone: anogenital warts are unsightly and infective, but they can safely be left untreated.

Topical creams and other treatments that the patient applies at home (for example podophyllotoxin and imiquimod) are also available to speed up healing. They cannot be used in pregnancy. If needed, more intense therapies such as cryotherapy (freezing them off) are possible. The choice depends on the type of wart and where the warts are.

However, getting rid of the warts will not get rid of the underlying infection, meaning that the warts can recur many times over a period of up to two years. After this time most people will have cleared the HPV infection, preventing recurrence unless reinfected.

The current recommended treatment pathway can be found here.


Herpes

Herpes is a viral infection caused by the Herpes Simplex Virus (HSV). There are two types of this virus, HSV-1 and HSV-2. Traditionally HSV-1 is associated with oral ulcers and HSV-2 is associated with genital ulcers. However, it has since been shown that both of the virus types can cause both oral and genital ulcers.

Infection with any strain of HSV is especially dangerous in pregnancy, as it can cause neonatal herpes which can be fatal to the newborn child.


Symptoms

Commonly presents with painful ulcers, dysuria or discharge in both men and women. Can be asymptomatic.

It is transmissible in asymptomatic and symptomatic states, but is more infectious with ulceration.


Investigation

Genital herpes is often suspected from the history and examination (a clinical diagnosis). The diagnosis should be confirmed by taking a swab from an ulcer for viral PCR (polymerase chain reaction, a test that detects the genetic material of the virus), ideally in a specialist sexual health service. Serology (a blood test for antibodies) has a limited role and is not routinely used for acute diagnosis.


Treatment

Oral aciclovir (an antiviral drug) is the mainstay of treatment for genital herpes. However, herpes is impossible to cure. Aciclovir can reduce the length of ulceration (the time the ulcers last) in an attack. Daily suppressive antiviral treatment (taken every day to reduce attacks) can reduce the frequency of recurrences while treatment continues. Neither treatment eradicates latent HSV (virus that stays dormant in the body), so symptoms may come back after treatment stops. On average, people have 4 to 5 recurrences a year after a first symptomatic episode caused by HSV-2. HSV-2 recurs about four times as often as HSV-1. Recurrences usually become less severe and less frequent over time.

Lifestyle modifications might also aid in relieving the symptoms associated with the ulceration, such as using an emollient such as Vaseline, and avoiding sharing towels with other family members.

The current recommended treatment pathway can be found here. 


Trichomoniasis

A sexually transmitted protozoal infection (an infection with a single-celled parasite) caused by Trichomonas vaginalis.

Symptoms

Men - often asymptomatic but can cause dysuria or discharge.

Women - typically yellow vaginal discharge that irritates the vulva and vagina, has a foul smell and may be frothy in appearance.


Investigation

High vaginal swabs in women and urethral or penile-meatal swabs (a swab of the opening at the tip of the penis, often taken by the patient) in men are tested using nucleic acid amplification tests (NAATs, which detect the genetic material of the organism) for diagnosis. Urine samples can be used in men if the local NAAT allows it.


Treatment

Oral metronidazole is the treatment of choice for Trichomonas vaginalis.

The current recommended treatment pathway can be found here.


Other Infections of the Genitourinary Tract (Non-Sexually Transmitted Infections)

This section of the article is dedicated to infections of the reproductive tract that can be, but are not always, transmitted sexually.


Scabies and Pubic Lice

Scabies and pubic lice are small parasites that cause irritation (itching) of the skin. Scabies is caused by a tiny mite that lays its eggs in the skin. Pubic lice are tiny insects that live on body hair, most often the pubic hair. Both can occur around the genital region, and scabies can affect any other region of skin. Both are spread mainly by close body contact, which is often sexual contact. Scabies can also spread through shared towels, clothes or bedsheets, especially in crusted scabies (a severe form with very large numbers of mites). Pubic lice rarely spread this way. The skin or hair is said to be infested rather than infected.


Bacterial Vaginosis

This vaginal infection is commonly caused by Gardnerella vaginalis but can be caused by many other anaerobic bacteria. It is caused by an imbalance in the normal flora of the vagina. Any practice that disrupts the vaginal flora and the normal pH of the vagina, including douching and washing inside the vagina, can cause the condition although the specific pathophysiology is unclear. Although not an STI itself it can increase the risk of contracting an STI.


Symptoms

Offensive smelling discharge that is often greyish in colour, but not associated with pruritus (itching) or pain.


Investigation

Diagnosis is usually clinical, supported by vaginal pH testing and/or microscopy. Routine culture is not recommended.


Treatment

Bacterial vaginosis without symptoms usually needs no treatment. For symptoms, oral metronidazole is the treatment of choice, as well as curtailing any risky practices such as douching.

The current recommended treatment pathway can be found here.


Vulvovaginal Candidiasis (Thrush)

This fungal infection of the vagina is commonly caused by Candida albicans and has multiple risk factors including immunosuppression (a weakened immune system, for example from HIV infection), pregnancy (higher oestrogen levels can lead to overgrowth of the fungus), diabetes (sugar in the urine encourages fungal growth), recent antibiotics (kill the local flora) and possibly the combined oral contraceptive pill (COCP), although evidence for this association is limited. Thrush can also present orally and is a common finding in elderly patients.


Symptoms

White, thick, non-offensive discharge associated with severe pruritus, pain and often dyspareunia.


Investigation

Investigation is not usually required in uncomplicated cases. High vaginal swabs may be considered if symptoms are recurrent, severe, or do not respond to treatment.


Treatment

Management of thrush can be tricky, especially if the precipitating risk factors cannot be treated. Thrush can often present as a recurring problem.

Treatment can be through creams, pessaries (tablets placed in the vagina) or oral antifungals (medicines that kill fungi) of the -azole class like the oral treatment fluconazole. Oral fluconazole must not be used in pregnancy. A vaginal clotrimazole pessary is used instead.

The current recommended treatment pathway can be found here.


Vaginal Discharge

Vaginal discharge is a common initial presentation of many of these diseases. It is therefore important to understand the different types of vaginal discharge as this will assist in achieving a diagnosis.

Vaginal discharge is normal, and it is normal for it to vary slightly in texture or amount throughout the menstrual cycle. It is important to emphasise that it is the change from normal for that patient that is a cause for concern.
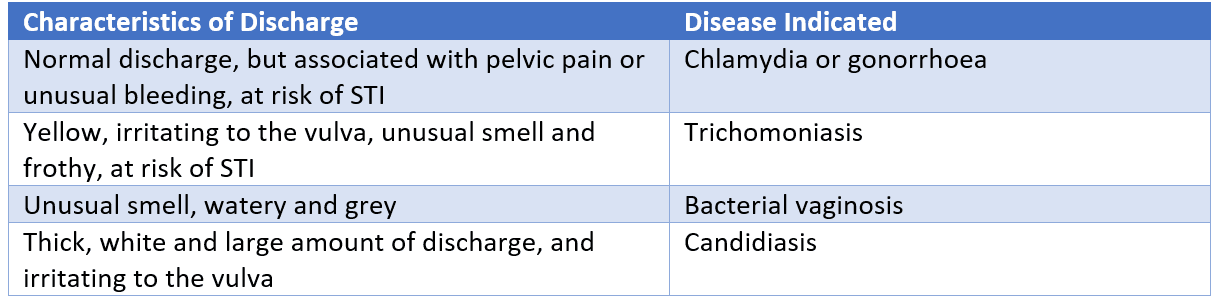
 

Vaginal Discharge SimpleMed

Table - The characteristics of vaginal discharge and the possible conditions associated with that presentation

SimpleMed original by Dr. Maddie Swannack


While the above table can be helpful in practice, it is also important to include the rest of the clinical picture when making a diagnosis.


Guidance is revised from time to time, so check the current version of the treatment pathways on the website https://cks.nice.org.uk/ before relying on any treatment in this article.


Edited by: Dr. Ben Appleby

Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge

Free account

Keep reading for free

Create a free account to continue reading Infections of the Reproductive Tract.

Your account includes:

  • Thousands of free practice questions
  • Tools to track your revision progress
Sign up free Already have an account? Log in

No payment. No spam. Just free medical revision.

Quiz

Preview the Infections of the Reproductive Tract quiz

Practice this topic

Free single best answer questions written by UK doctors, with an explanation after every answer.
  • Infections of the Reproductive Tract: free SBA questionsQuestions on this article→
  • Reproductive System question bankEvery question in this subject→
  • Free medical question bankAll subjects, with full explanations→
SimpleMed+ EncyclopaediaShort and simple explanations of hard topics, with memory aids→
SimpleMed+

Want More?

Access more on SimpleMed+

Lock it in with practice questions, the full question bank and revision tools that track what you know.

Practice now
5233
simplemedlonglogo.png
  • Home
  • Terms & Conditions
  • Privacy Policy
  • Contact

The medical information on this site is provided as an information resource only, and is not to be used or relied on for any diagnostic or treatment purposes. This information is intended for medical education, specifically to biological/medical learning inclined individuals, and does not create any doctor-patient relationship, and should not be used as a substitute for professional diagnosis and treatment.

©2026 Lili's Ark Limited, UK Company #15424953
S+

Search

  • Pre-Clinical
    • Cardiovascular System
      • 1. Anatomy of the Cardiovascular System
      • 2. The Cardiac Cycle
      • 3. Pulses and Pressures
      • 4. Control of Cardiac Output
      • 5. Cardiac Conduction and Contraction
      • 6. Embryology of the CVS
      • 7. Congenital Heart Defects
      • 8. Hypertension
      • 9. Electrocardiograms
      • 10. Electrocardiogram Pathology
      • 11. Cardiovascular Drugs
      • 12. Murmurs
      • 13. Special Circulations
      • 14. Heart Failure
      • 15. Artery and Vein Disease
      • 16. Acute Coronary Syndromes
      • 17. Haemodynamic Shock
    • Musculoskeletal System
      • The Human Body
        • 1. Anatomical Terms
        • 2. Structure of the Muscles
        • 3. Muscles in Action
        • 4. Connective Tissue
        • 5. Cartilage: Structure, Growth and Repair
        • 6. Structure of Bones
        • 7. Basics of Bone Anatomy
        • 8. Joints
        • 9. The Spine
        • 10. Dermatomes and Myotomes
        • 11. The Brachial Plexus
        • 12. The Lumbar Plexus
        • 13. The Sacral Plexus
      • Clinical Conditions
        • 1. Conditions of the Foot
        • 2. Conditions of the Ankle
        • 3. Conditions of the Lower Leg
        • 4. Conditions of the Knee
        • 5. Conditions of the Thigh
        • 6. Conditions of the Hip
        • 7. Conditions of the Lower Back
        • 8. Conditions of the Back and Neck
        • 9. Conditions of the Shoulder and Clavicle
        • 10. Conditions of the Arm
        • 11. Conditions of the Elbow
        • 12. Conditions of the Forearm and Wrist
        • 13. Conditions of the Hand
      • Musculoskeletal Anatomy
        • 1. Muscles of the Gluteal Region
        • 2. Muscles of the Thigh
        • 3. Key Areas of the Lower Limb
        • 4. Bones of the Lower Limb
        • 5. Bones of the Foot
        • 6. Muscles of the Lower Leg
        • 7. Bones of the Upper Limb
        • 8. Muscles of the Shoulder
        • 9. Muscles of the Upper Arm
        • 10. Bones of the Hand
        • 11. Muscles of the Forearm
        • 12. Key Areas of the Upper Limb
    • Cell Physiology & Biology
      • 1. An Introduction to the Cell
      • 2. Introduction to DNA
      • 3. The Cell Cycle, Checkpoints and Apoptosis
      • 4. Structure of Proteins
      • 5. Protein Function in Oxygen Transport
      • 6. Enzymes and Regulation of Protein Function
      • 7. Molecular Techniques for Medics
      • 8. Post-translational Modification and Collagen Biosynthesis
      • 9. Protein Targeting
      • 10. Biological Membranes
      • 11. G-Protein Coupled Receptor
      • 12. Enzyme-linked and Intracellular Receptor Signalling
      • 13. Membrane Transport and Intracellular Calcium Regulation
      • 14. Membrane Potentials
      • 15. Action Potentials
      • 16. Autonomic Nervous System Introduction
    • Metabolism
      • 1. Nutrition, Diet and Body Weight
      • 2. Energy Reactions in Cells
      • 3. Dietary Energy Production
      • 4. Vitamins, Cofactors, Minerals and Trace Elements
      • 5. Glycolysis
      • 6. Oxygen-dependent Pathway
      • 7. Lipid Metabolism and Transport
      • 8. Protein and amino acid metabolism
      • 9. Purine and Pyrimidine Metabolism
      • 10. Inborn Errors of Metabolism and Newborn Screening
      • 11. Alcohol Metabolism
      • 12. Oxidative Stress
      • 13. Energy Storage
      • 14. Temperature Regulation
      • 15. Metabolic and Endocrine Regulation
    • Endocrinology
      • 1. An Introduction to Endocrinology
      • 2. Control of Appetite
      • 3. The Adrenal Glands and Adrenal Disorders
      • 4. HPA and Growth Hormone
      • 5. Pituitary Disorders
      • 6. The Thyroid Gland
      • 7. The Endocrine Pancreas
      • 8. Diabetes Mellitus
      • 9. Calcium Metabolism
    • Haematology
      • 1. Haematopoiesis and the Spleen
      • 2. Full Blood Count
      • 3. Blood Groups, Crossmatching and Transfusion Reactions
      • 4. Anaemia
      • 5. Vitamin B12 and Folate
      • 6. Iron Metabolism
      • 7. Haemoglobinopathies
      • 8. When Haematopoiesis goes wrong
      • 9. Haematology in Systemic Disease
    • Genetics
      • 1. Mitosis and Meiosis
      • 2. Genotype, Phenotype and Inheritance
      • 3. Gene Expression
      • 4. Epigenetics, Genomic Imprinting and Mitochondrial Inheritance
      • 5. Introduction to Gene Mutation
      • 6. DNA Repair and Cancer
      • 7. Genetic Testing and Counselling
    • Infection
      • 1. An Introduction To Infection
      • 2. The Infection Model
      • 3. Bacterial Structure, Classification and Growth
      • 4. Biofilms
      • 5. Innate Immunity
      • 6. Adaptive Immunity
      • 7. Gram Staining and Infection Investigations
      • 8. Staphylococci and Other Gram-positive Bacteria
      • 9. Streptococci
      • 10. Gram-negative Bacteria: Structure, Entry Routes and Endotoxin
      • 11. The Organisms Gram Staining Misses
      • 12. Sepsis
      • 13. Antibiotics
      • 14. Principles of Medical Virology
      • 15. Hepatitis
      • 16. Human Immunodeficiency Virus
      • 17. Fungi and Parasites: The Eukaryotic Pathogens
      • 18. The Immunocompromised Host
      • 19. Travel-related Infections
    • Pathology
      • 1. An Introduction to Pathology
      • 2. How to Read a Histology Slide
      • 3. The Basics of Pathology
      • 4. Epithelium, Skin and Exocrine Glands
      • 5. Acute Inflammation
      • 6. Chronic Inflammation
      • 7. Regeneration and Repair of Tissues
      • 8. The Lymphatic System
      • 9. Haemostasis and Clotting
      • 10. Thrombosis and Embolism
      • 11. Atherosclerosis
      • 12. Cellular Adaptations
      • 13. Introduction to Neoplasia
      • 14. Pathogenesis of Neoplasms
      • 15. Behaviour of Neoplasms
    • Population & Social Science
      • 1. Introduction to Population Science
      • 2. Describing Data and Testing Hypotheses
      • 3. Epidemiological Studies
      • 4. Models of Health
      • 5. Beliefs of the Public
      • 6. Health Economics
      • 7. Evidence-Based Practice
      • 8. Patient Safety and Quality Control
      • 9. Summary and Glossary
    • Patient-Centred Care
      • 1. Lifestyle Medicine
      • 2. Childhood Immunisations
      • 3. Sepsis in Paediatrics
      • 4. Child Safeguarding
      • 5. Ageing
      • 6. Falls
      • 7. Men's Health
      • 8. Palliative Care
    • Reproductive System
      • 1. Anatomy of the Man
      • 2. Anatomy of the Woman
      • 3. The Pelvic Floor
      • 4. Development of the Reproductive System
      • 5. Puberty
      • 6. The Menstrual Cycle and Menstrual Abnormalities
      • 7. Gametogenesis
      • 8. Sex, Infertility and Contraception
      • 9. Physiology of the Mother
      • 10. Diseases of the Mother in Pregnancy
      • 11. Physiology of the Fetus
      • 12. The Placenta
      • 13. Labour and Delivery
      • 14. The Postpartum Period
      • 15. Infections of the Reproductive Tract
      • 16. Pelvic Inflammatory Disease
      • 17. The Menopause
      • 18. Malignancies of the Reproductive Tract
      • 19. Introduction to the Breast
      • 20. Benign Conditions of the Breast
      • 21. Malignant Breast Disease
    • Respiratory System
      • 1. Anatomy of the Respiratory System
      • 2. Development of the Respiratory System
      • 3. Ventilation and Lung Mechanics
      • 4. Properties of Gas Exchange
      • 5. Carbon Dioxide Transport
      • 6. Chemical Control of Breathing and Plasma pH
      • 7. Lung Function Testing
      • 8. Pulmonary Embolism
      • 9. Asthma
      • 10. Chronic Obstructive Pulmonary Disease
      • 11. Pneumonia and other Lower Respiratory Tract Infections
      • 12. Bronchiectasis and Cystic Fibrosis
      • 13. Tuberculosis
      • 14. Pneumothorax and Pleural Effusion
      • 15. Lung Cancer
      • 16. Respiratory Failure
    • Urinary System
      • 1. Anatomy of the Kidneys, Bladder and Urethra
      • 2. Development of the Urinary System
      • 3. The Nephron
      • 4. The Glomerulus – Tubular Reabsorption and Secretion
      • 5. Control of Plasma Volume
      • 6. Control of Plasma Osmolarity
      • 7. Control of Potassium
      • 8. Micturition
      • 9. Diuretics
      • 10. Glomerular Filtration Rate and the Measurement of Kidney Function
      • 11. Hyponatraemia
      • 12. Urinary Incontinence
      • 13. Glomerular Disease
      • 14. Diabetic Nephropathy
      • 15. Acute Kidney Injury
      • 16. Chronic Kidney Disease
      • 17. Urinary Tract Obstruction
      • 18. Urinary Tract Infections
      • 19. Prostate Pathology
      • 20. Male Urological Conditions
      • 21. Urological Malignancy
    • Gastrointestinal System
      • 1. Development of the Gastrointestinal Tract
      • 2. Abdominal Wall and Inguinal Canal
      • 3. Anatomy and Physiology of the Foregut
      • 4. Anatomy and Physiology of the Midgut
      • 5. Anatomy and Physiology of the Hindgut
      • 6. Gastrointestinal Motility and the Enteric Nervous System
      • 7. Liver, Biliary and Exocrine Pancreatic Physiology
      • 8. Gastrointestinal Secretion, Digestion and Absorption
      • 9. Upper Gastrointestinal Pathology
      • 10. Hepatic, Biliary and Pancreatic Pathology
      • 11. Intestinal Pathology
      • 12. Distal Gastrointestinal Tract Pathology
      • 13. Gastrointestinal Malignancy
      • 14. Gastroenteritis and Enterocolitis
      • 15. Gastrointestinal Emergencies
    • Head & Neck
      • 1. Introduction to Head & Neck Anatomy
      • 2. Blood Supply of the Head and Neck
      • 3. Lymph Nodes and Neck Lumps
      • 4. The Skull
      • 5. The Temporomandibular Joint
      • 6. The Meninges
      • 7. Cranial Nerves I-VI
      • 8. Cranial Nerves VII-XII
      • 9. Development of the Head and Neck
      • 10. Autonomics in the Head and Neck
      • 11. Anatomy of the Ear
      • 12. Ear Pathology
      • 13. The Nose
      • 14. The Oral Cavity and Pharynx
      • 15. The Eye
      • 16. The Larynx
      • 17. Head and Neck Cancers
      • 18. Imaging of the Head and Neck
      • 19. Fascial Planes, Muscles and Triangles
    • Immunology
      • 1. An Introduction to Hypersensitivity
      • 2. Type 1 Hypersensitivity
      • 3. Food Allergy
      • 4. Introduction to Autoimmunity
      • 5. Rheumatoid Arthritis
      • 6. Systemic Lupus Erythematosus (SLE)
      • 7. Immunological Therapies | Monoclonal Antibodies
    • Neuroanatomy & Psychiatry
      • 1. Basics of Neuroanatomy
      • 2. Cells and Components of the Nervous System
      • 3. Arterial Supply to the Brain
      • 4. Development of the Nervous System
      • 5. Production and Circulation of CSF and Related Disorders
      • 6. Somatosensory System
      • 7. Motor System
      • 8. The Cerebellum: Circuits, Coordination and Clinical Signs
      • 9. Visual System
      • 10. Auditory and Vestibular Systems
      • 11. The Hypothalamus and Limbic System
      • 12. Higher Cortical Function
      • 13. Reticular Formation
      • 14. Movement Disorders
      • 15. Infections of the Central Nervous System
      • 16. Dementia
      • 17. Delirium
      • 18. Headaches
      • 19. Stroke
      • 20. Raised Intracranial Pressure (ICP)
      • 21. Subarachnoid Haemorrhage
      • 22. Anxiety
      • 23. Mood Disorders
      • 24. Psychosis
    • Embryology
      • 1. The Basics of Embryology
      • 2. Development of the Limbs and Body Wall
      • 3. Teratology and Congenital Malformations
      • 4. Development of the Gastrointestinal Tract
      • 5. Development of the Reproductive Systems
      • 6. Development of the Urinary System
      • 7. Development of the Respiratory System
      • 8. Development of the Head and Neck
      • 9. Development of the Nervous System
      • 10. Embryology of the Cardiovascular System
    • Pharmacology
      • 1. Research Methods in Pharmacology
      • 2. Pharmacokinetics
      • 3. Pharmacodynamics
      • 4. Pharmacovigilance and Pharmacogenetics
      • 5. Safe Prescribing
      • 6. Cholinergic Pharmacology
      • 7. Adrenergic Pharmacology
      • 8. Hypertension and Heart Failure
      • 9. Cardiac Arrhythmias
      • 10. Antiplatelets, Anticoagulants and Thrombolysis
      • 11. Hyperlipidaemias
      • 12. Diuretics and Renal Pharmacology
      • 13. Pharmacology of Insulin
      • 14. Reproductive and Post-reproductive Health
      • 15. Antibiotics
      • 16. Antivirals
      • 17. Cancer Chemotherapy
      • 18. Anaesthetics
      • 19. Opioids
      • 20. Introduction to Psychopharmacology
      • 21. Epilepsy and Anti-epileptic Drugs
      • 22. Parkinson's Disease and Myasthenia Gravis
      • 23. NSAIDs
      • 24. Immunosuppression and Disease-modifying Therapy
      • 25. Pharmacology of Airway Control
      • 26. Drugs Affecting Acid Secretion
      • 27. Antiemetics and Laxatives
      • 28. Poisoning and STOPP/START
  • OSCE
    • Index Conditions for OSCE exams
    • Cardiovascular System Examination
    • Shoulder Examination
    • Hand Examination
    • Venepuncture
    • Blood Pressure
    • Respiratory System OSCE Examination
    • Peripheral Vascular OSCE Examination
    • Varicose Vein OSCE Examination
    • Deep Vein Thrombosis (DVT) OSCE Examination
    • Abdominal OSCE Examination
    • Rectal (PR) OSCE Examination
    • Stoma OSCE Examination
    • Hernia OSCE Examination
    • Upper Limb Neurological OSCE Examination
    • Lower Limb Neurological OSCE Examination
    • Cranial Nerve OSCE Examination
    • Cerebellar OSCE Examination
    • GALS Screening OSCE Examination
    • Elbow OSCE Examination
    • Hip OSCE Examination
    • Knee OSCE Examination
    • Ankle and Foot OSCE Examination
    • Spine OSCE Examination
    • Thyroid Status OSCE Examination
    • Diabetic Foot OSCE Examination
    • Cushing's Syndrome OSCE Examination
    • Acromegaly OSCE Examination
    • Ear, Otoscopy and Hearing OSCE Examination
    • Nasal OSCE Examination
    • Eye and Vision OSCE Examination
    • Fundoscopy (Ophthalmoscopy) OSCE Examination
    • Visual Acuity OSCE Assessment
    • Anterior Segment Eye OSCE Examination
    • Pigmented Skin Lesion OSCE Examination
    • Rash and Non-Pigmented Skin Lesion OSCE Examination
    • Breast OSCE Examination
    • Testicular OSCE Examination
    • Neck Lump OSCE Examination
    • Lymphoreticular OSCE Examination
  • Question Bank
  • About
  • How to Use SimpleMed
  • SimpleMed Lecture Series
  • DON'T PANIC - Guide to the Wards
  • SimpleMed Plus
Your privacy We use optional cookies for analytics and advertising, to improve SimpleMed and measure our ads. Privacy policy
