

Next Lesson - Systemic Lupus Erythematosus
Core
Rheumatoid arthritis (RA) is an autoimmune inflammatory disease with systemic features (effects outside the joints) that typically presents as a symmetrical inflammatory polyarthritis (inflammation of many joints at once, affecting the same joints on both sides of the body). It is believed to be caused by a combination of genetic and environmental factors. It is a relatively common condition, with a prevalence of about 1% of the UK population. It is about 2 to 4 times more common in females than in males. It often starts in adulthood but can occur at any age. Onset peaks between the ages of 30 and 50 years, while the peak age of incidence in the UK is in the 70s (source).
The textbook presentation of rheumatoid arthritis can be memorised as the 3 S's:
- Stiffness - usually reported as early morning stiffness lasting for over 30 minutes, often over 1 hour
- Swelling - persistent joint swelling, commonly in the hands
- Squeezing - squeezing the metacarpophalangeal (MCP) joints (the knuckles at the base of the fingers) together during examination is usually painful
An important differential to exclude when making a diagnosis of rheumatoid arthritis is osteoarthritis (OA). Here are some key characteristics of each to help differentiate between the two:

Table - The symptomatic differences between rheumatoid arthritis and osteoarthritis
RA and OA can also be differentiated by characteristic radiological features. Features of RA can be remembered as LESS, and those of OA can be remembered as LOSS.

Table - The differentiating radiological features between rheumatoid arthritis and osteoarthritis
If left untreated, RA can lead to severe joint deformities, but these are much rarer nowadays with the advent of better treatments. The deformities can be remembered by the following mnemonic: BUS Z.
- Boutonnière Deformity - proximal interphalangeal joint (PIP) flexion (the middle joint of the finger stays bent) and distal interphalangeal joint (DIP) hyperextension (the joint at the end of the finger bends backwards beyond its normal range)
- Ulnar Deviation - the fingers drift towards the little-finger side of the hand because of subluxation (partial dislocation) at the swollen metacarpophalangeal joints (MCPs, the knuckles)
- Swan-neck Deformity - proximal interphalangeal joint (PIP) hyperextension and distal interphalangeal joint (DIP) flexion
- Z-thumb (duck-bill deformity) - MCP flexion with IP hyperextension (the interphalangeal, or IP, joint nearest the tip of the thumb bends backwards beyond its normal range). This thumb posture differs from swan-neck deformity of the fingers, which combines PIP hyperextension with DIP flexion.
Routine tests to consider for a patient suspected to have RA should include:
- Full Blood Count (FBC) - which could show signs of anaemia of chronic disease (anaemia caused by long-term inflammation) and a raised platelet count (thrombocytosis), which can occur in RA.
- C-reactive Protein (CRP) - which can be elevated as it is a marker of inflammation although it can be within the normal range, particularly in early disease.
- Erythrocyte Sedimentation Rate (ESR) - which can be elevated in proportion to the level of inflammation.
- Liver and kidney function tests (LFTs and U&Es, urea and electrolytes) can also be requested to help choose safe management options.
NICE advises an X-ray of the hands and feet in adults with suspected RA and persistent synovitis (joint swelling from inflammation of the joint lining that does not settle). Ultrasound scans and MRI are more sensitive than X-ray to erosions (areas where the bone has been worn away), but whether they are used depends on local policy and availability.
Two blood tests look for autoantibodies (antibodies that attack the body’s own tissues) to aid diagnosis. NICE advises testing for rheumatoid factor in adults with suspected RA who have synovitis, and considering anti-CCP antibodies if rheumatoid factor is negative. A negative result does not rule out RA. The two tests are:
- Rheumatoid Factor (RF) - it is positive in about 60 to 70% of people with RA, so a negative result does not rule RA out. It can also be positive in people without RA, and high levels are linked to a higher risk of extra-articular complications (problems outside the joints).
- Anti-cyclic Citrullinated Peptide (anti-CCP) - this is more specific for RA than rheumatoid factor (about 95%, so few people without RA test positive) and is positive in about two-thirds to 80% of people with RA (its sensitivity).
The 2010 ACR/EULAR classification criteria for RA are a useful tool to support the classification of RA in the appropriate clinical context. A score of ≥6/10 meets the classification threshold in a patient with clinical synovitis in at least one joint that is not better explained by another diagnosis. These criteria support classification and do not replace clinical judgement.
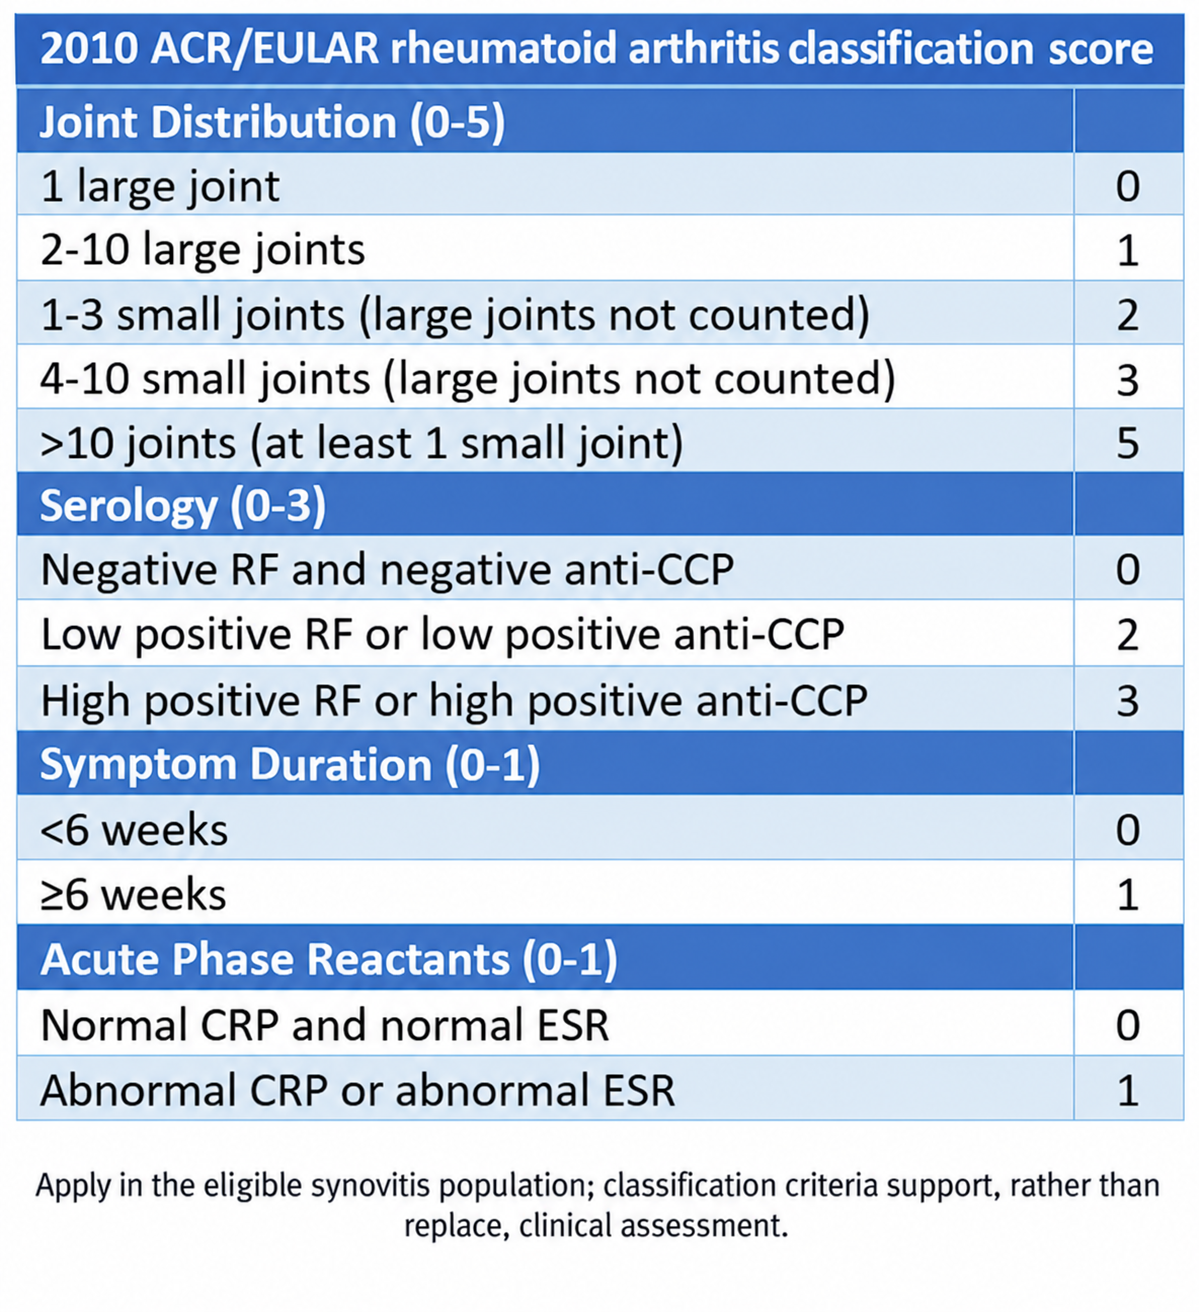
Table - 2010 ACR/EULAR classification criteria for RA. A score of ≥6/10 meets the classification threshold in a patient with clinical synovitis in at least one joint, when no other diagnosis better explains the synovitis. Classification is distinct from clinical diagnosis; the duration point applies from 6 weeks onwards.
Any adult with suspected persistent synovitis of undetermined cause should be referred to rheumatology (the specialty that looks after joint and autoimmune disease) for a specialist opinion. Referral should be urgent (within 3 working days of presentation, according to CKS) if the small joints of the hands or feet are affected, more than one joint is affected, or there has been a delay of 3 months or longer between the onset of symptoms and seeking medical advice. Investigations ordered in primary care should not delay referral, and normal inflammatory markers or negative antibody results do not make it less urgent. Initial management is then usually provided in secondary care. Rheumatologists should perform a thorough examination of the joints and quantify the disease activity with the DAS28 (disease activity score), which assesses 28 different joints commonly affected in RA. NICE advises measuring CRP and disease activity (with a composite score such as the DAS28) monthly in specialist care until the treatment target of remission or low disease activity is reached.
The mainstay of treatment of RA is early use of disease-modifying anti-rheumatic drugs (DMARDs). Short-term steroids may be used as bridging therapy (treatment to control symptoms until the DMARDs start working) or during flares (sudden worsening of symptoms) to control inflammation while DMARDs take effect. Early use of DMARDs can improve disease outcomes and prevent progression of the disease. DMARDs should ideally be started within 3 months of the onset of persistent symptoms and can take 6 to 12 weeks to produce noticeable effects.
Commonly prescribed DMARDs include methotrexate, hydroxychloroquine, sulfasalazine and leflunomide. NICE advises starting with methotrexate, leflunomide or sulfasalazine on its own (monotherapy) as first-line treatment, with hydroxychloroquine as an alternative for mild disease, and adding further DMARDs if the treatment target is not reached. Newer DMARDs, such as biological DMARDs and targeted synthetic DMARDs, are further options when intensive treatment with two or more conventional DMARDs used together has not worked. Steroids help to reduce inflammation and alleviate symptoms. Because long-term steroid use has complications, steroids are ideally used only for short courses, either as bridging therapy when starting a DMARD or for acute flare-ups. Prednisolone (by mouth) and methylprednisolone (by injection into a muscle or a joint) are commonly used steroids in RA.
Importantly, patients should be informed that steroids and many DMARDs are immunosuppressive (they lower the activity of the immune system), which gives an increased susceptibility to infection. They also require regular monitoring of their FBC and LFTs (and kidney function) to screen for neutropenia (low neutrophil count) or inflammation of the liver caused by the drugs. Some DMARDs have other specific side effects, for example hydroxychloroquine can damage the retina.
Other non-surgical (conservative) measures to be provided in combination with pharmacological management are specialist physio and occupational therapies (help with everyday tasks) to help patients improve their quality of life and minimise the disease impact. Smoking cessation should also be recommended and encouraged as smoking can worsen symptoms in RA.
Finally, surgery might be required in advanced cases or to relieve common complications such as carpal tunnel syndrome (compression of the median nerve at the wrist).
The systemic nature of the inflammation in RA can lead to a range of complications. In the wrist, swelling of the joint space can lead to carpal tunnel syndrome (compression of the median nerve at the wrist) and vascular inflammation (vasculitis, inflammation of the blood vessel walls) can cause skin ulcers. On the skin, RA can manifest through rheumatoid nodules (firm lumps under the skin). Patients with RA also have an increased risk of cardiovascular disease, pericarditis (inflammation of the pericardium, the sac around the heart), parenchymal lung disease (disease of the lung tissue itself), osteoporosis (thinning of the bones), serious infections and lymphoma.
A rarer but serious complication of RA to look for is Felty’s syndrome, which is characterised by a triad of rheumatoid arthritis, splenomegaly (enlarged spleen) and neutropenia (low neutrophil count). This puts patients at high risk of recurrent infections.
Other complications can also be associated with side effects of the drugs used in the management of rheumatoid arthritis. Examples are infection (steroids and immunosuppressive drugs increase the risk), bone marrow suppression (low blood cell counts) and liver inflammation, which is why regular blood tests are needed.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 1026
