

SimpleMedSimpleMed
Hit enter to search or ESC to close

Get in Touch

Contact Us

Use our contact form.

The Pelvic Floor

Share:

By Dr. Maddie Swannack

Next Lesson - Development of the Reproductive System

Reproductive System


Contents

  1. Functions of the Pelvic Floor
    • Support of the Pelvic Organs
    • Continence
    • Intra-abdominal Pressure
    • Childbirth
  2. Composition of the Pelvic Floor
    • Deep Muscles
    • Superficial Muscles
    • Ligaments
    • Perineal Body
    • Urogenital Diaphragm
  3. Pelvic Floor Dysfunction
    • Pelvic Organ Prolapse
    • Urinary Incontinence
  4. Trauma to the Pelvic Floor
    • Childbirth
    • Episiotomies
  5. Pelvic Floor Exercises
  6. Quiz

Abstract

  • The pelvic floor has many functions. It supports the pelvic organs (especially with increased intra-abdominal pressure), is important in continence (control over passing urine and faeces), and helps to facilitate childbirth.
  • The pelvic floor is made up of:
    • The levator ani muscles (deep muscles) - pubococcygeus, puborectalis and iliococcygeus
    • The superficial muscles - bulbospongiosus, ischiocavernosus and superficial transverse perineal
    • The ligaments - cardinal ligaments, pubocervical ligaments and uterosacral ligaments
    • The perineal body
    • The urogenital diaphragm 
  • The neurovascular supply to the pelvic floor includes the pudendal nerve and vessels to the perineum (the area between the external genitalia and the anus), as well as direct branches from the sacral nerve roots S3 to S5 to the levator ani muscles.
  • The organs of the pelvis can collapse into the space occupied by the vagina. An anterior prolapse involves the bladder (cystocele) or urethra (urethrocele). A central prolapse involves the uterus or the ‘vault’ of the vagina following hysterectomy (surgical removal of the uterus). A posterior prolapse involves the rectum (rectocele) or loops of bowel (enterocele).
  • Risk factors for pelvic organ prolapse include age, parity (the number of times a woman has given birth), oestrogen deficiency and increased abdominal pressure. Management can be non-surgical (pessaries, which are devices placed in the vagina to support the organs) or surgical (repair or lifting of the prolapsed organs). Vaginal mesh is now used only if there is no alternative.
  • Urinary incontinence relating to the pelvic floor is stress incontinence. Risk factors include increased age and oestrogen deficiency. Management includes pelvic floor muscle training, and slings.
  • The pelvic floor is often damaged in childbirth. This can be through accidental trauma such as tears, or surgical trauma such as an episiotomy (a cut made in the perineum to widen the birth canal). NICE advises against routine episiotomy. In some births, such as forceps deliveries, it may prevent a severe tear that damages the anal sphincter.

Core

Functions of the Pelvic Floor

Support of the Pelvic Organs

Support is facilitated by 3 main methods.

Suspension - this maintains the pelvic organs in the pelvic cavity by providing a strong, sling-like support inferiorly in the pelvis.

Attachment - the vagina is supported by its attachments to the endopelvic fascia (the connective tissue that surrounds and supports the pelvic organs), levator ani muscles and the perineal body.

Fusion - support from the fusion of the urogenital diaphragm and the perineal body.


Continence

A key function of the pelvic floor is to facilitate urination and defecation and to maintain continence when not attempting to use the toilet.


Intra-abdominal Pressure

The pelvic floor maintains the position of the pelvic organs during episodes of high intra-abdominal pressure, such as sneezing, coughing, or laughing.


Childbirth

The birth canal passes through the pelvic floor, which stretches to facilitate childbirth.


Composition of the Pelvic Floor

Deep Muscles

The levator ani are a U-shaped set of muscles that encircle the urethra, vagina and rectum. Anchored to the pubis (the front of the hip bone) and ischial spine (a bony point on the side wall of the pelvis), with fibres arising from the obturator fascia (the connective tissue covering the obturator internus muscle on the side wall of the pelvis), they spread in a fan shape and act like a sling to support the pelvic organs. The levator ani has three components: pubococcygeus, puborectalis and iliococcygeus. The names of the muscles denote their attachments. For example, pubococcygeus starts at the pubis (its origin) and ends at the coccyx (its insertion). Some fibres, particularly from pubococcygeus, contribute to the perineal body in the midline, while others form slings around the pelvic viscera (the pelvic organs).

The levator ani muscles sit very close to the coccygeus muscle, which is one of the deep muscles of the pelvic floor but is not part of the levator ani group.


Superficial Muscles

There are also three superficial muscles: bulbospongiosus (surrounds the vaginal opening in females or sits around the base of the penis in males), ischiocavernosus (along the line of the ischium), and the superficial transverse perineal. They aid in continence. If there is traumatic injury to the perineum these muscles can be damaged. For example, in childbirth a second degree tear (a tear into the perineal muscles) involves bulbospongiosus, and sometimes the superficial transverse perineal. In some episiotomies (cuts made in the perineum to widen the birth canal), fibres of the superficial transverse perineal may be cut to aid childbirth. An episiotomy does not reliably prevent perineal tears and is performed only when clinically indicated.
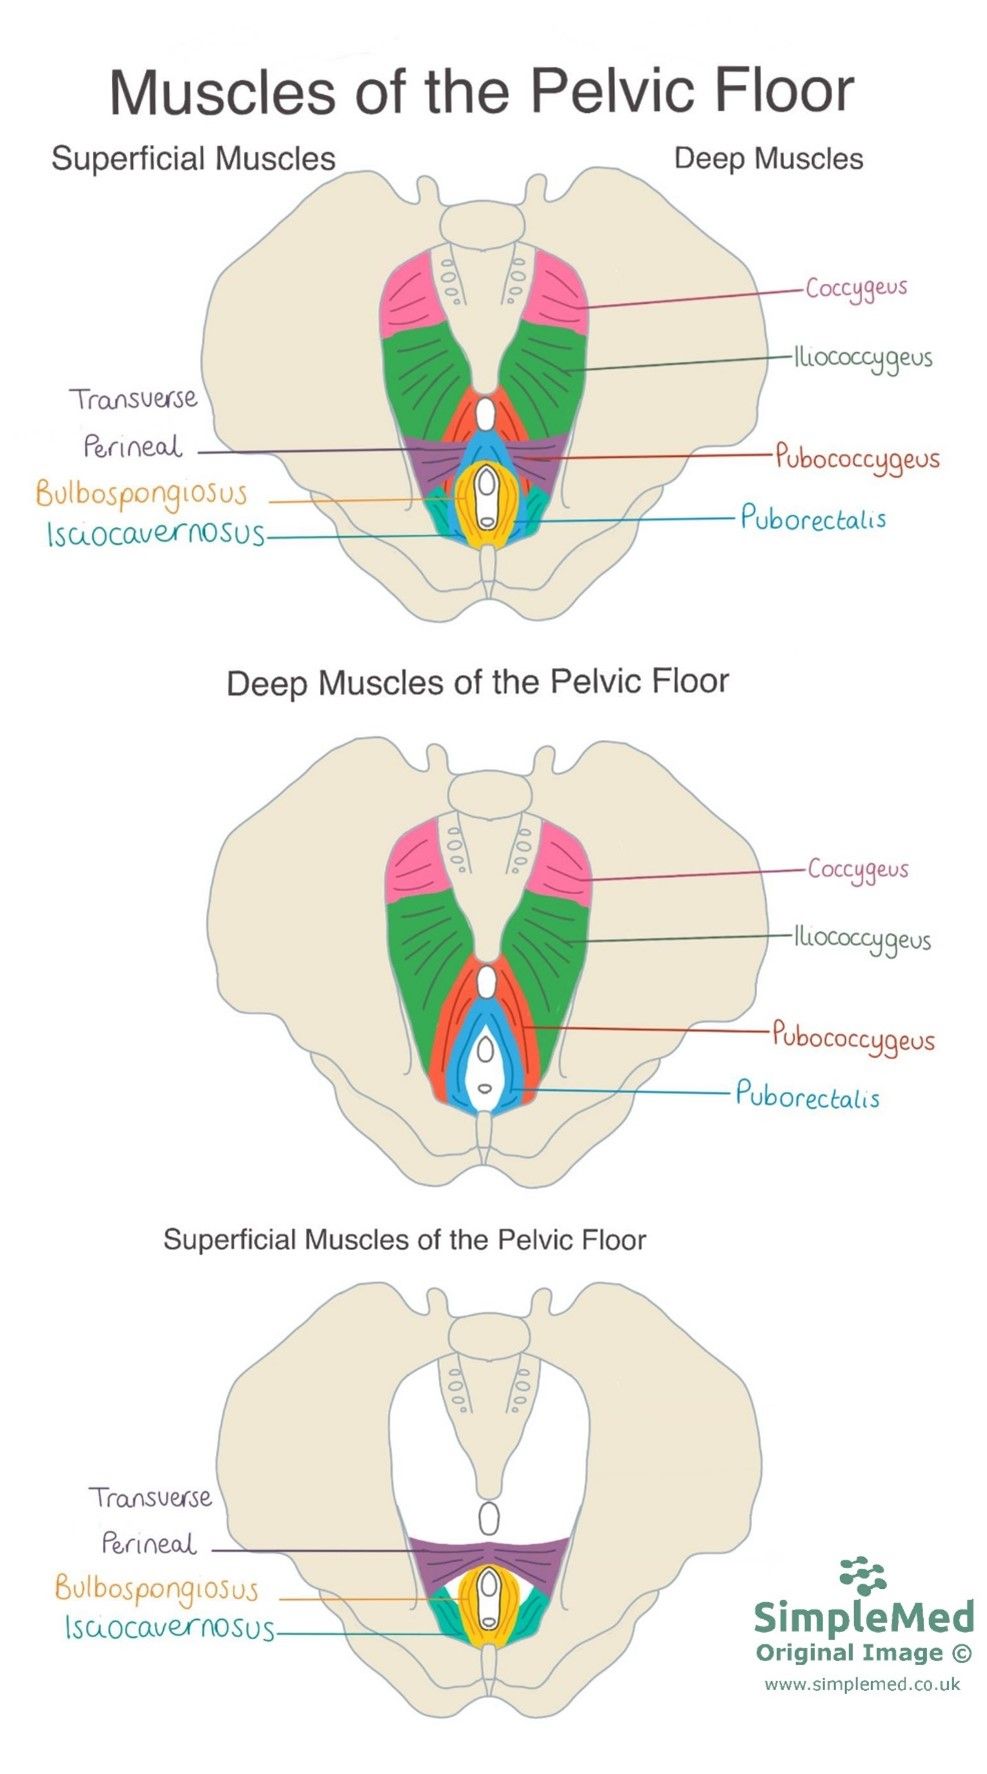
 

Muscles of the Pelvic Floor SimpleMed

Diagram - Muscles of the pelvic floor. It is divided into superficial and deep layers (shown together on the top image and then separately in the next two images)

SimpleMed original by Dr. Maddie Swannack


Ligaments

The three ligaments below all aid in the support of the uterus.

The cardinal ligaments (also known as the transverse ligaments) are situated along the inferior border of the broad ligament of uterus (a sheet of tissue draped over the uterus, tubes and ovaries). They arise from the side of the cervix and the lateral fornix of the vagina (the side of the recess around the cervix), and attach to the lateral pelvic wall at the level of the ischial spine.

The pubocervical ligaments attach from the cervix to the posterior surface of the pubic symphysis (the joint at the front of the pelvis where the two pubic bones meet).

The uterosacral ligaments attach the cervix to the sacrum. They are also known as the rectouterine ligaments and support the uterus.
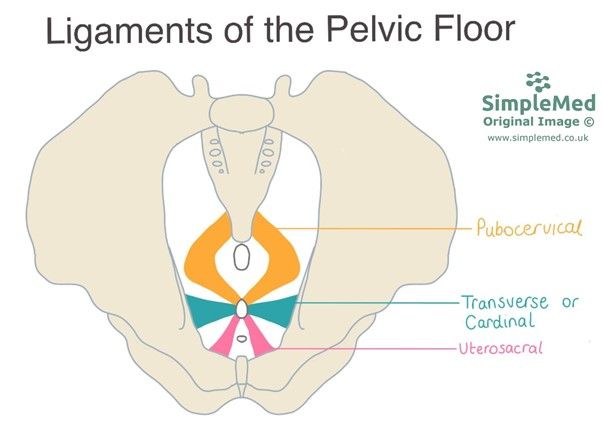
 

Ligaments of the Pelvic Floor SimpleMed

Diagram - Ligaments of the pelvic floor

SimpleMed original by Dr. Maddie Swannack


Perineal Body

The perineal body is a mass of muscle and fibrous tissue at the central point of the perineum (the area between the external genitalia and the anus). Several muscles of the pelvic floor and perineum attach to it. It lies between the vagina and the anus. It is key in maintaining support for the organs of the pelvis.


Urogenital Diaphragm

This term is traditionally used to describe the structures of the deep perineal pouch (a space below the pelvic floor muscles that contains part of the urethra, the external urethral sphincter and the vagina) in the anterior part of the pelvic floor, including muscles and associated fascia related to the urethra, vagina and perineal body.


Neurovasculature

The pudendal nerve, pudendal arteries and pudendal veins supply the pelvic floor and perineum. The word pudendal comes from a Latin word meaning ‘to be ashamed’, because the nerve supplies the perineum and genitalia.


Pelvic Floor Dysfunction

Pelvic Organ Prolapse (POP)

The uterus, bladder or rectum can all collapse into the vaginal space if inadequately supported. This can have various sexual, urinary or gastrointestinal side effects including pain or discomfort during sex, constipation and a feeling that the bladder is not emptying fully, and can be very psychologically troubling for the patient. Prolapses will often present with a feeling of dragging, bulging or a sensation of tissue descending into the vagina.

Prolapses can be classified by their origin.

An anterior prolapse involves organs anterior to the vagina including:

  • Cystocele - bladder prolapses into the vaginal space
  • Urethrocele - urethral collapse
  • Cystourethrocele - both bladder and urethra

A central prolapse is a uterine prolapse in which the uterus collapses down into the vaginal space. Central prolapses can occur even after a hysterectomy has removed the uterus. This is known as a ‘vault’ prolapse, in which the superior portion of the vagina collapses downwards.

A posterior prolapse can involve:

  • Rectocele - rectum prolapses into vaginal space 
  • Enterocele - a peritoneal sac (a pouch of the thin lining of the abdominal cavity) containing bowel, typically small bowel, descends into the rectovaginal space (between the rectum and the vagina) and bulges against the upper vagina.

Risk factors for pelvic organ prolapse: increased age, parity (having given birth, the more children the higher the risk), number of vaginal deliveries, oestrogen deficiency (usually seen during the menopause), and chronically increased abdominal pressure (for example caused by obesity, long-term constipation or a persistent cough).

Management strategies depend on how the patient is coping, severity of prolapse and their general health:

  • Non-surgical - supervised pelvic floor muscle training for at least 16 weeks can be the first option for women with symptoms from a prolapse of stage 1 or 2 (on the POP-Q grading scale, which runs from 1 to 4, where 4 is the most severe). A pessary (a device placed in the vagina to support the organs) can be used alone or with the training. Vaginal oestrogen can be added if there are menopausal vaginal symptoms. Losing weight (if the BMI is over 30), minimising heavy lifting and preventing or treating constipation also help.
  • Surgical - offered to women whose symptoms have not improved with non-surgical treatment, or who have declined it. The operation depends on the site of the prolapse and on whether the patient wants to keep the uterus. For uterine prolapse the options include hysterectomy (removal of the uterus) or an operation that keeps the uterus. For vault prolapse the top of the vagina can be fixed back in place, using sutures or mesh. An anterior (front wall) repair is done without mesh, and vaginal mesh is now used only if there is no alternative.

Discuss with the patient what each operation involves, the risk of the prolapse coming back and what recovery to expect, so that the choice reflects the patient’s wishes.


Urinary Incontinence

There is risk of stress urinary incontinence (SUI) if the pelvic organs are inadequately supported. SUI occurs when urine leaks from the bladder during episodes of increased abdominal pressure. Usually increased pressure will not cause leakage, however, if the pelvic floor muscles are not adequately supporting the urethra, the pressure cannot be resisted and leakage occurs.

Risk factors include increased age, pregnancy and vaginal birth, obesity, and oestrogen deficiency (usually due to menopause).

Management strategies include pelvic floor muscle training through pelvic floor exercises. NICE advises a supervised programme lasting at least 3 months, with at least 8 contractions three times a day. If non-surgical treatment is not effective, surgical interventions can be considered. These include a sling placed under the urethra to support it, made either from the patient’s own tissue or from synthetic mesh tape.


Trauma to the Pelvic Floor

Childbirth

Vaginal childbirth can be traumatic to the pelvic floor because the fetal head stretches the structures of the pelvic floor. Up to 9 in 10 first-time mothers who have a vaginal birth have some sort of tear, graze or episiotomy. In more severe cases, tearing of the perineum (the area between the vagina and the anus) can also involve the underlying structures.

Perineal tears in childbirth are graded as follows:

  1. First degree: tear involves the perineal skin only
  2. Second degree: tear extends into the perineal muscles
  3. Third degree: tear extends into the anal sphincter complex (the muscles that close the anus)
  4. Fourth degree: tear extends through the anal sphincter complex and anal epithelium (the lining of the anal canal)

Tears of a higher grade and severity can have lifelong consequences through the damage they cause to the structures of the perineum especially to the perineal body. This factor links to why increased parity is a risk factor for pelvic floor dysfunction.


Episiotomy

An episiotomy is a surgical incision made to the perineum in selected situations such as suspected fetal compromise (signs that the baby is unwell) or instrumental delivery (birth with forceps or a ventouse suction cup). NICE advises that it should not be done routinely, only when there is a clinical need.

It involves the cutting of bulbospongiosus and, in some women, the superficial transverse perineal muscle at an oblique angle (NICE advises 45 to 60 degrees to the vertical axis) to relieve pressure on the perineum, allowing more space to deliver the child. In some births, particularly forceps deliveries, an episiotomy may reduce the risk of a high grade tear (one that reaches the anal sphincter, such as a third-degree tear). NICE advises against doing an episiotomy routinely to prevent damage. A Cochrane review of births where an unassisted vaginal birth was expected found that using episiotomy only when needed may result in about 30% fewer women having severe perineal or vaginal trauma than routine use (low-certainty evidence).


Pelvic Floor Exercises

The pelvic floor can be weakened through childbirth, age and chronically increased intra-abdominal pressure. This can have many consequences, such as urinary incontinence and pelvic organ prolapse. Prolapse can cause a feeling of heaviness, and pain during sex.

To help strengthen the pelvic floor, a number of exercises can be performed. A common regimen is the Kegel exercises. The first step is to identify the pelvic floor muscles. This can be done by briefly stopping urination mid-stream to identify the muscles, but this should not be practised regularly. The muscles that are clenched to stop the stream of urine are the muscles of the pelvic floor. Another method of finding the pelvic floor muscles is less technical and more unconventional. Imagine sitting in a bath of eels and clenching the muscles to stop the eels getting into the vagina. This upward clenching motion uses the pelvic floor.

Once the muscles of the pelvic floor are identified, Kegel exercises can be performed. The muscles should be contracted for 5 seconds, then relaxed for 5 seconds. This should be repeated 10 times, ideally three times per day. The exercises should be continued even when improvement is noticed. This will help to strengthen the pelvic floor to lessen the effects of or prevent the symptoms of pelvic floor weakness.


Edited by: Dr. Ben Appleby and Dr. Thomas Burnell

Reviewed by: Dr. Marcus Judge

Free account

Keep reading for free

Create a free account to continue reading The Pelvic Floor.

Your account includes:

  • Thousands of free practice questions
  • Tools to track your revision progress
Sign up free Already have an account? Log in

No payment. No spam. Just free medical revision.

Quiz

Preview the The Pelvic Floor quiz

Practice this topic

Free single best answer questions written by UK doctors, with an explanation after every answer.
  • The Pelvic Floor: free SBA questionsQuestions on this article→
  • Reproductive System question bankEvery question in this subject→
  • Free medical question bankAll subjects, with full explanations→
SimpleMed+ EncyclopaediaShort and simple explanations of hard topics, with memory aids→
SimpleMed+

Want More?

Access more on SimpleMed+

Lock it in with practice questions, the full question bank and revision tools that track what you know.

Practice now
12385
simplemedlonglogo.png
  • Home
  • Terms & Conditions
  • Privacy Policy
  • Contact

The medical information on this site is provided as an information resource only, and is not to be used or relied on for any diagnostic or treatment purposes. This information is intended for medical education, specifically to biological/medical learning inclined individuals, and does not create any doctor-patient relationship, and should not be used as a substitute for professional diagnosis and treatment.

©2026 Lili's Ark Limited, UK Company #15424953
S+

Search

  • Pre-Clinical
    • Cardiovascular System
      • 1. Anatomy of the Cardiovascular System
      • 2. The Cardiac Cycle
      • 3. Pulses and Pressures
      • 4. Control of Cardiac Output
      • 5. Cardiac Conduction and Contraction
      • 6. Embryology of the CVS
      • 7. Congenital Heart Defects
      • 8. Hypertension
      • 9. Electrocardiograms
      • 10. Electrocardiogram Pathology
      • 11. Cardiovascular Drugs
      • 12. Murmurs
      • 13. Special Circulations
      • 14. Heart Failure
      • 15. Artery and Vein Disease
      • 16. Acute Coronary Syndromes
      • 17. Haemodynamic Shock
    • Musculoskeletal System
      • The Human Body
        • 1. Anatomical Terms
        • 2. Structure of the Muscles
        • 3. Muscles in Action
        • 4. Connective Tissue
        • 5. Cartilage: Structure, Growth and Repair
        • 6. Structure of Bones
        • 7. Basics of Bone Anatomy
        • 8. Joints
        • 9. The Spine
        • 10. Dermatomes and Myotomes
        • 11. The Brachial Plexus
        • 12. The Lumbar Plexus
        • 13. The Sacral Plexus
      • Clinical Conditions
        • 1. Conditions of the Foot
        • 2. Conditions of the Ankle
        • 3. Conditions of the Lower Leg
        • 4. Conditions of the Knee
        • 5. Conditions of the Thigh
        • 6. Conditions of the Hip
        • 7. Conditions of the Lower Back
        • 8. Conditions of the Back and Neck
        • 9. Conditions of the Shoulder and Clavicle
        • 10. Conditions of the Arm
        • 11. Conditions of the Elbow
        • 12. Conditions of the Forearm and Wrist
        • 13. Conditions of the Hand
      • Musculoskeletal Anatomy
        • 1. Muscles of the Gluteal Region
        • 2. Muscles of the Thigh
        • 3. Key Areas of the Lower Limb
        • 4. Bones of the Lower Limb
        • 5. Bones of the Foot
        • 6. Muscles of the Lower Leg
        • 7. Bones of the Upper Limb
        • 8. Muscles of the Shoulder
        • 9. Muscles of the Upper Arm
        • 10. Bones of the Hand
        • 11. Muscles of the Forearm
        • 12. Key Areas of the Upper Limb
    • Cell Physiology & Biology
      • 1. An Introduction to the Cell
      • 2. Introduction to DNA
      • 3. The Cell Cycle, Checkpoints and Apoptosis
      • 4. Structure of Proteins
      • 5. Protein Function in Oxygen Transport
      • 6. Enzymes and Regulation of Protein Function
      • 7. Molecular Techniques for Medics
      • 8. Post-translational Modification and Collagen Biosynthesis
      • 9. Protein Targeting
      • 10. Biological Membranes
      • 11. G-Protein Coupled Receptor
      • 12. Enzyme-linked and Intracellular Receptor Signalling
      • 13. Membrane Transport and Intracellular Calcium Regulation
      • 14. Membrane Potentials
      • 15. Action Potentials
      • 16. Autonomic Nervous System Introduction
    • Metabolism
      • 1. Nutrition, Diet and Body Weight
      • 2. Energy Reactions in Cells
      • 3. Dietary Energy Production
      • 4. Vitamins, Cofactors, Minerals and Trace Elements
      • 5. Glycolysis
      • 6. Oxygen-dependent Pathway
      • 7. Lipid Metabolism and Transport
      • 8. Protein and amino acid metabolism
      • 9. Purine and Pyrimidine Metabolism
      • 10. Inborn Errors of Metabolism and Newborn Screening
      • 11. Alcohol Metabolism
      • 12. Oxidative Stress
      • 13. Energy Storage
      • 14. Temperature Regulation
      • 15. Metabolic and Endocrine Regulation
    • Endocrinology
      • 1. An Introduction to Endocrinology
      • 2. Control of Appetite
      • 3. The Adrenal Glands and Adrenal Disorders
      • 4. HPA and Growth Hormone
      • 5. Pituitary Disorders
      • 6. The Thyroid Gland
      • 7. The Endocrine Pancreas
      • 8. Diabetes Mellitus
      • 9. Calcium Metabolism
    • Haematology
      • 1. Haematopoiesis and the Spleen
      • 2. Full Blood Count
      • 3. Blood Groups, Crossmatching and Transfusion Reactions
      • 4. Anaemia
      • 5. Vitamin B12 and Folate
      • 6. Iron Metabolism
      • 7. Haemoglobinopathies
      • 8. When Haematopoiesis goes wrong
      • 9. Haematology in Systemic Disease
    • Genetics
      • 1. Mitosis and Meiosis
      • 2. Genotype, Phenotype and Inheritance
      • 3. Gene Expression
      • 4. Epigenetics, Genomic Imprinting and Mitochondrial Inheritance
      • 5. Introduction to Gene Mutation
      • 6. DNA Repair and Cancer
      • 7. Genetic Testing and Counselling
    • Infection
      • 1. An Introduction To Infection
      • 2. The Infection Model
      • 3. Bacterial Structure, Classification and Growth
      • 4. Biofilms
      • 5. Innate Immunity
      • 6. Adaptive Immunity
      • 7. Gram Staining and Infection Investigations
      • 8. Staphylococci and Other Gram-positive Bacteria
      • 9. Streptococci
      • 10. Gram-negative Bacteria: Structure, Entry Routes and Endotoxin
      • 11. The Organisms Gram Staining Misses
      • 12. Sepsis
      • 13. Antibiotics
      • 14. Principles of Medical Virology
      • 15. Hepatitis
      • 16. Human Immunodeficiency Virus
      • 17. Fungi and Parasites: The Eukaryotic Pathogens
      • 18. The Immunocompromised Host
      • 19. Travel-related Infections
    • Pathology
      • 1. An Introduction to Pathology
      • 2. How to Read a Histology Slide
      • 3. The Basics of Pathology
      • 4. Epithelium, Skin and Exocrine Glands
      • 5. Acute Inflammation
      • 6. Chronic Inflammation
      • 7. Regeneration and Repair of Tissues
      • 8. The Lymphatic System
      • 9. Haemostasis and Clotting
      • 10. Thrombosis and Embolism
      • 11. Atherosclerosis
      • 12. Cellular Adaptations
      • 13. Introduction to Neoplasia
      • 14. Pathogenesis of Neoplasms
      • 15. Behaviour of Neoplasms
    • Population & Social Science
      • 1. Introduction to Population Science
      • 2. Describing Data and Testing Hypotheses
      • 3. Epidemiological Studies
      • 4. Models of Health
      • 5. Beliefs of the Public
      • 6. Health Economics
      • 7. Evidence-Based Practice
      • 8. Patient Safety and Quality Control
      • 9. Summary and Glossary
    • Patient-Centred Care
      • 1. Lifestyle Medicine
      • 2. Childhood Immunisations
      • 3. Sepsis in Paediatrics
      • 4. Child Safeguarding
      • 5. Ageing
      • 6. Falls
      • 7. Men's Health
      • 8. Palliative Care
    • Reproductive System
      • 1. Anatomy of the Man
      • 2. Anatomy of the Woman
      • 3. The Pelvic Floor
      • 4. Development of the Reproductive System
      • 5. Puberty
      • 6. The Menstrual Cycle and Menstrual Abnormalities
      • 7. Gametogenesis
      • 8. Sex, Infertility and Contraception
      • 9. Physiology of the Mother
      • 10. Diseases of the Mother in Pregnancy
      • 11. Physiology of the Fetus
      • 12. The Placenta
      • 13. Labour and Delivery
      • 14. The Postpartum Period
      • 15. Infections of the Reproductive Tract
      • 16. Pelvic Inflammatory Disease
      • 17. The Menopause
      • 18. Malignancies of the Reproductive Tract
      • 19. Introduction to the Breast
      • 20. Benign Conditions of the Breast
      • 21. Malignant Breast Disease
    • Respiratory System
      • 1. Anatomy of the Respiratory System
      • 2. Development of the Respiratory System
      • 3. Ventilation and Lung Mechanics
      • 4. Properties of Gas Exchange
      • 5. Carbon Dioxide Transport
      • 6. Chemical Control of Breathing and Plasma pH
      • 7. Lung Function Testing
      • 8. Pulmonary Embolism
      • 9. Asthma
      • 10. Chronic Obstructive Pulmonary Disease
      • 11. Pneumonia and other Lower Respiratory Tract Infections
      • 12. Bronchiectasis and Cystic Fibrosis
      • 13. Tuberculosis
      • 14. Pneumothorax and Pleural Effusion
      • 15. Lung Cancer
      • 16. Respiratory Failure
    • Urinary System
      • 1. Anatomy of the Kidneys, Bladder and Urethra
      • 2. Development of the Urinary System
      • 3. The Nephron
      • 4. The Glomerulus – Tubular Reabsorption and Secretion
      • 5. Control of Plasma Volume
      • 6. Control of Plasma Osmolarity
      • 7. Control of Potassium
      • 8. Micturition
      • 9. Diuretics
      • 10. Glomerular Filtration Rate and the Measurement of Kidney Function
      • 11. Hyponatraemia
      • 12. Urinary Incontinence
      • 13. Glomerular Disease
      • 14. Diabetic Nephropathy
      • 15. Acute Kidney Injury
      • 16. Chronic Kidney Disease
      • 17. Urinary Tract Obstruction
      • 18. Urinary Tract Infections
      • 19. Prostate Pathology
      • 20. Male Urological Conditions
      • 21. Urological Malignancy
    • Gastrointestinal System
      • 1. Development of the Gastrointestinal Tract
      • 2. Abdominal Wall and Inguinal Canal
      • 3. Anatomy and Physiology of the Foregut
      • 4. Anatomy and Physiology of the Midgut
      • 5. Anatomy and Physiology of the Hindgut
      • 6. Gastrointestinal Motility and the Enteric Nervous System
      • 7. Liver, Biliary and Exocrine Pancreatic Physiology
      • 8. Gastrointestinal Secretion, Digestion and Absorption
      • 9. Upper Gastrointestinal Pathology
      • 10. Hepatic, Biliary and Pancreatic Pathology
      • 11. Intestinal Pathology
      • 12. Distal Gastrointestinal Tract Pathology
      • 13. Gastrointestinal Malignancy
      • 14. Gastroenteritis and Enterocolitis
      • 15. Gastrointestinal Emergencies
    • Head & Neck
      • 1. Introduction to Head & Neck Anatomy
      • 2. Blood Supply of the Head and Neck
      • 3. Lymph Nodes and Neck Lumps
      • 4. The Skull
      • 5. The Temporomandibular Joint
      • 6. The Meninges
      • 7. Cranial Nerves I-VI
      • 8. Cranial Nerves VII-XII
      • 9. Development of the Head and Neck
      • 10. Autonomics in the Head and Neck
      • 11. Anatomy of the Ear
      • 12. Ear Pathology
      • 13. The Nose
      • 14. The Oral Cavity and Pharynx
      • 15. The Eye
      • 16. The Larynx
      • 17. Head and Neck Cancers
      • 18. Imaging of the Head and Neck
      • 19. Fascial Planes, Muscles and Triangles
    • Immunology
      • 1. An Introduction to Hypersensitivity
      • 2. Type 1 Hypersensitivity
      • 3. Food Allergy
      • 4. Introduction to Autoimmunity
      • 5. Rheumatoid Arthritis
      • 6. Systemic Lupus Erythematosus (SLE)
      • 7. Immunological Therapies | Monoclonal Antibodies
    • Neuroanatomy & Psychiatry
      • 1. Basics of Neuroanatomy
      • 2. Cells and Components of the Nervous System
      • 3. Arterial Supply to the Brain
      • 4. Development of the Nervous System
      • 5. Production and Circulation of CSF and Related Disorders
      • 6. Somatosensory System
      • 7. Motor System
      • 8. The Cerebellum: Circuits, Coordination and Clinical Signs
      • 9. Visual System
      • 10. Auditory and Vestibular Systems
      • 11. The Hypothalamus and Limbic System
      • 12. Higher Cortical Function
      • 13. Reticular Formation
      • 14. Movement Disorders
      • 15. Infections of the Central Nervous System
      • 16. Dementia
      • 17. Delirium
      • 18. Headaches
      • 19. Stroke
      • 20. Raised Intracranial Pressure (ICP)
      • 21. Subarachnoid Haemorrhage
      • 22. Anxiety
      • 23. Mood Disorders
      • 24. Psychosis
    • Embryology
      • 1. The Basics of Embryology
      • 2. Development of the Limbs and Body Wall
      • 3. Teratology and Congenital Malformations
      • 4. Development of the Gastrointestinal Tract
      • 5. Development of the Reproductive Systems
      • 6. Development of the Urinary System
      • 7. Development of the Respiratory System
      • 8. Development of the Head and Neck
      • 9. Development of the Nervous System
      • 10. Embryology of the Cardiovascular System
    • Pharmacology
      • 1. Research Methods in Pharmacology
      • 2. Pharmacokinetics
      • 3. Pharmacodynamics
      • 4. Pharmacovigilance and Pharmacogenetics
      • 5. Safe Prescribing
      • 6. Cholinergic Pharmacology
      • 7. Adrenergic Pharmacology
      • 8. Hypertension and Heart Failure
      • 9. Cardiac Arrhythmias
      • 10. Antiplatelets, Anticoagulants and Thrombolysis
      • 11. Hyperlipidaemias
      • 12. Diuretics and Renal Pharmacology
      • 13. Pharmacology of Insulin
      • 14. Reproductive and Post-reproductive Health
      • 15. Antibiotics
      • 16. Antivirals
      • 17. Cancer Chemotherapy
      • 18. Anaesthetics
      • 19. Opioids
      • 20. Introduction to Psychopharmacology
      • 21. Epilepsy and Anti-epileptic Drugs
      • 22. Parkinson's Disease and Myasthenia Gravis
      • 23. NSAIDs
      • 24. Immunosuppression and Disease-modifying Therapy
      • 25. Pharmacology of Airway Control
      • 26. Drugs Affecting Acid Secretion
      • 27. Antiemetics and Laxatives
      • 28. Poisoning and STOPP/START
  • OSCE
    • Index Conditions for OSCE exams
    • Cardiovascular System Examination
    • Shoulder Examination
    • Hand Examination
    • Venepuncture
    • Blood Pressure
    • Respiratory System OSCE Examination
    • Peripheral Vascular OSCE Examination
    • Varicose Vein OSCE Examination
    • Deep Vein Thrombosis (DVT) OSCE Examination
    • Abdominal OSCE Examination
    • Rectal (PR) OSCE Examination
    • Stoma OSCE Examination
    • Hernia OSCE Examination
    • Upper Limb Neurological OSCE Examination
    • Lower Limb Neurological OSCE Examination
    • Cranial Nerve OSCE Examination
    • Cerebellar OSCE Examination
    • GALS Screening OSCE Examination
    • Elbow OSCE Examination
    • Hip OSCE Examination
    • Knee OSCE Examination
    • Ankle and Foot OSCE Examination
    • Spine OSCE Examination
    • Thyroid Status OSCE Examination
    • Diabetic Foot OSCE Examination
    • Cushing's Syndrome OSCE Examination
    • Acromegaly OSCE Examination
    • Ear, Otoscopy and Hearing OSCE Examination
    • Nasal OSCE Examination
    • Eye and Vision OSCE Examination
    • Fundoscopy (Ophthalmoscopy) OSCE Examination
    • Visual Acuity OSCE Assessment
    • Anterior Segment Eye OSCE Examination
    • Pigmented Skin Lesion OSCE Examination
    • Rash and Non-Pigmented Skin Lesion OSCE Examination
    • Breast OSCE Examination
    • Testicular OSCE Examination
    • Neck Lump OSCE Examination
    • Lymphoreticular OSCE Examination
  • Question Bank
  • About
  • How to Use SimpleMed
  • SimpleMed Lecture Series
  • DON'T PANIC - Guide to the Wards
  • SimpleMed Plus
Your privacy We use optional cookies for analytics and advertising, to improve SimpleMed and measure our ads. Privacy policy
