

By Dr. Ethan Kavanagh and Dr. Marcus Judge
All done here! Check out our other subjects!
Core
What are Travel-related Infections?
Travel related infections occur when patients have travelled to another location which has a different set of common diseases. This is usually a location with a considerable climate difference or within the tropics. Some of the diseases acquired are referred to as NTDs (Neglected Tropical Diseases), because of their high impact in low income and poor communities, although many of them can be prevented or treated.
Many of these diseases are spread by a vector (a living carrier, such as an insect, that passes an infection on). The vector has to live in the area where the infection is caught. For example, the female Anopheles mosquito is the vector for the Plasmodium species that cause malaria, and it is common in sub Saharan Africa. Some Anopheles species also live in the UK, but malaria is not currently spread here.
Many travel-related infections should be identified and treated promptly, as they can be life-threatening. Some are transmissible between people, while others are acquired via vectors or environmental exposure, so transmission risk depends on the specific infection.
If a tropical disease is suspected, a comprehensive travel history should be taken. As it may not be readily apparent to the patient that their illness is related to their travel (some cases of malaria may have an incubation period, the time from infection to the first symptoms, of close to a year), patients are unlikely to tell you about their travels because the trip does not seem relevant to them. This can also mean easily treatable tropical infections can have time to develop complications as they are not considered in a differential diagnosis. This delay in diagnosis is of further concern if the particular disease is contagious. Therefore a good travel history helps to prevent complications and the spread of the disease through the hospital or community. It also allows proper containment and treatment to be set up.
It is important to be precise when establishing a travel history as some countries may have different strains of the same microorganism whose prevalence may vary by time of year. These different strains may also have differences in antibiotic or drug resistance, therefore this information is key in guiding treatment.
There are a number of travel-related infections, but only a few of the most important ones to be aware of will be covered here. Where the patients treated have travelled to recently will determine which infections are more likely than others (i.e. the most prevalent for a particular area).
Malaria is one of the most common and deadly infections in the world, spread rapidly by mosquitoes.
Malaria involves infection of the patient's red blood cells (erythrocytes) with protozoal Plasmodium microorganisms. These multiply within and destroy the erythrocytes, causing severe sickness, anaemia, fever of a cyclical nature and potentially death. Malaria can be identified on a patient's blood film, where parasites may be seen within infected red blood cells. Microscopy remains important, often alongside rapid diagnostic tests, to confirm the diagnosis.
Presentation
Recognising malaria is vital in a patient that has a travel history in areas that have a high prevalence of malaria, such as South and Central America, Oceania, Africa, the Caribbean, Middle East and Southeast Asia. A presenting patient with suspected malaria often has a fever, sweats or chills, headache and muscle aches, although the absence of fever does not rule malaria out. They might also have:
- Tachycardia (fast heart rate)
- Hypotension in severe cases
- Reduced oxygen saturation in severe disease
- Mild confusion
- History of mosquito bites
- Hepatosplenomegaly (enlarged liver and spleen)
- Vomiting and nausea
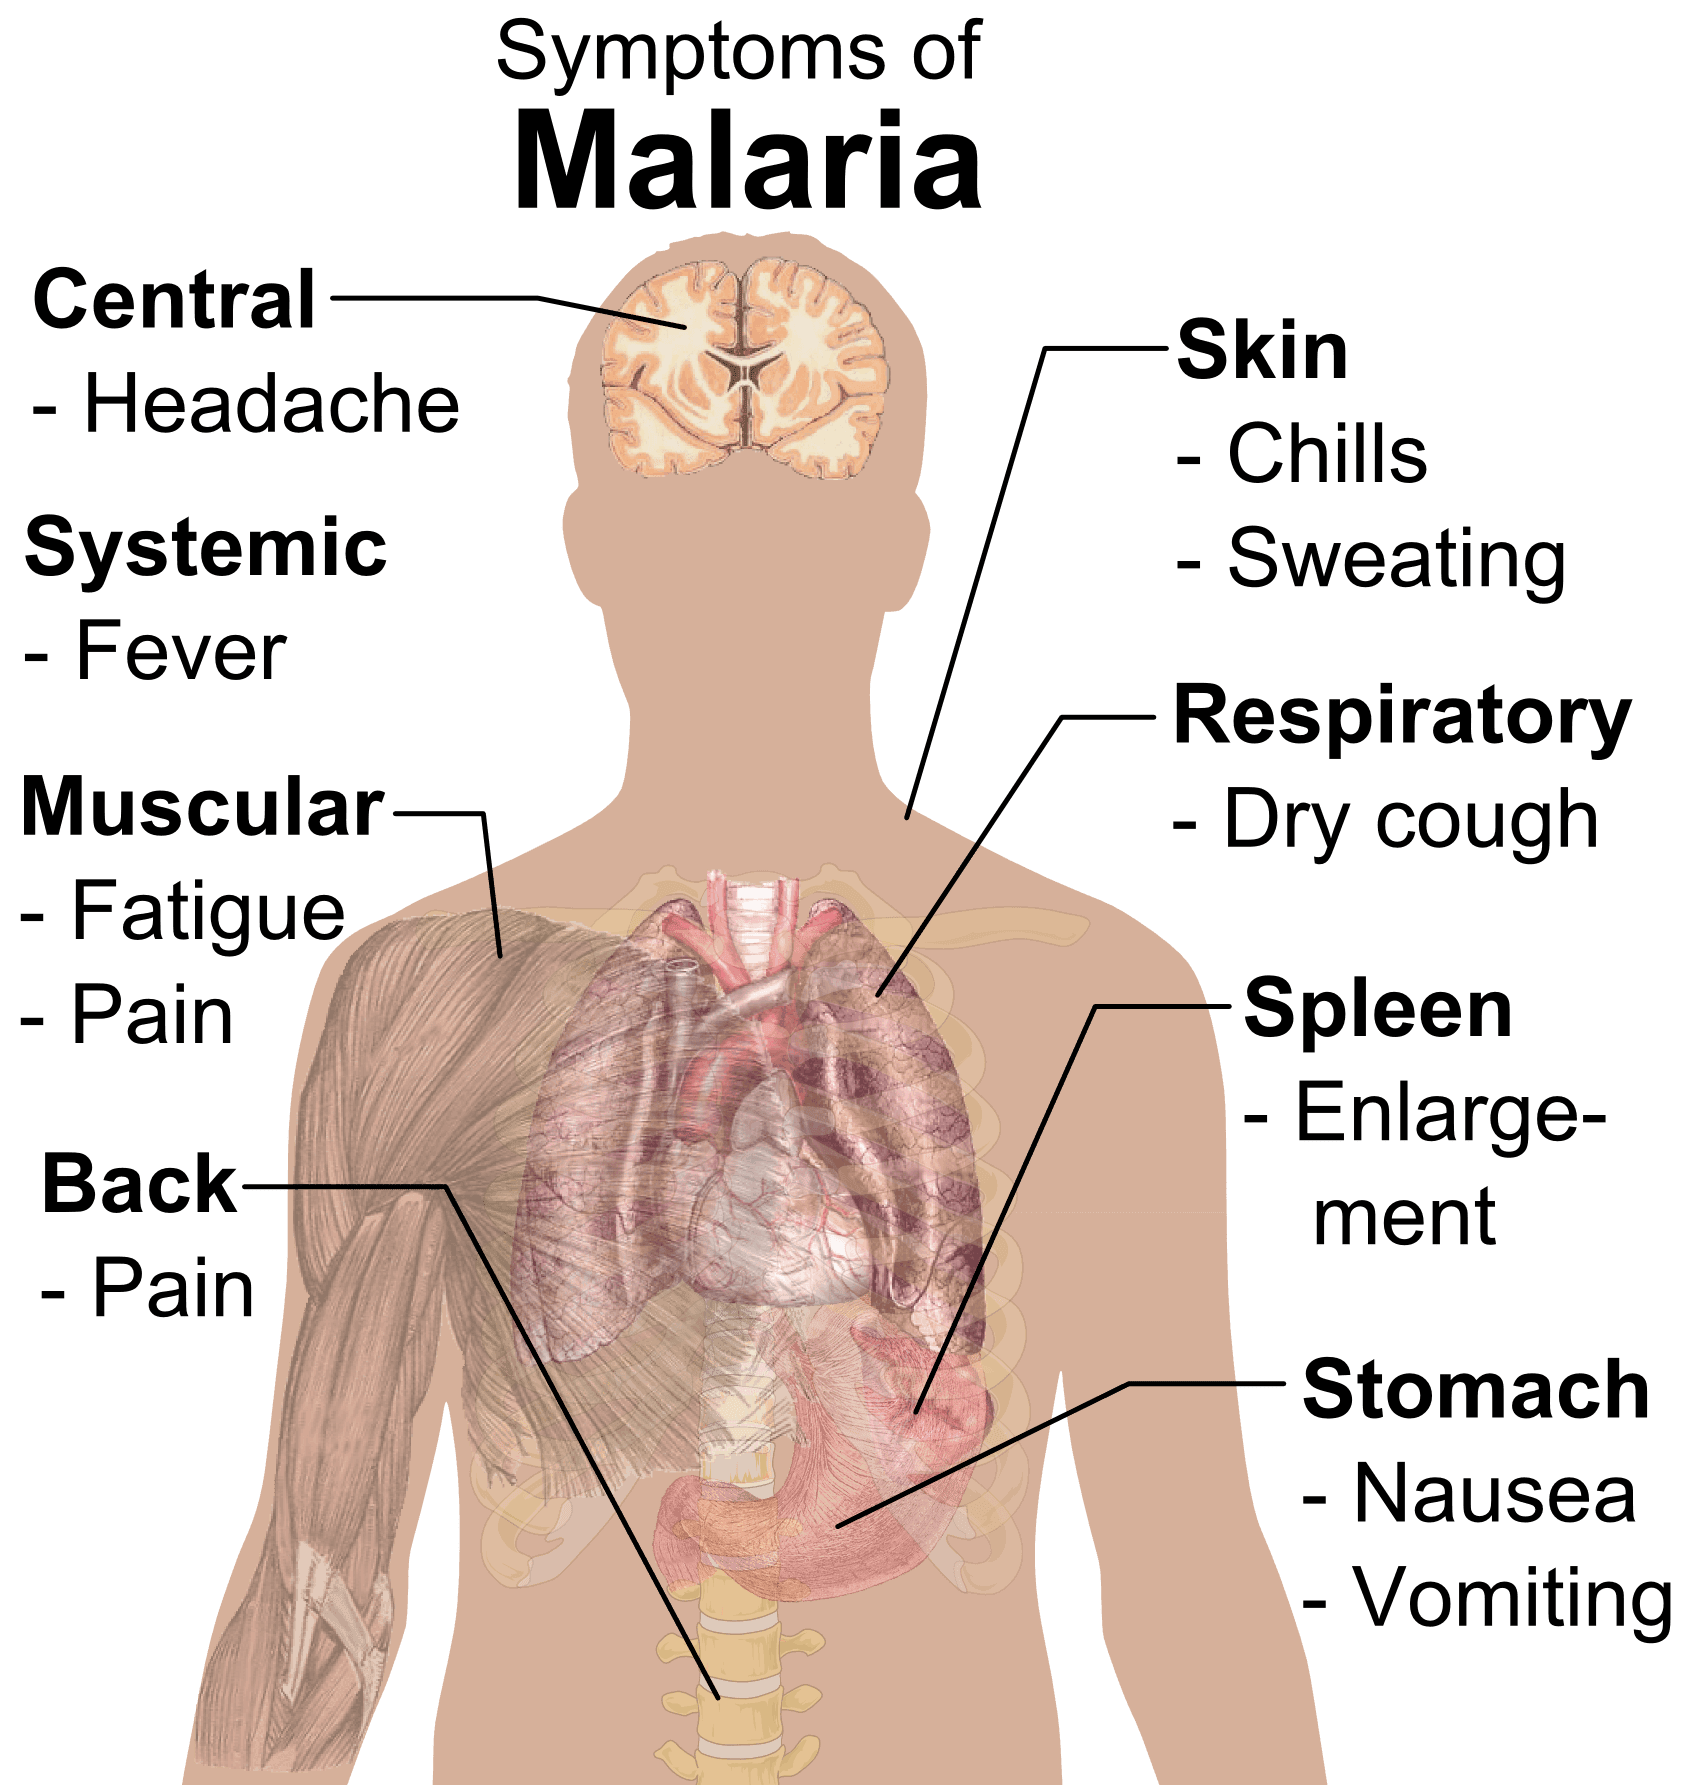
Diagram: The systemic symptoms of Malaria - any of these symptoms, especially fever, after travel to a malaria area should make you suspect malaria.
Creative commons source by [Häggström, Mikael (2014). "Medical gallery of Mikael Häggström 2014". WikiJournal of Medicine 1 (2). DOI:10.15347/wjm/2014.008. ISSN 2002-4436. Public Domain.orBy Mikael Häggström, used with permission. [Public domain]]
These symptoms are also seen in bacterial sepsis, so the two are easily confused. A good history is key to understanding a patient's presentation.
Pathophysiology
Malaria is caused by different species of the protozoal genus Plasmodium. There are many different species, but only five actually cause malaria in humans:
- Falciparum (causes the majority of malaria cases worldwide and is the deadliest human parasite, found throughout the tropics and subtropics and most prevalent in Africa)
- Ovale
- Vivax
- Malariae
- Knowlesi
Regardless of species, malaria is carried by the female Anopheles mosquito (the mosquito is the vector). Once a person is infected, there is an incubation period (the time from infection to the first symptoms), during which the parasite multiplies, first in the liver and then in the blood. In the case of malaria, this could be anywhere from six days to over a year!
Each species has a slightly different life-cycle when infecting humans, but we will focus on P. falciparum's life-cycle, the most common species of malaria.
Once a mosquito bites someone with its proboscis (biting mouthpart), the plasmodium moves from the mosquito’s salivary gland and into the blood stream of the person the mosquito has attacked. When it is in the bloodstream, the plasmodium is in the sporozoite stage of its life cycle (the form injected by the mosquito). Once these sporozoites get into the bloodstream, they go straight for the liver and get inside the liver parenchyma (functional tissue).
The P. falciparum then begin to multiply asexually (still in the liver, but rapidly) and mature from sporozoites to merozoites (the form that infects red blood cells). Once they’re ready, they burst out from the liver and go straight into the bloodstream where they attack and enter erythrocytes. P. falciparum can invade erythrocytes of all ages.
Now that they’ve gotten into the erythrocyte, the plasmodium begins to replicate (asexually) and mature (over about 2-3 days). When they’re ready to burst out of the erythrocyte, the erythrocyte is called a schizont. What actually bursts out is a mass of merozoites, ready to continue the cycle by infecting and destroying even more erythrocytes.

Image: Colourised scanning electron micrograph of red blood cell infected with malaria parasites, which are colourised in blue. The infected cell is in the centre of the image area. To the left are uninfected cells with a smooth red surface.
Creative commons source by NIAID [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Some plasmodia don’t follow the same path as the others once inside the erythrocytes and become gametocytes (the sexual form, which can infect mosquitoes) instead. These gametocytes stay inside the erythrocyte (the erythrocyte doesn’t rupture) and are instead sucked up by a different mosquito that is feeding on the same human. The infected erythrocyte then makes its way to the mosquito’s gut, forms a zygote, matures inside the mosquito by sexual reproduction and releases a mass of sporozoites. These sporozoites then travel to the mosquito’s salivary gland, ready for the mosquito to feed on someone else.
The key takeaway message is that malaria invades and either destroys red blood cells, causing many of the symptoms seen, or remains within cells to be taken back up by other mosquitoes.
Incubation time is the time from when a person becomes infected until they start to see the onset of symptoms. For malaria, this varies by species. Almost all P. falciparum infections cause symptoms within 6 months of exposure, and most within 2 to 3 months. Other species, such as P. ovale and P. vivax, may cause symptoms months or years after exposure. Antimalarial drugs can also delay malaria symptoms until long after the patient has left the area for species which produce dormant liver parasites (especially P. vivax and P. ovale).
One of the main symptoms the patient will experience with a systemic infection is a fever. Caused by cytokine release (cytokines are signalling chemicals made by immune cells), the fevers come in bursts (cycles) depending on when there is erythrocyte bursting (schizont rupture). Of course, this is different with the different species of plasmodium. P. knowlesi fevers occur in 24-hour waves, whereas P. vivax and P. ovale fevers occur in 48-hour waves and P. malariae fevers occur in 72-hour waves. P. falciparum is the odd one out with a more random fever cycle pattern. These fevers are called paroxysm fevers - fevers that occur in short bursts.
With the destruction of erythrocytes, an individual will present with the symptoms of haemolytic anaemia. These include:
- Pale in colour (pallor)
- Jaundice (release of haemoglobin from erythrocytes and thus build-up of bilirubin, its breakdown product)
- Dark coloured urine (also caused by presence of haemoglobin in urine)
- Weakness
- Dizziness and confusion
These features can occur in all Plasmodium infections, including P. falciparum, and are often more severe in falciparum malaria. Along with these symptoms of an uncomplicated malarial infection, P. falciparum creates a sticky protein that coats the surface of erythrocytes and causes them to clump together (like a clot) and block (occlude) blood vessels, leading to organ ischaemia (organs not getting enough blood). A variety of different organs are affected, and this would be a complicated malarial infection.
When malaria is suspected, diagnosis is confirmed by thick and thin blood films (x3) to test for the presence of parasites and then specifically which parasite is causing the infection (3 films are ordered as it is easy to produce false negative films depending on the sample and its timing). A full blood count is also ordered which should show a normocytic and normochromic anaemia. If it also shows a low platelet count (thrombocytopenia) and an increase in lactate dehydrogenase (from haemolysis) then the physician is likely to diagnose malaria.
Treatment
A severe (also called complicated) case of malaria needs immediate treatment with intravenous artesunate, ideally in a high dependency or intensive care setting. Artesunate is given via IV (intravenous) injection. After at least 24 hours, once the patient has improved and can take tablets, they complete a full course of an artemisinin combination therapy (ACT), such as artemether with lumefantrine. IV quinine is given if artesunate is not immediately available.
Uncomplicated malaria is treated with tablets. For P. falciparum, the first choice is an ACT, usually artemether with lumefantrine. Quinine (an antimalarial drug) with doxycycline (an antibiotic), or atovaquone with proguanil (another antimalarial combination), can be used if an ACT is not available. For P. vivax, P. ovale, P. malariae and P. knowlesi, either an ACT or chloroquine can be used. Chloroquine is not used for P. falciparum because of widespread resistance. For P. vivax and P. ovale, primaquine is also given to destroy the dormant liver parasites (hypnozoites) and so prevent relapse. Patients are screened for G6PD deficiency (an inherited red blood cell enzyme deficiency) first, because primaquine can cause haemolysis (breakdown of red blood cells) in people who have it.
If malaria is suspected or confirmed but the species is not known, or the infection is mixed and includes P. falciparum, start treatment as for falciparum malaria. Chloroquine is not used in this situation, because most P. falciparum is now resistant to it. Expert advice must be sought for every patient with suspected malaria.
Please see https://bnf.nice.org.uk/treatment-summary/malaria-treatment.html for up to date guidelines.
Malaria can come back after treatment. This recurrent malaria is split into three categories:
- Recrudescence (the treatment didn’t kill off the parasite)
- Relapse (patient is cleared of merozoites, but those dormant hypnozoites in the liver have decided to no longer be dormant)
- Reinfection (the patient was properly cured of malaria, but now has a completely new case of the same disease)
As with any disease, prevention is better than cure. When it comes to malaria, the main step is to avoid mosquito bites. This can be done by wearing clothing that covers your whole body, sleeping under mosquito nets at night, using insecticide sprays indoors and putting insect repellent on exposed skin. The Anopheles mosquito breeds in stagnant water, so community level control focuses on reducing breeding sites; for individuals, prevention relies on avoiding bites and using appropriate chemoprophylaxis (antimalarial tablets taken to prevent infection, where they are advised for the destination).

Figure: Key things tourists should avoid and be advised to not do if travelling to an area with a high malaria risk
Public Domain Image National Library of Medicine - History of Medicine [No restrictions]
Legionellosis (Legionnaires’ Disease)
Legionellosis is a group of conditions caused by Legionella bacteria (Gram negative, meaning they have a thin cell wall and an outer membrane). The most serious condition Legionella can cause is known as Legionnaires’ disease.
Although Legionella bacteria are found right across rivers and lakes, the most likely place of infection is from somewhere where the water is at a high enough temperature to help the bacteria grow (somewhere like a poorly maintained shower system or air conditioning unit). This makes it more likely to be caught in a poorly cleaned hotel, hospital or office. It is less common to catch it at home, but it can happen, for example from taps and showers that are not used often.
The bacteria are contracted by inhaling droplets of water that contain the bacteria. Once inside the body, L. pneumophila invades macrophages in the lungs and replicates inside them.
Legionnaires' disease usually develops two to 10 days after exposure to legionella bacteria. It frequently begins with the following signs and symptoms:
- Headache
- Muscle/ chest pain
- Chills
- Fever that may be 40°C or higher
And it can progress to include:
- Cough, which may bring up mucus and sometimes blood
- Shortness of breath
- Gastrointestinal symptoms, such as nausea, vomiting and diarrhoea
- Confusion or other mental changes
Legionnaires’ disease is an uncommon cause of pneumonia, but it can be severe, and delayed or inadequate treatment is linked to a worse outcome. It is treated with antibiotics if it is identified: either a fluoroquinolone (a class of antibiotics, such as levofloxacin) or a macrolide (another class, such as clarithromycin or azithromycin). Antibiotic treatment usually lasts one to three weeks and most people make a full recovery (but it might take a few weeks more to get back to normal).
Schistosomiasis is a parasitic disease caused by Schistosoma species, a group of flatworms common in tropical areas. Humans acquire the flatworms through unprotected skin contact in areas of fresh water contaminated with the helminths (parasitic worms) which have been released from snails (hence its other name of ‘snail fever’).
Patients may have a fever-like illness, alongside:
- Diarrhoea
- Coughs
- Rashes
- Abdominal pain
- Muscle and joint pain
These symptoms are referred to as acute schistosomiasis.
Schistosomiasis can also involve chronic inflammation, causing damage due to the host’s immune response. Often there are no symptoms at all, or symptoms only start weeks, months or years after infection. Conditions caused include anaemia, cystitis (bladder irritation), cardiovascular and respiratory problems or, rarely, neurological symptoms such as seizures and dizziness.
Diagnosis is made by finding eggs in a urine or stool sample, or by a blood test for antibodies. In travellers, microscopy often misses eggs, especially in acute infection, and antibodies may take some weeks to appear, so tests can be negative early on.
People with acute schistosomiasis symptoms may be given a course of steroids to reduce inflammation. The curative treatment, praziquantel, is normally most effective once the worms have matured, so a patient might find that they aren’t given treatment until a number of weeks post-infection.
Typhoid fever is one of the two types of enteric fever (the other is paratyphoid fever, which is typically milder). It is caused by Salmonella enterica serovar Typhi (a serovar is a subtype of a bacterial species). These are rod-shaped Gram negative bacteria. The usual presentation is a prolonged high fever, abdominal pain, and constipation or diarrhoea. Fatigue, headache and nausea are also common. If left untreated, it may also cause delirium (acute confusion), gastrointestinal (GI) haemorrhage (bleeding from the gut) and bowel perforation. It can even be fatal, a month after infection.
Typhoid fever is most common where there is poor sanitation and limited access to clean water. Children are at highest risk of typhoid fever. In hospitalised patients, a review of many studies found no significant difference between children and adults in how often complications occurred.
If the infection is diagnosed early and is uncomplicated, some people can be treated as outpatients with a course of oral antibiotics, such as azithromycin, often for about seven days. Careful monitoring is needed, because treatment can fail. More serious infections need injections of antibiotics in hospital, often ceftriaxone. The choice of antibiotic depends on where the infection was caught, because some strains are resistant (for example, a strain resistant to third-generation cephalosporins, a class of antibiotics that includes ceftriaxone, was first reported in 2017 in a traveller returning to the UK from Pakistan). Most patients will start to feel better after a few days.
There are two vaccinations against typhoid fever: a single injection, or a course of three capsules taken by mouth. Neither offers 100% protection, so it is important to take other precautions when travelling to certain areas (e.g. only consuming food and water you know is “clean”). Any cases in the UK are normally from patients that recently travelled in Bangladesh, India or Pakistan. These are not the only places: Asia, Africa and South America are also on the list of places where a patient is likely to catch typhoid fever.
Dengue fever or "breakbone fever", is caused by the dengue virus. The virus has four serotypes (versions of the virus that the immune system sees as different, called DENV-1 to DENV-4), which are usually transmitted by mosquitoes (Aedes aegypti and Aedes albopictus).
The good news for people with dengue is that most infections cause only a mild illness or no symptoms at all (they are asymptomatic).
Around four to ten days after the bite, someone may suddenly present with:
- An intense headache
- Fever
- Muscle/joint pain (hence the name breakbone fever)
- A widespread red rash
Dengue normally resolves itself within a few days (which is good because there is no specific treatment for it other than to treat the symptoms as they present). Supportive treatments include taking paracetamol to relieve pain and fever and drinking plenty of fluids to avoid dehydration. Non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen or aspirin should be avoided because of bleeding risk.
The bad news is that, rarely, dengue progresses to severe dengue (especially in patients who have been previously infected by dengue), which can be fatal. WHO has used the term severe dengue since 2009. Older texts use the terms dengue haemorrhagic fever and dengue shock syndrome (when the blood pressure falls dangerously low). As with uncomplicated cases of dengue, the severe form has no cure so may require intensive care with IV fluids (to replace the fluid that leaks out of the blood vessels), oxygen therapy if required and sometimes blood transfusion if there is serious bleeding. Platelet transfusions are not recommended just because the platelet count is low.
A patient can rapidly progress from standard dengue fever to severe dengue, often after the fever has gone away. This can result in symptoms such as:
- Restlessness
- Persistent vomiting
- Severe abdominal pain
- Bleeding or bruising under the skin (petechiae)
- Nosebleeds
- Large decreases in blood pressure (shock)
Along with bleeding from various places, this stage of dengue fever is characterised by plasma leakage (fluid escaping from the blood vessels, which can lead to shock). Low levels of platelets in the blood are also common, but they occur in milder dengue too.
Attempts to increase platelet levels have led to claims that papaya can ‘cure’ dengue fever; however, there is no good quality evidence that papaya leaf extract is effective or safe for this purpose, and it is not recommended in clinical guidelines. Management remains supportive, with careful monitoring and treatment of complications. Paracetamol is the preferred painkiller. Aspirin and other NSAIDs increase the risk of bleeding because they impair platelet function, which is particularly dangerous in dengue.
Edited by: Dr. Ben Appleby
- 9444

