

Next Lesson - Human Immunodeficiency Virus (HIV)
Core
Hepatitis simply means inflammation of the liver. It has many causes besides viral infection. Common causes include:
- Viral hepatitis - the focus of this article.
- Alcoholic hepatitis (also called alcohol-related hepatitis) - inflammation of the liver caused by drinking too much alcohol over a long period of time.
- Autoimmune hepatitis - where the body attacks its own liver. This is treated with immunosuppression (medicines that dampen the immune system). The cause of autoimmune hepatitis is unknown.
Viral hepatitis can result from infection with hepatotropic viruses (viruses that mainly infect liver cells) or from other viral infections that involve the liver. The mechanism of liver injury varies with the virus and the host response.
- Systemic infections, such as Epstein–Barr virus (EBV), can cause hepatitis. In typical EBV hepatitis, infiltrating lymphocytes and the immune response contribute to liver injury; direct infection of hepatocytes is not the usual explanation. Do not assume that every systemic virus causes liver injury in this way.
- Classical viral hepatitis is caused by hepatotropic hepatitis viruses. Infection of liver cells does not mean that injury is caused solely by viral replication: hepatitis B, for example, produces predominantly immune-mediated liver damage.
The five main hepatitis viruses are designated A to E. Types A and E usually cause acute infection, while B and C can cause chronic infection. Hepatitis D occurs only with hepatitis B. These viruses differ in their biology and in the immune responses responsible for liver injury.
Hepatitis B and hepatitis C are the main causes of long-term (chronic) viral hepatitis worldwide. WHO estimates that 240 million people were living with chronic hepatitis B in 2024. Together, hepatitis B and C are the most common cause of liver cirrhosis worldwide, although cirrhosis from fatty liver disease and alcohol is rising in several regions.
Looking at England, the UK Health Security Agency (UKHSA) estimates that about 269,000 people were living with chronic hepatitis B in 2021 (0.58% of people). Across the UK, about 0.4% of pregnant women have hepatitis B. In certain inner-city areas the figure is 1% or more (1 in 100 or more). An earlier estimate of 180,000 people in the UK came from the British Liver Trust hepatitis B page, which can no longer be opened at this address.
The WHO hepatitis C fact sheet updated on 28 July 2026 estimates that 47 million people worldwide live with chronic hepatitis C. WHO estimates that hepatitis C caused approximately 239,000 deaths in 2024, mainly from cirrhosis and hepatocellular carcinoma (primary liver cancer).
Hepatitis B virus (HBV) is a partially double-stranded DNA virus with an outer lipid coat (an envelope). Transmission of HBV is via blood, sexual intercourse and vertical transmission (passed from mother to baby). Once an individual has been infected with HBV, it can take 6 weeks to 6 months for the virus to incubate (develop before any symptoms appear) and begin to cause damage to the individual’s liver.
Most people newly infected with HBV have no symptoms (they are asymptomatic) or only vague, flu-like symptoms. Jaundice (yellowing of the skin and eyes) develops in about 30% to 50% of adults with acute infection. Other symptoms include fever, nausea, vomiting and arthralgia (joint pain).
Most immunocompetent adults (people with a normally working immune system) will clear the infection themselves within around 6 months. About 5% or fewer will progress from an acute to a chronic infection. In parts of Asia and Africa, where HBV is common, many babies are infected at birth by their mothers, and about 90% of these babies will progress to a chronic infection.
The most important test for hepatitis B is serology. This is the analysis of blood serum (blood without cells or clotting factors) to see what immune response has occurred and look for the presence of extra substances. The serology of hepatitis B involves three antigens and three antibodies.
The first antigen detectable is HBsAg which is the hepatitis B (HB) surface (s) antigen (Ag). The matching antibody produced is HBsAb (also written anti-HBs), hepatitis B (HB) surface (s) antibody (Ab). HBsAb appears later than HBsAg, as the infection clears during recovery, or after vaccination. It can be detected in the blood and indicates immunity due to past infection or vaccination.
HBeAg is hepatitis B e antigen, a secreted protein derived from the viral core; the “e” does not stand for envelope. Its presence generally suggests active viral replication and greater infectivity. HBV DNA measures viral replication more directly. Some HBV variants replicate without producing HBeAg, so a negative HBeAg result does not exclude infectivity. The corresponding antibody is HBeAb (also written anti-HBe).
The third antigen is HBcAg and its matching antibody, HBcAb (although only the Ab is detected). Here the “c” stands for core. HBcAb first appears as IgM (immunoglobulin M, the early-response antibody), which marks a recent or acute infection. IgM is gradually replaced by IgG (immunoglobulin G, the longer-lasting antibody), which usually persists for life and shows past infection.
Although the antigens appear in the order above, the antibodies actually appear in the reverse order. So, for a patient that hasn’t had a hepatitis B infection before, their timeline would look like:
- Contract the virus through unprotected sex on a holiday in sub-Saharan Africa
- After 6 weeks the HBsAg is detectable in blood serum and there is a corresponding rise in ALT (alanine aminotransferase, a liver enzyme) on liver function tests. They would now be considered infected
- Symptoms start to appear at this point
- HBeAg may appear and generally indicates greater viral replication and infectivity; transmission is not restricted to the HBeAg-positive stage.
- HBcAg is present within infected hepatocytes and is not detectable in serum by routine serology
- HBcAb appears in the form of IgM (as it is an acute infection)
- HBeAb appears and after HBeAg has been cleared infectivity usually falls, although viral replication can still persist in some cases
- HBsAb appears as HBsAg clears and the infection resolves. The virus can persist in liver cells, so infection can reactivate (flare up again) if the immune system is later suppressed
- IgM then converts to IgG and persists in the body
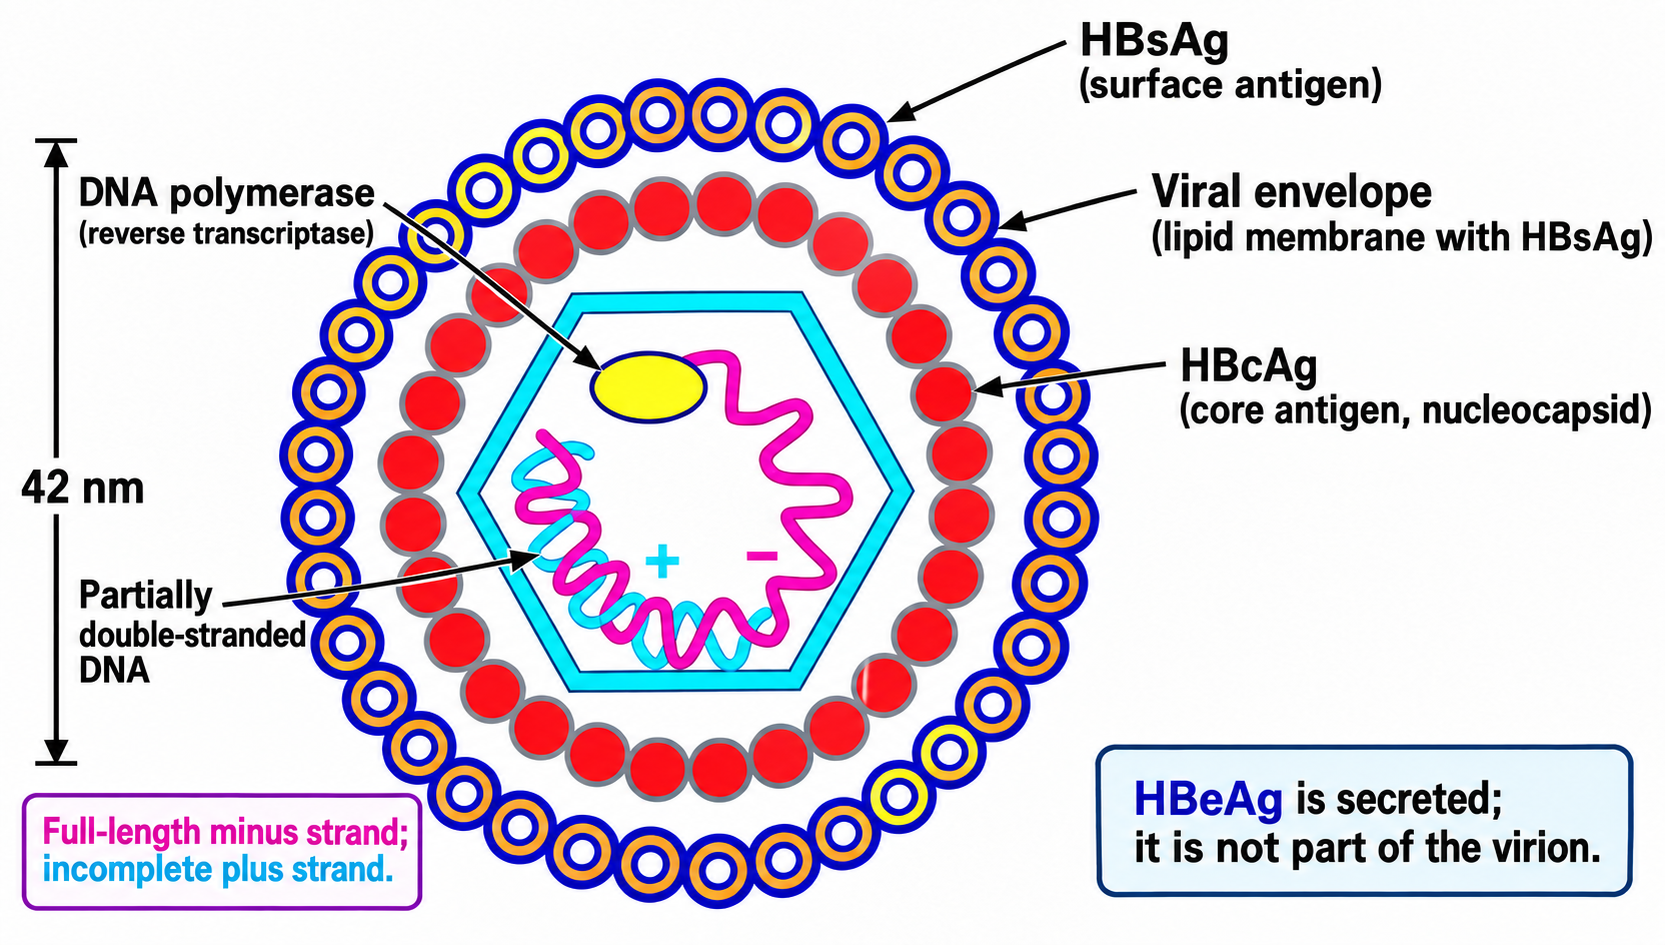
Diagram - Hepatitis B virion (the whole virus particle). HBsAg is in the envelope (outer coat) and HBcAg forms the core. The full-length minus DNA strand (the complete strand) is pink and carries the polymerase (the enzyme that copies the DNA); the incomplete plus strand (the partly built strand) is cyan. HBeAg is secreted and is not part of the virion.
Adapted for SimpleMed (2026) from Hepatitis B virus v2.png, created by Graham Colm and originally uploaded by TimVickers; the source bitmap is released into the public domain. Changes: HBeAg removed from the particle, genome polarity corrected, and labels revised.
Another test that can be done is an HBV DNA PCR (polymerase chain reaction) test, which detects tiny amounts of genetic material, to see how much viral DNA is in the body.
If HBV infection doesn't resolve, then a patient can develop a chronic HBV infection. Chronic HBV is a lifelong infection that is defined by HBsAg staying in the body for longer than 6 months. Of the chronically infected patients, about 20 to 25% will develop progressive liver disease, which can lead to cirrhosis, and to an increased risk of hepatocellular carcinoma.
Chronic HBV cannot currently be cured, but antivirals are used to suppress viral replication in selected patients and treatment is not always lifelong. Most acute HBV infections are managed supportively, with antivirals reserved for severe disease or fulminant hepatitis (sudden, severe liver failure).
There is a vaccine for HBV. It involves injecting the patient with a genetically engineered surface antigen for HBV (HBsAg) that is harmless and allows the body to develop HBsAb so it can fight off an HBV infection. The amount of HBsAb (anti-HBs) in the blood is measured in mIU/mL (milli-international units per millilitre). A level of at least 10 mIU/mL is generally accepted as protective, and a level above 100 mIU/mL is preferable. The usual course is three or four doses, depending on age and risk, and most people respond well to it. People with a normally working immune system do not usually need booster doses (extra doses given later) after a full course. The WHO recommends that all babies are vaccinated preferably within 24 hours of birth. In the UK, the NHS offers all babies the 6-in-1 vaccine (which also protects against five other infections) at 8, 12 and 16 weeks old. Babies born on or after 1 July 2024 are offered a fourth dose at 18 months. Babies of mothers with hepatitis B have extra doses, starting within 24 hours of birth.
Hepatitis C virus (HCV) is a single-stranded RNA virus that is enveloped (has an outer lipid coat) and icosahedral (20-sided) in shape. Transmission of HCV is primarily blood-borne, with sexual transmission occurring less commonly. In the UK, most HCV infection is spread by sharing needles and other equipment used to inject drugs. Healthcare workers can also be infected through needlestick injuries. Others at risk include infants born to HCV positive mothers and those who had blood transfusions before 1991. Incubation is usually shorter with HCV than with HBV. It is about 7 weeks on average, but reviews report a range of 2 to 20 weeks.
Around 80% of acute HCV infections are asymptomatic. When symptoms present, they include fatigue, decreased appetite, nausea, vomiting, abdominal pain, dark coloured urine, grey faeces, arthralgia and jaundice. The WHO estimates that about 30% (15-45%) of infected people clear the virus within about 6 months without treatment. The other 70% (55-85%) will develop a chronic infection.
Testing and detecting HCV is different to HBV. The usual first test is for the anti-hepatitis C antibody. It shows that a person has been infected with HCV at some point, but it cannot tell whether the infection is current or past. Antibodies can take 5 to 12 weeks to appear, so a very early test can be negative. This antibody is not protective and is only really of diagnostic value.
As the anti-hepatitis C antibody remains after clearance, the next step is to do a viral PCR to look for HCV RNA to confirm if the patient has a chronic infection. For those that can clear HCV, they will still be positive for anti-hepatitis C antibody. Once a patient is confirmed to have a chronic infection, the degree of liver scarring (fibrosis or cirrhosis) and the HCV genotype (strain) need to be found out to guide the patient’s treatment. Some newer drugs, such as glecaprevir with pibrentasvir, work against all genotypes.
HCV does not have a vaccine, so prevention is limited to avoiding exposure. However, direct-acting antivirals (DAAs, tablets that block the virus from multiplying) can treat and cure HCV. DAAs cure more than 95% of people, meaning that no virus can be found in the blood 12 weeks after treatment ends. The treatment of HCV lasts about 8-12 weeks and costs between £20,000 to £60,000.
A needlestick exposure requires prompt assessment. Transmission risk depends on the infection, whether the source has transmissible virus, the depth and type of injury, the amount of blood transferred, and the exposed person’s hepatitis B immunity. The figures below are not universal probabilities for every injury.
- HIV: risk depends on the source’s infection and viral suppression (treatment keeping the amount of virus in the blood very low) and on the exposure. The British HIV Association (BHIVA) estimates the risk at about 0.3% (1 in 333) after a needlestick injury from a person with HIV who is not on suppressive treatment. Seek urgent assessment for post-exposure prophylaxis (PEP, medicines started soon after exposure to prevent infection).
- Hepatitis B: a susceptible worker (someone with no protective immunity) can face a substantial risk after exposure to infectious blood. Published estimates are 19% to 37% when the source is HBeAg positive. Documented vaccine-induced protection lowers that risk greatly. Source infectivity and injury characteristics also matter.
- Hepatitis C: risk depends on exposure to blood containing HCV RNA. The US Centers for Disease Control and Prevention (CDC) estimates an average risk of about 0.2% after percutaneous (through the skin) exposure, based on US studies. UK surveillance of healthcare workers from 1997 to 2007 found a higher rate of 2.2% (14 of 626). Neither figure is a prediction for an individual injury.
Report the exposure immediately for urgent assessment by occupational health (the hospital or employer service for staff health) or the emergency department. The source patient should be risk assessed and, if they consent, tested for HIV, hepatitis B and hepatitis C. Another member of staff, not the exposed person, should ask for that consent. HIV PEP, when indicated, should start as soon as possible, preferably within 24 hours. It should not be started more than 72 hours after the exposure. Hepatitis B management depends on vaccination, documented antibody response and source status, and may include vaccine and hepatitis B immunoglobulin (HBIG, ready-made antibodies against hepatitis B). There is no recommended routine antiviral post-exposure prophylaxis for hepatitis C; arrange testing and follow-up through occupational health, with treatment if infection is detected. NICE Clinical Knowledge Summaries (CKS) advise HCV antibody tests at 12 and 24 weeks and HCV RNA tests at 6, 12 and 24 weeks after the exposure.
- The PEP treatment for HIV consists of 3 different antiviral drugs (antiretrovirals, ARVs) for 28 days. A follow-up HIV test is then done at least 45 days after the course ends.
- The hepatitis B vaccine is very effective as post-exposure prophylaxis for a potential needlestick injury.
- Fully vaccinated (a complete primary course): no prophylaxis is needed if the source is HBsAg negative. If the source is HBsAg positive, a booster dose is given when the last dose was at least a year ago (a booster is considered if the source is unknown).
- Known non-responder to the vaccine (anti-HBs below 10 mIU/mL after the course): if the source is HBsAg positive or unknown, HBIG is given, with a booster dose of vaccine (a booster is considered if the source is unknown).
- Partly vaccinated: if the source is HBsAg positive or unknown, one dose of vaccine is given and the course is finished. If the source is HBsAg negative, the course is completed.
If someone has received a needlestick injury, they should wash the area with soap and water without squeezing the wound, cover it, and report to occupational health as soon as possible. If blood splashes into the eyes or mouth, they should flush the area with plenty of water. After this, they should be referred for counselling and follow-up blood tests. If they are given HIV PEP, they should also be advised to use condoms until their follow-up HIV test is negative.
Edited by: Dr. Thomas Burnell and Dr. Ben Appleby
Reviewed by: Dr. Marcus Judge
- 8890

