

By Dr. Marcus Judge & Dr. Ethan Kavanagh
Next Lesson - Principles of Medical Virology
Core
Antibiotics, also known as antibacterials, are a group of drugs used to treat infections caused by bacteria. They belong to a wider group, the antimicrobials, which also includes antiviral, antifungal and antiparasitic medicines. Antibiotics do not treat viral infections. This article also covers some antifungals and antivirals. Antibiotics come in a range of formulations, from topical creams to intravenous (IV) infusions used for more serious bacterial infections.
Since the discovery of penicillin by Fleming, there are now a wide range of antibiotics available for a doctor to prescribe. When designing an ideal antibiotic, or indeed any drug, there are a few desirable goals:
- A drug with few adverse side effects and few drug to drug interactions - improves patient comfort and compliance (taking the medicine as prescribed), and minimises further harm to the patient.
- Selectively toxic (also called specifically toxic) - it damages the target microbe but not the patient’s own cells and tissues.
- Able to achieve high concentrations at the site of infection.
- A long half-life reduces the need to frequently repeat doses.
- A wide range of formulations - allows for multiple routes of administration and application e.g. oral tablets for home use, IV formula to deliver directly into the bloodstream in hospital.
Half-life is the time taken for the concentration of a drug within plasma to fall to a half of what its initial starting concentration was. This is determined by how quickly the drug is eliminated (clearance) from the plasma and how widely it spreads within the tissues (volume of distribution). The desired length of half life depends on what the drug is being used for. With antibiotics, how long the drug stays active must suit the infection. It must also suit the drug’s pharmacokinetic properties (what the body does to the drug) and pharmacodynamic properties (what the drug does to the body). The aim is an effective concentration without unnecessary toxicity or extra doses. A long half-life can improve compliance, because the patient takes fewer doses (e.g. only 3 tablets instead of 7). In hospital, it also reduces the staff workload of giving repeat doses or re-hanging IV bags.
We can classify antibiotics based on a number of different criteria, such as:
- Lethal to bacteria (bactericidal) or slows/ stops growth and reproduction (bacteriostatic).
- Attack a wide variety of bacteria (broad spectrum) or specific to only a few types (narrow spectrum).
- The site of action on bacteria - where is the target site and what is the mechanism of action.
- Chemical structure of the antibiotic
These diagrams summarise antibiotic mechanisms of action. Trimethoprim and sulphonamides inhibit folate metabolism, reducing the availability of folate (a B vitamin) needed for nucleic acid synthesis:
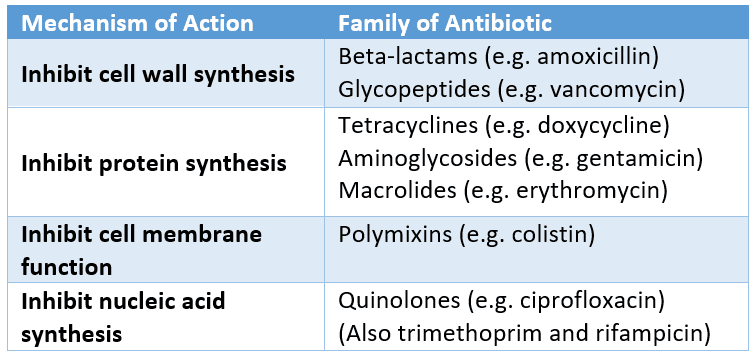
Figure: The mechanisms of antibiotics and the classes of antibiotics that use each mechanism. Trimethoprim is grouped here by its downstream effect on nucleic acid synthesis; its direct target is dihydrofolate reductase in folate metabolism.
SimpleMed original by Dr. Ethan Kavanagh
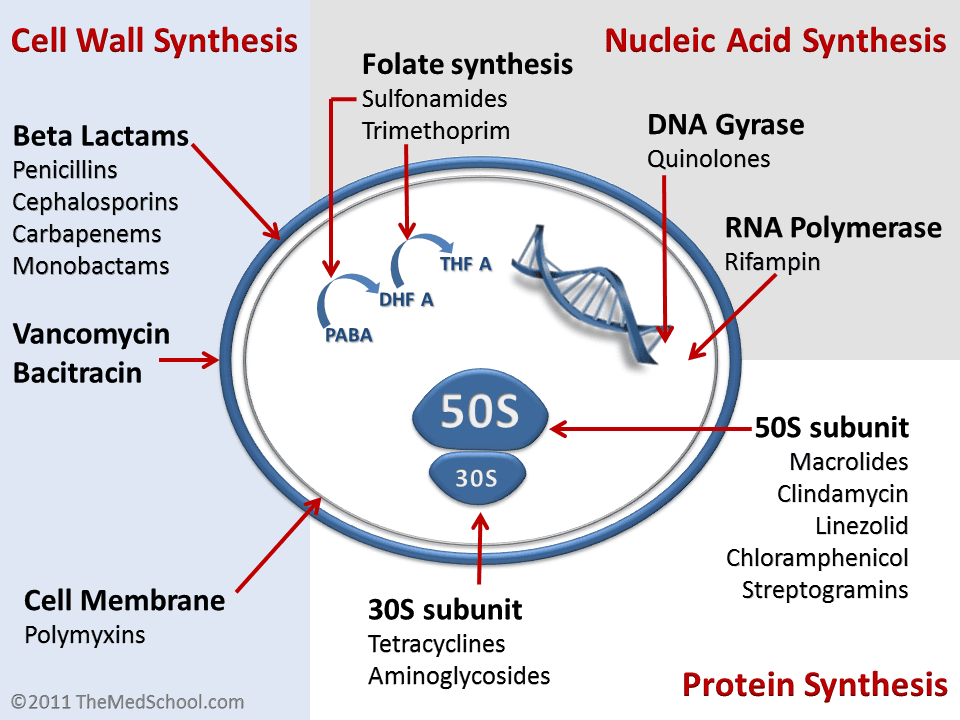
Figure: Shows the mechanism of action of antibiotics and where they act within bacteria. The folate pathway is simplified: sulphonamides inhibit dihydropteroate synthase upstream of dihydrofolate formation, while trimethoprim inhibits dihydrofolate reductase, which converts dihydrofolate to tetrahydrofolate.
Creative commons source by Kendrick Johnson [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
Key:
Family of antibiotic
- Class of antibiotic
- Example within the class
- Example within the class
Please see below the list for further information on specific antibiotics of note
Beta-lactams
- Penicillins
- Penicillin/ Benzylpenicillin
- Amoxicillin
- Flucloxacillin
- Co-amoxiclav
- Cephalosporins
- Ceftriaxone
- Carbapenems
- Meropenem
- Imipenem
The rest
- Glycopeptides
- Vancomycin
- Teicoplanin
- Tetracycline
- Tetracycline
- Doxycycline
- Macrolides
- Erythromycin
- Aminoglycosides
- Gentamicin
- Quinolones
- Ciprofloxacin
- Trimethoprim
- Trimethoprim
- Co-trimoxazole
Antifungals
- Polyenes
- Nystatin
- Amphotericin
- Azoles
- Fluconazole
Broad-spectrum antibiotics, particularly certain classes, are associated with a higher risk of C. difficile infection. Risk relates to the antibiotic class and spectrum rather than the first letter of the drug name.
N.B. This article mentions bacteria that are susceptible to (killed or stopped by) certain antibiotic classes, but local antibiotic prescribing guidelines are definitive in guiding treatment. If ever in doubt, check the British National Formulary (BNF) and local guidelines.
This is an umbrella group that encompasses four families of antibiotics: penicillins, cephalosporins, carbapenems and monobactams.

Figure: Shows the Beta-lactam family with examples of antibiotics within each family
Creative commons source by Helito, edited by Dr. Tom Burnell [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
Penicillins
Most penicillins have the suffix “-cillin” so you can mostly tell immediately if an antibiotic is a penicillin. In a variety of different ways, they all interfere with the third and final stage of bacterial cell wall synthesis.
Important penicillins to remember are benzylpenicillin (what is usually referred to as just ‘penicillin’ or Ben Pen), amoxicillin, flucloxacillin and co-amoxiclav.
Penicillins are particularly effective against Gram-positive bacteria (which stain purple with the Gram stain), mainly Streptococci (bacteria that grow in chains). These have a thicker and more exposed cell wall. Activity against Gram-negative bacteria (which have a thinner cell wall covered by an outer membrane) varies by penicillin subclass, with some agents such as amoxicillin having useful Gram-negative coverage. Flucloxacillin is effective against both Staphylococci and Streptococci.
Co-amoxiclav is a combination of amoxicillin and clavulanic acid (a beta-lactamase inhibitor). Amoxicillin’s efficacy versus some bacteria such as Staphylococcus aureus can be reduced (and is a mechanism of resistance) by an enzyme which these bacteria excrete called beta-lactamase. This beta-lactamase reduces antibacterial efficacy as it breaks down the antibiotic preventing it from working against the bacteria. Clavulanic acid inhibits beta-lactamase allowing amoxicillin to function for longer before it is broken down and thus making it more effective. This makes co-amoxiclav active against beta-lactamase-producing bacteria that are resistant to amoxicillin alone. These include resistant strains of Staphylococcus aureus, Escherichia coli and Haemophilus influenzae, as well as many Bacteroides species (anaerobic bacteria) and Klebsiella species (Gram-negative bacteria). It should be kept for infections likely, or known, to be caused by these amoxicillin-resistant bacteria.
Cephalosporins
There are considered to be five generations of cephalosporins but each of them works by inhibiting cell wall synthesis.
Unlike some penicillins, most cephalosporins have limited activity against anaerobic bacteria, but they are otherwise relatively broad spectrum. Ceftriaxone is useful in treating meningitis. Cephalosporins pass poorly into the cerebrospinal fluid unless the meninges are inflamed, as they are in meningitis. Ceftriaxone and cefotaxime are suitable cephalosporins for these infections.
There is some concern over cephalosporins causing Clostridium difficile infection. C. diff is a commensal bacterium (one that can live harmlessly in the body) found in your normal gut microbiome (the community of microbes that live in the gut). It competes for nutrients with the other gut flora. This constant competition prevents C. diff overgrowth. Cephalosporins can also eliminate some of the natural gut flora as well as the pathogenic organism in an infection. This reduces competition allowing C. diff to proliferate and overgrow, causing disease.
A commonly taught rule of thumb is that several antibiotics beginning with the letter ‘C’ are associated with an increased risk of C. diff infection. However, this is an oversimplification. The risk relates more to the antibiotic spectrum and impact on gut flora rather than the name itself.
Carbapenems
Meropenem is the main carbapenem that works by inhibiting cell wall synthesis. Alongside Gram-positive and Gram-negative bacteria, it is active against anaerobic bacteria. Meropenem and imipenem are also active against Pseudomonas aeruginosa, although acquired resistance is emerging. Carbapenems are not active against meticillin-resistant Staphylococcus aureus (MRSA) or Enterococcus faecium (a Gram-positive gut bacterium).
Meropenem has a similar chemical structure to penicillins (both are beta-lactams), so a patient with a penicillin allergy may also react to it. The BNF advises avoiding meropenem if the patient has had an immediate hypersensitivity reaction (a rapid allergic reaction) to a beta-lactam antibiotic. It should be used with caution in patients with other beta-lactam sensitivity.
Vancomycin is the main glycopeptide. It inhibits cell wall synthesis by preventing two subunits from being incorporated into the peptidoglycan matrix that is the core structural component of the cell walls of Gram-positive bacteria. It is active against both aerobic and anaerobic Gram-positive bacteria. It can also affect membrane permeability and RNA synthesis of the bacteria, but the key mechanism is inhibition of cell wall synthesis. When vancomycin is given intravenously, it has a narrow therapeutic window (a small gap between an effective dose and a toxic one). Doses are therefore adjusted according to blood levels of the drug (therapeutic drug monitoring).
Vancomycin is used to treat serious Gram-positive infections, including those caused by MRSA. Given by mouth, it is also the first-line treatment for C. difficile infection. Many bacteria are still sensitive to it, including multi-resistant staphylococci, so it is used only when it is needed, to slow the spread of resistance. There are some reports of reduced susceptibility in Staphylococcus aureus and reports of glycopeptide resistant enterococci.
Vancomycin is normally given IV (especially for systemic infections, which affect the whole body) because it isn’t absorbed via the gut. The exception to this is in the case of a C. diff infection whereby it is given orally because the infection is in the gastrointestinal (GI) tract.
The other glycopeptide of note is Teicoplanin. This has a larger therapeutic index and is therefore much easier to monitor with the risk of a toxic dose less likely.

Figure: Shows the process of vancomycin resistance
Creative commons source by Mcstrother [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
The two main tetracyclines are doxycycline and tetracycline. Both are bacteriostatic antibiotics through their action of inhibiting protein synthesis of the bacteria. This holds the bacteria in the stationary phase of their growth cycle (when they stop multiplying) instead of killing them outright, which would be bactericidal. Both doxycycline and tetracycline are broad-spectrum antibiotics. Doxycycline is one option for some infections in patients with a penicillin allergy, such as low-severity community-acquired pneumonia (pneumonia caught outside hospital).
These antibiotics are effective against illness such as Chlamydia, rocky mountain spotted fever and typhoid fever. Their value has decreased because of increasing bacterial resistance, but they are still useful for a number of illnesses. One example is leptospirosis (an infection caught from the urine of infected animals) in patients with a penicillin allergy, where a tetracycline is an alternative to erythromycin.
Tetracycline should not be given to children under 12 years old. It binds to calcium in growing bones and teeth, which stains the teeth and occasionally causes dental hypoplasia (poorly formed tooth enamel). In the UK, tetracycline is given by mouth. Calcium, for example in milk, binds to tetracyclines (chelation) and can reduce how much is absorbed.
Aminoglycosides include gentamicin (the main aminoglycoside), amikacin and streptomycin. They work by inhibiting protein synthesis. They have a bactericidal action which is particularly strong against Gram-negative bacteria.
Aminoglycosides are active against many Gram-negative and some Gram-positive bacteria. Gentamicin, amikacin and tobramycin are also active against Pseudomonas aeruginosa. Streptomycin is active against Mycobacterium tuberculosis and is now used almost only for tuberculosis.
Gentamicin has good activity in the blood and urine. It is the aminoglycoside of choice in the UK and is used widely for serious infections, such as Gram-negative sepsis. When the cause of a serious infection is not yet known, it is usually given with a penicillin or metronidazole (or both). It is inactive against anaerobes and has poor activity against haemolytic streptococci (streptococci that break down red blood cells) and pneumococci (Streptococcus pneumoniae).
Gentamicin does have a couple of issues though. It is nephrotoxic (damaging to the kidney), as it attacks the cells of the proximal convoluted tubule (the first part of the nephron’s tubule). This kidney damage is usually reversible. Gentamicin is mainly removed by the kidneys, so it can build up if the kidneys are already impaired, which increases the risk of kidney and ear damage. It also causes ototoxicity (damage to the inner ear), which is usually irreversible. It damages the sensory cells of both the cochlea (the hearing organ) and the vestibular system (the balance organ). Damage to the hair cells of the cochlea leads to a loss of high frequency hearing, followed by low frequency hearing. People with certain mitochondrial DNA variants (particularly m.1555A>G) have a higher risk of deafness.
Because of these risks, patients on gentamicin are monitored for symptoms, and their hearing and balance should also be checked. Blood levels of gentamicin are measured to keep them within the therapeutic window, which helps to prevent toxicity and makes sure the drug works. Courses are kept as short as possible: whenever possible, treatment should not go beyond 7 days.
Macrolides work by inhibiting protein synthesis. They include erythromycin, clarithromycin and azithromycin. They have a similar spectrum of action to that of penicillins, which makes them a good alternative in patients with a penicillin allergy (for mild Gram-positive infections). They are also active against many penicillin-resistant staphylococci, but some of these are now also resistant to macrolides.
Erythromycin is good for atypical pathogens in pneumonia (bacteria such as Mycoplasma pneumoniae that amoxicillin does not reliably treat), Legionnaires’ disease, early syphilis and Chlamydia. What it does not have great activity against is Haemophilus influenzae.
Another issue with erythromycin specifically, is that it tends to make patients nauseous, vomit or give them diarrhoea. If a patient has a mild infection then a lower dose can be prescribed, but when the infection is more serious (such as with a Legionella infection/pneumonia) then a higher dose needs to be prescribed. This is where the good and bad need to be compared to see which possible treatment plan has the best effect with the least repercussions for the patient.
Both azithromycin and erythromycin have activity against many Gram-positive bacteria, particularly Streptococcus species. Azithromycin is slightly less active than erythromycin against Gram-positive bacteria, but more active against some Gram-negative bacteria, including H. influenzae. Clarithromycin was derived from erythromycin and is slightly more active than it. Clarithromycin is used to treat Helicobacter pylori infection. NICE recommends a proton pump inhibitor (PPI, a drug that suppresses stomach acid) with amoxicillin and either clarithromycin or metronidazole. For people with a penicillin allergy, it recommends a PPI with clarithromycin and metronidazole.
Quinolones are a collection of antibiotics that work by inhibiting bacterial replication through inhibiting DNA gyrase (a bacterial enzyme that coils and uncoils DNA so it can be copied). Within the UK, the only quinolones that are available to prescribe are fluoroquinolones so they are the only ones that will be touched on in this article.
Ciprofloxacin is best against Gram-negative bacteria such as Escherichia coli, Salmonella and Shigella. It is only moderately active against Gram-positive bacteria such as Streptococcus, and a lot of Staphylococci are resistant to quinolones so make sure not to use them in MRSA infections. Resistance amongst other bacteria to quinolones is also increasing, and there is a risk of a C. diff infection for those taking quinolones.
Ciprofloxacin is given as an eye drop, ointment, orally and IV. It is used for UTIs, some GI infections and septicaemia due to susceptible organisms. It is not routinely used for gonorrhoea in the UK because of resistance, unless susceptibility is confirmed. Researchers are also studying whether ciprofloxacin could be used against cancer. Most of this evidence is preclinical (from laboratory and animal research, not studies in patients), so it is not an established cancer treatment.
Trimethoprim and Sulphonamides
Trimethoprim inhibits bacterial dihydrofolate reductase (DHFR), which converts dihydrofolate to tetrahydrofolate in the folate pathway. Trimethoprim is also available in combination with the sulphonamide sulfamethoxazole. Sulphonamides inhibit bacterial dihydropteroate synthase (DHPS), an earlier enzyme in the same pathway, by competing with para-aminobenzoic acid (PABA). This combination, co-trimoxazole, blocks the folate pathway at two different stages. The drugs potentiate (boost) each other's antibacterial activity in vitro (in laboratory tests); clinical effectiveness depends on organism susceptibility and the infection being treated. For acute uncomplicated urinary tract infections, or acute exacerbations (flare-ups) of chronic bronchitis, co-trimoxazole should be used only when there is evidence of susceptibility. There should also be a good reason to prefer the combination to a single antibiotic.
Trimethoprim is used to treat and prevent urinary tract infections. It is occasionally used for acne that has not responded to other antibiotics, although it is not licensed for this. It is an alternative for acute prostatitis (infection of the prostate gland) when a fluoroquinolone is unsuitable, with specialist advice and treatment guided by susceptibility results when available. Co-trimoxazole is also used to treat pneumocystis pneumonia (a lung infection caused by the organism Pneumocystis jirovecii). Trimethoprim is a folate antagonist (it blocks the use of folate), so it carries a risk of harm to the developing baby (a teratogenic risk) in the first trimester, the first 12 weeks of pregnancy. Manufacturers advise avoiding it during pregnancy. Any use in pregnancy requires an individual benefit-risk assessment and a check of current prescribing guidance and the specific product's contraindications.
This article covers two main families of antifungals: azoles and polyenes. Other antifungals include the echinocandins (such as caspofungin), which act only against Candida and Aspergillus, and terbinafine, which is the drug of choice for fungal nail infections.
Fluconazole is an example of an azole. It can be used for both systemic and superficial fungal infections. Of the azoles, fluconazole is less often linked with liver damage than itraconazole, but it still interacts with many other medicines (see below). Some resistant strains of Candida have been detected, so a susceptibility test will need to be done first before prescribing. Fluconazole is not effective against Aspergillus (a type of fungus). For aspergillosis, voriconazole is the treatment of choice. Posaconazole is used if the infection does not respond to, or the patient cannot tolerate, other antifungals such as itraconazole or amphotericin.
Fluconazole works by inhibiting ergosterol synthesis in the fungal cell membrane, impairing membrane function and growth. Ergosterol is a fat-like molecule (a sterol) that fungi need in their cell membranes, much as human cells use cholesterol. Fluconazole is not completely selective for fungi: it also inhibits some human cytochrome P450 enzymes (enzymes, mainly in the liver, that break down many drugs). This means it interacts with other medicines. For example, it increases the anticoagulant effect of warfarin and raises blood levels of simvastatin (a statin used to lower cholesterol).
Polyenes do not share a common name ending, unlike the azoles, whose names end in -azole. The mechanism of action of polyenes is to inhibit cell membrane function. Neither nystatin nor amphotericin is absorbed when given by mouth. Nystatin is used for Candida infections by local application, for example as a liquid held in the mouth for oral thrush. Amphotericin is given intravenously for systemic fungal infections, but it is toxic when given this way and side effects are common.
Aciclovir works by inhibiting viral DNA polymerase (the enzyme that copies the virus’s DNA). It is used against herpes simplex virus and varicella zoster virus. Herpes simplex causes genital herpes, and it can also infect other sites, such as the skin, the eye and the brain (encephalitis). Varicella zoster causes chickenpox and shingles. An enzyme made by these viruses phosphorylates aciclovir (adds phosphate groups to it), which turns it into its active form so that it can begin to work.
There has been debate over the use of aciclovir in Bell’s palsy (sudden weakness of one side of the face, caused by a problem with the facial nerve). NICE CKS advises considering prednisolone (a steroid) for people who present within 72 hours of their symptoms starting. Antivirals such as aciclovir are not recommended on their own. Adding an antiviral to a steroid may give a small benefit, but specialist advice should be sought first. This is a great example where you can turn to the evidence behind the use of aciclovir (and steroids for that matter) to treat Bell’s palsy. If you check out the facts, you’ll see that:
- A large proportion of cases of Bell’s palsy will resolve on their own over time.
- Prescribing aciclovir on its own has not been shown to provide significant benefit in most cases.
- Steroids alone give a significant benefit, and adding aciclovir to a steroid may make only a small extra difference.
So, for a small difference which may or may not help the patient, is prescribing the combination therapy a good idea? Taking an extra medicine is a burden for the patient, and the cost of the drugs to the NHS also matters. This debate is beyond the aims of this article, but still an interesting point.
Oseltamivir, sold under the brand name Tamiflu®, is another antiviral but it works by inhibiting neuraminidase (a viral enzyme that releases new virus particles from infected cells). It is used specifically as prophylaxis and treatment of patients that are of at least two weeks of age and have had symptoms of Influenza A and/or Influenza B for no more than forty-eight hours. Oseltamivir phosphate is a pro-drug (an inactive form that the body converts into the active drug). It is an ethyl ester, which an enzyme called carboxylesterase 1 converts into the active drug, oseltamivir carboxylate. So, unlike aciclovir, it is not activated by having phosphate added.
One final drug that requires mentioning is metronidazole. Its main targets are anaerobic bacteria and protozoa (single-celled parasites).
It is used for many infections, including H. pylori, fistulae in Crohn’s disease, bacterial vaginosis, pelvic inflammatory disease, ulcerative gingivitis and protozoal infections such as amoebiasis, trichomoniasis and giardiasis. It is also active against Clostridioides difficile, but it is no longer a first-line treatment for C. difficile infection (see below).
The length of a metronidazole course depends on the infection. Many anaerobic infections are usually treated for 7 days, while bacterial vaginosis can be treated for 5 to 7 days or with a single dose. For C. diff infection, NICE recommends oral vancomycin for 10 days first line, and oral fidaxomicin for 10 days if vancomycin does not work. Metronidazole is now only given intravenously, alongside oral vancomycin, when specialists advise it (for example, in life-threatening infection). Other antibiotics should be reviewed and stopped unless essential. The need for proton pump inhibitors should also be reviewed, because acid-suppressing drugs are a risk factor for C. diff infection.
Unfortunately as a consequence of natural selection and random mutation bacteria can easily develop resistance to antibiotics. There are three main types of antibiotic resistance:
- Intrinsic - the bacteria have no target for the drug to work on e.g. a penicillin can’t act on a microbe without a cell wall, because the cell wall is where penicillin acts.
- Acquired - this is done either through mutation or horizontal gene transfer.
- Adaptive - the bacteria are only resistant when exposed to an antibiotic as they adapt to the environment. This form of resistance is unstable, therefore when the antibiotic is removed, the bacteria become susceptible once again. (This is one reason why an antibiotic may work less well as treatment goes on.)
Acquired resistance is the most commonly referred to mechanism of antibiotic resistance and is linked with antibiotic overuse.
Development of Resistance by Mutation
Resistance by mutation develops in several simple steps.
Within a population of bacteria, through random mutation, some bacteria will develop antibiotic resistant traits. This is of no real concern as these bacteria are few and far between within the larger population. On the introduction of a selection pressure i.e. the introduction of an antibiotic, only these resistant cells will survive and are thus selected for. This is a problem, because only the resistant bacteria are left alive to reproduce. This leads to a population which is entirely resistant to the antibiotic, compared to one with only a few resistant individuals.

Figure: Shows how antibiotic resistance develops through natural selection as only the high resistance bacteria are selected for
Creative commons source by Wykis [CC BY-SA 3.0 (https://creativecommons.org/licenses/by-sa/3.0)]
Horizontal gene transfer is the sharing of genetic material between bacteria in the same generation, rather than from parent to offspring. It happens in three main ways. In conjugation, DNA passes from one bacterium to another by direct contact. In transformation, a bacterium takes up free DNA from its surroundings. In transduction, DNA is carried between bacteria by bacteriophages (viruses that infect bacteria). Horizontal gene transfer allows luxury genes (extra genes that are not essential for survival) to be passed between bacteria, often on plasmids (small circles of DNA separate from the main chromosome). Some luxury genes confer antibiotic resistance attributes and as a result can lead to the spread of antibiotic resistance, even between different species.
Editor’s note: It is unrealistic to be able to remember every single antibiotic and its uses but it is helpful to be familiar with some examples, mechanisms and principles of antibiotics which this article hopes to achieve. For practitioners in the UK the BNF is the definitive guide for all drugs (please see our disclaimer at the foot of the page) and should be considered along with your local antibiotics guidelines.
Edited by: Dr. Ben Appleby and Dr. Thomas Burnell
- 35694



