

Next Lesson - HPA and Growth Hormone
Core
The adrenal glands are situated above the kidneys. They consist of (from peripheral to central) a capsule, a cortex, and a medulla.
The adrenal cortex can be sub-divided into the zona glomerulosa, zona fasciculata, and zona reticularis, which all function to produce different types of corticosteroids (steroid hormones made by the adrenal cortex), outlined below:
- Zona glomerulosa: produces mineralocorticoids (hormones that control salt and water balance), for example aldosterone.
- Zona fasciculata: produces glucocorticoids (hormones that mainly affect glucose handling and inflammation), for example cortisol and corticosterone. Cortisone is an inactive form of cortisol, made from cortisol by the enzyme 11β-hydroxysteroid dehydrogenase in other tissues.
- Zona reticularis: produces glucocorticoids and androgens (male-type sex hormones), for example dehydroepiandrosterone (DHEA) and androstenedione. Other tissues (such as the gonads) convert these into testosterone and oestrogens.
A useful saying to help you remember the different layers of the adrenal cortex and what they produce is 'salt, sugar, sex; the deeper you go the sweeter it gets'!
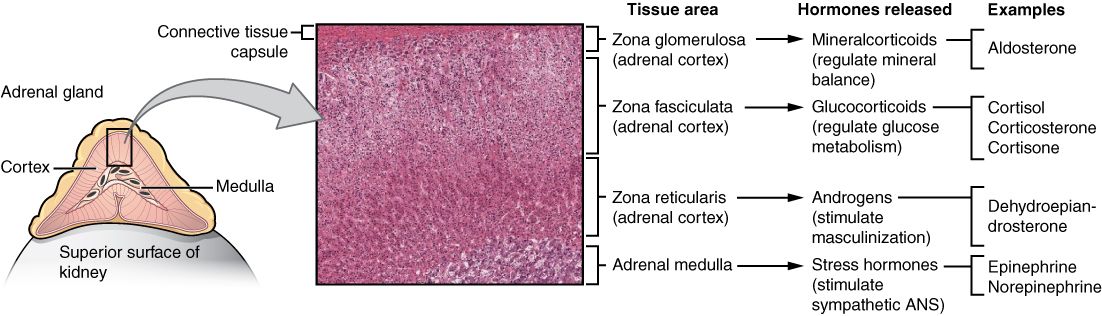
Diagram: Shows the different layers of the adrenal gland histologically (under the microscope) and the hormones each layer produces.
Creative commons source by OpenStax College [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
Corticosteroids are an example of steroid hormones that are produced in the adrenal cortex (hence the cortico- in the name). Steroid hormones are synthesised from cholesterol and are lipid soluble hormones that bind to nuclear receptors. They mainly act through modulating gene transcription.
Corticosteroids enter cells through simple diffusion across the plasma membrane, where they bind to their own receptors: glucocorticoids bind to glucocorticoid receptors, and mineralocorticoids such as aldosterone bind to mineralocorticoid receptors. The steps below are described for glucocorticoids. Glucocorticoid binding causes the dissociation of chaperone proteins from the receptor. Chaperone proteins hold the receptor inactive until the hormone binds (an example is heat shock protein 90). The receptor-ligand complex (the receptor with its hormone attached; the hormone is the ligand) can then translocate (move) to the nucleus. There, two receptors join together (dimerisation). The complex then binds to glucocorticoid response elements (GREs), which are specific sequences on DNA. In summary, glucocorticoids bind to glucocorticoid receptors, which dissociates chaperone proteins, causing translocation to the nucleus and binding to DNA.
Aldosterone is the most abundant mineralocorticoid in the body. It is transported in the blood bound to serum albumin and, to a lesser extent, transcortin (corticosteroid-binding globulin, a carrier protein in the blood).
The main function of aldosterone is the regulation of plasma [Na+] and [K+], in order to control arterial blood pressure. It acts on the distal tubules and collecting ducts (the later parts of the kidney nephrons, where urine is finalised). There it promotes Na+ reabsorption and K+ excretion. It does this by increasing production of the Na+/K+ ATPase pump (a membrane pump that uses energy from ATP to move sodium out of the cell and potassium in) and of epithelial sodium channels (ENaC). Water follows the reabsorbed sodium, so this causes an increase in water reabsorption. This consequently causes an increase in blood volume and therefore increases blood pressure. Aldosterone release is mainly controlled by the Renin-Angiotensin-Aldosterone-System (RAAS). When blood pressure falls, the kidney releases renin (an enzyme). Renin starts a chain of steps that makes angiotensin II (a hormone that narrows blood vessels), and angiotensin II stimulates the adrenal cortex to release aldosterone. The system is outlined below:

Diagram: Shows an overview of the Renin-Angiotensin-Aldosterone-System. The RAAS is covered in the Cardiovascular Article Hypertension.
SimpleMed Original by Dr. Jenny Hubball
Hyperaldosteronism is defined as a condition in which there is excessive production of aldosterone. This can be further divided into primary and secondary hyperaldosteronism:
- Primary hyperaldosteronism: excess aldosterone production due to a defect in the adrenal cortex.
- The main defect of the adrenal cortex which causes the hyperaldosteronism is bilateral idiopathic adrenal hyperplasia (overgrowth of both adrenal glands, with no known cause), but an aldosterone-secreting adrenal tumour (Conn’s syndrome) can also be the cause.
- Secondary hyperaldosteronism: excess aldosterone production due to overactivity of the RAAS.
- Overactivity of the RAAS can be caused by, for example, a renin-producing tumour or renal artery stenosis (narrowing of the artery that supplies the kidney).
The two types differ in their renin levels (renin is the enzyme that starts the RAAS). Primary hyperaldosteronism produces low renin levels (there is a high aldosterone:renin ratio). Secondary hyperaldosteronism produces high renin levels (there is a low aldosterone:renin ratio).
Signs and symptoms of hyperaldosteronism include:
- High blood pressure
- Left ventricular hypertrophy
- Hypernatraemia (high blood sodium), which is usually mild
- Hypokalaemia (low blood potassium), which is present in only some patients
Excess aldosterone makes the body retain salt and water, which raises blood pressure. Aldosterone also makes the kidneys lose potassium in the urine. Left ventricular hypertrophy (thickening of the wall of the left ventricle) is more common in primary aldosteronism than in essential hypertension (high blood pressure with no single identified cause).
Treatment of hyperaldosteronism depends on the cause. If one adrenal gland is the source, for example an aldosterone-secreting adenoma (a benign tumour of gland tissue), surgery is preferred (laparoscopic adrenalectomy, removal of the gland through small cuts). Spironolactone (a mineralocorticoid receptor antagonist, which blocks the receptor that aldosterone acts on) is used mainly for bilateral adrenal hyperplasia, or when surgery is unsuitable.
Cortisol is the most abundant glucocorticoid. In an adult, about 10 mg of cortisol and about 3 mg of corticosterone are secreted each day. It is transported in the blood bound to transcortin. The levels of cortisol are highest in the morning, and cortisol levels fluctuate during the day in a daily (circadian) rhythm.
Cortisol is released from the adrenal cortex in response to adrenocorticotropic hormone (ACTH) released from the anterior pituitary gland. ACTH is released in response to corticotropin-releasing hormone (CRH), released from the hypothalamus. Cortisol itself controls this through negative feedback: it acts on the anterior pituitary and hypothalamus to inhibit CRH and ACTH release.

Diagram: Shows the negative feedback mechanism in the control of cortisol production.
SimpleMed Original by Dr. Jenny Hubball
Cortisol has a wide range of systemic effects:
- Catabolic effects (effects that break down molecules and tissues):
- Increases protein breakdown in muscle.
- Increases lipolysis (the breakdown of fat) in fat tissue.
- Increases gluconeogenesis in the liver.
- In the muscle, cortisol inhibits insulin-induced GLUT4 translocation (the movement of GLUT4, a glucose transporter, to the cell surface). This prevents glucose uptake by the muscle, so more glucose stays in the blood. This is called a glucose-sparing effect.
- Resistance to stress:
- Increases supply of glucose in the blood.
- Raises blood pressure through increasing the sensitivity of blood vessels to vasoconstrictors.
- Anti-inflammatory effects:
- Inhibits macrophage activity
- Inhibits mast cell degranulation (mast cells release histamine and other inflammatory chemicals).
- Suppression of the immune response:
- Corticosteroid drugs such as prednisolone (synthetic steroids that act like cortisol) are used in organ transplant patients, for example to treat acute rejection, because they suppress the immune response.
Steroid receptors form part of a family of nuclear DNA binding proteins (including thyroid and vitamin D receptors). They all have three main regions, a hydrophobic hormone-binding region (hydrophobic means water-repelling), a DNA-binding region rich in cysteine (an amino acid) and basic amino acids, and a variable region. There is sequence homology (similarity in structure) in the hormone binding regions of the receptors. The hormone binding region of the glucocorticoid receptor is most similar to that of the mineralocorticoid receptor, then the androgen receptor, then the oestrogen receptor, and least similar to the thyroid receptor. This means that cortisol can bind to the mineralocorticoid receptor with an affinity (binding strength) similar to that of aldosterone, and to the androgen receptor with low affinity. In the kidney, the enzyme 11β-hydroxysteroid dehydrogenase type 2 inactivates cortisol, so aldosterone normally activates the mineralocorticoid receptor. This protection may fail when high levels of the hormone are present.
Cushing's Syndrome is caused by chronic excessive exposure to cortisol. The main cause of Cushing’s syndrome is prescribed glucocorticoids (steroid drugs), but there can also be endogenous causes (causes from inside the body):
- Cushing’s Disease: caused by a benign pituitary adenoma (a tumour of gland tissue) that secretes ACTH.
- Adrenal Cushing’s: caused by excess cortisol produced by an adrenal tumour.
- Other: caused by non-pituitary-adrenal tumours producing ACTH and/or CRH (e.g. a lung tumour such as small cell lung cancer). Tumours that make ACTH in an unusual place like this are called ectopic. They cause about 10 to 20% of the cases driven by too much ACTH (ACTH-dependent Cushing’s syndrome).
The signs and symptoms of Cushing’s syndrome include:
- Plethoric (red, flushed) moon-shaped face
- Buffalo hump - hump behind the shoulders caused by fat deposition
- Abdominal obesity - due to the redistribution of fat
- Purple striae (stretch marks) - cortisol thins and weakens the skin, so it tears when stretched by fat deposition
- Gradual weight gain
- Easy bruising and thin skin
- Weakness of the muscles around the hips and shoulders (proximal muscle weakness)
- Hyperglycaemia (high blood glucose) - due to increased gluconeogenesis
- Hypertension - due to mineralocorticoid effects of excess cortisol
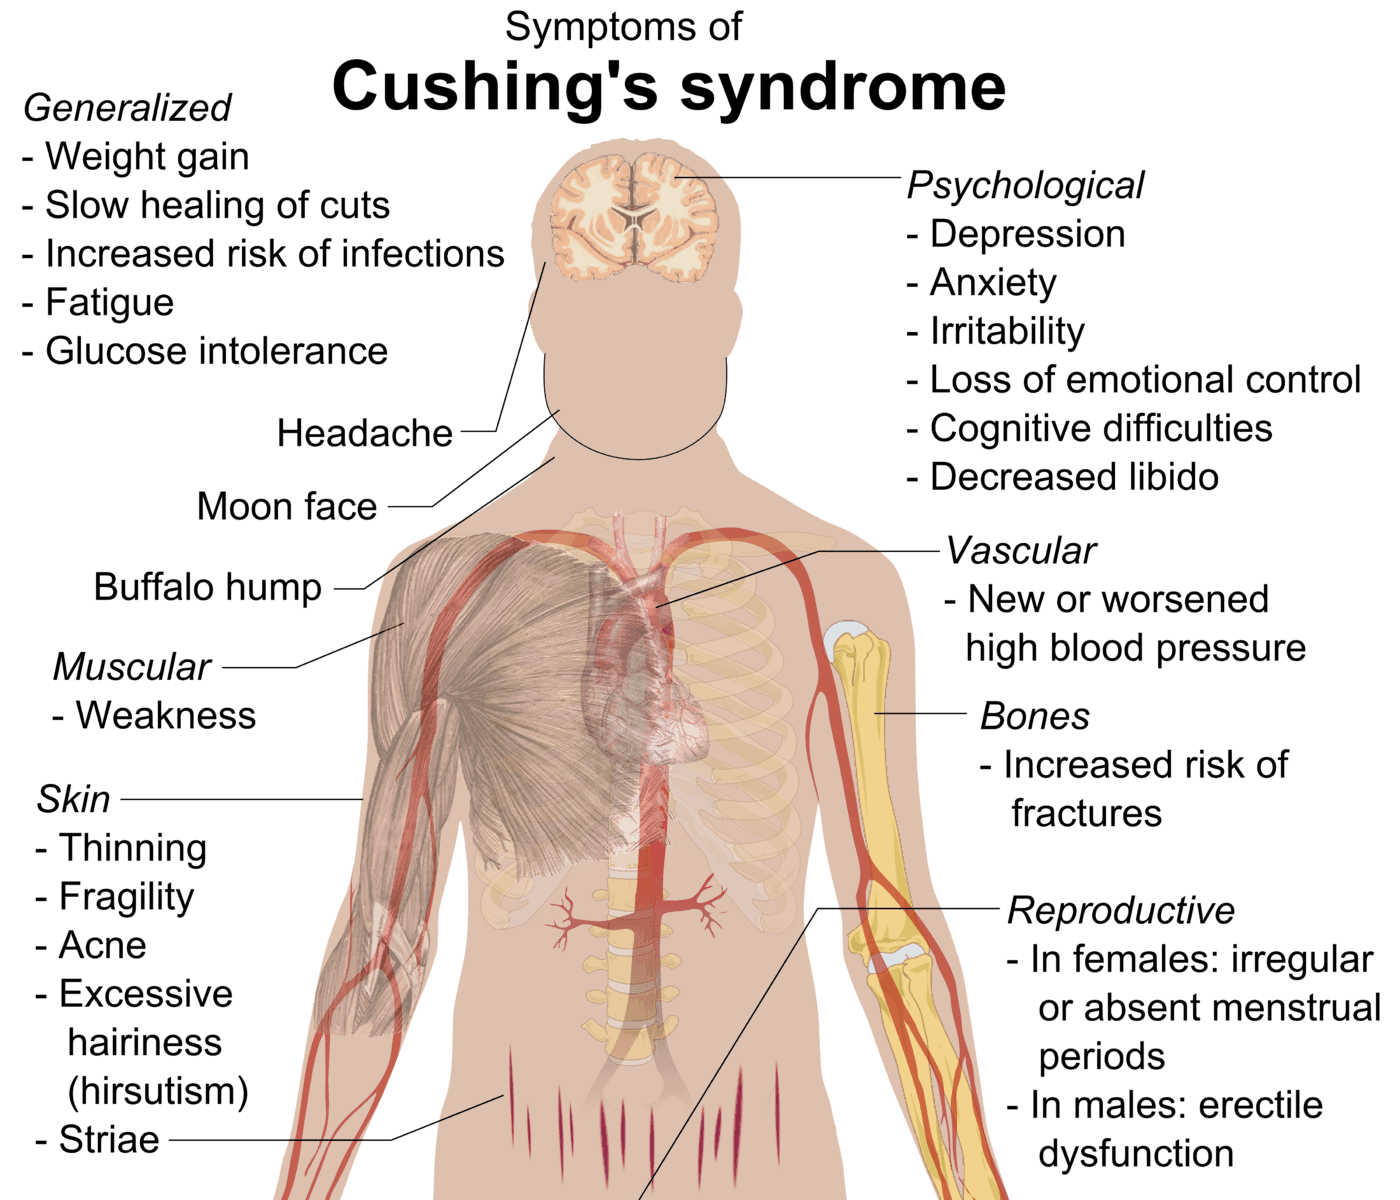
Diagram: Shows the symptoms of a patient with Cushing's Syndrome.
Creative commons source by Mikael Häggström [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
It is important to note that the side effects of steroid drugs (e.g. prednisolone and dexamethasone) are similar to the effects of higher levels of cortisol. One difference is that dexamethasone has negligible mineralocorticoid action and prednisolone only a slight one, so they are less likely than excess cortisol to cause salt and water retention. Long-term steroid treatment can suppress the body’s own cortisol production (adrenal suppression). Steroids taken for a long time should therefore be reduced gradually and not stopped suddenly, because stopping suddenly can cause adrenal insufficiency (the adrenal glands cannot make enough cortisol).
Androgens and Genetic Defects in the Adrenal Glands
Androgens are partially regulated by ACTH and CRH.
In pre-pubescent males dehydroepiandrosterone (DHEA) released from the adrenal glands is converted to testosterone in other tissues of the body (called peripheral conversion). After puberty this production is insignificant as the testes themselves release testosterone.
In females, adrenal androgens promote libido (sex drive), and are converted to oestrogens by other tissues. After menopause, the conversion of adrenal androgens is the only source of oestrogens in the body. The ovaries act as a source of oestrogens after puberty.
In both sexes, androgens promote axillary (armpit) and pubic hair growth.
A number of clinical conditions, together called congenital adrenal hyperplasia (CAH), can arise as a genetic defect in one or more enzymes required for the synthesis of corticosteroid hormones from cholesterol. This causes a lack of cortisol. With less cortisol there is less negative feedback (think about the negative feedback loop discussed earlier), so the pituitary releases large amounts of ACTH. The high ACTH in turn causes adrenal cortex hyperplasia (the adrenal cortex grows larger).
The severity and consequences of these conditions depend on which enzyme is affected. The most common form is deficiency of the 21-hydroxylase enzyme, which is needed to make cortisol and aldosterone. The enzyme sits on the pathway that makes corticosteroids from cholesterol, so the deficiency decreases glucocorticoid production. In the more severe salt-wasting form (at least three-quarters of classic cases), mineralocorticoid production falls too. The steroid precursors that build up behind the blocked enzyme step (such as 17α-hydroxyprogesterone, 17-OHP) are therefore diverted to more androgen synthesis. In female infants, this excess androgen is converted to testosterone and can cause genital ambiguity (external genitalia that are not clearly male or female). In the salt-wasting form, lack of aldosterone causes “salt-wasting crises”, because a lot of sodium is lost in the urine.
The adrenal medulla is a modified sympathetic ganglion of the autonomic nervous system which contains chromaffin cells (cells that release hormones). Chromaffin cells lack axons, but act as post-ganglionic nerve fibres that release adrenaline and noradrenaline (both catecholamines, hormones that help the body respond to stress) into the blood. Adrenaline and noradrenaline are released in roughly a 4:1 ratio, with adrenaline in the larger share (noradrenaline is roughly 5% to 25% of the catecholamines in the human adrenal medulla). The enzyme N-methyl transferase (phenylethanolamine N-methyltransferase, PNMT) converts noradrenaline into adrenaline inside chromaffin cells.
Adrenaline works through associated G protein-coupled receptors (GPCRs), and its actions can be thought of in terms of the fight or flight response.
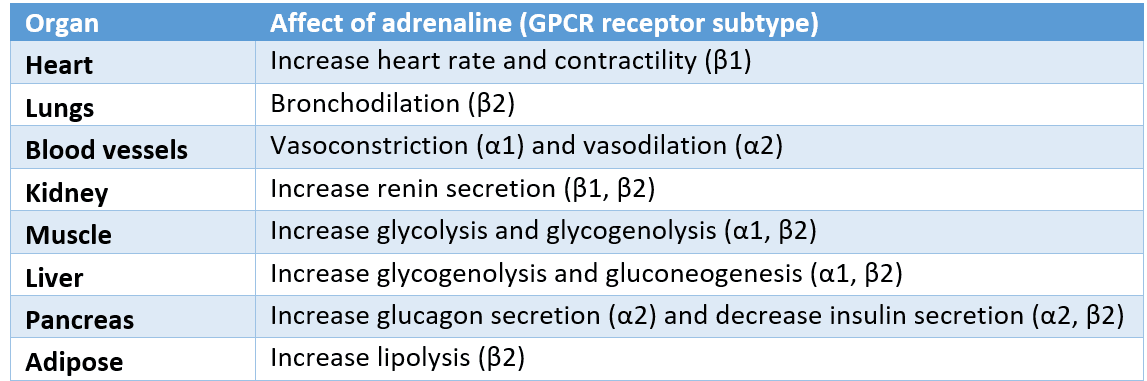
Diagram: Shows the actions of adrenaline in the body and the receptors it acts on.
SimpleMed Original by Dr. Jenny Hubball
Phaeochromocytoma
A chromaffin cell tumour that secretes catecholamines (about half mainly secrete adrenaline, and the others mainly noradrenaline). Under the microscope (histologically), phaeochromocytomas are characteristic because they stain dark with chromium salts. Diagnosis starts with a blood or urine test for metanephrines (breakdown products of adrenaline and noradrenaline). CT scanning (or MRI in some patients) then locates the tumour.
The tumour releases too much adrenaline and noradrenaline, which cause the characteristic features:
- Severe hypertension - this may become life-threatening
- Headaches
- Palpitations
- Diaphoresis (sweating)
- Anxiety
- Weight loss
- Elevated blood glucose
The primary treatment of a phaeochromocytoma is surgical resection (removal of the tumour). Drugs that block catecholamine receptors are also an important part of management. An alpha blocker (a drug that blocks alpha receptors, which relaxes blood vessels) is started first. A beta blocker (a drug that blocks beta receptors) is added later, and only together with an alpha blocker, never on its own.
Addison’s disease
Chronic adrenal insufficiency means the adrenal glands cannot make enough hormones over a long period. Addison’s disease is chronic adrenal insufficiency caused by disease of the adrenal glands themselves (primary adrenal insufficiency). In Western countries it is most commonly caused by destruction of the adrenal cortex (wasting, or atrophy) by an autoimmune response, in which the immune system attacks the glands. This accounts for around 90% of cases. Other causes include infections such as tuberculosis, cancer that has spread to the adrenal glands, and adrenal haemorrhage (bleeding into the glands). Chronic adrenal insufficiency can also be caused by long-term steroid treatment, or by disease of the hypothalamus or pituitary gland. These causes are not Addison’s disease.
Signs and symptoms of Addison’s disease include:
- Postural hypotension (low blood pressure on standing)
- Lethargy
- Weight loss
- Anorexia (loss of appetite)
- Increased skin pigmentation
- Hypoglycaemia (low blood glucose)
- Nausea or vomiting
- Salt craving
- Low blood sodium (hyponatraemia) and high blood potassium (hyperkalaemia), because of aldosterone deficiency
The hyperpigmentation seen in Addison’s disease is caused by a decrease in cortisol levels. This means there is reduced negative feedback on the anterior pituitary, and so more pro-opiomelanocortin (POMC) is produced to synthesise ACTH. POMC also produces alpha-melanocyte-stimulating hormone (α-MSH), which causes melanin synthesis, and thus hyperpigmentation. The ACTH itself can also activate melanocortin receptors on melanocytes, thus also contributing to the hyperpigmentation directly.
Adrenal crisis (Addisonian crisis)
A life-threatening emergency due to adrenal insufficiency.
Stress and illness raise the body’s need for cortisol. If the adrenal glands cannot meet that need, an adrenal crisis can follow. An adrenal crisis can be triggered by:
- Severe stress
- Salt deprivation
- Infection or other illness, including vomiting
- Trauma or surgery
- Cold exposure
- Overexertion
- Abrupt steroid drug withdrawal
The signs and symptoms include:
- Nausea
- Vomiting
- Pyrexia (fever)
- Hypotension
- Vascular collapse (circulatory shock)
An adrenal crisis is treated straight away. Adults are given 100 mg of hydrocortisone (a form of cortisol given as a drug) by injection into a vein or muscle. They are also given 1 litre of 0.9% sodium chloride (saline) into a vein over 30 minutes, and are admitted to hospital as an emergency. Treatment is not delayed to do tests.
Suspected adrenocortical disease (disease of the adrenal cortex) is investigated with blood and urine tests. Plasma cortisol is measured at a set time, usually 8 to 9 am, because cortisol follows a daily rhythm and is highest in the morning. ACTH helps to show where the problem lies: it is high in Addison’s disease (primary adrenal insufficiency) but low in secondary adrenal insufficiency. For suspected Cushing’s syndrome, the first-line screening tests are the overnight dexamethasone suppression test, 24-hour urinary free cortisol (cortisol measured in urine collected over a full day) and late-night salivary cortisol. Dynamic function tests (tests that give a stimulus and measure the response, such as the dexamethasone suppression test and ACTH stimulation tests) may then be used in the differential diagnosis (working out the cause).
- Dexamethasone (a strong steroid drug) normally suppresses ACTH release and so lowers cortisol. In the overnight test, 1 mg is given at night and cortisol is measured the next morning. This low-dose test is used to screen for Cushing’s syndrome.
- A higher dose of dexamethasone can help to find the cause of ACTH-dependent Cushing’s syndrome. Suppression of plasma cortisol by >50% suggests Cushing’s disease, but suppression does not normally occur with adrenal tumours or ectopic ACTH production (ACTH made outside the pituitary, for example by a lung tumour). The test is imperfect, so scans and other tests are also used.
- Synacthen (tetracosactide, a synthetic form of ACTH) is given by injection (250 micrograms), and cortisol is measured before and 30 or 60 minutes afterwards. Cortisol would normally rise. In Addison’s disease the adrenal cortex is already stimulated as much as it can be by the body’s own ACTH, so cortisol does not rise adequately (a peak below 500 nanomol/L is diagnostic of primary adrenal insufficiency). A normal rise in cortisol after Synacthen usually excludes Addison’s disease.
Reviewed by: Dr. Marcus Judge
Edited by: Dr. Maddie Swannack
- 12783


