

Next Lesson - When Haematopoiesis Goes Wrong
Core
Haemoglobin (Hb) is a globular protein (a compact, rounded protein) composed of four protein chains. These four chains are made up of 2α paired with 2 other chain types (see table below for normal variants of these chains). Each globin chain holds a haem group (a ring-shaped molecule) with an iron (Fe2+) ion at its centre. This iron ion is the part that binds oxygen.
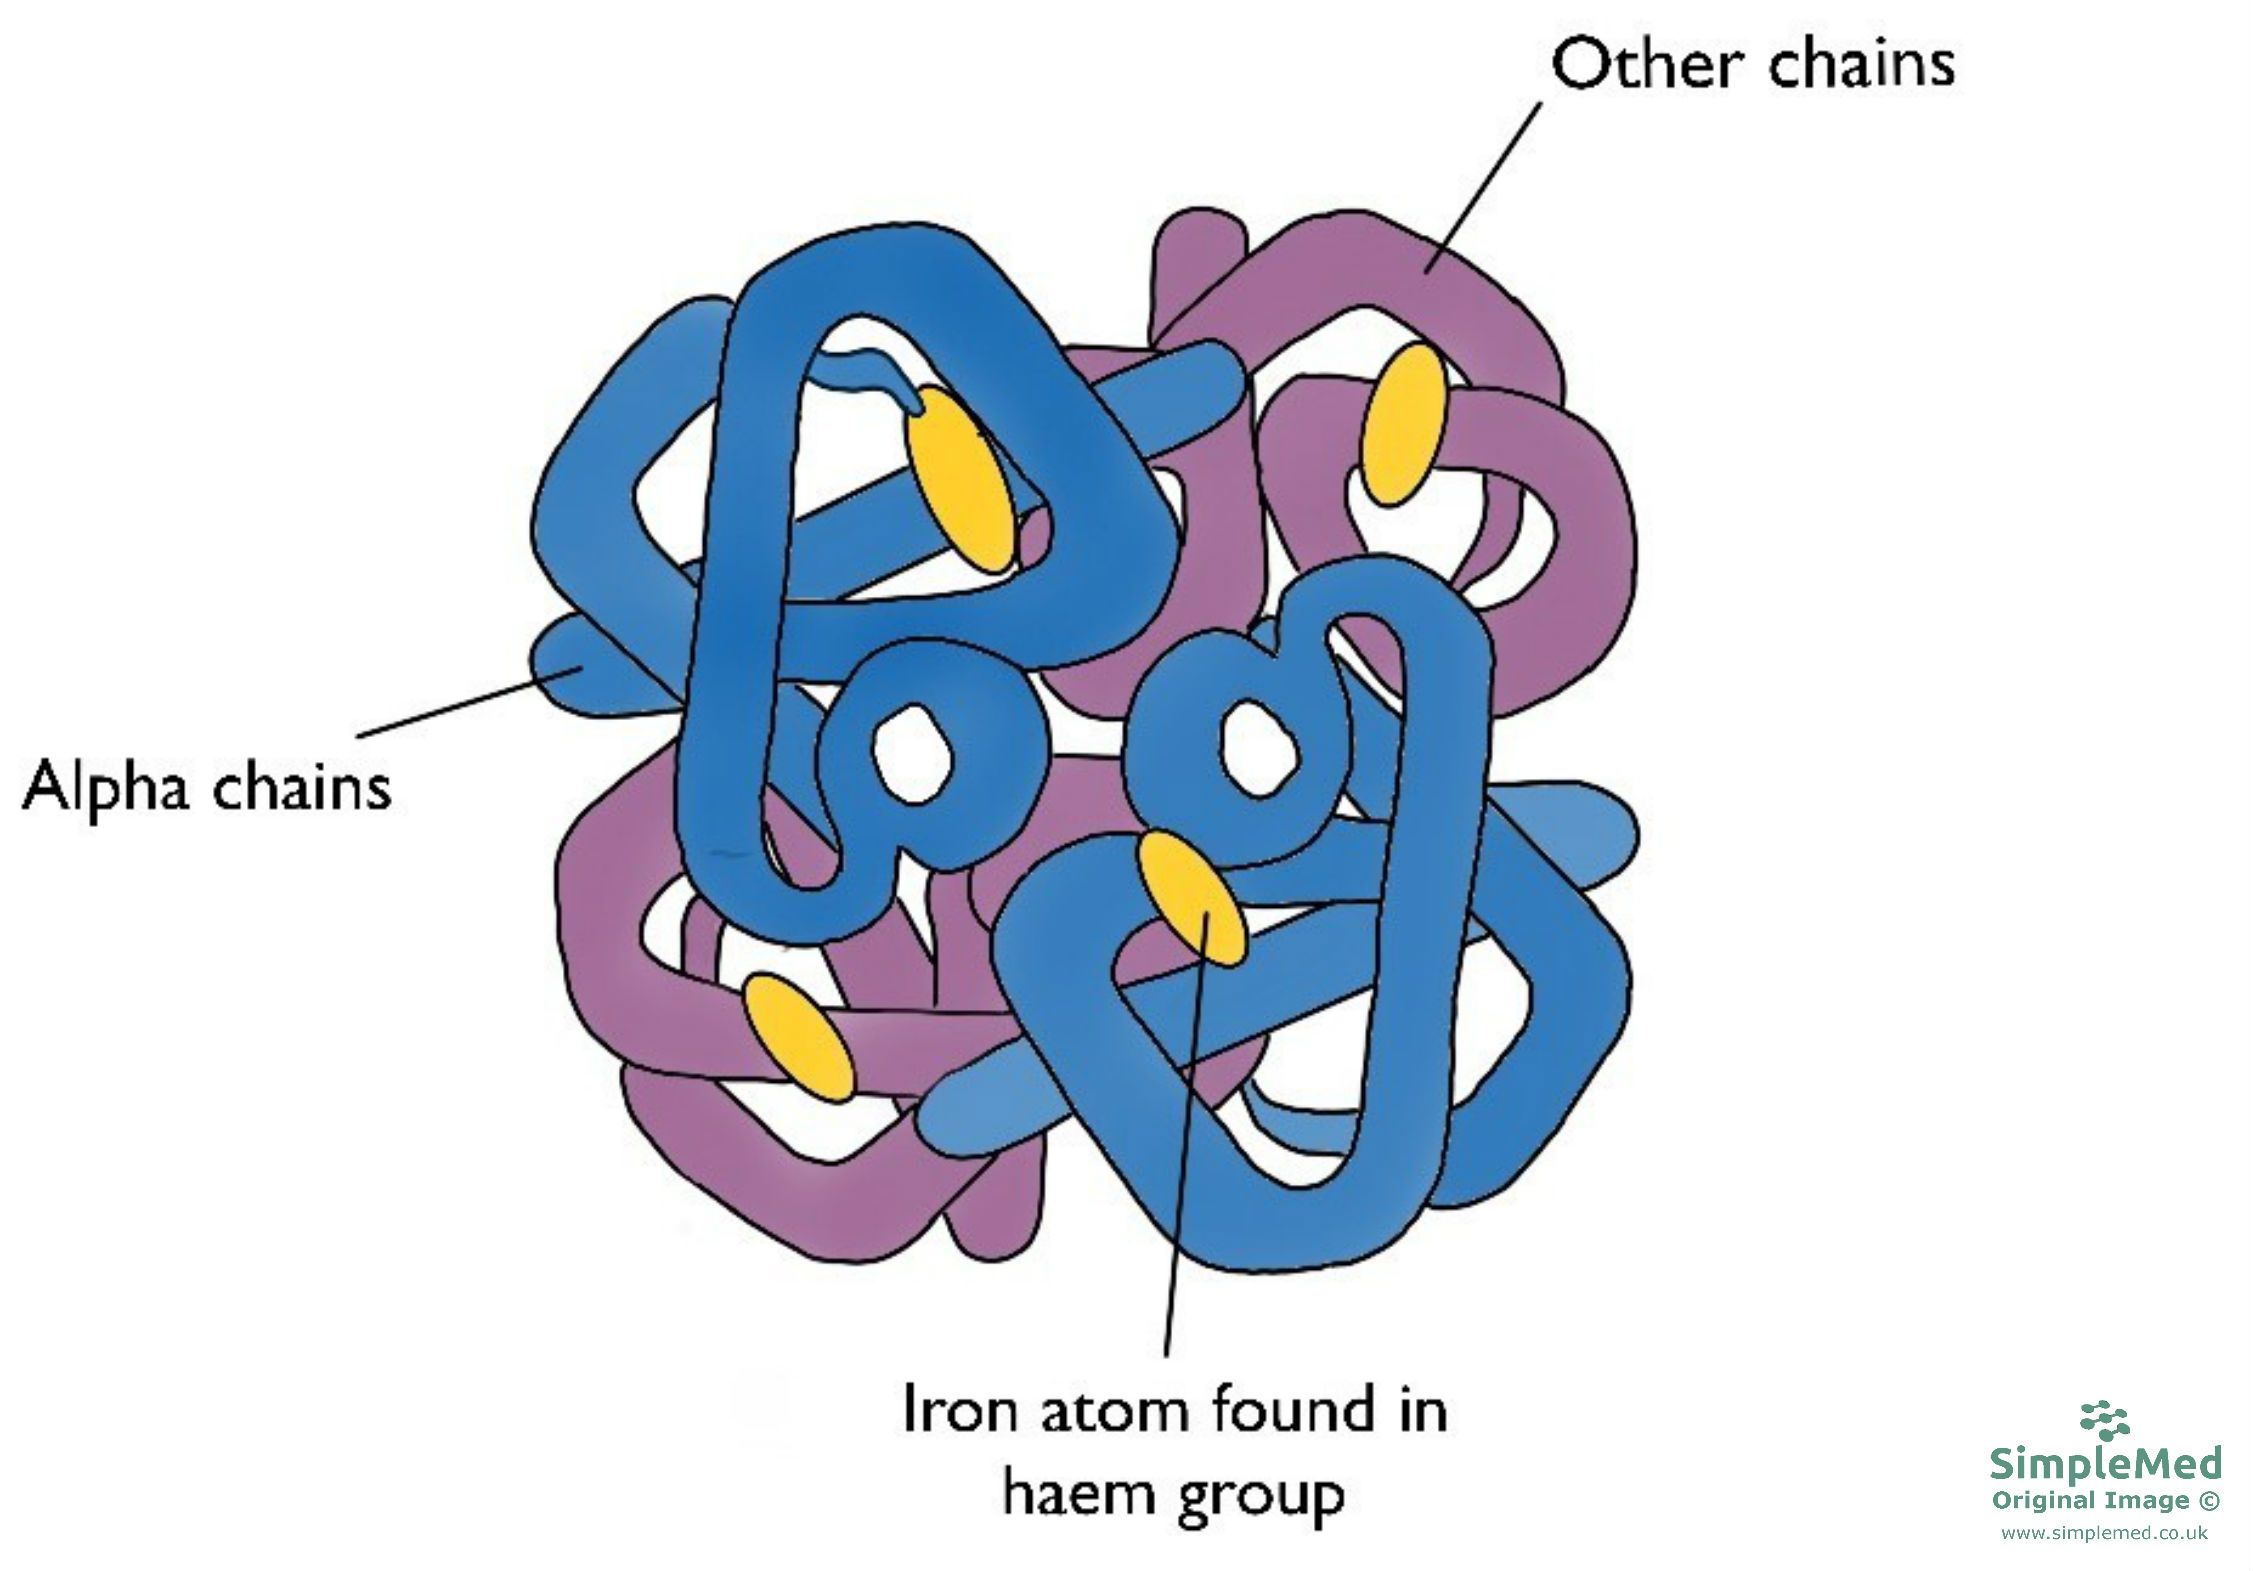
Figure 1. The structure of haemoglobin
SimpleMed original by Dr. Keertana Anne
Common forms of normal (physiological) haemoglobin found in the adult body are highlighted in the table below.
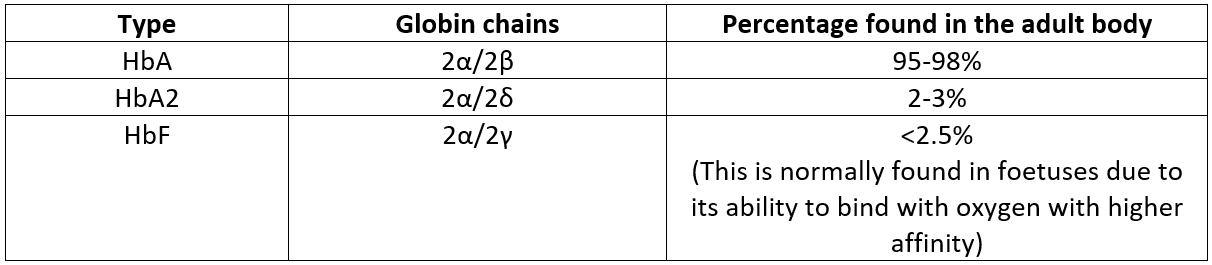
Figure 2. A table of the different haemoglobin variants
SimpleMed original by Dr. Keertana Anne
Mutations to the DNA which codes for Hb can produce haemoglobin variants. Some mutations do not cause disease and often go undetected, and these are called non-pathological variants. On the other hand, some mutations may be pathological (disease-causing) and lead to haemoglobinopathy.
Haemoglobinopathies are genetic disorders (usually autosomal recessive) that affect haemoglobin in one of two ways. Either its structure is altered, giving deformed molecules (as in sickle cell disease), or too little of a particular globin chain is made, which is called thalassaemia (covered in more detail later). Either problem reduces the oxygen carrying capacity of the blood, and produces symptoms of anaemia (for more details, see our article on Anaemia).
The most common types of haemoglobinopathies are thalassaemias and sickle cell disease.
Thalassaemias are autosomal recessive, inherited diseases resulting from the reduced rate of synthesis of normal α- or β- globin chains. This results in a lower level of haemoglobin inside each red cell. The red cells are therefore hypochromic (paler than normal) and microcytic (smaller than normal) in patients with thalassaemia. In thalassaemia, abnormal red cells are broken down in the spleen, contributing to anaemia. Iron from haem is normally recycled, but patients may develop iron overload due to increased intestinal absorption and repeated blood transfusions. Splenomegaly (an enlarged spleen) and hypersplenism (an overactive spleen that destroys too many blood cells) can worsen anaemia. Splenectomy (removal of the spleen) is reserved for selected cases because the operation has long-term risks.
Thalassaemias are classified based on which globin chain is affected. α-globin chains are encoded by two closely linked genes on chromosome 16. We each have two copies of chromosome 16, so we have four α-globin genes in total. β-globin chains are encoded by a single gene on chromosome 11, so we have two β-globin genes in total.
α-thalassaemia:
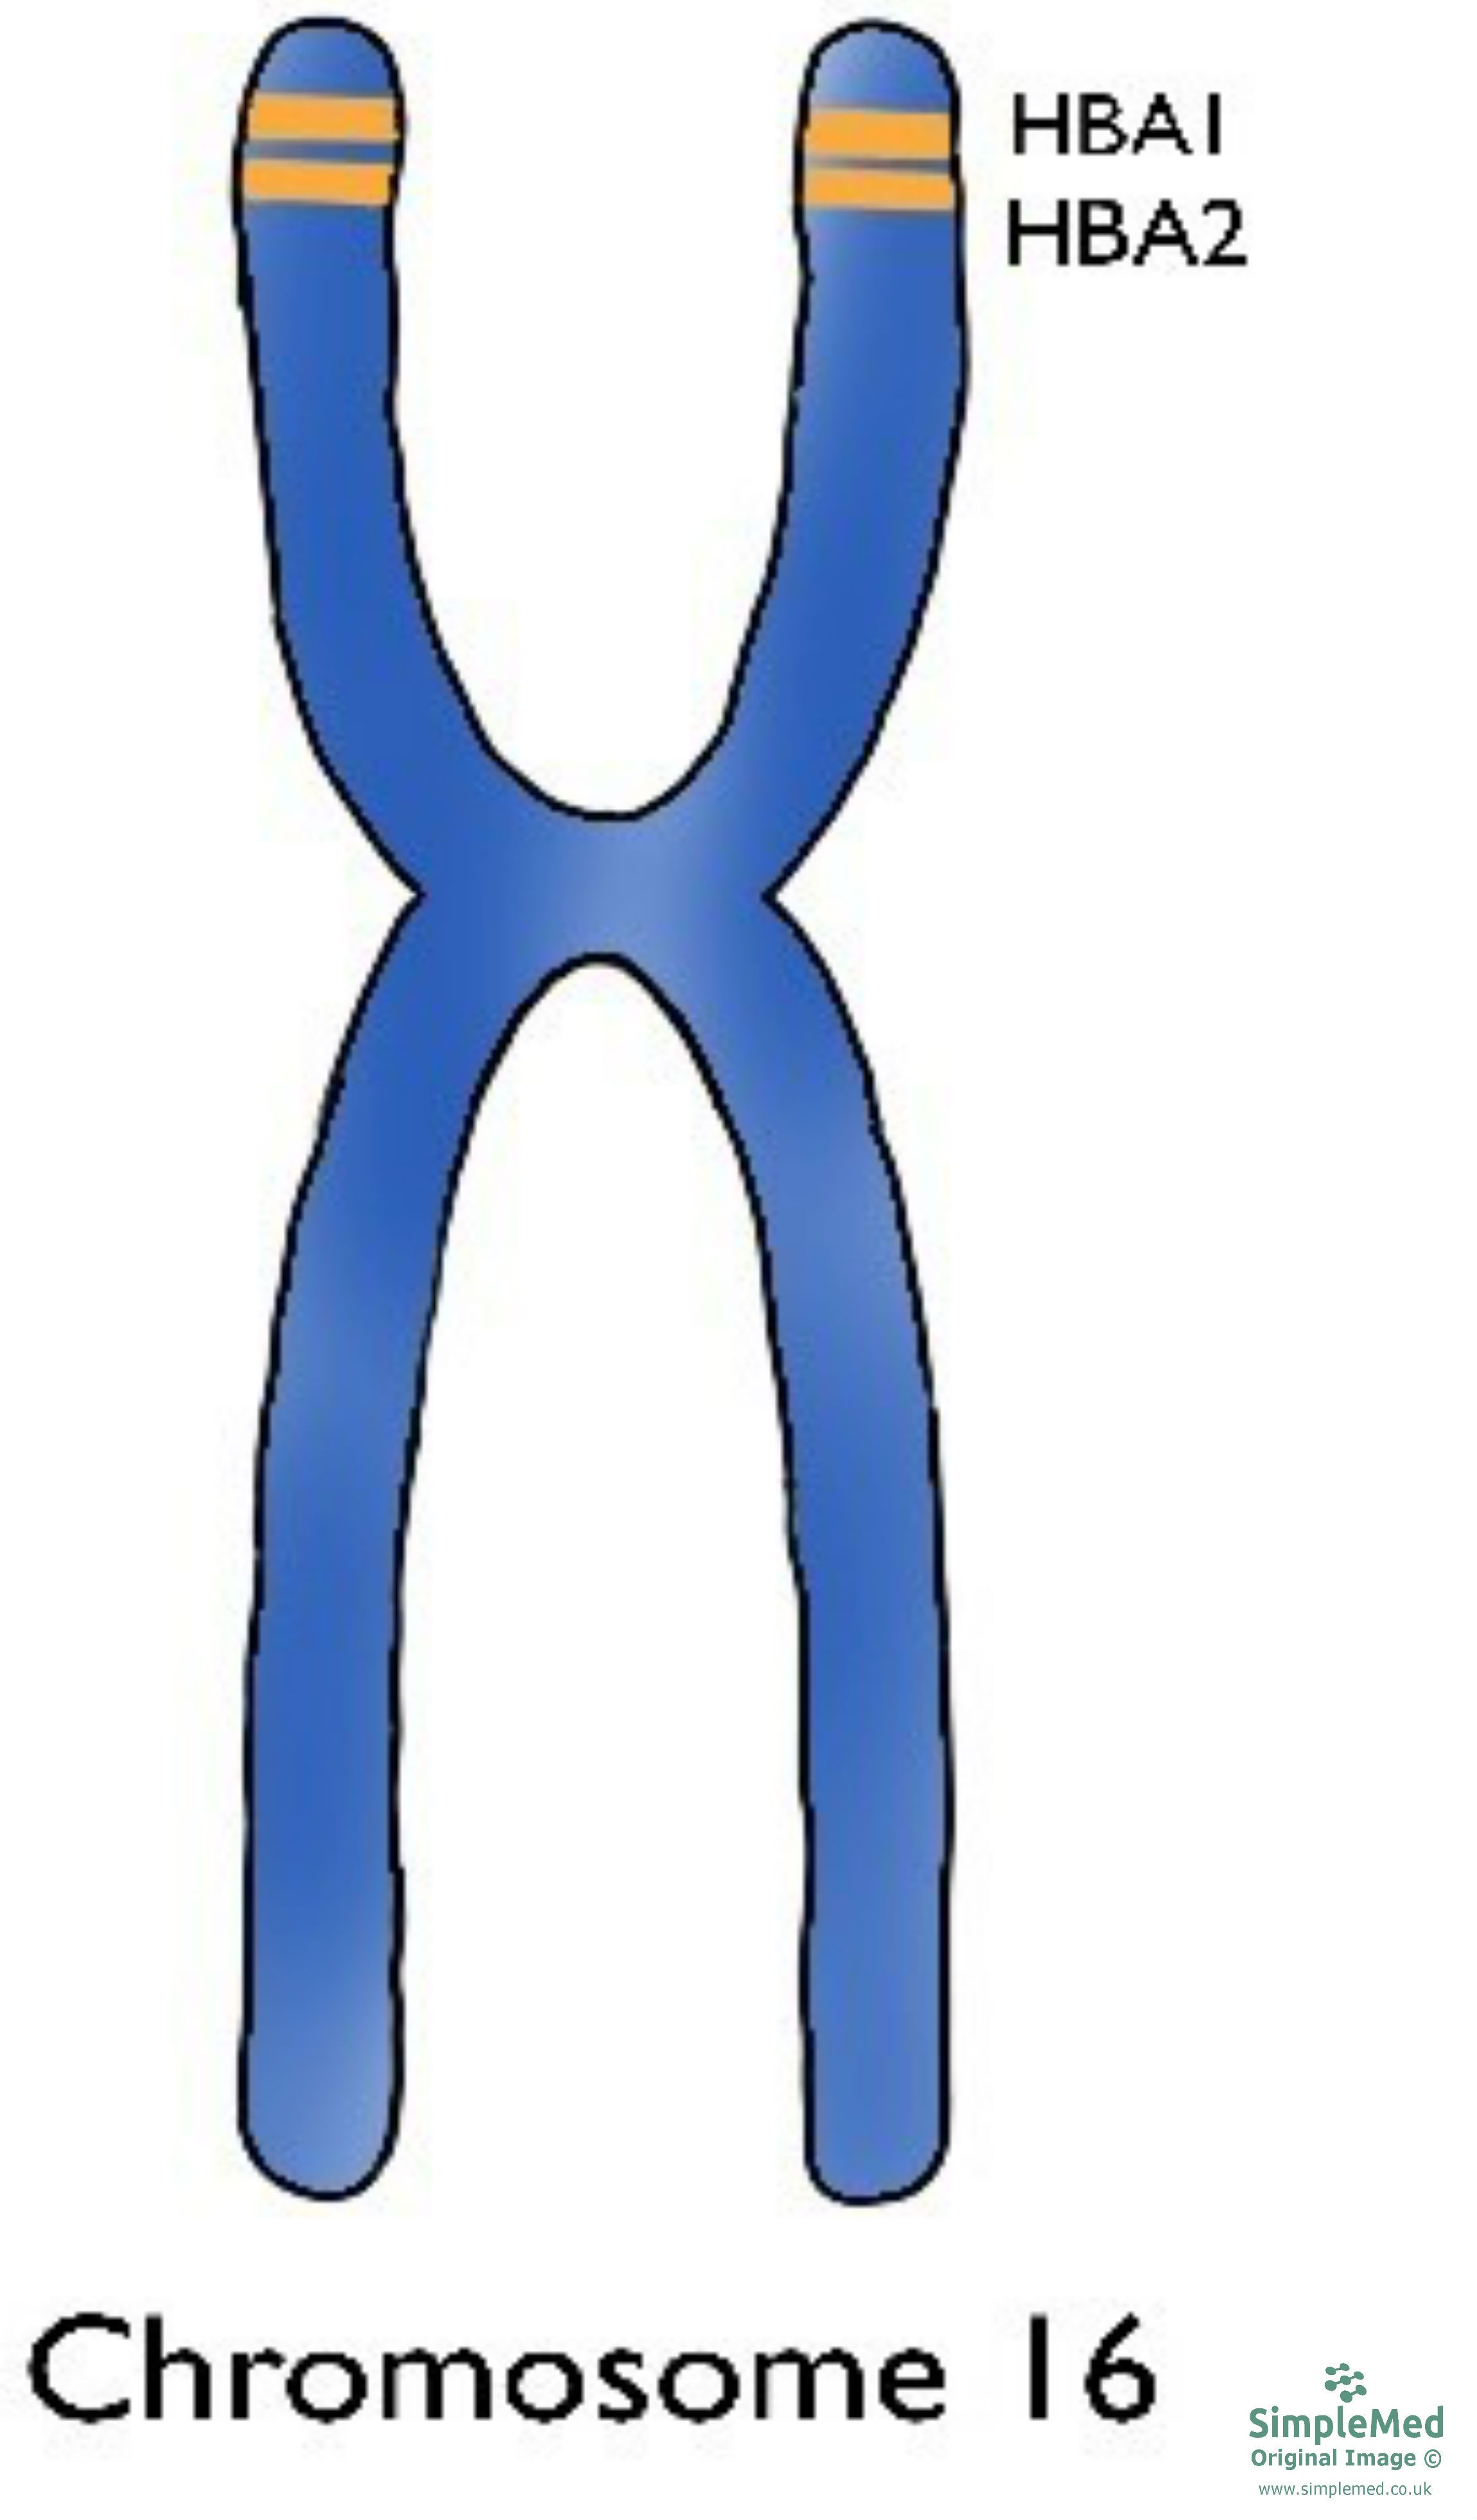
Figure 3. Chromosome 16 with the location of the α-globin chain gene shown
SimpleMed original by Dr. Keertana Anne
α-thalassaemias are caused by mutations (usually deletions, meaning that part of the gene is lost) in the HBA1 and/or HBA2 genes (the two α-globin genes) on chromosome 16. Deletion of α-globin genes means fewer α chains are made. This leaves an excess of β chains in adults, and γ chains in fetuses. The patient therefore makes less normal haemoglobin (2α paired with 2 other chains). How much less depends on how many of the four α-globin genes are lost, and if all four are lost none can be made. The relative excess of these other chains leads to defective red cells, which are destroyed in large numbers by the spleen. This causes haemolytic anaemia (anaemia from red cells being broken down early).
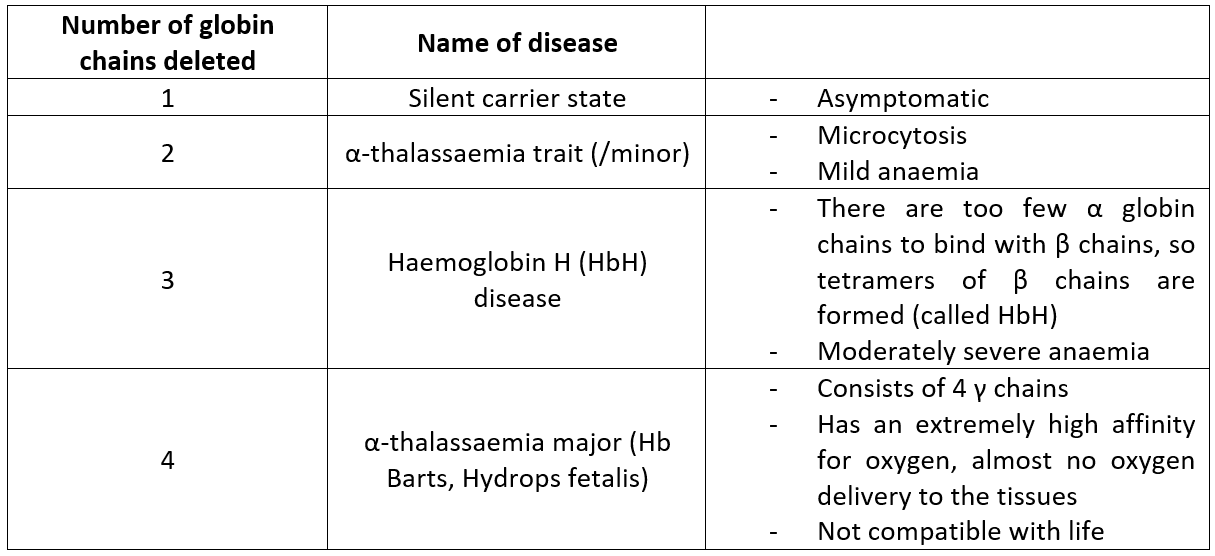
Figure 4. A table of the different types of α-thalassaemias
SimpleMed original by Dr. Keertana Anne
Alpha thalassaemias are most commonly seen in African, Caribbean, South Asian, Chinese, South East Asian, Middle Eastern and Mediterranean populations. Carriers are more common in these groups, which is why NHS antenatal screening uses a family origin questionnaire in areas where these conditions are less common.
β-thalassaemia:
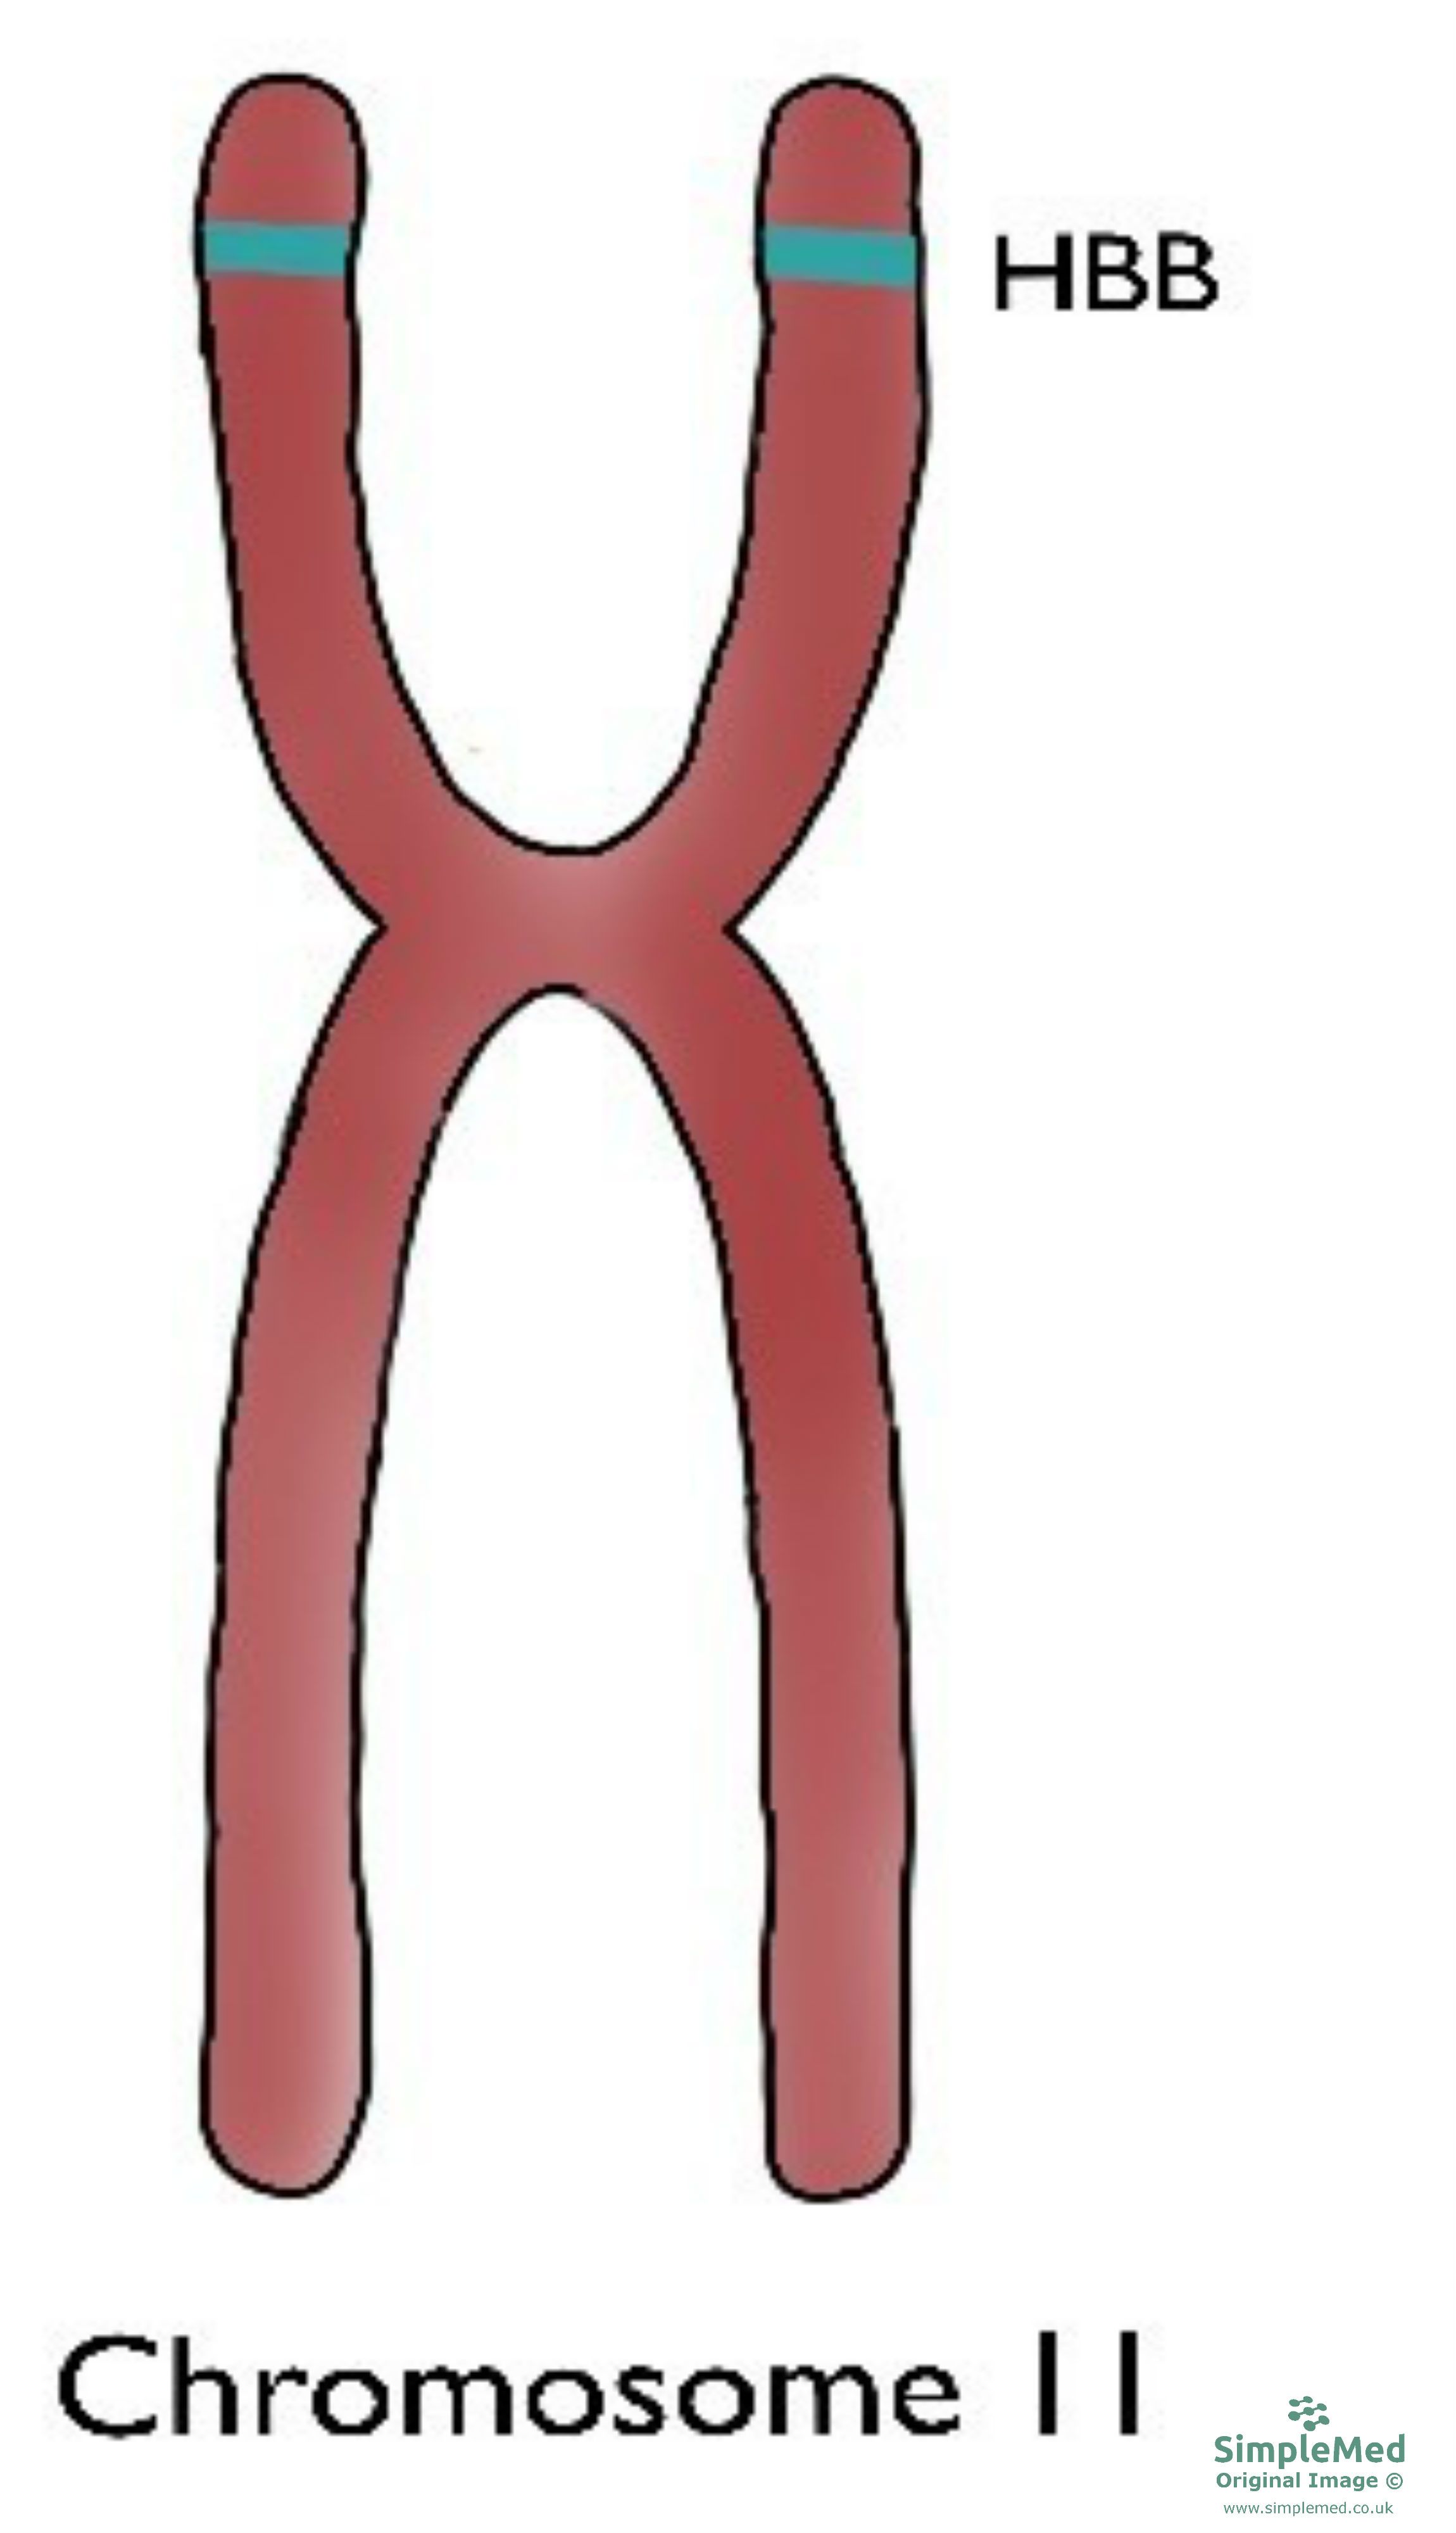
Figure 5. Chromosome 11 with the location of the β-globin chain gene shown
SimpleMed original by Dr. Keertana Anne
Beta thalassaemias are caused by mutations in the HBB gene (the β-globin gene) on chromosome 11. The body’s reduced or absent ability to make β chains leads to the underproduction of HbA, which is the most prominent haemoglobin variant in the body. This, similarly to α-thalassaemia, leads to microcytic anaemia.
There are 3 main types of β-thalassaemia: thalassaemia minor, thalassaemia intermedia and thalassaemia major.
- Thalassaemia Minor
- This is the form of β-thalassaemia where only one of the alleles in chromosome 11 has a mutation. This patient is a carrier (they have one faulty copy of the gene but do not have thalassaemia themselves), also called having the thalassaemia trait.
- The patient usually has no significant symptoms, but may have mild microcytic anaemia (anaemia with smaller than normal red cells).
- Patients usually need no treatment, and iron supplements do not correct their mild anaemia. Unnecessary transfusions may result in iron overload, leading to transfusion haemosiderosis (iron building up in the tissues), which damages the liver, heart and endocrine glands.
- Thalassaemia Intermedia
- In patients with beta thalassaemia intermedia, anaemia is present, and its symptoms range from mild to severe. These individuals are not transfusion dependent, meaning they do not need regular blood transfusions to stay well.
- Patients are clinically heterogeneous (how severe the disease is varies widely from person to person).
- Thalassaemia Major
- Also known as Cooley’s anaemia, this is the form where both alleles in chromosome 11 have mutations (the same mutation twice, called homozygous, or two different mutations, called compound heterozygous).
- Due to the massively reduced ability to produce HbA, the patient has severe microcytic and hypochromic anaemia and is transfusion and chelation dependent. This means regular blood transfusions, plus chelation (medicine that removes the excess iron that builds up from the transfusions).
- Patients whose anaemia is untreated or poorly treated may have abnormal skull bones. This is because the bone marrow expands as it makes extra red cells to keep up with haemolysis (the breakdown of red cells).
- Hepatosplenomegaly (an enlarged liver and spleen) is also seen in these patients, along with extramedullary haemopoiesis (making blood cells outside the bone marrow).
Sickle Cell Disease and Sickle Cell Anaemia
Sickle cell disease (SCD) is another inherited haemoglobinopathy. Normally red blood cells have a biconcave shape (a disc that is thinner in the middle) and are flexible, meaning they can easily move through blood vessels.
However, in sickle cell disease, when deoxygenated (having given up its oxygen) the defective haemoglobin S (HbS, the abnormal haemoglobin that causes sickling) polymerises (forms long, rigid strands). This deforms the cell, which loses its biconcave structure and becomes ‘sickle’ (or crescent moon) shaped. This irregular shape causes the sickle cells to become stuck in blood vessels, impairing the flow of blood to certain areas of the body. Furthermore, the cells are quite fragile so easily break down or are removed by the spleen, leading to a haemolytic anaemia.

Figure 6. Image showing the differences between normal red blood cells and sickle cells in blood vessels
SimpleMed original by Dr. Keertana Anne
Like thalassaemia, sickle cell disease is inherited in an autosomal recessive pattern. In sickle cell disease, abnormal haemoglobin S (HbS) is produced due to a mutation in the beta globin gene. Sickle cell anaemia (HbSS) is the most common and severe type of SCD. The person inherits the HbS gene from both parents (homozygous recessive), so they make no normal HbA, leading to marked sickling of red cells. Other types of SCD occur when one HbS gene is paired with a different abnormal gene, such as the gene for haemoglobin C (HbC, another abnormal haemoglobin variant) or for β-thalassaemia. Sickle cell trait (one HbS gene and one normal gene, so the person is a carrier and rarely has symptoms) is common across sub-Saharan Africa. In Nigeria, a pooled analysis of studies in children and adolescents found it in about 21% of people. The trait protects against severe malaria, which is why the gene is common there. Malaria is likely to be severe in people with sickle cell disease because the spleen works poorly, so they should take malaria prophylaxis (medicine to prevent malaria) when they travel to areas with malaria. People with sickle cell trait should take it too.
Signs and symptoms of sickle cell disease usually begin in early childhood and are caused by the sickle shape of RBC. The premature breakdown of the cells leads to anaemia, which can cause dyspnoea (breathlessness), fatigue and tachycardia (a fast heart rate). If the breakdown is severe enough, it also causes pre-hepatic jaundice (yellowing of the skin and eyes because red cells break down faster than the liver can clear the bilirubin). If sickle cells get stuck in blood vessels this can lead to vaso-occlusive crises (episodes of very painful blockage of small blood vessels). The blockage deprives tissues and organs of oxygen, so they become ischaemic. One of the most severe complications of sickle cell anaemia is acute chest syndrome (a sudden lung problem with chest pain, fever and breathlessness). It is also exquisitely painful.
Treatments are available to help manage the condition and alleviate symptoms of the disease. A bone marrow (stem cell) transplant can cure sickle cell disease. For some people aged 5 or over, gene therapy (exagamglogene autotemcel) may also cure it, but how well it works in the long term is not yet clear. NICE recommends the gene therapy within a managed access agreement (a controlled early-access arrangement while more evidence is collected). It is for people aged 5 or over who have sickle cell anaemia (HbSS) or HbS with β-thalassaemia. They must have had at least 2 vaso-occlusive crises a year for the previous 2 years, and a stem cell transplant must be suitable but no matched related donor available. Multiple infarcts (areas of tissue that die when their blood supply is blocked) damage the spleen, causing hyposplenism (reduced spleen function) and a higher risk of serious infection. Children are offered prophylactic antibiotics (penicillin from 3 months until 5 years of age), and people who stay at high risk of pneumococcal infection are offered antibiotics for life. Everyone with sickle cell disease should also have the full national immunisation schedule, including influenza vaccine every year. Despite advancing care, life expectancy is reduced: one UK study estimated a median survival (the age by which half of patients have died) of 67 years in people with sickle cell anaemia. Important causes of death include acute chest syndrome, infection (sepsis), stroke and pulmonary hypertension (raised blood pressure in the arteries of the lungs).
Edited by: Dr. Thomas Burnell and Dr. Ben Appleby
Reviewed by: Dr. Marcus Judge
- 11075
