

Next Lesson - Conditions of the Hand
Core
Want to revise the anatomy before you begin looking at conditions? Head to our articles on Bones of the Hand, Muscles of the Forearm and Bones of the Upper Limb for more information!
Scaphoid fractures are the most common carpal bone fracture, making up about 50-80% of them in published estimates. They are caused by a fall onto an outstretched hand (FOOSH) and are most common in young adults.
A scaphoid fracture presents with pain in the anatomical snuffbox (the small hollow on the back of the wrist at the base of the thumb) that is exacerbated by movement. Important complications are non-union (the broken ends fail to join together) and avascular necrosis (death of bone because its blood supply is lost). Both are linked to the scaphoid’s retrograde blood supply: blood enters the distal part of the bone and runs backwards to the proximal pole (the end nearest the forearm). A fracture that disrupts this blood supply can stop the bone healing.
The fracture may not show on the initial X-ray, so a suspected scaphoid fracture is treated as a fracture: the wrist is immobilised in a splint and the patient is seen by a specialist within 7 days (guidance from the British Society for Surgery of the Hand, BSSH). NICE advises considering MRI (a detailed scan of bone and soft tissue) as the first-line scan for a suspected scaphoid fracture, and BSSH guidance describes MRI within one week when the X-rays are inconclusive, depending on local policy. Repeat X-rays are arranged at about 1 week, as the fracture line can become easier to see once the body clears away bone along it (bone resorption). CT is used to assess a fracture seen on repeat imaging. Fractures that are not displaced are usually treated in a splint or cast for around 6 to 8 weeks so that the bone fragments can unite. Surgery is advised for fractures displaced by more than 2 mm, proximal pole fractures with any displacement, and fractures with an associated unstable wrist injury or displaced distal radius fracture.
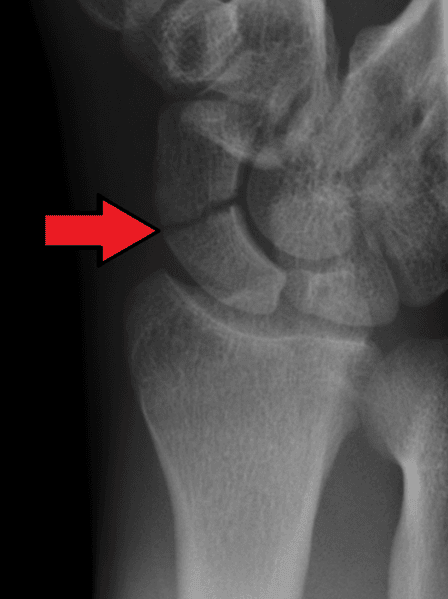
Image - An X-ray showing a scaphoid fracture. The red arrow shows the fracture line
Creative commons source by Gilo1969 [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
A Colles’ fracture is an extra-articular fracture (one that does not reach the wrist joint surface) of the distal radius. The broken end of the bone is angled (bent out of line) and impacted (driven into the bone above it), and it tilts towards the dorsal side, so the gap in the fracture opens towards the back of the hand. It is caused by a FOOSH, with a pronated forearm (palm facing down) and dorsiflexed wrist (bent backwards).
This condition presents with pain, a 'dinner fork' deformity and swelling. An associated fracture of the ulnar styloid process (the bony point at the end of the ulna on the little-finger side) is relatively common. Treatment may include manipulation (moving the bone back into position) followed by a plaster cast, or surgery such as K-wire fixation (thin metal pins that hold the bone in place).
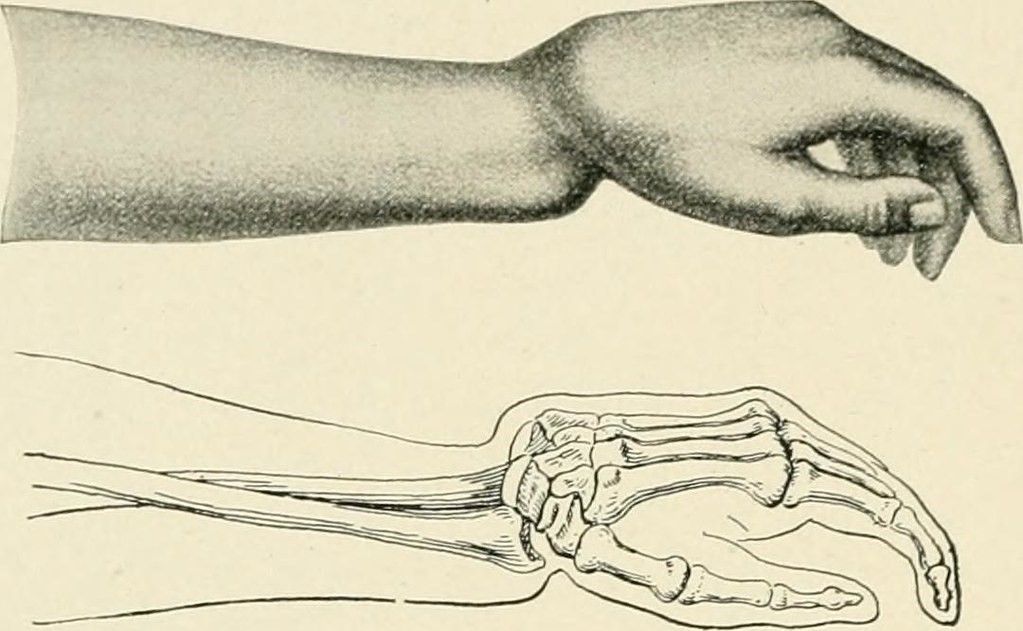
Image - A drawing of a Colles' fracture
Creative commons source by The Practice of Surgery by Mumford, James Gregory (1910) [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
A Smith’s fracture is an extra-articular fracture (one that does not reach the wrist joint surface) of the distal radius. The broken end of the bone is angled (bent out of line) and impacted (driven into the bone above it), and it tilts towards the palmar side, so the gap in the fracture opens towards the palm. It often follows a fall onto the palm of the hand, with the wrist bent back (extended). It can also be caused by a fall onto a flexed wrist (bent towards the palm) or a blow to the back of the wrist. This condition is relatively rare but usually occurs in young males or elderly females.
It presents with pain, a 'garden spade' deformity and swelling. Complications include malunion (the bone heals in the wrong position), which leaves a permanent garden spade deformity. Carpal tunnel syndrome can follow any distal radius fracture, and deformity after malunion is one recognised predisposing factor. Treatment may include casting, closed reduction (moving the bone back into place by hand, without an operation) or surgery.
Carpal tunnel syndrome is the compression of the median nerve as it passes through the carpal tunnel from the forearm into the hand. Risk factors for this condition include being female, obesity, pregnancy (a change in body fluid balance is thought to increase the volume in the tunnel), rheumatoid arthritis (an inflammatory arthritis that can inflame the tissues in the tunnel), hypothyroidism (an underactive thyroid gland), diabetes mellitus, and work involving forceful or repetitive hand movements or vibrating hand tools. The evidence linking carpal tunnel syndrome to computer work, such as typing, is not consistent. It presents with paraesthesia (pins and needles) in the palmar side of the thumb, index finger, middle finger and the thumb side of the ring finger (digits 1-3 and the lateral half of the 4th digit). Symptoms are often worse at night and can wake the person from sleep. There is weakness of abduction (moving the thumb away from the palm) and opposition (bringing the thumb across to touch the little finger) of the 1st digit, and the thenar muscles (the bulge at the base of the thumb) can waste in severe disease.
Sensation to the palm is spared as the palmar cutaneous branch (the skin branch to the palm) of the median nerve does not enter the carpal tunnel. Adduction of the 1st digit (moving the thumb towards the palm) is typically spared as it is supplied by the ulnar nerve.
Non-surgical treatment includes bracing or splinting and NSAIDs to reduce inflammation and manage pain, as well as avoiding or modifying harmful activities. If the symptoms are more severe, however, surgery followed by exercises to regain full movement is the usual treatment plan.

Diagram - The location where the median nerve is compressed in carpal tunnel syndrome
Creative commons source by Blausen.com staff (2014). "Medical gallery of Blausen Medical 2014". WikiJournal of Medicine 1 (2). DOI:10.15347/wjm/2014.010. ISSN 2002-4436. [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Ulnar Nerve Compression in Guyon’s Canal
Ulnar nerve compression in Guyon’s canal (also called ulnar tunnel syndrome) is caused by entrapment of the ulnar nerve as it passes superficial to the flexor retinaculum (the strong band across the front of the wrist), through a tunnel between the pisiform and the hook of hamate (two small carpal bones on the little-finger side of the wrist). The most common cause is a ganglion cyst (a fluid-filled swelling). It is also seen in cyclists, because pressure from the handlebars can compress the nerve, hence the name ‘Handlebar palsy’.
Symptoms depend on which part of the nerve is compressed within the canal. Sensory involvement causes paraesthesia (pins and needles) in the little finger and ulnar half of the ring finger. Motor involvement weakens the intrinsic hand muscles (the small muscles that lie wholly within the hand), including finger abduction and adduction and thumb adduction. The forearm flexor digitorum profundus (the deep muscle that bends the fingertips) is supplied proximal to Guyon’s canal and is spared when the damage is confined to the canal (an isolated lesion).
Assess the cause of compression, including repetitive pressure, a ganglion cyst or another structural lesion. Reduce pressure and aggravating activities; a short-term wrist splint may help. Persistent symptoms, progressive weakness or a structural cause may require specialist assessment and decompression (surgery to release the pressure on the nerve).
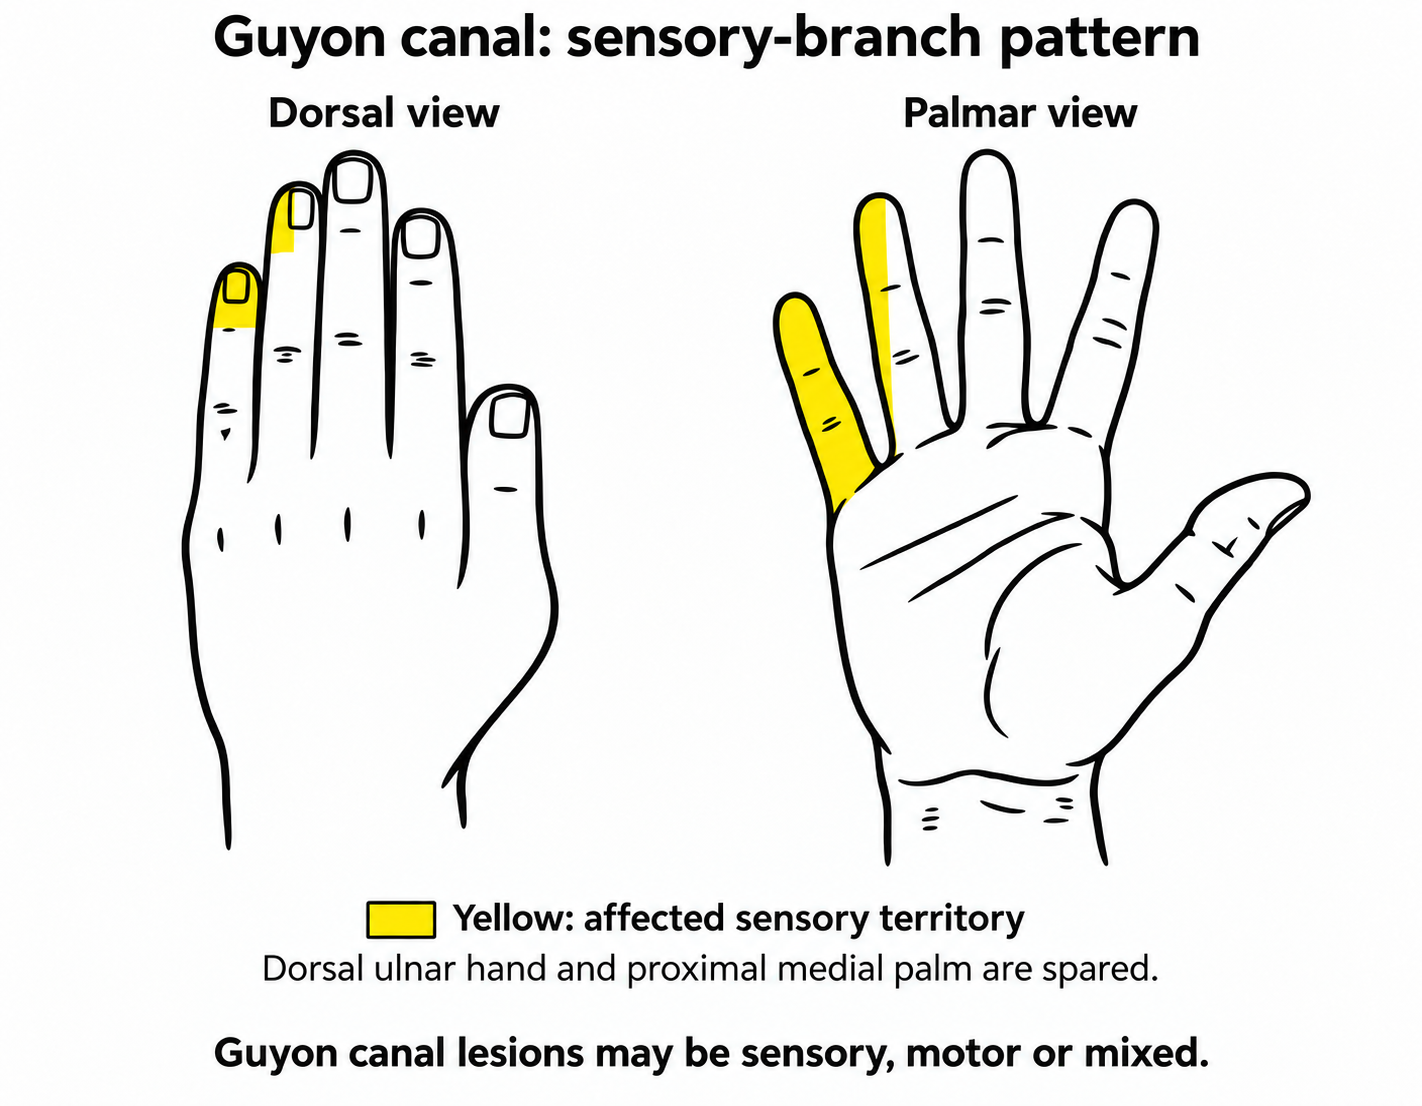
Diagram - A schematic sensory-branch pattern in an isolated Guyon canal lesion. Yellow marks the palmar little finger and ulnar half of the ring finger, including their distal dorsal fingertips. The dorsal ulnar hand and proximal medial palm are spared because their cutaneous branches leave the nerve before it enters the canal. Guyon canal lesions may be sensory, motor or mixed; the shaded pattern does not describe every lesion.
Diagram supplied for SimpleMed, 1 October 2026. Anatomy reference: ulnar nerve anatomy.
A penetrating wrist injury can damage the median nerve (a ‘low’ injury, at the wrist rather than higher up the arm). Weakness of the thenar muscles (the muscle bulge at the base of the thumb) impairs thumb opposition (bringing the thumb across to touch the little finger) and may produce an adducted thumb (held against the side of the hand, as in ape hand deformity) with flattening of the thenar eminence as wasting develops. The lateral two lumbricals (small muscles inside the hand that move the finger joints), supplying the index and middle fingers, may also be affected; their weakness is a separate finding from the thumb changes.
Sensation over the lateral palm is spared only if the palmar cutaneous branch (the skin branch to the palm) remains intact. It leaves the median nerve proximal to the carpal tunnel, but a penetrating wound may injure it separately. Sensory sparing cannot be assumed from the label “wrist injury”.
A penetrating wound with signs of median nerve injury needs prompt hand-surgery assessment for exploration and repair if the nerve has been cut. Splinting and hand therapy support recovery as advised by the treating team. Corticosteroid injection for carpal tunnel compression is a different treatment and does not repair a divided nerve.
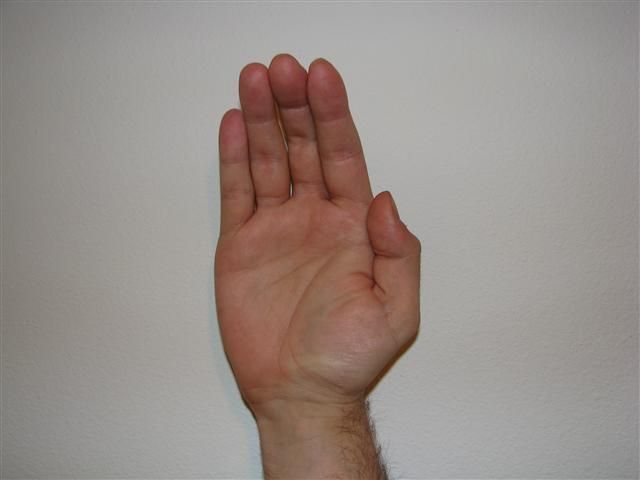
Image - A hand with ape hand deformity (the thumb is held against the side of the hand)
Creative commons source by Emily Barrett [CC BY 3.0]; resized for this article
A low injury to the ulnar nerve occurs due to a penetrating injury at the wrist. It presents with a ‘low ulnar claw’: hyperextension at the metacarpophalangeal joints (the knuckles), and flexion at the interphalangeal joints (the finger joints beyond the knuckles) of the 4th and 5th digits. There may also be paraesthesia in the little finger and ulnar half of the ring finger, including their palmar surfaces and distal dorsal skin.
Dorsal ulnar hand sensation may be spared if the dorsal cutaneous branch, which leaves the ulnar nerve in the forearm, remains intact. A penetrating wound can damage that branch separately. Palmar digital sensation in the little finger and ulnar half of the ring finger may be lost; the entire ulnar border is not necessarily spared.
A penetrating wrist wound with signs of ulnar nerve injury needs prompt hand-surgery assessment for exploration and repair if the nerve has been cut. Splinting and hand therapy may support recovery. Pressure modification is relevant to compression neuropathy (nerve damage caused by pressure); corticosteroid injection does not repair a traumatic nerve division.
A low ulnar lesion spares the forearm flexor digitorum profundus (the deep muscle that bends the fingertips). Its continued pull on the ring and little fingers can make clawing more pronounced than in a high lesion (at or above the elbow) that also weakens their deep flexor. This is the ulnar paradox: less nerve damage can give more obvious clawing. Its prominence varies with lesion completeness, and one small series of patients with unrepaired injuries found similar deficits above and below the elbow.
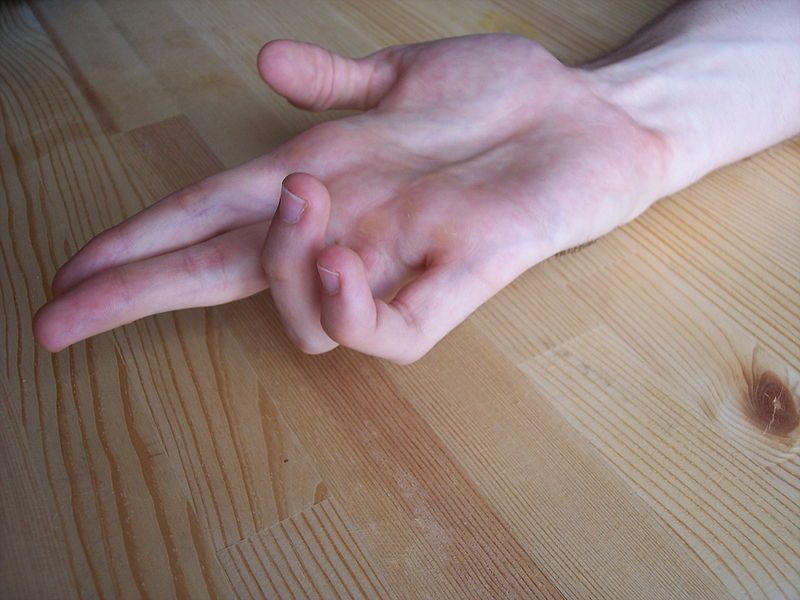
Image - A healthy hand imitating ulnar clawing. The photograph does not document a nerve lesion or establish whether a lesion is high or low.
Creative commons source by Mcstrother [CC BY 3.0]; resized for this article
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
Edited by: Dr. Maddie Swannack
- 7245



