

By Dr. Keertana Anne and Dr. Tom Bradley
Next Lesson - Full Blood Count
Core
Haematopoiesis is the production of mature blood cells (red blood cells (RBCs), platelets and the majority of white blood cells (WBCs)) from stem cells occurring in the bone marrow. In infants, it takes place throughout the skeleton. In adults it is more limited. It takes place mainly in the axial skeleton (the bones of the head and trunk), including the pelvis, sternum, skull, ribs and vertebrae, and in the upper ends of the femur (thigh bone) and humerus (upper arm bone).
This process begins from a single cell type: the multipotent haematopoietic stem cell (HPSC), sometimes called a haemocytoblast. Multipotent means able to develop into several different types of cell. Production of certain cell types is regulated by hormones and by other signalling proteins called cytokines.
- RBC production is stimulated by Erythropoietin (EPO).
- Platelet production is stimulated by Thrombopoietin.
- Granulocyte production (granulocytes are WBCs with granules in their cytoplasm: neutrophils, eosinophils and basophils) is stimulated by cytokines. G-CSF (granulocyte colony-stimulating factor) is the main stimulus for neutrophils, interleukin-5 (IL-5) for eosinophils and interleukin-3 (IL-3) for basophils.
- Lymphocyte production depends on interleukins (signalling proteins released by immune and other cells), especially interleukin-7 (IL-7).
The HPSCs differentiate into either common myeloid progenitor cells or common lymphoid progenitor cells, and from them all the other blood cells develop. Progenitors are early cells already committed to a limited range of cell types. Myeloid progenitors go on to form red cells, platelets and most white cells. Lymphoid progenitors go on to form lymphocytes.
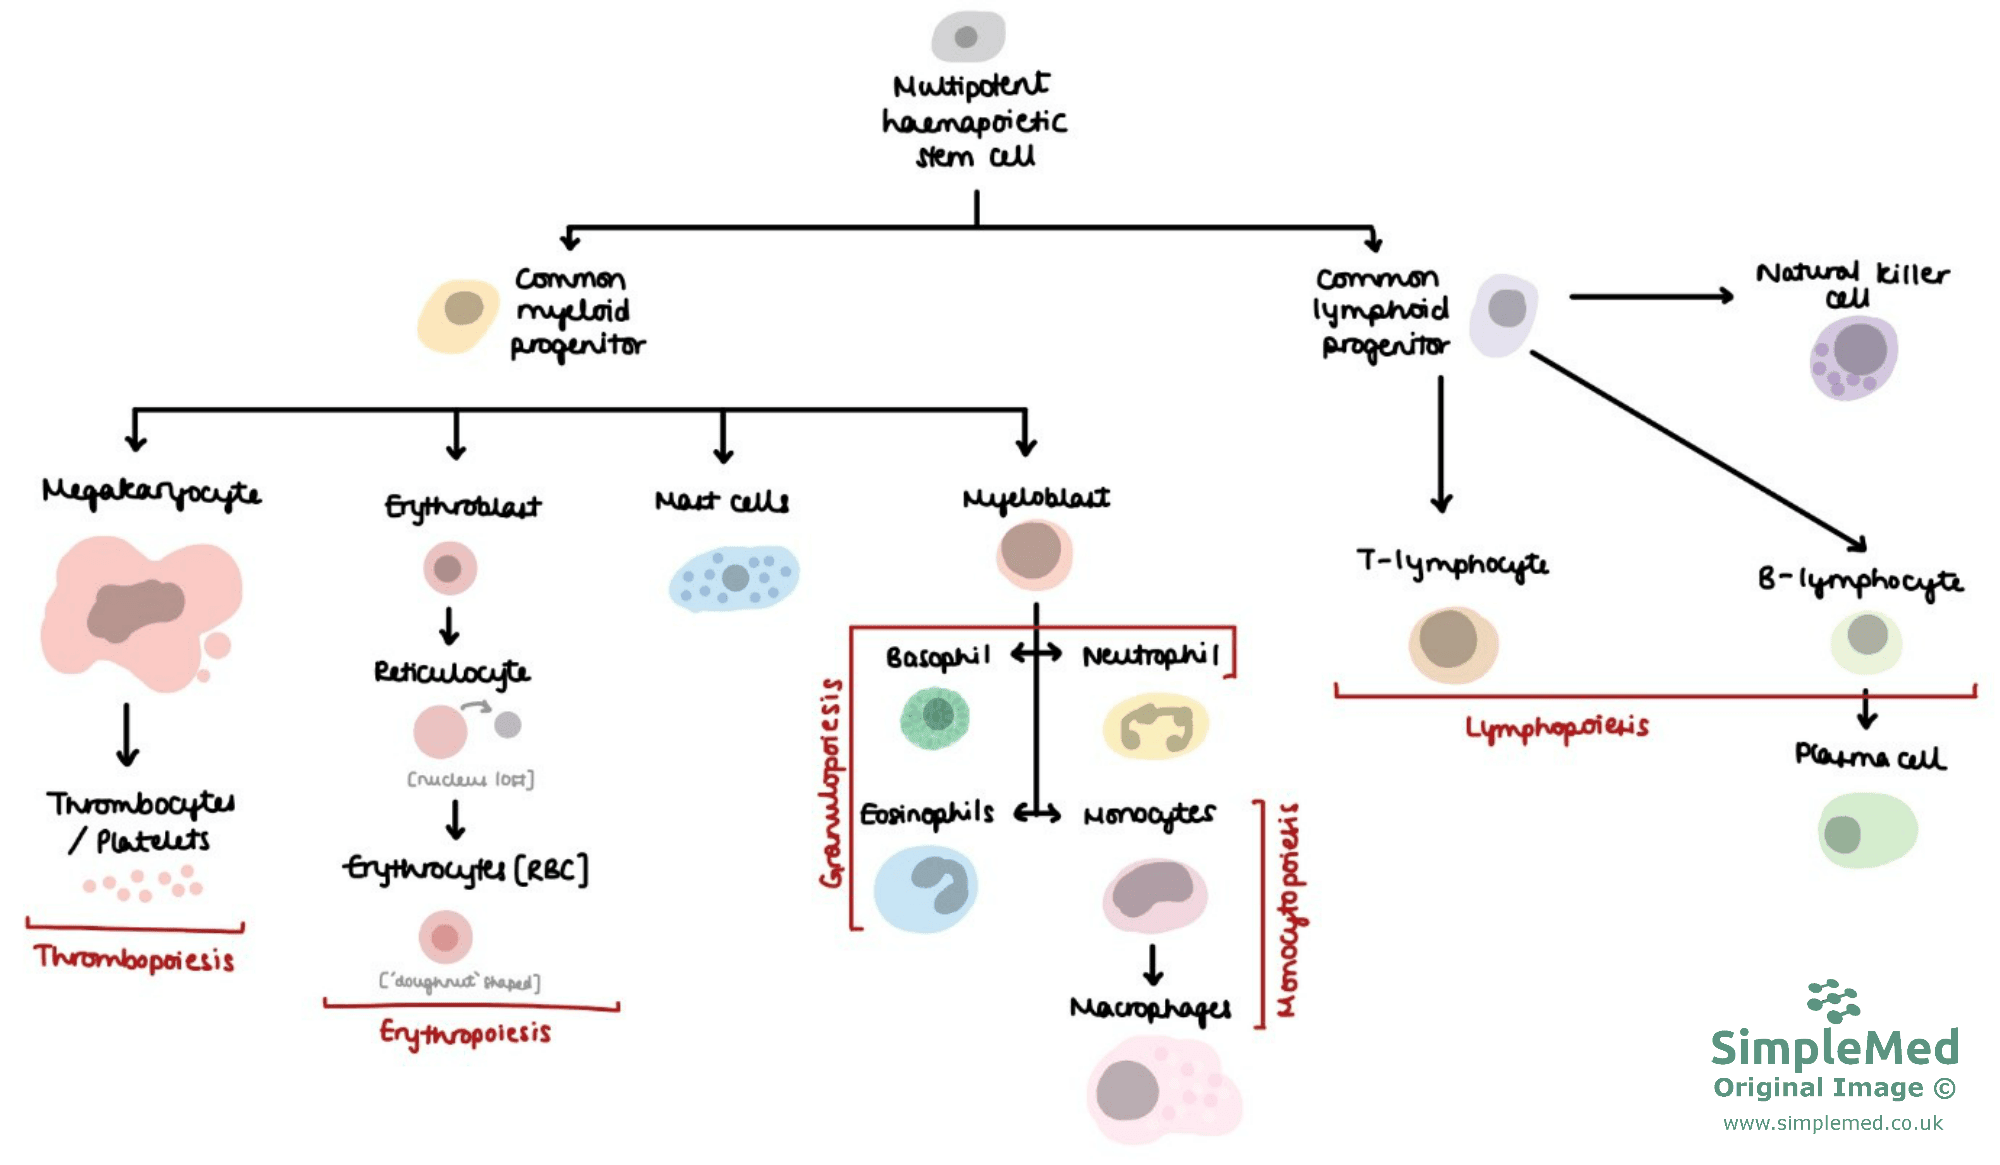
Diagram - Lineage of the Multipotent Haematopoietic Stem Cell
SimpleMed original by Dr. Keertana Anne
Erythropoiesis is the continuous process of erythrocyte production. Erythrocytes or red blood cells transport oxygen around the body.
Erythrocytes classically have a biconcave structure (a disc that is dented on both faces) with a diameter of 8µm. Their small size coupled with their shape helps them to squeeze through the small lumen of capillaries. Erythrocytes are enucleated cells (without a nucleus), which allows more space for haemoglobin to be contained within each erythrocyte (haemoglobin is the most abundant protein in the red blood cell).
See our article on biological membranes for more information on the structure of the erythrocyte cell membrane and the various diseases that can result from alterations in membrane structure.
Haemoglobin is a globular (rounded) protein with a tetramer (four-subunit) structure of two pairs of globin chains: two alpha chains and two beta chains (α2β2). Each chain has its own essential prosthetic haem group (a non-protein part permanently attached to the chain: an iron atom held at the centre of a ring-shaped molecule called protoporphyrin). One molecule of O2 binds to the haem group and causes movement of the iron into the plane of the ring, and a conformational change in the structure (a change in the three-dimensional shape of the protein).
Haemoglobin exists in a low affinity (T, tense) state, which binds oxygen weakly, or a high affinity (R, relaxed) state, which binds oxygen tightly. Deoxyhaemoglobin (haemoglobin without oxygen) is in the T state. When oxygen binds, the haemoglobin converts from the T state to the R state, which allows oxygen to bind much more easily. This especially favours oxygen loading in the lungs, where the partial pressure of oxygen (pO2) is high, and the release of oxygen at the tissues, where the pO2 is low. Each haemoglobin molecule can bind 4 O2 molecules.
Each red blood cell has a lifespan of 120 days therefore frequent erythropoiesis is required to replenish the supply of RBCs in the blood.
RBCs cannot undergo mitosis due to their lack of a nucleus; the process of erythropoiesis is as follows:
- Red blood cells are originally derived from common myeloid progenitor (CMP) cells which are committed to the path of erythropoiesis by transcription factors (proteins that switch genes on or off).
- Activation of transcription factors drives differentiation from CMP cells through a series of erythroid precursor stages (immature cells that lead to red blood cells), eventually forming reticulocytes (immature red blood cells that have lost their nucleus). During this process the nucleus and most organelles are pushed out of the cell. The hormone erythropoietin (EPO) is essential for survival and maturation of these erythroid precursors.
- Once reticulocytes are in the bloodstream, they mature over two days into erythrocytes by removing the remaining organelles.
The amount of production of erythrocytes can vary. More erythrocytes can be formed, in response to a shortage of oxygen in the blood. This response is driven by increased levels of EPO and is as follows:
- Interstitial peritubular cells in the kidney (cells in the connective tissue between the kidney tubules) detect hypoxia (reduced oxygen supply to the tissues). Hypoxia has several causes. Two examples are decreased oxygen carrying capacity in the blood (anaemic hypoxia) and a low oxygen level in the arterial blood (hypoxaemic hypoxia), for example from the lower oxygen pressure at high altitude.
- Increased production of EPO in the kidney (and, to a smaller extent, the liver).
- EPO stimulates maturation and release of red cells from the bone marrow, mainly by promoting survival and differentiation of erythroid progenitor cells.
- The number of red cells and the amount of haemoglobin rise, so more O2 is delivered to the tissues and the hypoxia is relieved.
B and T lymphocytes are cells of the lymphatic system (even though they can be found in the bloodstream).
B lymphocytes are a type of WBC that assist in the adaptive immune response of the body. They are able to recognise non-self-antigens and produce a large number of antigen specific antibodies. The development of B lymphocytes begins in the fetal bone marrow and liver. These then continue to mature in the bone marrow (unlike T-cells), where they remain until they are required during an immune response.
T lymphocytes are another type of WBC that have a key role in the body’s immune response. These also arise from the bone marrow but migrate to the thymus gland, where they develop and mature.
For a more detailed explanation of the action of lymphocytes, take a look at our article on adaptive immunity.
This is the process of platelet (or thrombocyte) formation. Platelets are key in the process of blood clotting. Platelets are shed from megakaryocytes (very large cells in the bone marrow, derived from CMP cells). The megakaryocyte extends long branching projections called proplatelets into the bone marrow blood vessels, and platelets break off from them. Budding from the cell membrane has also been described. Platelet production is driven by the hormone thrombopoietin (TPO).
Monocytes are phagocytic cells which circulate in the blood. They develop from monoblasts (immature monocyte precursor cells), which in turn develop from common myeloid progenitor via the granulocyte-monocyte progenitor (a cell that can form either monocytes or neutrophils). Blood monocytes circulate for about one day (classical monocytes) or about 4 to 7 days (the other two types, intermediate and non-classical monocytes) before leaving the blood circulation and becoming known as tissue macrophages, which have a phagocytic action.
The granulocytes are a family of white blood cells made up of basophils, neutrophils and eosinophils. Granulocytes are all white blood cells involved in microbial clearance. They all have large quantities of cytoplasmic granules within the cells. Each granule contains enzymes and other chemicals that damage microbes or drive inflammation. Like monocytes, granulocytes develop from the common myeloid progenitor, but they then pass through a different immature stage, the myeloblast.
- Neutrophils phagocytose (engulf) and destroy foreign organisms, using reactive oxygen species (highly reactive oxygen-containing molecules) and enzymes and proteins released from their granules.
- Eosinophils are effector cells (cells that carry out an immune response directly), which have actions against parasitic infections and are involved in many different immune responses. Pathologically, they take part in the process of allergic reactions.
- Basophils are circulating white blood cells that contain histamine (a chemical that causes swelling and itch in allergy), which they release as part of the immune response.
The spleen is one of the main organs in the reticuloendothelial system (RES, also called the mononuclear phagocyte system), the network of phagocytic cells (cells that engulf and destroy microbes and old cells) that also includes the liver and lymph nodes. The spleen’s function is to identify and act against foreign pathogens (using phagocytic cells). Blood is filtered as it passes through the spleen by the reticuloendothelial (RE) cells.
The spleen consists of red pulp which removes old red blood cells and metabolises haemoglobin; and white pulp which forms antibodies (formed of lymphoid tissue) and removes any bacteria or erythrocytes coated in antibodies. The spleen is particularly effective against encapsulated bacteria. White cells and plasma preferentially pass through the white pulp and red blood cells pass through the red pulp.
Another function of the spleen is limited blood pooling. Platelets and some red cells can be stored within the spleen and released into the circulation, although this reserve plays only a small part in humans during bleeding.
Splenomegaly - Enlargement of the Spleen
Splenomegaly usually occurs when the spleen has an increased workload, for example when it has to clear more abnormal red blood cells (red pulp) or respond to infection (white pulp). Other causes include:
- Back pressure due to portal hypertension (raised pressure in the portal vein, which carries blood from the gut to the liver, usually caused by liver disease).
- Infiltration by abnormal cells, such as malignant cells in the blood (e.g. leukaemia). Spread of other cancers to the spleen (metastases) is uncommon.
- Infections (e.g. malaria, schistosomiasis, a parasitic worm infection, and HIV).
- Accumulation of waste products of metabolism, for example in Gaucher disease (a rare inherited condition in which a missing enzyme lets a substance build up inside cells).
A healthy spleen should not be palpable (able to be felt through the abdominal wall) as it will lie under the ribs. An enlarged spleen is usually palpable in the left hypochondrium (the upper left part of the abdomen, under the lower ribs), and it will no longer be protected by the ribs. Therefore, the risk of rupture is increased. Splenic rupture is life-threatening as it will cause a large amount of internal bleeding due to the spleen's rich blood supply. If untreated this can cause haemodynamic shock (circulatory failure with dangerously low blood pressure) and death. Patients with splenomegaly are encouraged to avoid activities (such as contact sport) that may cause splenic rupture.
Hyposplenism - Reduction in the Function of the Spleen
There are multiple causes of hyposplenism including:
- Splenectomy (surgical removal of the spleen) - this may be required for splenic rupture from trauma, for cancer, or to treat diseases such as hereditary spherocytosis (an inherited condition in which red blood cells are round and fragile) or ITP (immune thrombocytopenia, in which the immune system destroys platelets).
- Diseases that damage the spleen or reduce its function (e.g. sickle cell disease and coeliac disease, an autoimmune reaction to gluten that damages the lining of the small intestine).
Hyposplenic or asplenic patients have an increased risk of developing sepsis, especially from encapsulated organisms (Neisseria meningitidis, Streptococcus pneumoniae & Haemophilus influenzae). This is as the white pulp is no longer present to remove the encapsulated bacteria allowing them to proliferate in the blood and manifest as sepsis. Hyposplenic patients therefore are usually given extra vaccinations (against pneumococcus, with boosters every five years; against meningococcus, groups A, C, W, Y and B; and against influenza every year), long-term prophylactic antibiotics (antibiotics taken to prevent infection, usually phenoxymethylpenicillin) and should carry a card notifying medical staff of their condition.
A typical blood film (a thin smear of blood on a glass slide, examined under a microscope) from a hyposplenic patient will contain RBCs with Howell-Jolly bodies (remnants of nuclear DNA still in the cytoplasm). These are a clue to damage to the spleen, as a normally functioning spleen would remove these defective cells as they pass through it.

Image - A Red Blood Cell film showing a Howell-Jolly Body
Creative commons source Isis325 [CC BY-SA 2.0 (https://creativecommons.org/licenses/by-sa/2.0)]
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Marcus Judge
- 13054
