

Next Lesson - Chronic Inflammation
Core
Inflammation is the rapid response of any vascularised tissue (living tissue with a blood supply) to injury. It delivers defensive materials, such as white blood cells and proteins, to the site of injury. The purpose of inflammation is to defend against infection and to clear damaged tissue.
The suffix '-itis' is used to indicate inflammation of an organ or tissue. For example, appendicitis is an inflammation of the appendix.
Acute inflammation is a type of inflammation which develops over the course of minutes, hours or days. If the inflammation lasts for weeks, months or years, it is chronic inflammation. Chronic inflammation is typically marked by three features: macrophages and lymphocytes (types of white blood cell) replacing neutrophils, ongoing tissue damage, and attempts at repair by fibrosis (scarring).
Clinical Signs of Inflammation
There are 5 clinical signs of inflammation, which are as follows:
- Rubor - Redness
- Calor - Heat
- Tumor - Swelling
- Dolor - Pain
- Functio laesa - Loss of function
- This loss of function, together with the pain, forces the injured person to rest the affected area, which helps to reduce further damage.
The five signs can be remembered with the memory aid - Raging Cows Trampled Down Fred, or Really Can't Tolerate Dead Languages.
Common causes of acute inflammation include:
- Microbial infections e.g. pyogenic (pus causing) organisms
- Hypersensitivity reactions (immune over-reactions, such as allergy), in their early phase
- Foreign bodies e.g. splinters, sutures, dirt
- Tissue necrosis
- Physical trauma
- Chemical agents or radiation
Acute inflammation is innate (present from birth) and stereotyped (happens the same way no matter the cause of the inflammation). It is controlled by chemical mediators (signalling chemicals that coordinate the response), such as histamine (explained below).
There are four stages of acute inflammation:
- Stimulus
- Vascular stage - the blood vessels widen and become leaky, the circulation then slows, and exudate forms at the site of inflammation
- Cellular stage - the migration of neutrophils to the site
- Resolution or persistence
Vascular Phase of Acute Inflammation
The vascular phase follows the stimulus. It occurs in the following steps:
- Vasoconstriction of arterioles (for a few seconds).
- Vasodilation of arterioles and then capillaries. This increases the blood flow to the affected area, resulting in heat and redness (calor and rubor).
- Increased permeability of local blood vessels allows proteins, cells and fluid to leave the blood vessel and enter the interstitial fluid (the fluid in the spaces between cells). This causes swelling (tumor). The fluid, protein and cells that leak out are called exudate.
- The increased concentration of red blood cells in small vessels and increased blood viscosity (thickness) leads to stasis (very slow or stopped blood flow) within the vessel.
The whole vascular phase is controlled by different chemical mediators. Within the first minutes of inflammation, mediators such as histamine are released from mast cells (cells in connective tissue), basophils (a type of white blood cell) and platelets. Histamine acts to dilate vasculature and increase vascular permeability. As the inflammatory response continues it is mediated by chemicals known as leukotrienes (chemicals made by white blood cells) and bradykinins. Bradykinin and prostaglandins (chemicals made by cells in the inflamed tissue) stimulate pain nerve endings, which produces pain (dolor).
Exudate is a collection of fluid, protein and cells that have left the blood vessel and formed in the interstitium (the tissue space between cells). It is protein-rich because the vessel wall has become more permeable, unlike a transudate (a protein-poor fluid that collects when the pressures across an intact vessel wall change, for example in heart failure). Exudate has several functions:
- To deliver fibrin, inflammatory mediators and immunoglobulins (antibodies) to the site of damage.
- Dilutes toxins to reduce the damage to tissues.
- Increases lymphatic drainage to deliver antigens and pathogens to lymph nodes to initiate an immune reaction.
The fluid flow across the vessel walls is controlled by a combination of two pressures. Hydrostatic pressure (the pressure exerted by a fluid) forces fluid out. Oncotic pressure (the osmotic pressure exerted by proteins) draws fluid in. Together these are known as Starling’s Forces. Starling’s Forces are a simplified model used for learning. More recent models place greater emphasis on the permeability of the endothelium (the cells lining the blood vessels). They also place emphasis on the glycocalyx (the sugar-rich coating on the inner surface of blood vessels).
- If there is increased hydrostatic pressure, there is an increased flow of fluid out of the vessel.
- If there is increased oncotic pressure within the vessel then there will be a reduction in the flow of fluid out of the vessel.
- If oncotic pressure rises in the interstitial fluid, it draws more fluid out of the capillary.

Diagram - The Starling forces and how they control the fluid movement into and out of the blood vessels
SimpleMed original by Benjamin Norris
Before exudate can form, the vasculature must become ‘leakier’ to allow proteins and fluid to cross more easily into the tissue space. Vascular leakage can occur due to the following mechanisms:
- Endothelial contraction forming gaps between cells.
- Mediated by histamine and leukotrienes.
- Cytoskeletal reorganisation forming gaps between cells.
- Mediated by cytokines (signalling proteins released by immune cells), such as interleukin-1 (IL-1) and TNF (tumour necrosis factor).
- Direct injury - e.g. toxic burns, chemicals.
- Leucocyte dependent injury - leucocytes (white blood cells) damage the endothelial cells, causing gaps to form between them.
- Reactive oxygen species (highly reactive oxygen molecules that damage cells) and enzymes from leucocytes.
- Increased transcytosis - production of channels within the endothelial cell to allow proteins and fluid to pass through the cell.
- Mediated by VEGF (vascular endothelial growth factor).
Exudate forms via the following sequence of events:
- Arteriolar dilation (but unchanged venous tone, meaning the veins stay at their normal degree of constriction) increases hydrostatic pressure in the capillaries.
- Increased vessel permeability by the above mechanisms causes movement of protein into the interstitium. This increases the oncotic pressure in the tissue and decreases the oncotic pressure in the vessels.
- The changes in oncotic and hydrostatic pressures result in a net flow of fluid out of the vessels, leading to tissue oedema.
- Pus (purulent exudate)
- Creamy yellow or white, as it is rich in neutrophils. This is typical of infections of pyogenic bacteria. A localised collection of pus is called an abscess.
- Haemorrhagic
- Red due to the presence of red blood cells. This indicates significant vascular damage.
- Serous
- Clear fluid with few leucocytes. This exudate is produced in blisters and burns.
- Fibrinous
- Significant deposition of fibrin. This can cause friction between serosal surfaces (the thin, smooth membranes lining the heart, lungs and abdominal organs). The friction can be heard as a rubbing sound on auscultation, e.g. in pericarditis (inflammation of the pericardium, the sac around the heart).
The Role of Neutrophils in Acute Inflammation
The primary type of white blood cell involved in inflammation is the neutrophil, which is a type of granulocyte (a white blood cell with visible granules inside it). Neutrophils are normally found in the blood and bone marrow, and their accumulation in tissues usually indicates the presence of a pathogenic organism or injury. They are short-lived. Their circulating half-life (the time for half of them to be cleared from the blood) is classically given as about 6 to 8 hours, although estimates vary and a more recent human study found about 19 hours. They cannot multiply, so the bone marrow must keep making new ones.

Diagram - The different granulocytes found in the body
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
To capture and kill a bacterium in the tissue space, a neutrophil must infiltrate the tissues. Neutrophils infiltrate the tissue and attach to bacteria through a series of overlapping steps:
- Chemotaxis - neutrophils are attracted towards the site of injury by chemical attractants.
- Activation - neutrophils switch to a higher metabolic level and change shape to help them move towards the chemical attractant.
- Margination - neutrophils move towards the endothelial wall (the lining of the vessel) where they then roll along it until they stick firmly to it (adhesion). Once firmly attached, they begin to crawl out of the vessel.
- Diapedesis - neutrophils relax the junctions between the endothelial cells so they can move across the endothelium. They also use collagenase (an enzyme that digests collagen) to break down the basement membrane (the thin supporting layer beneath the cells lining the vessel).
- Recognition and attachment - neutrophils recognise the bacterium via opsonins (explained below), which attach to the bacterium. Neutrophils then move towards and attach to the bacterium.
- Opsonins are substances which coat a target and make it easier for phagocytes (cells that engulf and destroy particles, such as neutrophils) to recognise it. Examples include immunoglobulin G (IgG) antibodies and complement proteins (a group of blood proteins that help immune cells), such as the complement fragment C3b.
- Phagocytosis - this is the process by which the neutrophils engulf and destroy the bacteria.
Chemotaxis is the directional movement towards a chemical attractant. Chemical attractants can come from outside the body (exogenous, such as bacterial products) or from within it (endogenous, such as complement fragments). See the summary table for examples. Within seconds of a chemical attractant binding to the cell surface receptors, the leucocyte undergoes a conformational change (its surface proteins change shape) to ‘activate’ it, which makes the cell more able to stick to microorganisms.
In most forms of acute inflammation neutrophils predominate in the inflammatory infiltrate (the cells that have moved into the inflamed tissue) during the first 6-24 hours. Neutrophils are replaced by monocytes in 24-48 hours.
Phagocytosis (cell eating) is the engulfment of solid particulate material by phagocytes, such as neutrophils. The process of phagocytosis is summarised in the diagram below.
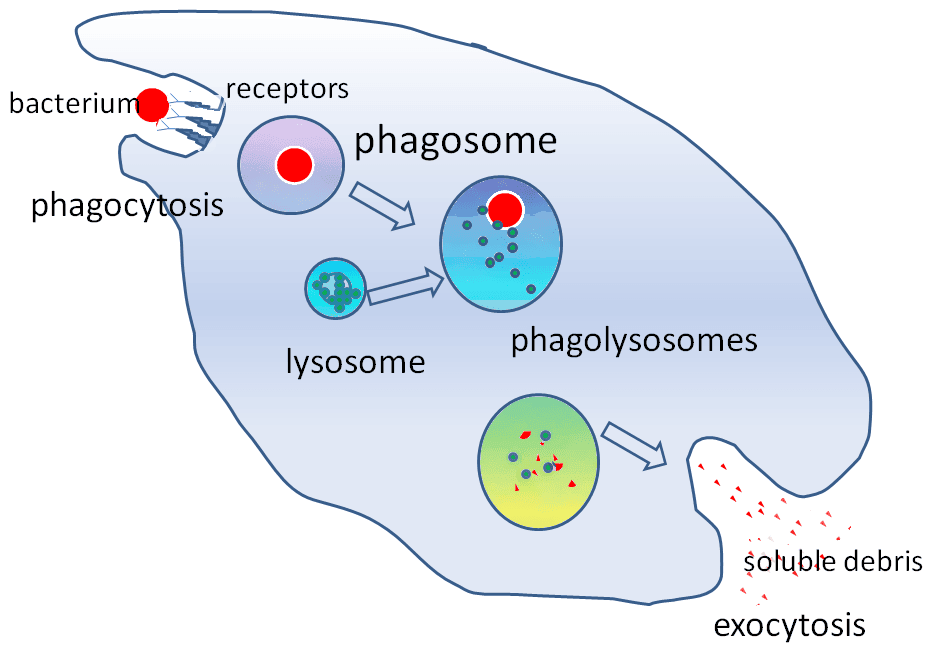
Diagram - The stages in phagocytosis
Creative commons source by Graham Colm [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The membrane of the phagocyte forms a crater around the particle to be eaten. The edges then come together, and the two plasma membranes meet and fuse. The particle is then in a vacuole (a membrane-bound sac) known as a phagosome. Lysosomes fuse with the phagosomes forming a phagolysosome. Chemicals are released that break down the engulfed particle. The debris is released by exocytosis.
Engulfed bacteria can be killed in one of two ways:
- O2 dependent mechanisms - release of oxygen-derived free radicals (highly reactive molecules that damage bacteria) into the phagosome. The mechanism of killing is known as the oxidative burst.
- O2 independent mechanisms - uses enzymes to kill bacteria inside the phagolysosome e.g. proteases (which break down proteins), lipases (fats), nucleases (nucleic acids) and lysozyme (an enzyme that helps break down bacteria).
A Summary of Chemical Mediators of Inflammation
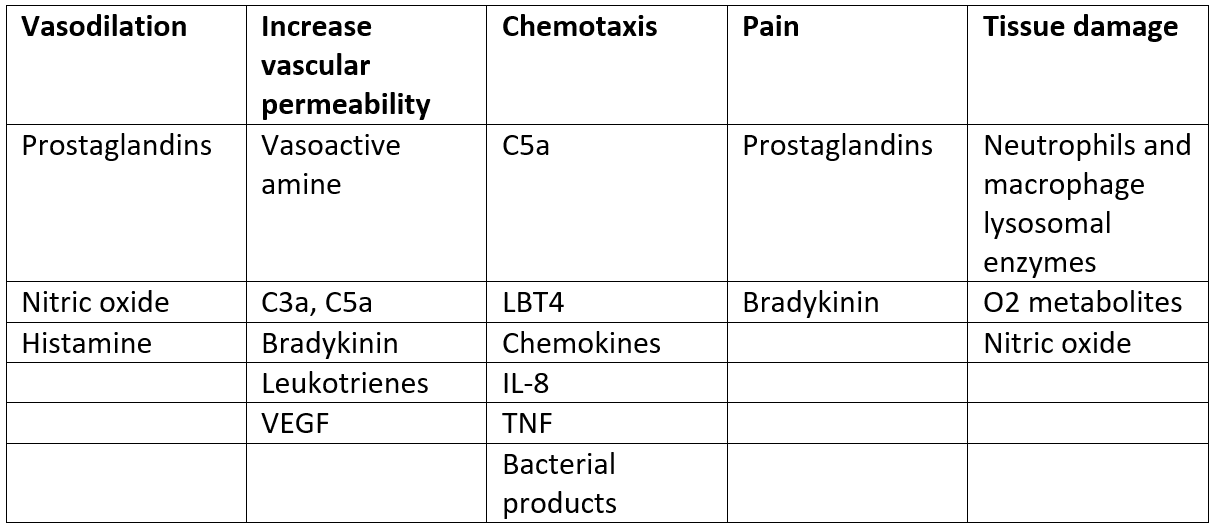
Table - The different chemical mediators in the body and the functions they have during inflammation
SimpleMed original by Benjamin Norris
Local Complications of Acute Inflammation
- Damage to normal tissue caused by substances produced by neutrophils and released in phagocytosis
- Obstruction of tubes, e.g. bile duct, intestine due to compression by surrounding swelling
- Compression of vital structures by swelling
- Loss of fluid as exudate, e.g. burns
- Pain and loss of function
Systemic Effects of Acute Inflammation
- Fever
- Pyrogenic substances (fever-causing chemicals), such as interleukin-1 (IL-1) and TNF, are released and stimulate the hypothalamus to raise the body temperature.
- Prostaglandins can also cause fever. Prostaglandin synthesis is inhibited by aspirin, so aspirin can be used to help reduce fevers in adults. It should not be given to children under 16 (unless specifically indicated) because of the risk of Reye’s syndrome (a very rare condition that can cause serious brain problems after a viral illness).
- Leucocytosis (a raised white blood cell count)
- IL-1 and TNF produce accelerated release of leucocytes from the bone marrow.
- Macrophages and T lymphocytes also stimulate the further release of other leucocytes.
- Acute phase response
- There is a change in the level of some plasma proteins (proteins in the blood). The liver changes its pattern of protein synthesis, driven by cytokines such as interleukin-6, IL-1 and TNF.
- The response causes decreased appetite, increased pulse rate, altered sleep patterns and changes in plasma concentration of acute phase proteins. Albumin and transferrin (the main iron-carrying protein in the blood) fall, while others rise, such as:
- C-reactive protein (CRP) (clinically useful in assessing the level of inflammation)
- Alpha-1 antitrypsin (a protein that protects tissues from enzymes released during inflammation)
- Haptoglobin (a protein that binds free haemoglobin)
- Fibrinogen
- Serum amyloid A protein (a protein that attracts immune cells and promotes inflammation)
- Haemodynamic shock
- A clinical syndrome of circulatory failure (haemodynamic means to do with blood flow and pressure), which can often be fatal.
- Can happen if bacterial products or inflammatory mediators spread around the body in the bloodstream and trigger a body-wide inflammatory response. When an infection causes this body-wide response and the response leads to life-threatening organ dysfunction, the condition is called sepsis.
- In septic shock (the form of shock that can complicate sepsis) there is a dramatic drop in blood pressure. This is caused by widespread vasodilation and increased vascular permeability in response to the bacterial products in the blood.
What Can Happen After Acute Inflammation?
There are several possibilities following acute inflammation, including persisting and becoming chronic inflammation with fibrous repair (repair with scar tissue). Acute inflammation can also continue alongside chronic inflammation in an established lesion (an area of damaged tissue). This can happen, for example, when irritation is severe and persistent or when acute episodes keep recurring. An abscess is a localised collection of pus: chronic inflammation may accompany a persistent abscess, but is not required for an abscess to form. The best scenario for acute inflammation is resolution.
With resolution the changes gradually reverse and vascular changes stop:
- Neutrophils no longer marginate
- Vessel permeability returns to normal
- Exudate drains to lymphatics
- Fibrin is degraded by plasmin (an enzyme that breaks down fibrin) and other proteases
- Neutrophils die and break up, and the remains are carried away or engulfed by macrophages
- Damaged tissue may be able to regenerate
Edited by: Dr. Bethany Turner
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 24566


