

Next Lesson - Asthma
Core
An embolus is material carried in the bloodstream from its site of origin to another site, where it may obstruct a vessel. A thrombus is a clot formed at its original site; a detached fragment travelling through the circulation is a thromboembolus.
A pulmonary embolism (PE) is therefore material that has moved from one part of the vasculature, through the right side of the heart, and lodges in the pulmonary arteries.
An embolus is usually made from a blood clot (thromboembolism), but can also be formed from tumour, air, fat, or amniotic fluid - note that the rest of this article will be focussing on thromboemboli. Pulmonary emboli are the third most common cause of vascular death, after myocardial infarction and stroke, and are the most common cause of preventable death in hospital patients.
Most pulmonary thromboemboli arise from a deep vein thrombosis (DVT) in the legs or pelvis. A detached clot travels through the right heart before lodging in the pulmonary arteries. The main factors that contribute to thrombus formation are stasis of blood flow, hypercoagulability of blood, and endothelial injury, also known as Virchow’s Triad. This means that the risk factors for a DVT (and therefore PE) are factors that will contribute to the causation of part of this triad:
- Pregnancy
- Prolonged immobilisation (e.g. post-operatively or on a long-haul flight)
- Previous venous thromboembolism
- Combined oral contraceptive pill
- Cancer
- Obesity
- Hormone replacement therapy
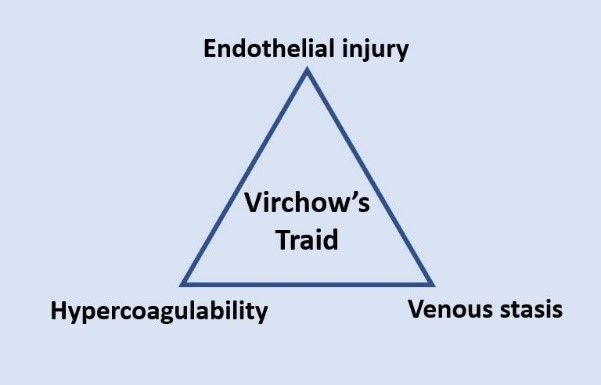
Diagram - Virchow's Triad: the relationship between endothelial injury, hypercoagulability, and venous stasis
Creative commons source by Dr.Vijaya chandar, MBBS [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The above risk factors can be divided into those that are;
- Temporary; for example, pregnancy, the pill, and immobilisation.
- Persistent while present; for example, active cancer. Risk factors can change over time and should be reassessed.
It is thought that 50% of patients with a PE have a temporary risk factor and that 25% have a permanent, but that 25% don’t have any risk factors at all. It is important to realise that prevention of a PE, for example through the use of compression stockings on a long haul flight, is extremely important, and more easily implemented than treatment.
Pulmonary emboli cause mechanical obstruction of pulmonary arteries. Obstruction and mediator-driven pulmonary vasoconstriction, including effects of serotonin and thromboxane, increase pulmonary vascular resistance and right ventricular afterload. The right ventricle may dilate and fail, reducing blood flow through the lungs and filling of the left ventricle. Cardiac output and systemic blood pressure can then fall. Acute right ventricular failure is the principal lethal mechanism in severe PE.
Ventilated lung supplied by an obstructed artery becomes poorly perfused, increasing alveolar dead space. Redistribution of blood to other lung regions can produce low ventilation-perfusion ratios, contributing to hypoxaemia. Reduced cardiac output and atelectasis can also contribute. Hyperventilation commonly lowers arterial CO2, so PE may cause type 1 respiratory failure: low arterial O2 with normal or low CO2. Normal oxygen saturation does not exclude PE.
The part of the lung that is poorly perfused may undergo infarction, however, this is rare as the bronchial arteries will normally supply the tissue with adequate oxygen. If this does happen then the patient may present with haemoptysis and pleuritic chest pain.
In a patient with a patent foramen ovale, PE-related elevation of right atrial pressure can permit right-to-left shunting. A venous embolus may then cross into the arterial circulation, causing a paradoxical embolism, including stroke. The risk depends on the presence of a shunt; PE does not make every patent foramen ovale shunt right to left.
Symptoms of a PE include:
- Shortness of breath
- Pleuritic chest pain
- Cough
- Substernal chest pain
- Fever
- Haemoptysis
- Syncope
- Unilateral leg pain (DVT)
Signs of a PE include:
- Dyspnoea
- Tachycardia
- Low BP
- Raised jugular venous pressure
- Pleural rub in cases of pulmonary infarction
- Evidence of DVT, e.g. erythema, increased temperature and tenderness on palpation of the leg
The main differential diagnoses for a pulmonary embolism are pneumothorax, pneumonia, musculoskeletal chest pain, and myocardial infarction.
Patients with a suspected PE should undergo a series of investigations:
- Arterial Blood Gas (ABG) - may show respiratory alkalosis with hyperventilation, but findings are variable and a normal result does not exclude PE.
- Chest X-ray - to exclude differentials such as pneumothorax or pleural effusion.
- ECG:
- The most common sign of a PE on an ECG is sinus tachycardia.
- This could show an S1Q3T3 pattern; a large S wave in lead I, and a Q wave with an inverted T wave in lead III, which are all classic signs of right heart strain. This is a common textbook presentation but is not actually common in clinical practice.
- There could also be no signs on ECG - a normal ECG cannot rule out a PE.
- D-dimers:
- Measured in a blood test, d-dimer is a fibrin degradation product released into the blood when a thrombus is degraded by fibrinolysis.
- In a patient with a low likelihood of PE, a normal d-dimer can rule a PE out. However, if the patient has a high probability of PE a normal D-dimer should not be used to rule a PE out, as its negative predictive value is too low to use.
- This means that if a PE is likely, a D-dimer is not a useful investigation, because it cannot be used to rule in or out a PE, and so a CT pulmonary angiography (CTPA) should be done immediately.
- A Wells Score should be calculated for any patient where a PE is a possible cause of symptoms. The components of a Wells Score are:
- Clinical Signs or Symptoms of a DVT - 3 points
- PE is the most likely clinical diagnosis - 3 points
- Heart rate >100 bpm - 1.5 points
- The patient has been immobilised for more than 3 days or has had surgery in the past 4 weeks - 1.5 points
- Previous PE or DVT - 1.5 points
- Haemoptysis - 1 point
- Malignancy with treatment within the past 6 months or active palliative malignancy -1 point
- A score of >4 indicates a PE is likely
- A score of <= 4 indicates a PE is unlikely
- Imaging:
- CT Pulmonary Angiogram (CTPA)
- Ventilation Perfusion Lung Scintigraphy (VQ scan)
Pulmonary emboli can be imaged through the use of a CT pulmonary angiogram or ventilation-perfusion lung scintigraphy (usually if CTPA is not available or a patient is pregnant). These should be used in conjunction with a convincing history.
A patient with a suspected PE should be given O2 if they are hypoxic, and anticoagulation (for example heparin or a direct oral anticoagulant (DOAC)) where clinically appropriate, which reduces mortality by preventing the thrombus from propagating in the pulmonary artery and allowing the body’s fibrinolytic system to lyse the thrombus. It reduces the frequency of further embolism but doesn’t dissolve the clot already present.
Patients with a high risk of PE may also require haemodynamic support, respiratory support, and thrombolytic therapy, with catheter-directed techniques reserved for selected cases in specialist settings. Procedures used to remove the embolus include percutaneous catheter directed thrombectomy, or surgical pulmonary embolectomy.
After the initial course of anticoagulation for PE, reassess the benefits and risks of continuing, stopping or changing treatment with the patient.
- For a provoked PE, consider stopping after the recommended initial course if the provoking factor has resolved and the clinical course has been uncomplicated.
- For an unprovoked PE or an ongoing risk factor, consider longer-term treatment according to the balance between recurrent VTE and bleeding risk, taking the patient's preferences into account. Continuing indefinitely is not automatic.
Edited by: Dr. Marcus Judge
Reviewed by: Dr. Maddie Swannack
- 6469

