

Next Lesson - Protein and Amino Acid Metabolism
Core
Lipids are a structurally diverse group of molecules which are hydrophobic (they repel water) and contain carbon, hydrogen and oxygen. Some lipids, such as phospholipids, also contain nitrogen and phosphorus.
Lipids can be grouped in several ways. This article uses a simple grouping of 3 classes (the international LIPID MAPS system uses 8 categories):
- Fatty acid derivatives - fatty acids, triacylglycerol and phospholipids
- Hydroxy-methyl-glutaric acid derivatives - ketone bodies and cholesterol, which are both made from HMG CoA (3-hydroxy-3-methylglutaryl coenzyme A)
- Vitamins - fat-soluble vitamins A, D, E and K
The main storage form of lipid in the body is in the adipose tissue (body fat). Adipose stores energy as triacylglycerol (TAG, also known as triglycerides). A TAG is made up of one hydrophilic (water-attracting) molecule of glycerol attached to three hydrophobic fatty acid chains.
As lipids are hydrophobic, it is not feasible to transport them freely in the blood. This means that free fatty acids are transported attached to albumin, and TAGs being produced in the liver are transported in lipoproteins. This allows the TAGs to be targeted to the peripheral tissues that need them. Lipid transport is explained later in more detail.
- Phospholipids - two non-polar fatty acid chains (chains that do not mix with water) bound to glycerol with a phosphate group. A phospholipid is very similar in structure to a TAG, but with a phosphate group replacing one of the fatty acids. Phospholipids form bilayers (used to form cell membranes), micelles (tiny balls with the water-repelling tails pointing inwards) and liposomes (hollow spheres made from a phospholipid bilayer).
- Cholesterol - made in the liver and also taken in from the diet. Cholesterol is a precursor (starting material) for steroid hormones and bile acids.
- Lipoproteins - particles used to transport lipid in the bloodstream. Each has a core of triglyceride and cholesterol ester (cholesterol with a fatty acid attached), surrounded by a surface layer of phospholipids, free cholesterol and proteins called apolipoproteins. There are five types of lipoprotein, with different functions, as shown in the table below.
- Apolipoproteins - the proteins on the surface of lipoproteins. Some have a structural (packaging) role. Others have a functional role, either as co-factors (helpers that switch enzymes on) or as ligands (molecules that bind to receptors).
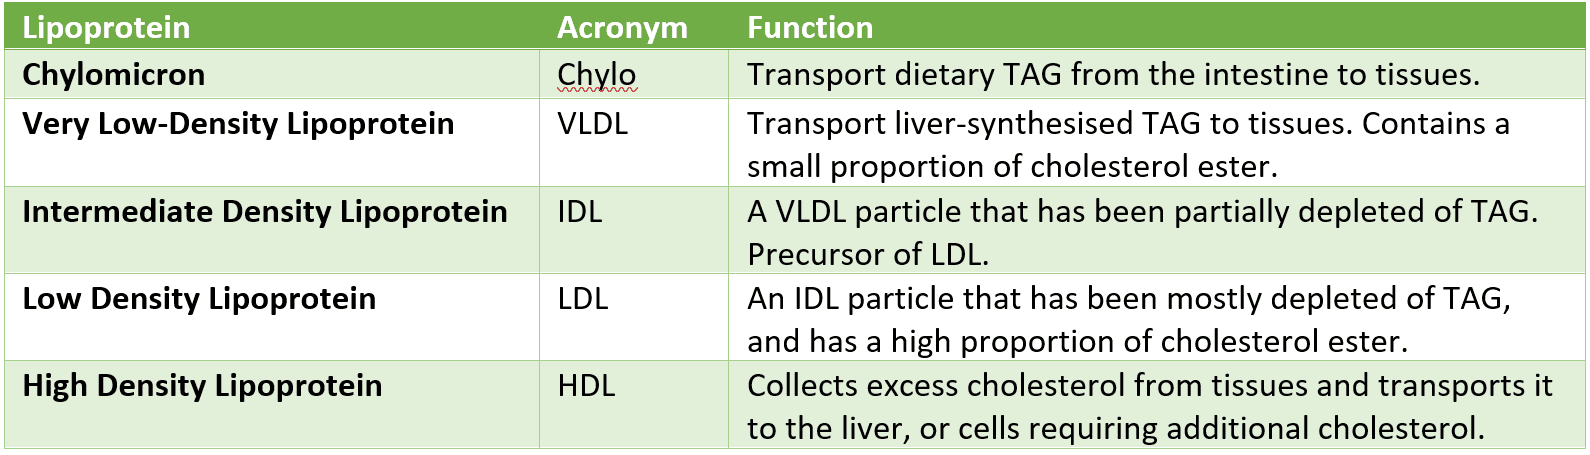
Table - The different types of lipoproteins found in the body
SimpleMed original by Dr. Maddie Swannack
Fatty acids have the general structure of CH3(CH2)nCOOH. The carbon chain is commonly between 14 and 18 carbons long. It can be saturated (no double bonds in the carbon chain) or unsaturated (one or more double bonds). Long-chain fatty acids are amphipathic (a mix of hydrophobic and hydrophilic parts). They are transported into the mitochondria by the carnitine shuttle. This system carries long-chain fatty acyl groups (fatty acid chains attached to coenzyme A) across the double membrane of the mitochondria. The fatty acyl group is transferred between CoA (coenzyme A) and carnitine (an ammonium compound), which allows it to be carried across the two membranes.
Once inside the mitochondria, the fatty acid is broken down (catabolised) through a process called beta oxidation. With each cycle of beta oxidation, a two-carbon molecule is liberated from the fatty acid (making the fatty acid 2C shorter each time until it has been fully degraded). This molecule goes on to become acetyl CoA, which is used in the Krebs Cycle to generate energy.
During the process of beta oxidation, NADH and FADH2 (reduced flavin adenine dinucleotide) are made. These molecules carry high-energy electrons, which can be used to produce energy in the electron transport chain.
Fatty acids are more reduced than carbohydrates, meaning fatty acids release more molecules of ATP per carbon during respiration than carbohydrates.
The brain mainly uses glucose. Fatty acids do enter the brain from the blood, but breaking them down is not a major source of energy there. To get in, they cross the blood-brain barrier (the tightly sealed lining of the brain's small blood vessels). During periods of low glucose availability, the brain can use ketone bodies as an energy source instead. Red blood cells cannot break down fatty acids for energy, because they have no mitochondria. They rely on glycolysis instead.
Glycerol is a component of TAGs. This diagram shows how NADH is produced from glycerol to be used for ATP production in the electron transport chain. The products of glycerol breakdown (metabolites) are used to make intermediate molecules for glycolysis and for making new triacylglycerol.

Diagram - The metabolic pathway of glycerol to be used in glycolysis
SimpleMed original by Dr. Maddie Swannack
Ketone bodies are water soluble molecules produced by the liver. There are three types: acetoacetate, beta-hydroxybutyrate, and acetone.
Ketone bodies can act as an alternative substrate (fuel) in starvation, when glucose availability is reduced. This is physiological ketosis, a normal rise in ketone bodies in the blood. In diabetic ketoacidosis (pathological ketosis), a lack of insulin makes harmful amounts of ketones build up in the blood. Diabetic ketoacidosis usually affects people with type 1 diabetes mellitus. It can also happen in people with type 2 diabetes, including some who take SGLT2 inhibitors (diabetes medicines that make the kidneys pass glucose out in the urine). In these people the blood glucose may be only moderately raised, which can delay diagnosis. Ketone bodies can cross the blood-brain barrier, so the brain can use them as an energy source when glucose is in short supply.
Lipids eaten in the diet are broken down (hydrolysed) in the small intestine by pancreatic lipases (enzymes from the pancreas that digest fat). The products are absorbed into the cells lining the intestine, where they are rebuilt into TAGs and packaged into chylomicrons (large lipoprotein particles that carry dietary fat). The chylomicrons leave these cells and enter the lacteals (lymphatic vessels in the intestinal wall that carry absorbed fat). Most other digested nutrients enter the blood instead. The TAGs in chylomicrons can be stored in adipose tissue if there is plenty of glucose (i.e. they are not needed as a fuel source immediately).
This diagram shows the fatty acid cycle as it occurs in adipose tissue. It illustrates how, with a constant supply of glucose, the stored fatty acids are not static (they are continually cycling).
However, if the supply of glucose is too low, less glycerol-3-phosphate is available. Glycerol-3-phosphate is the glycerol backbone with a phosphate group, normally made from glucose, and fatty acids attach to it when TAG is rebuilt. Reaction 3 in the diagram (esterification, which joins fatty acids to glycerol-3-phosphate to make TAG) therefore slows down, although some re-esterification continues during fasting. More of the fatty acids and glycerol then leave the cycle and are released into the blood to be used as an alternative fuel source.
This release of fatty acids and glycerol is under hormonal control. The best understood effects are the opposing actions of insulin, which holds fat breakdown back, and the catecholamines (adrenaline and noradrenaline), which stimulate it. When glucose levels are low, insulin falls and fat breakdown speeds up. Lipases (enzymes that digest fat), including hormone-sensitive lipase, then break down the triglyceride to provide an alternative fuel source. Glucagon (released when glucose levels are low) is sometimes said to trigger fat breakdown. However, in one small study of seven healthy men, a raised glucagon level did not increase fat breakdown in abdominal fat, so its direct role in people is uncertain.

Diagram - The metabolic pathway of the storage of TAGs in adipose tissue. Glucose is taken up by adipocytes and turned into triglycerides, which can be released as fatty acids and glycerol when blood glucose is low
SimpleMed original by Dr. Maddie Swannack
This diagram shows the formation and metabolism of chylomicrons. Lipid moves from the small intestine to the lymph via lacteals in the villi (the finger-like folds of the gut lining). It is then emptied into the blood via the thoracic duct (the main lymphatic vessel, which drains most of the body). The duct usually empties at the junction of the left subclavian vein (under the collarbone) and the left internal jugular vein (in the neck). At the walls of capillaries, chylomicrons are partially metabolised by lipoprotein lipase, supplying lipid to cells that need it. Once much of its triglyceride has been removed, the chylomicron becomes a chylomicron remnant. This smaller particle is rich in cholesterol ester. It travels to the liver, which takes it up and finishes breaking it down.

Diagram - The pathway of chylomicrons from the small intestine, to the lymph, to the blood in order to release fatty acids and glycerol to tissues. When the chylomicron becomes depleted, it becomes a remnant and travels to the liver for metabolism
SimpleMed original by Dr. Maddie Swannack
This diagram shows how cholesterol and TAG produced in the liver travel around the body to supply muscles and fat stores.
The triglycerides are released by the liver contained within a Very Low-Density Lipoprotein (VLDL), which contains predominantly lipid, and a small proportion of cholesterol ester. As the lipoprotein is metabolised by lipoprotein lipase, its TAG content is depleted, and the particle becomes an Intermediate Density Lipoprotein (IDL). Once the TAGs have been almost completely removed, and the predominant molecule is cholesterol ester, the lipoprotein is now called a Low-Density Lipoprotein (LDL).
LDL enters hepatocytes or other cells that need cholesterol. These cells have receptors that bind ApoB-100 (apolipoprotein B-100, the main protein on the surface of LDL). The LDL is taken into the cell by endocytosis and then digested by lysosomes.
LDL is often referred to as 'bad cholesterol'. This is because it has a long half-life, meaning it stays around long enough to be trapped in the artery wall, where it can become oxidised (chemically damaged). Oxidised LDL is engulfed (phagocytosed) by macrophages, which fill with fat and become foam cells. Foam cells contribute to atherosclerosis. A low level of LDL cholesterol is therefore good: fewer foam cells form, so the risk of atherosclerosis is lower.

Diagram - The pathway of lipoproteins in the body. Lipoproteins deliver TAGs to peripheral tissues using the enzyme lipoprotein lipase. The diagram also shows how LDL can become oxidised and contribute to the formation of atherosclerotic plaques
SimpleMed original by Dr. Maddie Swannack
This diagram shows how an empty HDL particle is released from the liver and intestine and receives excess cholesterol from body cells. The HDL particle then carries this cholesterol to the liver, either directly or by passing it to VLDL and LDL (using cholesteryl ester transfer protein, CETP). HDL can also deliver cholesterol directly to steroidogenic cells (cells that make steroid hormones). The liver can use the cholesterol to make bile salts, and steroidogenic cells can use it to make steroid hormones. HDL is also known as 'good cholesterol' because it removes excess cholesterol from peripheral tissues. A higher HDL level is linked to a lower risk of atherosclerosis. However, in large trials, medicines that raised HDL cholesterol (extended-release niacin and dalcetrapib) did not reduce cardiovascular events. HDL is therefore a marker of lower risk, not a proven treatment target.

Diagram - The pathway of HDL particles through the body to collect excess cholesterol from body cells and deliver it to the liver and to cells that need it
SimpleMed original by Dr. Maddie Swannack
This article covers three diseases relating to lipid metabolism. They are not a complete list, but they are examples of how impaired lipid metabolism can lead to disease. For more information see the article on Atherosclerosis.
Hyperlipoproteinaemias are a group of diseases that present with high levels of one or more class of lipoprotein. The cause is overproduction (making too much lipoprotein) or under-removal (not clearing lipoprotein from the blood well enough). There are six types in the Fredrickson classification, which groups them by which lipoproteins are raised. A type describes this pattern, not one fault. The same pattern can have inherited causes or secondary causes, such as other diseases. Here are three examples:
- I - chylomicrons present in the plasma even when fasting. Causes include a defective lipoprotein lipase, or a fault in a protein that the enzyme needs, such as ApoC-II (apolipoprotein C-II, the co-factor that switches lipoprotein lipase on).
- IIa - high levels of LDL in the blood. A defective LDL receptor is the classic cause, as in familial hypercholesterolaemia (FH), which is a group of inherited genetic defects. This condition predisposes to atherosclerosis, because more LDL is trapped and oxidised in the artery wall.
- III - raised IDL and chylomicron remnants, usually due to a defective ApoE (apolipoprotein E, a protein on the surface of the particles). The remnants cannot be cleared properly from the blood.
Treatment depends on the type. For raised LDL (such as type IIa), it includes improving diet, increasing exercise and taking statins. Statins block an enzyme used in cholesterol production, called HMG CoA reductase (3-hydroxy-3-methylglutaryl coenzyme A reductase), so less cholesterol is made. If a statin is not enough or cannot be taken, ezetimibe (which reduces the absorption of cholesterol from the gut) can be added or used instead. Bile salt sequestrants keep bile salts in the intestine, so the liver uses more cholesterol from the blood to make new bile salts. NICE advises against offering them to prevent cardiovascular disease. In familial hypercholesterolaemia they are used only on specialist advice. In type I, the main treatment is a very low-fat diet, because ordinary lipid-lowering medicines work poorly. Type III is treated with a diet low in fat plus a statin, a fibrate (another type of lipid-lowering medicine) or both.
Hypercholesterolaemia means a high level of cholesterol in the blood. It overlaps with the hyperlipoproteinaemias above: for example, familial hypercholesterolaemia (FH, an inherited condition in which cholesterol is high from birth) is most often seen as type IIa. High cholesterol does not usually cause symptoms. Very high levels can cause visible signs. Xanthelasma appears as yellow patches on the eyelids. Tendon xanthoma appears as nodules on tendons, most often the Achilles tendons at the back of the ankle. Corneal arcus appears as a grey or white ring at the edge of the cornea (the clear front of the eye). These signs are due to the deposition of cholesterol in tissues. Xanthelasma is not specific: only about half of adults with it have abnormal blood lipid levels. Having no signs does not rule out FH.
Treatment for hypercholesterolaemia combines diet, exercise and a statin. NICE advises a high-intensity statin for adults with FH, aiming for at least a 50% fall in LDL cholesterol. Ezetimibe can be added, or used instead if a statin cannot be taken. Adults whose LDL cholesterol does not fall by more than 50% from baseline (the level before treatment) on the maximum tolerated statin plus ezetimibe should be offered referral to a specialist. Bile salt sequestrants are used only on specialist advice, for example when statins or ezetimibe cannot be used.
Raised serum LDL is associated with the formation of atherosclerotic plaques. This happens because of the long half-life of LDL, which gives it a higher chance of being trapped in the artery wall. There it can become oxidised and be engulfed (phagocytosed) by macrophages, which then become foam cells. Plaques can narrow the arteries, which can cause angina (chest pain or tightness when the heart muscle gets too little blood). A plaque can also rupture, and the blood clot (thrombus) that forms on it can block an artery. This can cause a myocardial infarction (MI, or heart attack) or a stroke.
These are general guides for healthy adults, measured in millimoles per litre (mmol/l). A good target for you depends on your age, any health conditions and your risk of cardiovascular disease. For people who already have cardiovascular disease, NICE advises lower aims: LDL cholesterol of 2.0 mmol/l or less, or non-HDL cholesterol of 2.6 mmol/l or less.
- Total cholesterol < 5 mmol/l
- HDL cholesterol: above 1.0 mmol/l in men and above 1.2 mmol/l in women
- Non-HDL cholesterol (total cholesterol minus HDL cholesterol): below 4 mmol/l
- Total cholesterol to HDL cholesterol ratio: lower is better (for example, 4 is better than 6).
- A single total of all the lipids in the blood is not routinely used in clinical practice. Individual measurements, such as those above, are more helpful.
Edited by: Dr. Ben Appleby and Dr. Bethany Turner
Reviewed by: Dr. Marcus Judge
- 14929
