

Next Lesson - Fungi and Parasites: The Eukaryotic Pathogens
Core
Globally, HIV is a major public health concern and has proven to be a great challenge since it was first identified in the early 1980s. Despite an estimated decrease in incidence (new cases), prevalence (total cases) of HIV is increasing worldwide as life expectancy with the disease has increased with new treatments. To illustrate the scale of the disease, UNAIDS estimated that 41.0 million people were living with HIV in 2025. About 1.2 million people newly acquired HIV that year. About 88% of people with HIV knew their status (UNAIDS fact sheet). Since 2010, new HIV acquisitions have fallen by 42%.
HIV (Human Immunodeficiency Virus) is a retrovirus (an RNA virus that copies its RNA into DNA inside the host cell) that belongs to the Retroviridae family (the family of all retroviruses), Lentivirus genus (a group of retroviruses).
HIV affects cells of the immune system, specifically CD4 cells (a type of white blood cell). After hijacking the cell’s machinery to replicate, the virus destroys the cell. The CD4 count therefore falls as the infection progresses, so a low count means weaker immunity. The CD4 T-cell count is used to estimate the extent of immune damage. It is used with the viral load (the amount of HIV in the blood) to see whether treatment is working. A normal CD4 T-cell count for a healthy adult is about 500 to 1,200 cells per microlitre (μL) of blood. The US Centers for Disease Control and Prevention (CDC) groups HIV infection into stages, using the CD4 count and other information:
- Stage 0 is early infection, recognised by a negative HIV test within 6 months before the HIV diagnosis;
- Stage 1 is a CD4 count of 500 cells/μL or more, and the patient is usually asymptomatic (has no symptoms);
- Stage 2 is a CD4 count of 200 to 499 cells/μL;
- Stage 3 is a CD4 count below 200 cells/μL, or an AIDS-defining illness (see below). This stage is also called AIDS.
These stages are used by the CDC to count cases, not to make clinical decisions about one patient. Doctors also describe the usual course of untreated HIV in clinical stages:
- Seroconversion (the stage when the body first makes antibodies to HIV): some people have a short flu-like illness around 2 to 6 weeks after infection. It can include a high temperature, a sore throat, swollen glands, muscle aches, tiredness and a skin rash. Not everyone has symptoms. The image below shows the CD4+ count dropping soon after infection while the viral load rises sharply. The seroconversion illness can easily be mistaken for glandular fever (infectious mononucleosis, usually caused by the Epstein-Barr virus), which looks similar. Because anyone can catch HIV, include it in the differential diagnosis of a glandular-fever-like illness. A fourth-generation laboratory test (it detects HIV antibodies and p24 antigen, a protein from the inside of the virus, at the same time) picks up infection sooner than older tests. A negative rapid test does not rule HIV out. A test done within the window period (the weeks after infection before a test can detect HIV) needs repeating.
- Latent stage (also called the asymptomatic stage): this stage can last for several years with no obvious symptoms. The virus is not dormant, because HIV keeps replicating at low levels. CD4+ numbers slowly drop and the viral load slowly increases, but the person usually feels well. Infections linked to a weak immune system may begin to appear towards the end of this stage.
- AIDS: when the CD4+ count drops below 200 cells/μL, or an AIDS-defining illness develops, and opportunistic infections (infections that take advantage of a weak immune system) begin to take hold.
AIDS (Acquired Immunodeficiency Syndrome) is the term used to describe the most advanced stage of HIV infection when the patient has become ‘immunodeficient’ (or fully immunocompromised, meaning the immune system is badly weakened). The patient is now susceptible to serious complications from previously harmless infections, opportunistic pathogens (organisms that are not usually pathogenic in those with normal immune systems) and malignancies (cancers). Examples of AIDS-defining illnesses include: Kaposi’s sarcoma, a cancer caused by human herpesvirus 8 (HHV8); Pneumocystis pneumonia, a lung infection; candidiasis (thrush, a yeast infection) of the oesophagus (gullet), airways or lungs; and protozoal infections (infections caused by single-celled parasites), such as cerebral toxoplasmosis (a brain infection caused by the parasite Toxoplasma gondii). Without treatment, death usually results from opportunistic infections or malignancies associated with advanced HIV, rather than from direct effects of the virus alone. With effective treatment, most people with HIV do not go on to develop AIDS and can live a long and healthy life.
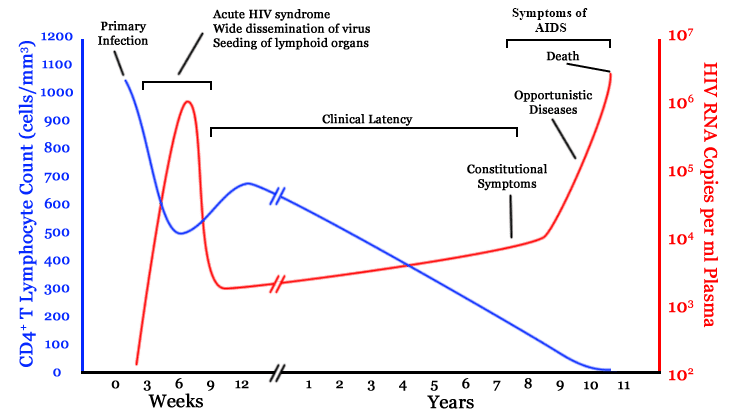
Figure: Shows the changes in CD4 lymphocyte count and viral load (HIV RNA) over time in a patient with HIV
Creative commons source by Jurema Oliveira [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
There is no specific physical sign relating to HIV infection itself, but signs related to worsening immunosuppression (a weakened immune system) can be observed at different stages of infection. These signs appear because the immune system gradually fails. Acute seroconversion can manifest with flu-like symptoms as described above. As the CD4+ cell count drops, recurrent and severe infections, e.g. oral candidiasis (thrush in the mouth), begin to present. Without treatment, the first signs of HIV-related illness usually develop within 5 to 10 years, or sometimes even sooner. In studies from before modern treatment, the median time from infection to AIDS was between 7.7 and 11.0 years, depending on age at infection. With effective treatment, most people with HIV never develop AIDS. How fast HIV progresses depends on how far the viral load (the amount of HIV in the blood) falls after seroconversion, and on how healthy the person’s immune system was to begin with.

Figure: The main signs and symptoms of an acute HIV infection
Creative commons source by Mikael Häggström [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
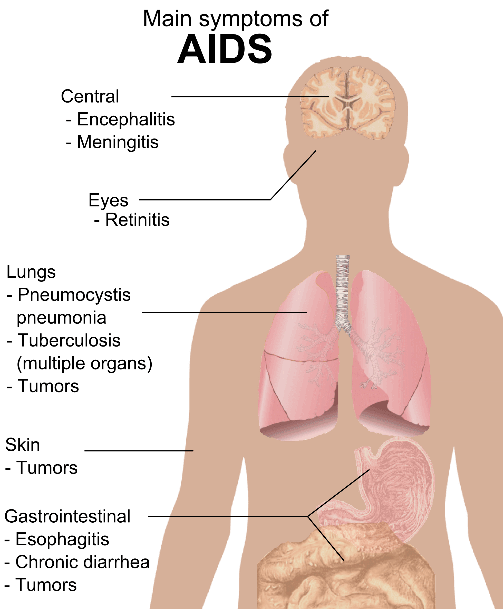
Figure: The main signs and symptoms of AIDS (advanced HIV infection)
Creative commons source by Mikael Häggström [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
The Life Cycle of HIV and Drug Targets
There are 7 steps of the HIV life cycle (i.e. how it hijacks and replicates in CD4 T cells). These are important to understand as they are used as targets for treatment:
- Binding (or Attachment) - HIV binds to the CD4 receptor on the surface of the CD4 cell. It then binds a second receptor, called a co-receptor, which is either CCR5 or CXCR4 (two receptor proteins on the cell surface that HIV uses to enter). Attachment inhibitors (such as fostemsavir), CCR5 antagonists (such as maraviroc) and post-attachment inhibitors (drugs that block HIV after it has attached to the CD4 cell) act here.
- Fusion - the viral envelope then fuses with the CD4+ cell membrane which allows the virus to penetrate the cell by emptying its contents inside the CD4+ host. These contents include HIV RNA and the reverse transcriptase enzyme (which copies RNA into DNA). Fusion inhibitors act here.
- Reverse transcription - inside the CD4+ cell, reverse transcriptase converts the HIV RNA into HIV DNA, which then enters the CD4+ cell nucleus. Nucleoside reverse transcriptase inhibitors (NRTIs) and non-nucleoside reverse transcriptase inhibitors (NNRTIs) act here. Both block the reverse transcriptase enzyme, in different ways.
- Integration - inside the nucleus, HIV integrases permanently combine the viral DNA with the CD4+ cell’s own DNA. Integrase inhibitors act here.
- Replication (or Transcription) - the host cell’s own machinery ‘reads’ the integrated viral DNA and makes new viral RNA. Some of this RNA becomes the genome of new viruses. The rest is used to make long chains of viral protein.
- Assembly - the new HIV proteins and RNA move to the surface of the cell and assemble into ‘immature’ (non-infectious) HIV.
- Budding - newly formed immature HIV pushes itself out of the host CD4+ cell. The new virus particle releases proteases (enzymes that cut proteins), which break up the long ‘immature’ protein chains into smaller ‘mature’ (infectious) HIV. Protease inhibitors (PIs) act here.

Figure: The Life Cycle of HIV
Creative commons source by NIAID [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
Many of these HIV enzymes are potential drug targets. Targeting different stages of the HIV life cycle at the same time makes treatment work better. It also lowers the risk of resistance (the virus mutating so that a drug stops working). This is why current treatment involves what is called ‘combination’ therapy. First-line treatment (the treatment tried first) for most people is an integrase inhibitor plus two nucleoside reverse transcriptase inhibitors (NRTIs). Examples are bictegravir in a single tablet with two NRTIs, or dolutegravir taken with two NRTIs. Dolutegravir with one NRTI (lamivudine) is a two-drug option for some people. A non-nucleoside reverse transcriptase inhibitor (NNRTI) or a boosted protease inhibitor (PI taken with a booster drug such as ritonavir or cobicistat) is used in place of the integrase inhibitor only in certain situations. The older name for this approach is highly active antiretroviral therapy (HAART). It is now usually called antiretroviral therapy (ART). A newer class, the capsid inhibitors (for example lenacapavir), blocks the HIV capsid, the protein shell that holds the viral genome. If you are particularly interested in this topic, it is worth visiting the NIAID page on antiretroviral drug development. The figure below shows some of the drugs used:

Figure: Some of the drugs used to treat HIV (this is not a complete list: newer drugs such as bictegravir, fostemsavir, lenacapavir and long-acting injections are not shown)
SimpleMed original by Dr. Elena Perez
Most people take their medicines as tablets every day. One combination is given instead as an injection into the buttocks every 2 months, but this is not available to everyone. Treatment is not a cure. It slows or halts progression, which increases life expectancy. When treatment keeps the viral load undetectable (too little HIV to be found on a blood test, although the virus is still there), HIV cannot be passed on through sex. This is known as ‘undetectable equals untransmittable’ (U=U).
As we have just seen, there is currently no cure for HIV. A very small number of people have been reported to be in remission, or possibly cured, after stem cell transplants from donors with a CCR5Δ32/Δ32 mutation (donors whose cells lack the CCR5 receptor that HIV uses to enter cells). The transplants were given to treat leukaemia or lymphoma, not HIV. The first reported case is known as the ‘Berlin patient’ (see this success story). Treatment allows people to have a near normal life expectancy and quality of life. However, it is costly and access remains unequal worldwide, with many people still not receiving antiretroviral therapy. Prevention is therefore a priority.
NHS and British HIV Association (BHIVA) advice on ways to help limit the risk of HIV transmission through sex includes:
- Using male or female condoms correctly every time you have sex. The NHS describes condoms as the most effective protection against HIV and other sexually transmitted infections (STIs)
- Taking antiretroviral drugs before exposure to prevent HIV infection (pre-exposure prophylaxis, PrEP)
HIV is a blood borne virus (a virus spread through blood and other body fluids), and sexual contact is one mode of transmission, but not the only one. HIV is passed on through blood, semen, vaginal fluid, mucus from inside the anus and breast milk. Through sex, it is passed on only when the person with HIV has a detectable viral load. Breastfeeding carries a small risk even when the viral load is undetectable. Saliva, urine, sweat, faeces and tears are not considered infectious unless they contain blood. Sexual contact accounts for the majority of infections globally. HIV can also be transmitted through blood transfusions and contaminated needles (mainly through needle sharing among people who inject drugs). It can also pass from mother to baby around the time of birth (perinatal transmission, also called vertical transmission). In the UK, the chance of infection from a blood transfusion is very low because donor blood is tested for a range of infections. Mother-to-baby transmission is now below 1% in the UK, with effective treatment in pregnancy, a careful choice of delivery method, a course of treatment for the baby and, in most cases, formula feeding instead of breastfeeding. UK guidance recommends formula feeding because breastfeeding still carries a small risk. A mother with a viral load below 50 copies per millilitre on treatment who chooses to breastfeed is supported by the HIV team with extra monitoring.
Not all these modes of transmission have an equal risk. Several factors affect the risk of transmission. One is the type of exposure: the type of sexual act, a transfusion, a needlestick injury (an injury from a used needle; see the article on hepatitis) or contact with a mucous membrane. Another is the viral load in the blood. People with a sustained undetectable viral load on effective antiretroviral therapy cannot pass on HIV through sex. Undetectable means too little HIV to be found on a blood test (below 200 copies per millilitre), although the virus is still there.

Figure: Shows the estimated risk of HIV transmission per exposure when the source has HIV and is not on suppressive treatment. Note that the figure gives 1 in 159 for mucous membrane exposure and 1 in 1,667 for insertive anal intercourse. BHIVA (2021) estimates about 1 in 1,000 and about 1 in 666 respectively. Oral sex carries a risk of less than 1 in 10,000.
SimpleMed original by Dr. Elena Perez
HIV Testing and Ethical Dilemmas
The earlier HIV is diagnosed, the better the prognosis, because treatment can start before the CD4+ count falls. Therefore anyone who suspects they might have become infected should go to a sexual health clinic or their GP for testing as soon as possible. Home testing kits are also available. Someone who may have been exposed in the last 72 hours should ask urgently about post-exposure prophylaxis (PEP, see below), which is available from sexual health clinics and A&E. A test done soon after an exposure may be negative because of the window period, so it may need repeating.
There are a few different tests that are used:
- Rapid Test (Point of Care (POC) test) - low cost test that gives a result within about half an hour. It uses either blood from a finger-prick or saliva (taken as an oral swab). It can be done in a clinic, or at home with a self-testing kit. A postal self-sampling kit is different: the sample is posted to a laboratory for testing. A negative result is reassuring, but false negatives (a negative result when the person is infected) can occur during the window period (the weeks after infection before a test can detect HIV). UK guidance (BHIVA) applies a window period of 90 days to all rapid tests, so a negative rapid test within 90 days of a possible exposure may need repeating. Rapid tests can also give false positives (a positive result when the person is not infected), so a positive result needs to be confirmed with laboratory serology testing (blood tests for antibodies and antigens).
- Serology - involves a blood sample sent off to a laboratory, so results are slower (usually within a few days). Modern (fourth-generation) laboratory tests look for HIV antigen (viral protein) and HIV antibody (immune response to the antigen) at the same time. This test is more accurate than rapid tests, but false negatives can still occur if testing is done during the window period. For a fourth-generation laboratory test the window period is about 45 days.
- PCR (Polymerase Chain Reaction) - detects HIV nucleic acid (the genetic material of the virus, RNA). It is a highly sensitive test which can detect infection earlier than antibody tests, but it is expensive, and results can take up to a week. It is not recommended for routine HIV diagnosis. It is used when the diagnosis is uncertain, for example when primary (very recent) HIV infection is suspected, and for follow-up and monitoring treatment response.
Who should be tested? UK guidelines (from the British HIV Association, BHIVA, in 2020, and from NICE, guideline NG60) say an HIV test should be offered and recommended in the situations below. Most of these are indicator conditions: medical conditions associated with undiagnosed HIV. They are linked to it either because they share transmission routes with HIV (for example hepatitis B and C) or because of dysregulated immunity (an immune system that is not working normally). These include the following (the tag in square brackets shows the specialty, such as respiratory, neurology, dermatology, gastroenterology, haematology, oncology or gynaecology):
- People not previously tested who use healthcare in an area where 2 to 5 in every 1,000 people have diagnosed HIV, if they are having blood taken (venepuncture); in areas with 5 or more in every 1,000, all attendees
- Bacterial pneumonia/TB [Resp]
- Meningitis/dementia [Neuro]
- Severe or atypical psoriasis; shingles (herpes zoster) [Derm]
- Chronic diarrhoea/weight loss with unknown cause [Gastro]
- Any unexplained blood abnormality [Haem]
- Lymphoma, anal cancer [Onc]
- Cervical intraepithelial neoplasia (CIN) [Gynae]
- Any sexually transmitted infection (STI), hepatitis B or hepatitis C
Someone exposed to HIV, for example a nurse with a needlestick injury (an injury from a used needle), may be offered post-exposure prophylaxis (PEP). PEP is a course of antiretroviral drugs taken soon after exposure to prevent infection. PEP is given only after a risk assessment. It should be started as soon as possible, preferably within 24 hours, and never later than 72 hours after the exposure. The first-line regimen is tenofovir disoproxil with emtricitabine plus raltegravir, taken once daily for 28 days. PEP is not recommended after a sharps injury (an injury from a used needle or other sharp object) or a mucosal splash (body fluid splashed onto the eyes or mouth) if the source is untested and from a low-risk group. It is generally not recommended if the source is untested and from a high-risk group, unless other factors make transmission more likely. After a work-related exposure, the person should be followed up by their occupational health department, ideally within 72 hours.
Because of the infectious nature of HIV, there are some ethical dilemmas healthcare professionals might face. HIV testing should be voluntary and confidential, so it needs the patient’s consent (a long pre-test discussion is not required, but the patient must know they are being tested for HIV). The patient should then be trusted to tell their partner(s) or anyone else they might put at risk of infection. However, a patient may sometimes ask their GP not to tell their partner. The ethical dilemma here is patient confidentiality versus the risk of serious harm to others, such as a partner who is at risk of infection. In this case, explain to the patient why telling their partner matters, and set out the dilemma of weighing patient confidentiality against other people’s safety (e.g. the health of a mother, an unborn child or a sexual partner).
Another important aspect of HIV is the stigma that still can be associated with the condition. When making a diagnosis of HIV, healthcare professionals must be aware of the impact this might have on their patients and provide them with the right support, medically but also psychologically.
Edited by: Dr. Ben Appleby and Dr. Thomas Burnell
Reviewed by: Dr. Marcus Judge
- 9081



