

All done here! Check out our other subjects!
Core
Invasion is when a tumour grows from its primary site into surrounding structures.
Epithelial to mesenchymal transition (EMT) is a process by which epithelial cells undergo multiple changes until they more closely resemble a mesenchymal cell (a loosely connected, mobile connective tissue cell). These changes reduce cell adhesion (how strongly cells stick together) and increase motility (the ability to move), which facilitates invasion.
For malignant cells to invade into surrounding tissues they require:
- Altered cellular adhesion
- Decreased expression of E-cadherin (a protein that holds neighbouring cells together) reduces the cell-cell adhesion.
- Changes to expression of integrin receptors (proteins on the cell surface that anchor it to its surroundings) alter the adhesion between cells and extracellular matrix (the network of material around cells).
- Increased secretion of proteolytic enzymes (enzymes that break down proteins)
- Matrix metalloproteinases (MMPs) are enzymes secreted by malignant cells to enable them to break down surrounding connective tissue.
- Increased cellular motility

Diagram - The progression of epithelial to mesenchymal transition which eventually allows epithelial cells to cross the basement membrane (the thin layer of supporting tissue under epithelial cells) and invade surrounding structures. (MMPs - matrix metalloproteinases)
SimpleMed original by Dr. Emily Smith
Metastasis is the process in which malignant cells migrate from the primary site of the tumour to a distant secondary site to form another tumour. It is a consequence of growth and invasion at the primary site. In order to metastasise, malignant cells need to:
- Invade through the basement membrane of blood or lymphatic vessels - intravasation.
- Avoid host immune defences.
- Attach to endothelium (the lining of blood and lymphatic vessels) at a distant location.
- Leave the blood or lymphatic vessel to enter surrounding tissue - extravasation.
There are several different routes of metastasis: bloodstream, lymphatics and transcoelomic spread (across a body cavity such as through the peritoneal, pleural or pericardial cavities). Carcinomas typically spread to the draining lymph nodes first, and then spread via the blood stream. Sarcomas tend to spread by the blood stream first.
Many malignant cells can reach a secondary site but might not grow for a number of reasons, including being caught by the immune system, or not being able to invade the tissue at the secondary site. This spread of cancer cells leads to micro-metastases - clinically undetectable groups of malignant cells. These micro-metastases can start to regrow after a period of time, which is what causes an apparently cured patient to relapse. Cancer cells that cannot be detected could also be carried in a donated organ, so people with active cancer cannot donate their organs. Some people who have had cancer may be able to donate after treatment, depending on the type of cancer.
Blood Stream Metastasis
Secondary tumours form in organs which are perfused by blood that has drained from the site of the tumour. For example, GI (gastrointestinal) malignancies often spread to the liver due to drainage by the portal vein which takes blood to the liver.
Metastases through the blood often form masses at the liver, lungs, bone and brain due to blood flow patterns.
Carcinomas originating from the lung, breast, thyroid, kidney and prostate commonly spread to bone. Metastases from the lung, breast, thyroid and kidney often cause lytic lesions, which means they destroy bone and decrease bone mass, although breast metastases are frequently sclerotic or mixed instead. Metastases from the prostate most often cause sclerotic lesions, which means extra bone forms and bone mass increases, although some are lytic or mixed. These changes can be visible on x-rays.
Lymphatic Metastasis
Malignant cells enter lymph nodes through the afferent lymph vessels (the vessels that carry lymph into the node) and settle at the periphery of the node. They grow inwards and the node is gradually replaced by cancer cells and connective tissue. This can result in lymphadenopathy (swollen lymph nodes) and blockage of lymph flow leading to lymphoedema (swelling caused by a build-up of lymph fluid) in the region drained by the blocked lymph vessels.
Transcoelomic Spread
This type of metastasis occurs within pleural, pericardial and peritoneal cavities. This results in formation of a protein rich effusion (an abnormal collection of fluid), called an exudate, within the cavity. The fluid contains malignant cells, so it can be drawn off with a needle (aspirated) and examined under a microscope for diagnosis.
Malignant peritoneal effusions (ascites, fluid in the abdominal cavity) are commonly caused by ovarian tumours, although cancers of the breast, colon, stomach and pancreas can also cause them. Ascites also has non-cancer causes, most often liver cirrhosis (scarring of the liver). Malignant pleural effusions are most often caused by lung and breast cancers, and these cancers can also cause pericardial effusions. Pleural effusions also have non-cancer causes, such as heart failure.
Growth of benign and malignant tumours can lead to compression and obstruction of adjacent structures. For example, growth of a pituitary adenoma (a tumour of the pituitary gland, which sits below the brain) can cause compression of the optic chiasm (where the two optic nerves cross), resulting in a bitemporal hemianopia - loss of the outer (temporal) half of the visual field in both eyes, which is felt as loss of peripheral vision. Colorectal carcinoma can cause constipation due to obstruction of the lumen of the bowel.
There are some local effects which are more specific to malignant neoplasms. Malignant neoplasms on mucosal surfaces often ulcerate and bleed, therefore GI malignancy is an important differential in adults with iron-deficiency anaemia (anaemia caused by too little iron, which slow bleeding can cause) and in people aged 60 and over with anaemia of any type. The bleeding could be occult (not visible to the naked eye) so patients may not realise.
A key feature of malignant neoplasms is their ability to invade into surrounding tissues. For example, at late stages cervical cancer can invade into the bladder and rectum, leading to fistula formation (an abnormal channel between two organs) and incontinence as urine or faeces leak out of the vagina.
A paraneoplastic syndrome is a clinically detectable systemic effect caused by a neoplasm but not related to metastasis. These signs and symptoms are typically caused by ectopic hormone secretion, immune cross-reactivity (immune cells or antibodies that attack the tumour also attacking normal tissue), or cytokine release (chemical messengers made by immune cells) rather than the direct effects of tumour growth.
An increase in tumour burden, and other factors such as release of cytokines, can lead to cachexia (weakness and wasting), malaise (feeling generally unwell), immunosuppression (a weakened immune system) and thrombosis (blood clots).
Tumours that secrete hormones can cause a range of effects. For example, a benign tumour of an endocrine gland may secrete hormones at a higher level than is secreted by healthy tissue. A thyroid adenoma secreting high levels of thyroid hormone results in thyrotoxicosis (hyperthyroidism), and an adenoma of the adrenal cortex can result in Cushing’s syndrome due to excess cortisol secretion.
Some malignant tumours are also able to produce hormones. This is called ectopic hormone secretion as they are not normal sites for hormone production. Examples of this include:
- Bronchial small cell carcinoma (a type of lung cancer) producing ACTH (adrenocorticotropic hormone) resulting in Cushing’s syndrome.
- Bronchial small cell carcinoma producing ADH (antidiuretic hormone) resulting in Syndrome of Inappropriate ADH (SIADH), in which the body holds on to too much water and blood sodium falls.
- Bronchial squamous cell carcinoma (a type of lung cancer that arises from the flat cells lining the airways) producing a PTH (parathyroid hormone) related peptide (PTHrP), resulting in hypercalcaemia (high blood calcium).
Tumour markers include substances produced by tumour cells or by other tissues in response to cancer or benign conditions, as well as tissue and molecular markers (changes in the tumour's own DNA or proteins) such as gene mutations. Circulating markers can be measured in blood or other body fluids. Serial measurements (repeated tests over time) can help assess treatment response or recurrence in an established cancer. Markers may also assist diagnosis or treatment selection, but results must be interpreted with other findings: a raised level does not by itself diagnose cancer, and a normal level does not exclude it.
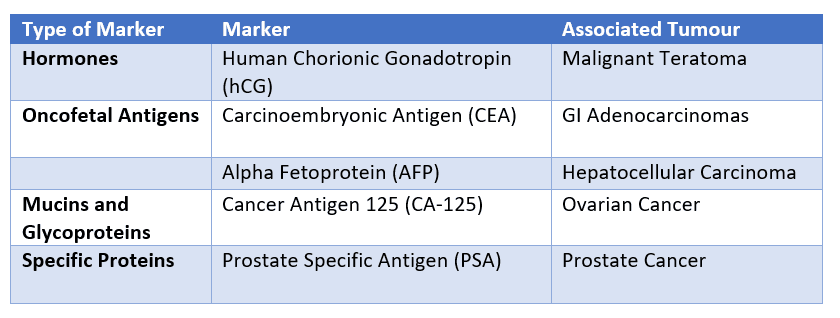
Table - Some tumour markers and their associated tumour
SimpleMed Original by Dr. Emily Smith
Edited by: Dr. Bethany Turner
Reviewed by: Dr. Maddie Swannack and Dr. Marcus Judge
- 9244
