

Next Lesson - The Eye
Core
The primary function of the mouth is to act as a receptacle for food and drink, and to initiate digestion.
The opening to the mouth is known as the oral fissure. Immediately posterior to this is the vestibule, which is a slit-like space between the lips and the gums and teeth. Beyond the teeth is the oral cavity proper.
The boundaries of the oral cavity proper are:
- Anterior boundary - Teeth
- Lateral boundaries of the oral cavity proper - the dental arches. The cheeks, containing buccinator, form the outer lateral walls of the oral vestibule.
- Roof - Hard and soft palate
- Floor - Tongue and mylohyoid muscles (the sling of muscle beneath the tongue)
- Posterior boundary - Palatoglossal arches
The palate forms the roof of the oral cavity. The anterior 2/3 of the palate is made of bone and is called the hard palate. The soft palate makes up the posterior 1/3 of the palate; it is moveable and made up of soft tissue. Most muscles of the soft palate are innervated by the vagus nerve (CN X, where CN stands for cranial nerve) through the pharyngeal plexus. The exception is tensor veli palatini (a small muscle that tenses the soft palate). It is supplied by the nerve to medial pterygoid (a chewing muscle), which comes from the mandibular division of the trigeminal nerve (CN V3). The trigeminal nerve is cranial nerve V, so V3 is its third division. The uvula hangs from the soft palate (it is the small fleshy projection at the back of the mouth). It has roles in speech, lubrication of the mouth and stimulation of the gag reflex.
The soft palate is continuous with the wall of the pharynx and extends laterally to form two arches: the palatoglossal arch (anteriorly) and palatopharyngeal arch (posteriorly). The space between these arches is called the tonsillar fossa (or tonsillar bed), which accommodates the palatine tonsils.
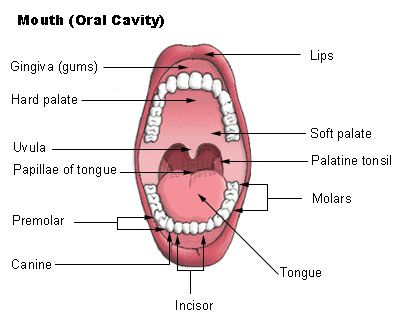
Diagram - Basic anatomy of the mouth
Public Domain Source [Public domain]
The tonsils are aggregations of lymphoid tissue found within the oropharynx and nasopharynx. They are therefore part of the immune system and specifically protect against ingested and inhaled pathogens.
There are 6 tonsils, which form an arrangement called Waldeyer’s ring:
- Lingual Tonsil - located within the submucosa (the layer just beneath the surface lining) of the posterior 1/3 of the tongue.
- Palatine Tonsils (x2) - located within the tonsillar fossae.
- Tubal Tonsils (x2) - located in the lateral walls of the nasopharynx, near the opening of the Eustachian tube. This tube is also called the pharyngotympanic tube and connects the nasopharynx to the middle ear.
- Pharyngeal Tonsil (adenoids) - located in the roof of the nasopharynx.
The pharynx and tonsils can become inflamed due to infection, resulting in pharyngitis (inflammation of the pharynx) and/or tonsillitis (inflammation of the tonsils). Most cases of tonsillitis are viral, but tonsillitis can also be caused by the bacterium Streptococcus pyogenes, which is the most common bacterial cause of sore throat. Most people recover within a week whether the cause is viral or bacterial. Doctors use the Centor criteria or FeverPAIN score to estimate how likely a bacterial cause is. These scoring systems add up points for signs such as fever, pus on the tonsils and absence of cough. Viral cases are managed conservatively whereas bacterial tonsillitis is treated with an antibiotic such as penicillin V. For more information, check out our article on Streptococci.
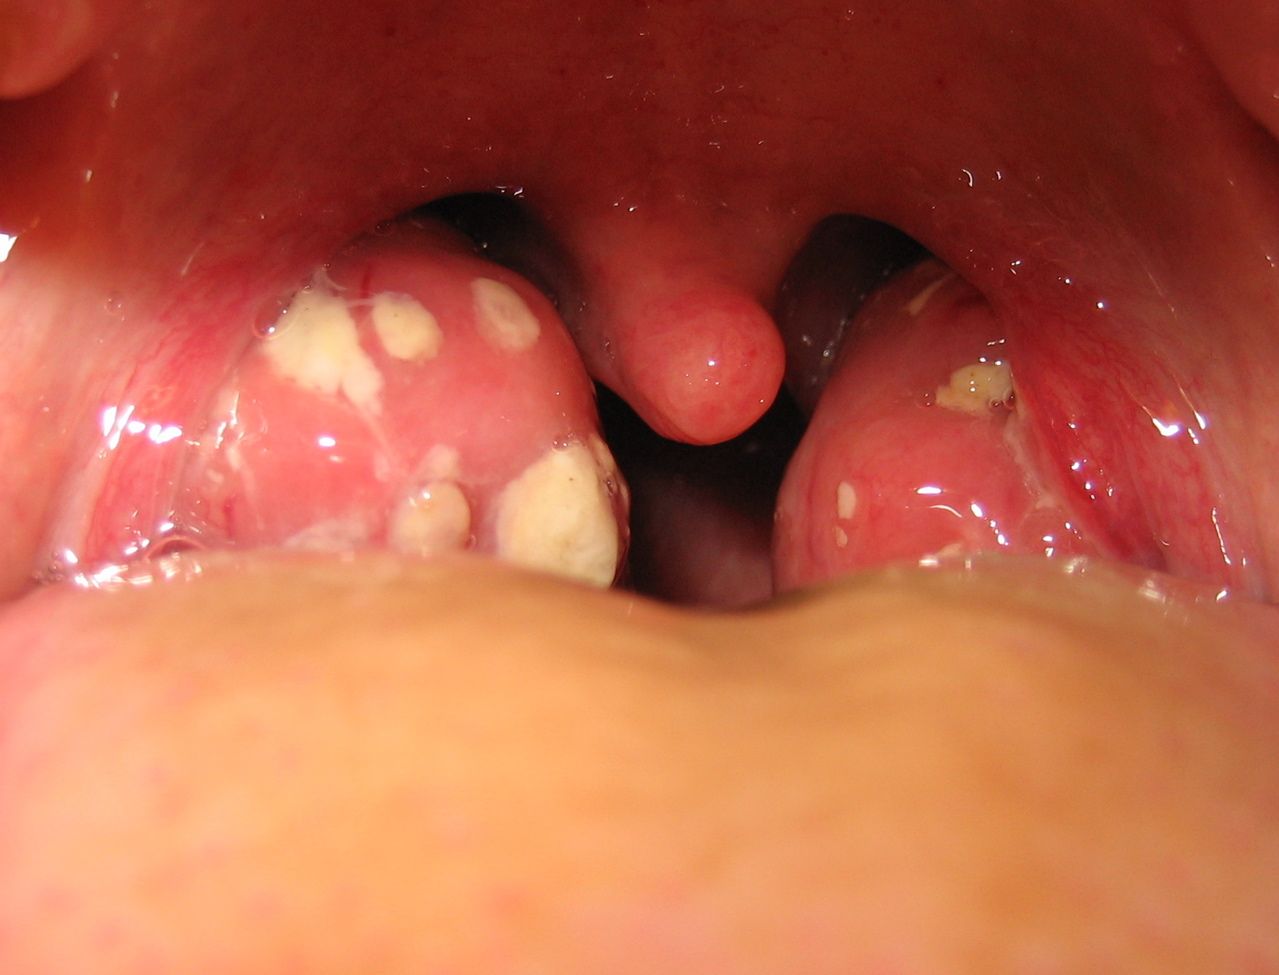
Image - Inflamed palatine tonsils with a purulent exudate (pus)
Public Domain Source by Michaelbladon [Public domain]
The primary function of the teeth is mastication (chewing). This increases the surface area of food for digestive enzymes to act on and enables the formation of a bolus (a soft ball of chewed food). The teeth also play a role in articulation of speech.
Humans have 2 sets of teeth during their lifetime: deciduous (primary) and permanent (secondary). Children have 20 deciduous teeth, which shed between the ages of 6-12 years as the permanent teeth erupt (break through the gum) and take their place. Adults normally have 32 permanent teeth, most of which erupt by age 12 years. The 3rd molars (wisdom teeth) can take up to the age of 25 to erupt and may not even be present in some individuals.
Teeth are classified by their shape and function:
- Incisors (8) - located centrally, these thin knife-like teeth act to cut food and break off food in the initial bite.
- Canines (4) - these cone-shaped teeth are designed for tearing food.
- Premolars (8) - these have 2 cusps (raised points on the biting surface) and a flatter surface for mashing and grinding.
- Molars (12) - these back teeth have 3 or more cusps and a flat surface for mashing and grinding.
Each tooth has a crown, a neck and a root. The crown is the externally visible part of the tooth which projects from the gingiva (gums). The neck is the region between the crown and root. The root is fixed in the tooth socket by connective tissue called the periodontal ligament. The periodontal ligament is part of the periodontium, the group of tissues that support the tooth (the gums, the covering of the root, the bone of the socket and the periodontal ligament itself). The majority of the tooth is composed of dentine (hard, bone-like tissue). The crown is lined with enamel (the hardest substance in the body!) and the root is lined with cementum (a thin, bone-like layer). The root canal transmits nerves and blood vessels.
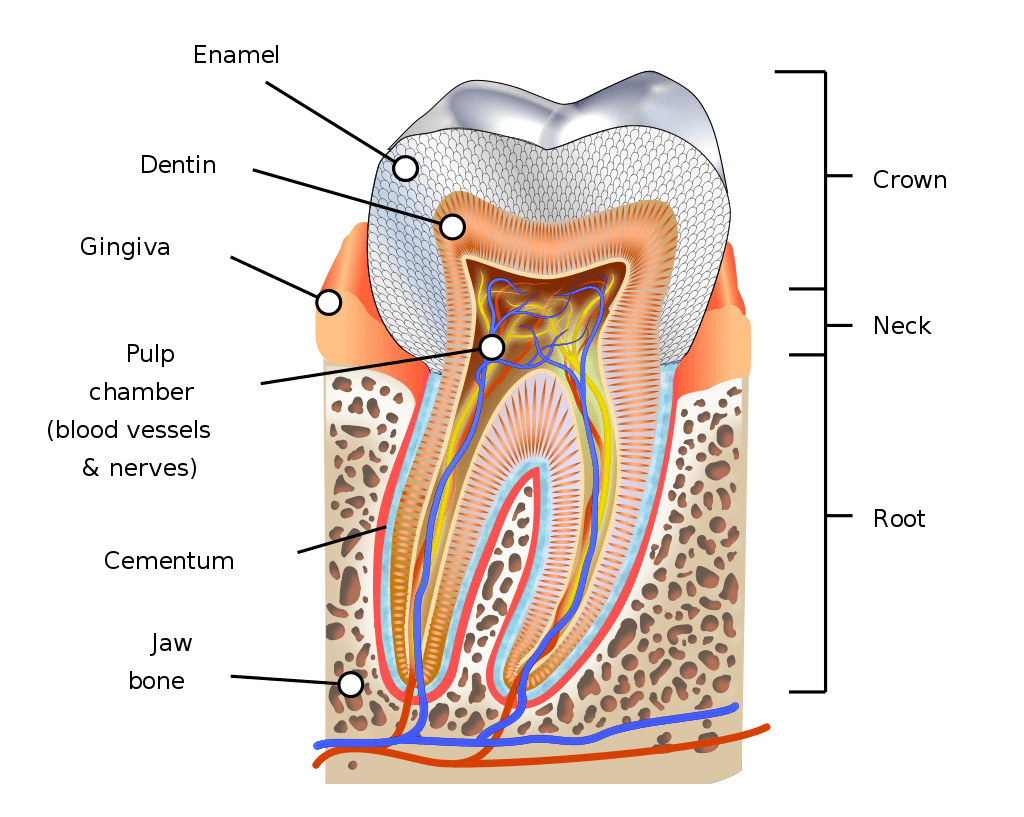
Diagram - Anatomy of the tooth
Creative commons source by KDS4444 [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Bacteria in the oral cavity feed on sugars and produce acid, which over time dissolves the minerals in the enamel of the tooth, resulting in dental caries (tooth decay). Left untreated, this decay can extend into the pulp cavity (the soft centre of the tooth, which contains nerves and blood vessels). This causes infection and inflammation of the pulp, which presents with considerable toothache. Without treatment, the infection could eventually lead to abscess formation (a collection of pus) and loss of the tooth. Treatment involves removal of the decayed tissue and replacement with a prosthetic filling.
Bacterial deposits in the mouth can also irritate the gums, leading to gingivitis. This presents with swollen, red gums which are tender and bleed easily. Gingivitis may progress to periodontitis (long-term inflammation of the tissues that support the teeth) if plaque is not removed. Periodontitis can lead to gum abscess formation and tooth loss. Management involves removing plaque with good oral hygiene: brushing twice a day with a fluoride toothpaste and cleaning between the teeth every day with interdental brushes or floss. Mouthwashes are not routinely recommended, but an antiplaque mouthwash such as chlorhexidine (an antiseptic) may be used for a short time, for example when brushing is painful. The dentist or hygienist can also offer more specialist cleaning treatments.
The tongue is a very mobile, muscular organ which occupies most of the oral cavity at rest. It has important roles in taste, speech and swallowing.
The tongue is lined with mucosa, which contains projections called papillae. The papillae increase the surface area of the tongue. Fungiform, circumvallate and foliate papillae carry taste buds (the receptors for taste). The filiform papillae are found across the whole upper surface of the tongue but have no taste buds; they give a rough texture that helps grip food.
The tongue is anchored to the floor of the mouth via the lingual frenulum (a thin fold of lining tissue under the tongue).
Muscles of the tongue are grouped as either intrinsic or extrinsic:
- Intrinsic - there are 4 pairs of intrinsic muscles which act to alter the shape of the tongue.
- Superior longitudinal
- Inferior longitudinal
- Transverse
- Vertical
- Extrinsic - these muscles connect the tongue to surrounding structures and act to alter the position of the tongue.
- Genioglossus - important in protruding the tongue.
- Hyoglossus - lowers and pulls back the tongue.
- Styloglossus - pulls the tongue back and up.
- Palatoglossus - raises the back of the tongue.
Most of the muscles of the tongue are innervated by the hypoglossal nerve (CN XII). The exception is palatoglossus, which is innervated by the vagus nerve (CN X).
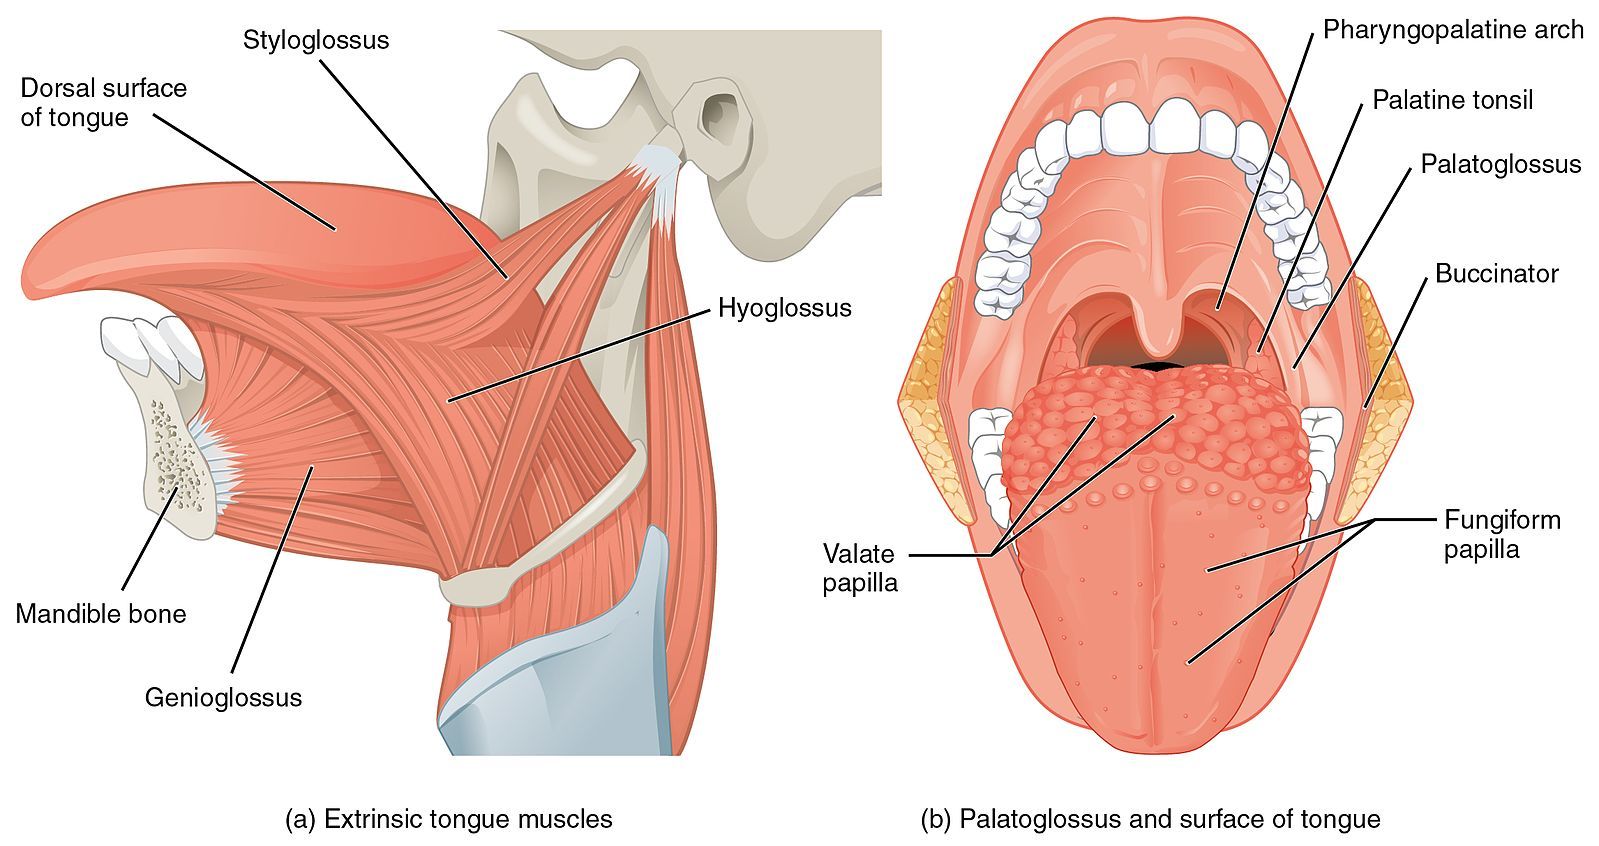
Diagram - Muscles of the tongue
Creative commons source by OpenStax [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The special sensory innervation of the tongue (i.e. taste) is the following:
- Anterior 2/3 - chorda tympani, a branch of the facial nerve (CN VII)
- Posterior 1/3 - glossopharyngeal nerve (CN IX)
The general sensory innervation of the tongue is:
- Anterior 2/3 - lingual nerve, a branch of the mandibular division of the trigeminal nerve (CN V3)
- Posterior 1/3 - glossopharyngeal nerve (CN IX)
The salivary glands include 3 pairs of major glands, which are exocrine glands whose ducts open into the oral cavity. There are also many tiny minor glands in the lining of the mouth. They produce saliva, which has important roles in digestion, lubrication, bolus formation and innate immunity.
The 3 pairs of major salivary glands are:
- Parotid Glands - the largest of the salivary glands. They are bounded by the zygomatic arch (cheekbone), the mandible, sternocleidomastoid (the large muscle at the side of the neck) and the masseter muscle (a chewing muscle). Each gland’s secretions enter the oral cavity via the Stensen duct, which opens into the vestibule opposite the upper 2nd molar tooth bilaterally.
- Submandibular Glands - situated within the submandibular triangle. This triangle is bounded by the mandible and the anterior and posterior bellies of the digastric muscle (a muscle that runs from the chin to behind the ear). Each gland’s secretions enter the oral cavity via Wharton’s duct, which opens at the base of the lingual frenulum bilaterally.
- Sublingual Glands - located in the sublingual fossa. Their ducts open onto the sublingual folds.
For more information on the composition and production of saliva, check out our article on Anatomy and Physiology of the Foregut.
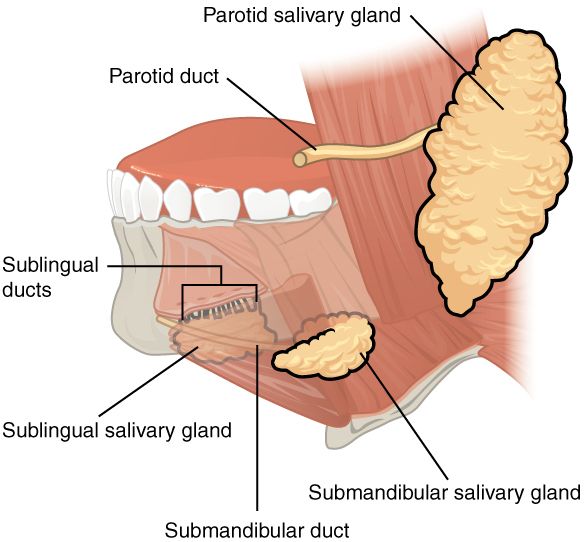
Diagram - Anatomy of the salivary glands
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Sialolithiasis is the formation of a stone within the duct or parenchyma (the working gland tissue) of a salivary gland. The submandibular glands are most commonly affected. Stones are associated with reduced salivary flow (salivary stasis), for example in dehydration, with some medications or in Sjögren’s syndrome (an autoimmune condition that causes a dry mouth). Submandibular saliva is rich in calcium and drains through a long duct that runs against gravity, which helps explain why most stones form there. Salivary gland stones can present with a unilateral facial swelling and pain on eating. The stone may be palpable (able to be felt by touch) or even visible on examination. Diagnosis is with history and examination, supported by imaging such as ultrasound, CT or MRI, or by looking inside the duct with a tiny camera (sialendoscopy). Many cases are managed without an operation, using fluids, analgesia (pain relief), gland massage, warm compresses and sialogogues (things that stimulate saliva flow). Stones that do not pass may need removal through the duct with a sialendoscope, breaking up with lithotripsy (breaking the stone into small pieces, for example with shock waves), or surgery.
The pharynx is a proximal part of the alimentary canal (the digestive tract) situated posterior to the oral and nasal cavities. It is an important structure as it provides a passage for air into the larynx and food into the oesophagus. It is important that these pathways do not get mixed up!
The pharynx is divided into 3 parts:
- Nasopharynx - situated posterior to the nasal cavity at the level of the first cervical vertebra (C1, the top bone of the spine in the neck). The adenoids are located here. It also communicates with the middle ear via the Eustachian tube.
- Oropharynx - situated posterior to the oral cavity at the level of C2-3. It extends from the soft palate to the epiglottis (the flap of cartilage that covers the larynx during swallowing). It is a common route for both air and food.
- Laryngopharynx - situated posterior to the larynx at the level of C3-6, extending from the epiglottis to the oesophagus.
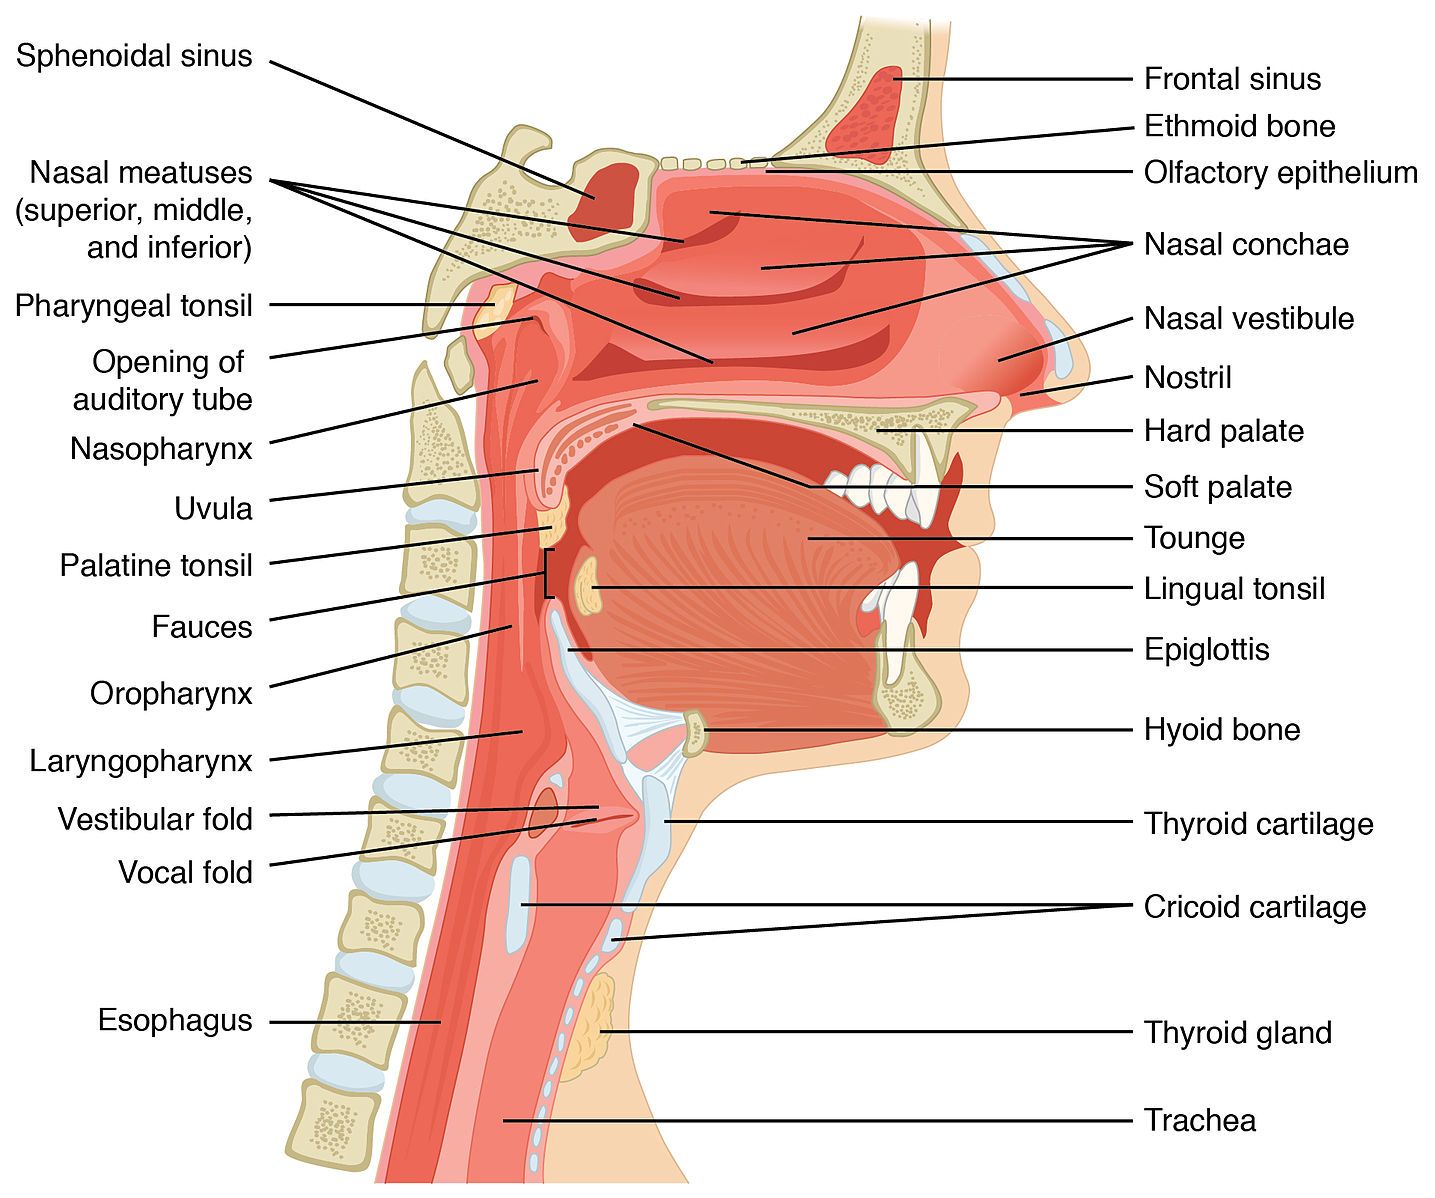
Diagram - Sagittal section of the head and neck, showing the anatomy of the pharynx and nearby structures
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The muscles of the pharynx are grouped into longitudinal and circular:
- Longitudinal Muscles - these elevate the larynx during swallowing.
- Stylopharyngeus
- Palatopharyngeus
- Salpingopharyngeus
- Circular Muscles (Pharyngeal Constrictors) - these push material down the pharynx via peristalsis.
- Superior
- Middle
- Inferior
The inferior pharyngeal constrictor contains a weakness (a gap between the cricopharyngeus muscle, the lowest band of the constrictor, and the rest of the constrictor) known as Killian’s dehiscence. Abnormal coordination of swallowing can cause the pharynx to herniate (bulge out) through this weakness, resulting in a pharyngeal pouch (or Zenker’s diverticulum). This presents with dysphagia (difficulty swallowing), choking, regurgitation (food coming back up into the mouth) and halitosis (foul-smelling breath). Occasionally a lump may be palpable in the neck, usually on the left, as most pharyngeal pouches are left-sided. Treatment is surgical: open surgery has been the traditional approach, but endoscopic techniques (using a camera passed through the mouth, with staples or a laser) are increasingly favoured.
In terms of motor innervation, most of the pharyngeal muscles are innervated by the vagus nerve (CN X). The exception is stylopharyngeus, which is innervated by the glossopharyngeal nerve (CN IX).
The sensory innervation of the pharynx is as follows:
- Nasopharynx - maxillary division of the trigeminal nerve (CN V2)
- Oropharynx - glossopharyngeal nerve (CN IX)
- Laryngopharynx - vagus nerve (CN X)
Swallowing is a complex mechanism involving highly coordinated movements of the skeletal muscles of the tongue, soft palate, pharynx and larynx.
The swallow is split into 3 phases:
- Oral Phase - the process of mastication produces a food bolus. The tongue then presses against the roof of the mouth and pushes the bolus towards the oropharynx. This phase is under voluntary control.
- Pharyngeal Phase - once the bolus reaches the pharynx, the swallowing reflex is stimulated and the rest of the swallow is a reflex (involuntary) response. During this phase, the actions of many muscles ensure that food is pushed into the oesophagus whilst also protecting the airway.
- The soft palate is elevated to seal off the nasopharynx.
- The larynx is elevated via contraction of the suprahyoid muscles (the muscles above the hyoid bone, a U-shaped bone in the neck) and the longitudinal pharyngeal muscles.
- The epiglottis folds back to close over the laryngeal inlet (the opening into the larynx), mainly because the larynx is elevated and the base of the tongue moves backwards.
- The vocal cords adduct to close off the glottis (the space between the vocal cords).
- The pharyngeal constrictors contract and the upper oesophageal sphincter (UOS) relaxes to allow food to enter the oesophagus.
- Oesophageal Phase - once the bolus has entered the oesophagus, it is pushed down the oesophagus via peristalsis.
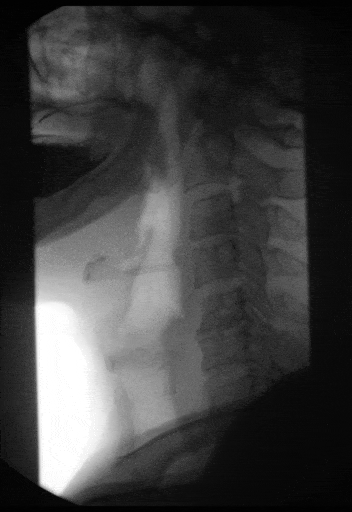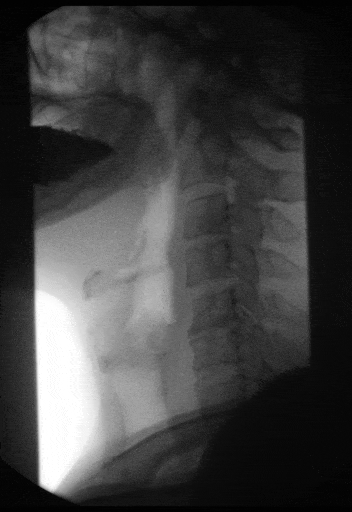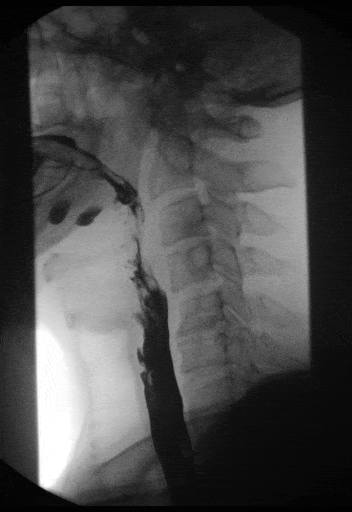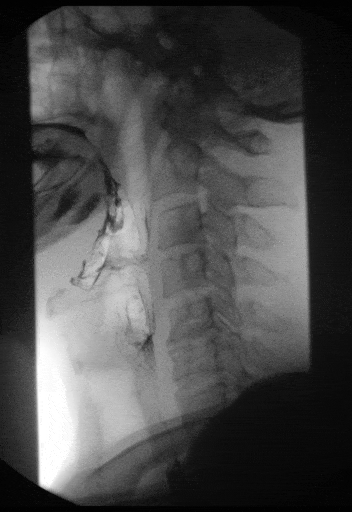
GIF - Barium swallow showing a normal swallowing reflex
Creative commons source by Hellerhoff, modified by Anka Friedrich [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Lesions (areas of damage or abnormality in a nerve) affecting cranial nerves V, VII and IX will result in sensory loss in their respective nerve territories, but the type of sensation lost differs. In the tongue, a lesion of the mandibular division of the trigeminal nerve (CN V3) causes loss of general sensation (touch and pain) from the anterior 2/3. A lesion of the facial nerve (CN VII) causes loss of taste from the anterior 2/3 (via the chorda tympani). A lesion of the glossopharyngeal nerve (CN IX) causes loss of both general sensation and taste from the posterior 1/3.
A lesion affecting the vagus nerve (CN X) will paralyse the ipsilateral soft palate. When the patient is asked to ‘say aaaah’, the ipsilateral soft palate will fail to rise and the uvula will deviate away from the side of the lesion. As the vagus nerve also supplies most of the pharyngeal muscles, the swallowing reflex may also be affected.
A lesion affecting the hypoglossal nerve (CN XII) will paralyse the ipsilateral skeletal muscle of the tongue. Therefore, when the patient is asked to protrude their tongue, the tongue will deviate towards the side of the lesion (to ‘lick the wound’). Muscle wasting and fasciculations (visible muscle twitches) may also be evident.
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 7839



