

By Dr. Keertana Anne and Dr. Tom Bradley
Next Lesson - Blood Groups, Crossmatching and Transfusion Reactions
Core
Put simply, an abnormal result is one which falls outside the normal range of values or is drastically different to a previous result.
A normal range (also called a reference range) is a set of values within which most healthy people fall (for normal ranges, please refer to Figure 1). Note that normal ranges can vary between laboratories.
However, a normal range is by no means a perfect measure. The normal range covers the middle 95% of values seen in healthy people. Therefore about 5% of results from healthy people (2.5% above the range and 2.5% below it) will lie outside the normal range without any pathology (disease). An FBC reports many values, so a healthy person can have one result slightly outside its range.
Therefore it is extremely important not to rely on blood tests alone. Blood tests should only be used as an adjunct (an addition) to a good history and examination. They should always be interpreted in the clinical context of the patient and in relation to any previous blood results.
The normal range also changes for different groups of people. It can be affected by age, sex, pregnancy, ethnicity and co-morbidities (other medical conditions the patient has).
A result may also be abnormal if it is very different from the patient’s previous results, because in a healthy person blood values usually change only a little between tests. Small changes can be normal variation.
If a result is unexpected the blood test should always be repeated as there are several sources of errors in processing an FBC:
Specimen collection error:
- There could be the wrong blood in the tube (blood is not that of the patient identified on the label).
- The wrong bottle could be used for the test (different bottles are required for different samples as they contain specific agents for that test).
- There could be pooling (mixing) of different samples: blood from repeated venepunctures (taking blood from a vein with a needle) is combined to fill one tube.
- Poor technique or heavy handling of the sample can spoil it and change the values, so the result is inaccurate. For example, a tube that is not gently mixed with its anticoagulant can clot, and vigorous mixing can burst the red cells (haemolysis).
Delivery of specimen to laboratory error:
- The specimen can be delayed, not delivered or lost. An FBC should be processed within a timeframe specified by the local laboratory, as stability depends on storage conditions and the analyser used.
- The specimen can be delivered by the wrong method. Some samples need to be kept at a set temperature. Others need to be hand delivered, because the sample can be damaged by the pneumatic tube (the air-pressure system that carries most samples through pipes).
Specimen analysis and result reporting error:
- A specimen mix-up can occur at the lab through human error.
- Clinical details can be recorded wrongly, for example when poor handwriting is misread or the wrong information is written down.
- The wrong test can be requested or performed.
- There is inherent test variability for the analysers as they are not 100% accurate all of the time.
- Technical errors can occur with the analysers.
Responsive action error:
- Sometimes nothing is done in response to an abnormal result.
- Reflex tests (extra tests required in response to the results of the FBC) are not carried out.
- The right result can be applied to the wrong patient.
These errors matter because a missed or misplaced result can delay a diagnosis or lead to the wrong treatment.
An FBC is measured on an automated analyser (a machine that counts and measures the blood cells). The analyser can process thousands of samples every day and is usually accurate, but errors can still occur (see the list of errors above).
The sample must be placed in a tube containing k-EDTA (potassium ethylenediaminetetraacetic acid, an anticoagulant) and gently mixed. The k-EDTA acts to chelate (bind) calcium ions to prevent clotting, which would render the sample unusable. Never use a k-EDTA FBC tube to take a sample for urea and electrolyte (U&E) analysis. The k-EDTA is a potassium salt, so it adds potassium to the sample and gives a falsely high potassium result. It also binds calcium and magnesium, so these can be falsely low. If a falsely abnormal result is not recognised, it can adversely affect patient care.
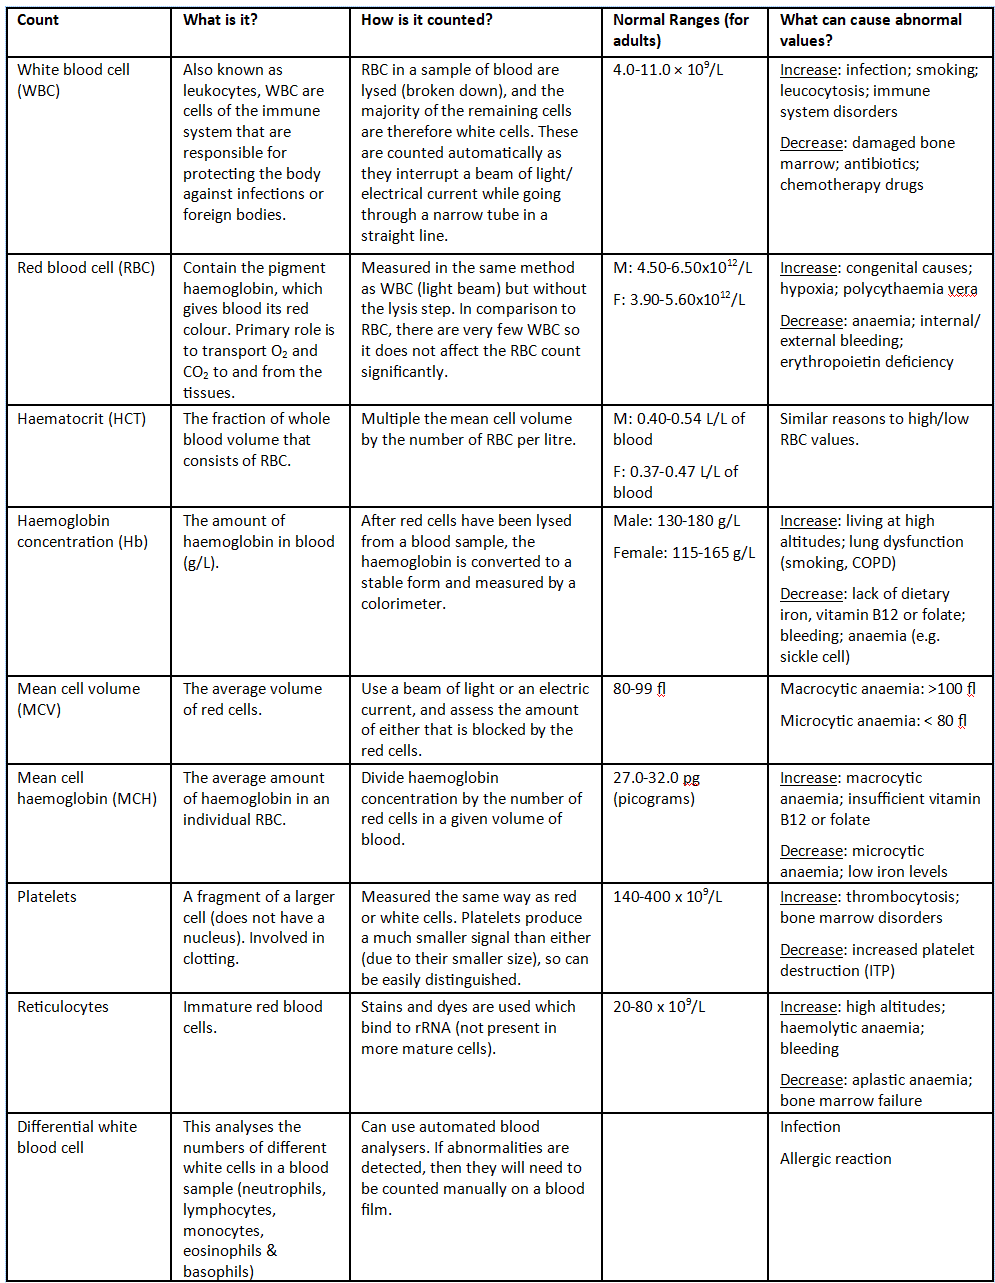
Figure 1: Shows what an FBC looks at, the normal ranges and what can cause it to increase or decrease
SimpleMed original by Dr. Keertana Anne and Dr. Tom Bradley
A blood film is made when the analyser flags:
- a result well outside the normal range;
- a large change from the patient’s previous result (even within the normal range); or
- abnormal cells (cells that look immature or that the analyser cannot identify).
The exact criteria vary between laboratories, and a doctor can also ask for a blood film.
To create a blood film:
- Place a drop of the patient’s blood onto a glass slide and spread it into a thin film. In the thin part of the film, the cells lie in a layer only one cell thick (a monolayer). This allows the cells to be viewed much more clearly, as they are not distorted by other cells lying on top of or below them.
- Fix (preserve) the film with methanol (an alcohol) to keep the cells’ shape and structure (morphology) intact for staining, and to reduce the infection risk to the observer.
- Stain the film so that the cells can be seen clearly under the microscope. Use a Romanowsky-type stain (a dye mixture that colours the parts of the cells; examples are Wright and Giemsa). It contains methylene blue derivatives (blue dyes) and eosin (a pink dye).
Biomedical scientists review the blood film and any previous haematological results for that patient. If there are areas of concern, the blood film is then passed on to a haematologist (a doctor who specialises in blood diseases). The haematologist reviews it, adds any medical comments and can request further tests. Urgent findings are phoned through straight away to the doctor who requested the test or the team responsible for the patient’s care, rather than waiting for the routine report. An example is blast cells (very immature white blood cells that can point to acute leukaemia).
Terminology Used for Describing Red Blood Cells
Red blood cells are described by their size, colour and shape. For size, macrocytic means abnormally large, microcytic means abnormally small and anisocytosis means abnormal variation in size. For colour, normochromic means normal colour and hypochromic means paler than normal. For shape, poikilocytosis means abnormal variation in shape. Figure 2 shows each term with a drawing.

Figure 2: Different types of cells seen in blood films
SimpleMed original by Dr. Keertana Anne and Dr. Tom Bradley. All individual blood films hand drawn by Dr. Tom Bradley and Dr. Keertana Anne.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 15896
