

By Dr. Ethan Kavanagh and Dr. Maddie Swannack
Next Lesson - Autonomics of the Head and Neck
Core
The embryonic development of the head and neck begins around day twenty-two. Up to this point, there are no discernible facial features, but the head and neck region still makes up half of the length of the embryo.
A complex tissue system called the pharyngeal (or branchial) arches forms many of the structures of the head and neck, including components of the face, jaws, neck and ears (the outer ear and the small bones of the middle ear). The eyes and nose are not pharyngeal arch structures. They develop from other tissues, including the sensory placodes (thickened patches on the surface of the embryo; the nasal placodes are described below). Each pharyngeal arch starts out with the same list of ingredients (a nerve, an artery, cartilage and muscle) but a different recipe (different development processes that turn them into different structures).
It would also be helpful to understand the anatomy of the gastrointestinal tract before reading this article. This is because the cranial part of the primitive gut tube (the early gut of the embryo) goes on to form the foregut (the front part of the gut tube). The foregut also contributes to a number of glands and other organs in the head and neck region, such as the thyroid, the parathyroids (small glands behind the thyroid that control calcium levels), the thymus and the palatine tonsils. The article ‘Development of the Gastrointestinal Tract’ covers the gut tube and the foregut.
The pharyngeal arches are a system of five pairs of mesenchymal proliferations (swellings of embryonic connective tissue) in the head and neck region. Although there are only five pairs, they are named one, two, three, four and six (in humans the fifth pharyngeal arch does not form, or regresses very soon after forming). The first pharyngeal arch is the largest and most cranial, with each new pair of arches getting smaller.
Each arch has a mesenchyme centre, an ectoderm outer covering (ectoderm is the outer layer of the early embryo), and an endoderm lining on the inside (next to the gut tube; endoderm is the inner layer of the early embryo). Each arch also has an associated artery, nerve, muscle and cartilaginous bar (a rod of cartilage) that form within it. The first arch has two discernible regions to it, named the maxillary and mandibular regions.
The recession between each arch on the inner side (the side lined with endoderm) is referred to as a pouch, and the recession between each arch on the outer side (the side lined with ectoderm) is referred to as a cleft.
Along with the pharyngeal arches, there is another structure named the frontonasal prominence; a single, unpaired structure that lies in front of (ventral to) the developing forebrain and forms the forehead and the bridge of the nose. Together, the frontonasal prominence (FNP) and five pairs of pharyngeal arches (PA) make up the developing elements in the head and neck region.

Diagram - The developing pharyngeal arches, along with their internal structure: each arch is associated with an artery, a nerve, cartilage and muscle
Creative commons source by Loki austanfell, edited by Dr. Maddie Swannack [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Nervous Derivative of the Pharyngeal Arches
There are a number of cranial nerves (CN) that are associated with the pharyngeal arches - CN V, VII, IX and X.
The trigeminal nerve (CN V) is associated with the first pharyngeal arch, and thus all derivatives of the first pharyngeal arch will be innervated by the trigeminal nerve. The same holds true for the second pharyngeal arch with the facial nerve (CN VII), the third pharyngeal arch with the glossopharyngeal nerve (CN IX), and the fourth and sixth pharyngeal arches with the vagus nerve (CN X).
Muscular Derivatives of the Pharyngeal Arches
As covered in the article ‘Fascial Planes, Muscles and Triangles’, there are two groups of muscles in the face: the muscles of facial expression and the muscles of mastication (the chewing muscles).
The muscles of mastication are derived from the first pharyngeal arch (explaining why they are innervated by the mandibular branch of the trigeminal nerve). The muscles of facial expression are derived from the second pharyngeal arch (fitting with their innervation from the facial nerve).
The third pharyngeal arch gives rise to the stylopharyngeus muscle, which acts to elevate the larynx and pharynx, and it is the only muscle in the pharynx innervated by the glossopharyngeal nerve.
The fourth pharyngeal arch is the origin of cricothyroid (which tenses the vocal cords), levator palatini (which lifts the soft palate) and the constrictors of the pharynx (the muscles that squeeze food down the throat). Finally, the sixth arch is where the intrinsic muscles of the larynx (the muscles inside the larynx that move the vocal cords), except cricothyroid, originate. All of these muscles are innervated by the vagus nerve because this is the cranial nerve associated with the fourth and sixth pharyngeal arches.
Cartilage Derivatives of the Pharyngeal Arches
The cartilage bars in each pharyngeal arch give rise to many of the skeletal elements (the bones and cartilages) of the head and neck. Just like the pharyngeal arch, the pharyngeal cartilages decrease in size moving cranial to caudal. The first and second are large enough to get their own names.
Meckel’s cartilage comes from the first pharyngeal arch. This gives rise to the malleus and incus (two of the three ossicles, the tiny bones of the middle ear), as well as the template used for the mandible.
Reichert’s cartilage is the name of the second pharyngeal cartilage, supplying the stapes (the third middle ear ossicle) along with the upper part of the hyoid bone (the U-shaped bone in the front of the neck, just above the larynx).
The remainder of the hyoid bone is derived from the third pharyngeal cartilage. Pharyngeal arches four and six contribute to the cartilages of the larynx.
Arterial Derivatives of the Pharyngeal Arches
Before any major developmental processes take place, the arterial derivatives of the pharyngeal arches are essentially symmetrical and well structured. However, a number of shunts (new routes for blood to flow) are needed for the embryo to continue to develop, so remodelling must take place.
The arteries of the first two pharyngeal arches largely regress. First-arch remnants contribute to the maxillary artery; the second arch gives rise to hyoid and stapedial arteries (small arteries named after the hyoid bone and the stapes), which mostly regress during development.
The third pharyngeal arch contributes to the common carotid artery and the proximal internal carotid artery (on both sides of the midline).
The fourth pharyngeal arch forms the arch of the aorta on the left and the proximal part of the right subclavian artery on the right.
The sixth pharyngeal arch gives rise to the pulmonary arteries and, on the left, the ductus arteriosus (a fetal blood vessel that lets blood bypass the lungs).
Summary of the Pharyngeal Arches
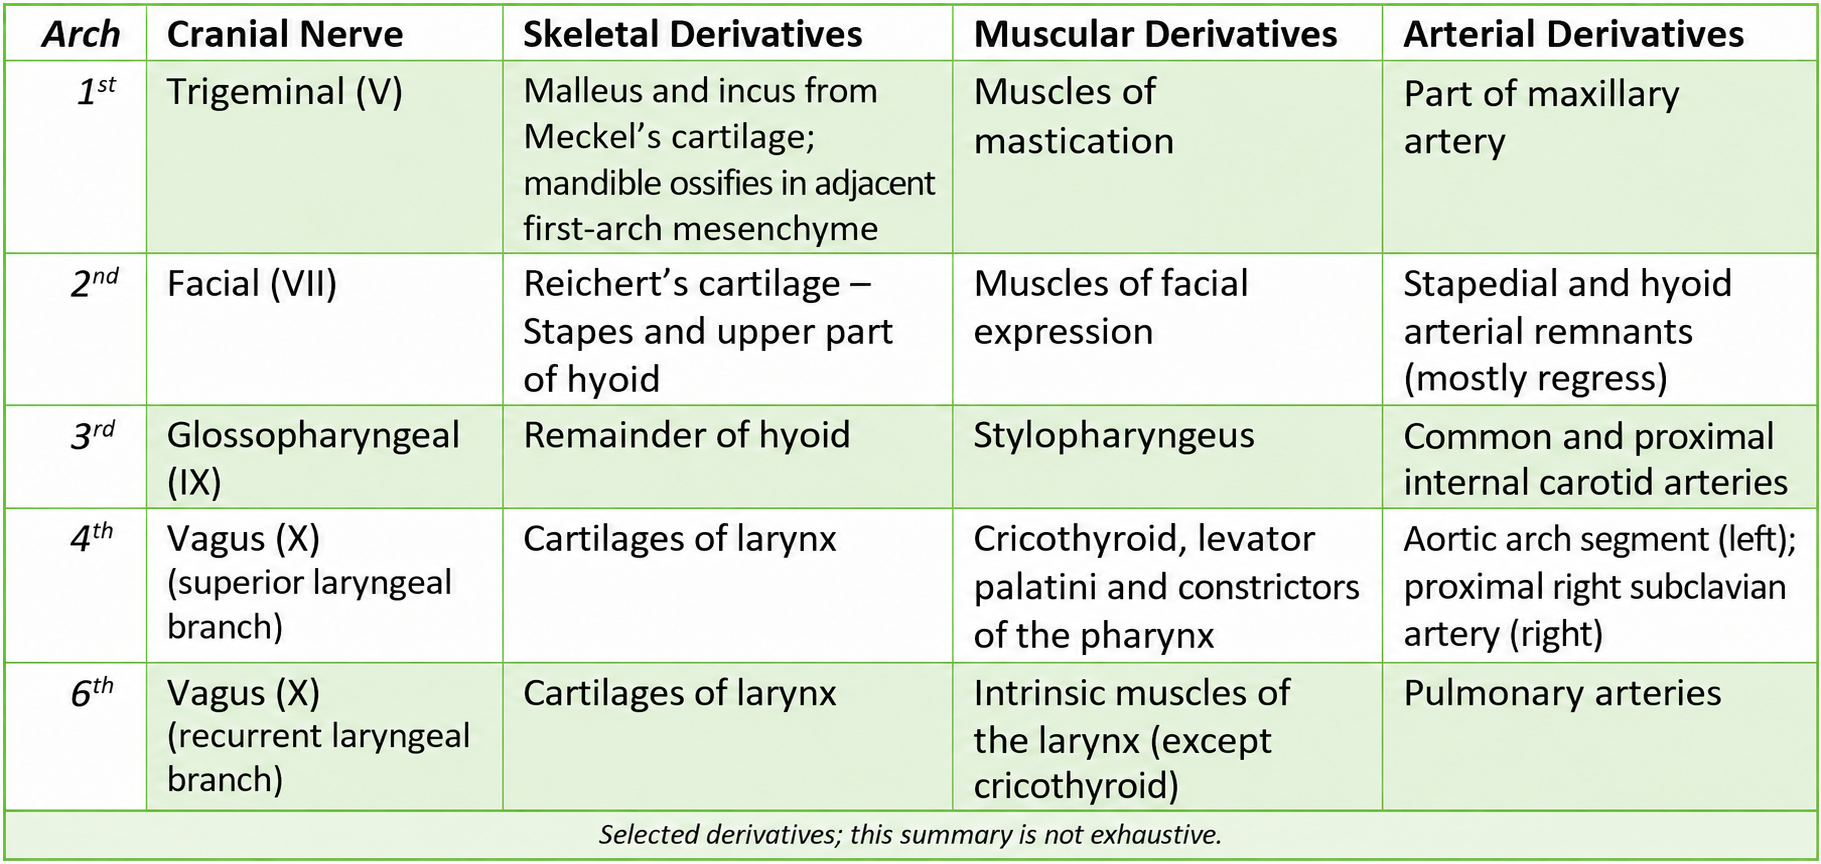
Table - Selected derivatives of the pharyngeal arches; this summary is not exhaustive. Most first- and second-arch arterial tissue regresses, with the selected remnants shown. Nerve labels indicate embryonic arch associations rather than a complete map of adult motor branches. Sources: UNSW head development; pharyngeal arch derivatives; human mandibular development.
As mentioned above, the pharyngeal pouches are the inner spaces between the pharyngeal arches that form pockets of endoderm in the pharynx.
As with the arches, the first pouch is the biggest, and ultimately becomes the tympanic cavity (the middle ear cavity, the space where the ossicles sit) and the pharyngotympanic tube (the Eustachian tube, which connects the middle ear to the pharynx).
Moving caudally, the palatine tonsils (in combination with some lymphoid cells, which are immune cells) originate from the second pharyngeal pouch. The thymus (one lobe from either side fusing together) and the inferior parathyroid glands develop from the third pharyngeal pouch. The superior parathyroid glands develop from the fourth pharyngeal pouch. The parathyroid glands are small glands behind the thyroid that control calcium levels.
Normally, only the first cleft remains as the external acoustic meatus (the ear canal). The remaining clefts are obliterated (closed off) when the second pharyngeal arch grows down over them.
On occasion, a cleft is not fully obliterated and leaves either a branchial cyst (an enclosed, fluid-filled remnant) or a fistula (an abnormal channel that opens onto the skin of the neck; in a complete fistula it also opens inside the throat, for example near the tonsil). A branchial cyst typically presents as a painless swelling at the side of the neck. A fistula typically presents as discharge from a small opening in the skin. Neck lumps are explained in the article ‘Lymph Nodes and Neck Lumps’.
The key components for the development of the face are:
- The frontonasal prominence
- Two maxillary prominences (one from each side)
- Two mandibular prominences (one from each side)
The stomodeum also contributes to the development of the face. This is a shallow depression on the outside of the embryo that will form the mouth. At first, the buccopharyngeal membrane (a thin plate, also called the oral membrane) separates it from the foregut. When this membrane ruptures, the mouth opens into the gut tube.
These components will then form the following features:

Table - The facial features that develop from each facial prominence. Note: in this table the sides of the nose are listed under the maxillary prominence, but they develop from the lateral nasal prominences (described below), which arise from the frontonasal prominence.
Development of the Nose and Palate
Before discussing the development of the nose, the term placode needs to be introduced. Placodes are ectodermal thickenings that form in the cranial region of the embryo on either side of the frontonasal prominence. They will differentiate and develop to form the special sensory structures of the nose.
The nasal placodes then invaginate (fold inwards) to form the olfactory pits, which will go on to become the nostrils. The olfactory pits lie dorsal to the stomodeum, separated from it by the oronasal membrane. This membrane will eventually rupture to form the primitive choanae (the openings between the nasal cavity and the pharynx). The oral and nasal cavities are separated later by the developing palate.
During development, a horseshoe-shaped ridge forms around the olfactory pits, with the ‘arms’ of the horseshoe being the medial and lateral nasal prominences. The maxillary prominences grow towards the midline and push the medial nasal prominences together. The medial prominences fuse together at the midline, forming the intermaxillary segment (the central piece of the upper lip and jaw). This creates the philtrum of the upper lip (the groove between the centre of the nose and the upper lip) and the primary palate (a small structure just internal to the medial prominences). On each side, the maxillary prominence then fuses with the medial nasal prominence, which joins the side of the upper lip to the middle.
Internally, two palatal shelves (shelf-like outgrowths) grow from the internal side of the maxillary prominences. As they grow, they fuse at the midline with each other, and with the primary palate, forming the secondary palate and separating the oral and nasal cavities.

Diagram - The ventral (front) surface of the embryo with the developing face. The most important parts to note are the medial and lateral nasal prominences (also called processes), the olfactory pits and the maxillary prominence
Public Domain Source by Henry Gray: Anatomy of the Human Body (20th edition) [Public domain]
Like any other process in the human body, separation of the nasal and oral cavities can go wrong. Specifically:
- Lateral Cleft Lip - failure of fusion of the medial nasal prominence and maxillary prominence unilaterally (can also extend into the primary palate/intermaxillary segment).
- Cleft Lip and Palate - failure of fusion involving the medial nasal prominence and maxillary prominence, with failure of the palatal shelves to meet in the midline as well.
- Cleft Palate on its own - failure of the palatal shelves to meet in the midline, with an intact upper lip.
These defects are usually surgically repaired: a cleft lip at about 3 to 6 months of age and a cleft palate at about 6 to 12 months. The child is cared for by a specialist NHS cleft team. Their care plan includes feeding support (for example, advice on positioning the baby at the breast, or a special type of bottle). Speech and language therapists monitor the child’s speech and language development throughout childhood and help with any problems.
Development of the Pituitary Gland
The pituitary gland is made up of two parts (lobes), the anterior and posterior pituitary, which develop from two different tissue types.
The first is ectoderm, which grows as a protrusion upwards from the roof of the mouth. This protrusion is called Rathke’s pouch and will go on to develop into the anterior pituitary gland. As the skull develops and the roof of the mouth forms, the connection between the pituitary gland and the mouth is pinched off.
The second is neuroectoderm (ectoderm that forms the nervous system), which grows as a protrusion downwards from the diencephalon (the part of the forebrain that includes the thalamus and hypothalamus) of the developing brain. This protrusion is called the infundibulum and will develop into the posterior pituitary gland.
The tissue type that each lobe develops from helps to explain how it works in adult life. The anterior lobe develops from ectoderm and makes its own hormones, so it has an endocrine function. The posterior lobe develops from neuroectoderm. It is made of the nerve endings of cells in the hypothalamus, and it releases the hormones that those cells make, so it has a neuroendocrine function (hormones released from nerve cells).
The precursor to the tongue appears on the floor of the oral cavity in the fourth week, before the palate begins to form (see above; the palate starts to form between the sixth and eighth weeks). Unlike most of what has been discussed above, the tongue does not derive from one pharyngeal arch, but is composed of elements from the first four arches to create a single, midline structure. These arches form the lining (mucosa) of the tongue. Its muscles come from the occipital somites (paired blocks of embryonic tissue near the back of the head) and are supplied by the hypoglossal nerve (CN XII), which is not a pharyngeal arch nerve.
A number of changes occur on the floor of the oral cavity during the formation of the tongue.
Two lateral lingual swellings arise from tissue of the first pharyngeal arch. Three median lingual swellings (the tuberculum impar, copula and epiglottal swelling) also appear, and these arise from a combination of the first to fourth arches.
During the fourth week of development, the lateral lingual swellings overgrow the tuberculum impar and fuse together, with their line of fusion being the median sulcus (the groove down the middle of the tongue).
The third arch part of the copula overgrows the second arch part and forms the back (posterior third) of the tongue. The anterior two-thirds of the tongue (from the first arch) and the posterior third then fuse, with their line of fusion marked by a V-shaped groove (the terminal sulcus), at the centre of which is the foramen caecum. This pit represents the origin of the thyroid gland.
The tongue forms at the floor of the oral cavity. Through programmed cell death (apoptosis), it is freed from the floor, leaving the lingual frenulum (the fold of tissue under the tongue) as the only attachment. If this frenulum is too short, the resulting condition is called ankyloglossia, or ‘tongue tie’.
The innervation (nerve supply) of the tongue is quite complex, because its parts come from different sources:
- Motor innervation is provided by the hypoglossal nerve (CN XII).
- General sensory innervation is provided by the lingual branch of the trigeminal nerve (CN V) in the anterior 2/3, and the glossopharyngeal nerve (CN IX) in the posterior 1/3.
- Special sensory innervation (taste) is provided by the chorda tympani branch (a branch that runs through the middle ear) of the facial nerve (CN VII) in the anterior 2/3, and the glossopharyngeal nerve (CN IX) in the posterior 1/3.
Development of the Thyroid Gland
The primordium (the earliest group of cells) of the thyroid gland begins on the floor of the oral cavity between the tuberculum impar and the copula, at the site of the future foramen caecum.
This developing thyroid tissue splits to form a bilobed diverticulum (a two-lobed outgrowth) which then descends through the embryonic neck. The lobes of the thyroid are connected by the isthmus (a narrow bridge of thyroid tissue).
During its descent, the thyroid is still connected to the tongue by the thyroglossal duct (a narrow tract linking the thyroid to the tongue). Once the thyroid migrates, this duct should close. If the duct does not close completely, thyroglossal duct cysts (fluid-filled lumps in the midline of the neck) can form.
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 8708

