

Next Lesson - Iron Metabolism
Core
Vitamin B12, also known as cobalamin, is a nutrient required for DNA synthesis. It is essential for the formation of red blood cells. It is primarily found in foods of animal origin, such as meat, fish, eggs, and cheese. It can also be obtained from fortified foods (foods with B12 added) and supplements. B12 is not found naturally in foods such as fruit, vegetables and grains, so people on vegan diets are at risk of deficiency. They need a reliable source, such as supplements or fortified foods, to maintain normal levels. Fortunately, there are reserves available in the liver that can sustain the body for 2 to 5 years. This means that after a change to a diet lacking B12, symptoms of deficiency can take a long time to appear. People who eat meat, fish or dairy foods usually get enough B12 from their diet.
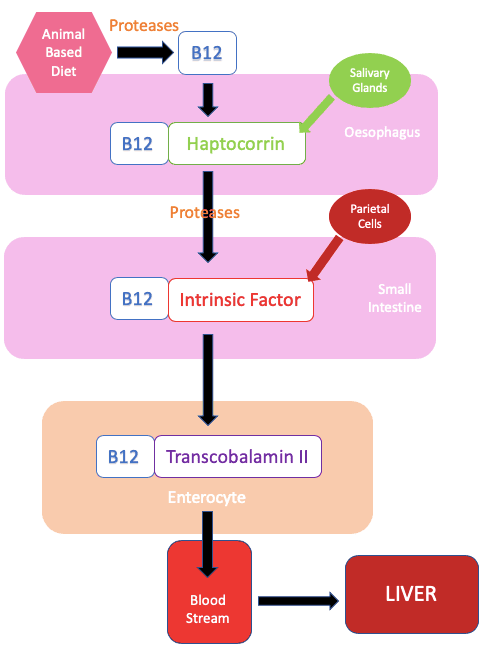
Diagram: The absorption pathway of vitamin B12. The first two steps happen in the stomach, not the oesophagus: gastric acid frees B12 from food, and B12 then binds to haptocorrin.
SimpleMed original by Dr. Tom Bradley
Gastric acid in the stomach releases B12 from the protein in meat. To be absorbed, free B12 must bind to haptocorrin (also known as transcobalamin-I), a protein secreted from the salivary glands. This B12-haptocorrin complex passes from the stomach into the duodenum (the first part of the small intestine). There, pancreatic proteases (enzymes that break down proteins) digest the haptocorrin and free the B12. The B12 then forms a new complex with a glycoprotein (a protein with sugar chains attached) called intrinsic factor. Intrinsic factor is secreted from parietal cells (the acid-secreting cells of the stomach lining). This B12-intrinsic factor complex is very important. It binds to receptors in the terminal ileum (the last part of the small intestine) and is then internalised (taken up) by enterocytes (the absorbing cells lining the small intestine). Once inside the enterocyte and released from the intrinsic factor, the B12 forms a new complex with transcobalamin II (a B12 transport protein). This B12-transcobalamin II complex is then released into the bloodstream where it reaches target tissues with the corresponding transporters, notably the liver.
B12 is needed for two key reactions. The first is the methyl group transfer (a methyl group is a carbon atom with three hydrogens attached) from methyltetrahydrofolate (methylTHF, see below) to homocysteine (an amino acid). This reaction forms methionine (another amino acid) and regenerates tetrahydrofolate (THF), which is needed to make thymidine, a building block of DNA. The second converts methylmalonyl-coenzyme A (CoA) to succinyl-CoA (molecules formed when some fats and amino acids are broken down). Without B12, methylmalonyl-CoA builds up and abnormal fatty acids are built into nerve lipids (fats). This leads to poor myelin formation (myelin is the fatty sheath around nerve fibres).
B12 can become deficient in a number of ways:
- Insufficient intake - through a poor or vegan diet.
- Insufficient absorption - this could be due to a number of things:
- Lack of intrinsic factor - this could be due to a gastrectomy (removal of all or part of the stomach) or an autoimmune disease resulting in destruction of parietal cells. The latter is known as pernicious anaemia (the most common cause of vitamin B12 deficiency in the UK).
- Disease of the ileum - Crohn’s disease (long-term inflammation of the gut) or an ileal resection (surgical removal of part of the ileum) reduces absorption of the B12-intrinsic factor complex.
- Insufficient transcobalamin - a congenital deficiency can prevent B12 from entering the target cells. This means there is a deficiency despite there being sufficient B12 in the blood.
- Drugs - some medicines, such as metformin (a diabetes drug) and proton pump inhibitors (acid-reducing drugs), can lower B12 levels. Recreational use of nitrous oxide (laughing gas) can also cause deficiency, because it inactivates B12.
Vitamin B12 deficiency is associated with neurological disease and can cause a serious condition called subacute combined degeneration of the spinal cord (damage to the dorsal and lateral columns of the spinal cord). Subacute combined degeneration commonly presents with numbness and tingling (paraesthesia), weakness, unsteadiness (ataxia) and difficulty walking. Without early treatment, the nerve damage can be permanent.
Folate (Vitamin B9) is required for DNA synthesis. Its active form is tetrahydrofolate (FH4, also written THF). Unlike B12, it is found in both animal-based foods and vegetables, particularly green leafy vegetables. The body’s folate stores last about 4 months, so a good dietary supply is key. Folate is absorbed mainly in the duodenum and jejunum (the first and second parts of the small intestine). It reaches the blood mainly as methyltetrahydrofolate and is carried in the portal vein to the liver.
Folate levels can become deficient in a number of ways:
- Insufficient intake - not enough folate in the patient’s diet.
- Excessive demand - situations such as pregnancy and increased erythropoiesis (red blood cell production) can cause shortages. Exfoliative skin diseases (conditions in which the skin peels widely) and haemolytic anaemias (anaemias in which red cells break down early) can also increase the use of folate.
- A lack of tetrahydrofolate (THF) - some drugs such as methotrexate (used to treat some cancers and inflammatory conditions) can inhibit the enzyme dihydrofolate reductase (the enzyme that regenerates tetrahydrofolate in the folate pathway). This creates a functional folate deficiency as folate is unable to be used.
- Duodenal and jejunal disease - coeliac disease (an immune reaction to gluten that damages the lining of the small intestine) is a well-recognised cause of folate malabsorption. Crohn’s disease can also reduce the absorption of folate from the diet.
Note that a folate deficiency in pregnancy increases the risk of neural tube defects (such as spina bifida) in the fetus. People who are trying for a baby, or could get pregnant, are advised to take a 400 microgram folic acid supplement (folic acid is the synthetic form of folate) daily until they are 12 weeks pregnant. Women at higher risk of a neural tube defect (for example after an earlier affected pregnancy, or with diabetes, or taking some epilepsy medicines) are advised to take a higher dose of 5 mg daily.
You should always check vitamin B12 levels in any patient with a folate deficiency, before starting treatment. This is because folic acid can correct the anaemia and so hide (mask) an underlying B12 deficiency, while nerve damage from the B12 deficiency carries on.
Tetrahydrofolate is a key molecule in metabolism as it is a one-carbon carrier, picking up single carbon units in several forms (for example methyl, methylene and formyl groups, which are carbon atoms with different numbers of hydrogen and oxygen atoms attached). The form carrying a methyl group is methyltetrahydrofolate (methylTHF). The collection of folate molecules carrying carbon units is known as the one-carbon pool. Once carbon units are attached, folate can pass them on in many reactions, the most important of which is thymidine synthesis. Thymine is one of the 4 bases used to form DNA. It is built into DNA as thymidine (the thymine base joined to a sugar), so thymidine synthesis is vital.
B12 and folate work together: B12 takes the methyl group from methylTHF, forming tetrahydrofolate. Without this step, tetrahydrofolate is not regenerated and thymidine synthesis falls. This is why a lack of vitamin B12 leads to a “functional” folate deficiency: the folate is trapped as methylTHF and cannot be used. This is known as the folate trap.
Vitamin B12 and folate deficiencies can lead to megaloblastic anaemia. When there is not enough thymidine, uracil (a base normally found in RNA, not DNA) is added to DNA instead. DNA repair enzymes recognise the uracil as a wrong base and remove it. Removing the uracil leaves nicks (small breaks) in the DNA chain, and two opposing nicks can break the chromosome. Although the nucleus cannot mature properly due to the lack of DNA, the cytoplasm is unaffected so it matures at a normal rate. Overall the nucleus and cytoplasm develop out of step, which is called being asynchronous. This leads to characteristic megaloblastic cells: large cells with open chromatin (an immature nucleus) and a cytoplasm that is more mature than the nucleus.
Investigations usually show a low haemoglobin and a high MCV (mean cell volume, the average size of the red cells, above 100 femtolitres, a very small unit of volume). Either finding can be absent: a normal MCV does not rule out B12 deficiency, because nerve damage can occur with a normal MCV. Lactate dehydrogenase (an enzyme released from damaged cells) and bilirubin may both be high. This is because many developing red cells are destroyed in the bone marrow, which reflects a high rate of cell turnover. A blood film (a smear of blood examined under a microscope) typically shows oval macrocytes (large, oval red cells) and hypersegmented neutrophils (neutrophils with five or more nuclear lobes). The megaloblasts themselves are seen in the bone marrow and, in severe cases, in the blood. If megaloblastic anaemia is suspected, B12 and folate need to be tested together.
To treat vitamin B12 deficiency, patients are usually given intramuscular injections of hydroxocobalamin (a form of vitamin B12). If the deficiency is caused by diet alone, daily B12 tablets may be used instead. Oral folic acid (usually 5 mg daily for about 4 months) is given to resupply folate levels. It is given only once vitamin B12 deficiency has been excluded or treatment has been started, to avoid masking neurological disease. Dietary advice should also be given.
Edited by: Dr. Thomas Burnell andDr. Ben Appleby
Reviewed by: Dr. Marcus Judge
- 15872
