

All done here! Check out our other subjects!
Core
Case - an individual with a disease or condition of interest.
Control - an individual without a disease or condition of interest used as a comparison.
Exposure - a factor which is being studied to determine whether it affects disease development.
Epidemiology - The study of the distribution and determinants of health and disease in populations, and the application of this study to control health problems.
Random error - Variation in a study’s results that happens by chance alone. Every study has some. It makes results less precise (see Precision below), and it can be reduced by increasing the sample size (the number of people studied) or by reducing measurement error.
Systematic error - A consistent bias in the design, conduct, or analysis of a study that leads results away from the true value.
External validity - How far a study’s results can be applied (generalised) beyond the people studied, to the whole population and to other settings. It depends partly on how similar and representative the sample is to the whole population. For example, it can’t be assumed that because a group of all men acted a certain way, a mixed gender population would act the same.
Internal validity - how trustworthy the conclusions are for the people and conditions studied. It depends on the design, conduct and analysis controlling bias and confounding (a third factor that distorts the link between exposure and disease, see Confounder below) so that an observed association is not explained by systematic error or another factor. Comparable groups can help, but group similarity alone does not establish internal validity.
Recall error - Errors in recollection that can occur if studies are done retrospectively (looking back at events that have already happened).
Observer error - Errors in what the observer records because of their pre-conceived expectations. This is combated by blinding observers to which group is which.
Measurement error - Errors arising from inaccurate measurement, such as an instrument that has not been calibrated (set to read correctly), observer variation, or faulty equipment.
Accuracy - How close the data measured is to the true value.
Precision - How close points in a data set are to each other.
Prevalence, incidence and risk
The below use fictitious figures regarding lightning strikes in the UK. Any figures on asthma are derived from this source (a British Lung Foundation page with data for 2004 to 2012; if the link does not load, try the archived copy).
Prevalence - The proportion of people who have a disease at a given time in a population. Calculated by dividing number of cases by total population. E.g. about 8 million people in the UK have ever been diagnosed with asthma (many children grow out of it, so fewer are living with it now).
Incidence - Number of new cases of a disease within a certain time frame. The incidence rate is the number of new cases divided by the population years at risk (the years each person was at risk, added together; see Population years below). E.g. around 160,000 people a year in the UK receive a first diagnosis of asthma.
Incidence rate ratio - The ratio of the incidence rates of two groups, taking into account the person-time in each group (the total time that everyone in it was at risk).
Odds - The chance of someone getting the outcome (disease) versus not getting the outcome. Calculated by dividing cases by non-cases. For example, if 1264 people walk on hills during thunderstorms and 5 get struck by lightning, then 1259 are not struck. The odds are 5/1259 = 0.004, which is about 1 to 250. So for every 250 or so people who walk on a hill in a thunderstorm and are not struck, one is struck. Odds are not the same as risk (the proportion who get the outcome). Here the risk is 5/1264, which is also about 0.004, but only because the outcome is rare.
Odds ratio - A method of comparing the odds of an outcome (such as a disease) between two groups, for example an exposed group and an unexposed group. If the odds ratio is 1 there is no difference between the groups. For example, compare people walking on a clear day (unexposed: 1 struck by lightning out of 684, so 683 not struck) with people walking during a thunderstorm (exposed: 2 struck out of 832, so 830 not struck). The odds on the clear day are 1/683 = 0.0015. The odds in the thunderstorm are 2/830 = 0.0024. The odds ratio is 0.0024 / 0.0015 = 1.6 (rounded). As the odds ratio is greater than 1, there is a positive association between thunderstorms and lightning strikes in these made-up figures. With only 3 strikes in total, chance could easily explain this.
Absolute risk - The probability of developing a disease over a specified period of time in a defined population.
Relative risk - Ratio of the absolute risks of two groups. For example ‘you are twice as likely to get hit by lightning in Scotland than in England’ (made-up figures). This statement can be misleading however as the absolute risk may be very small e.g. 5 cases of lightning strikes in England vs 10 in Scotland (in populations of the same size). Although it is true in this example to say you are twice as likely to get struck, the absolute risk is in fact very low.
Risk difference - Difference between the absolute risk data for two groups. Using the above example the risk difference would be 5 extra cases, which sounds much less dangerous than 2x more likely.
Confounder - A factor that affects the independent variable (exposure) and the dependent variable (disease) and distorts the relationship between them. These cannot always be known about or adjusted for (though it should be attempted).
Standardisation - A method of adjusting for confounding variables to minimise their effects.
Retrospective - When a study occurs now, looking at exposures in the past and current disease state.
Prospective - When a study begins now, identifies people (exposed and unexposed) and follows them forward in time to see who develops the disease.
Population years (also called person-years) - The years at risk of each member of the population all added together, e.g. if ten factory workers were exposed for five years each, the population years would be 50 years.
Inverse Care Law - The availability of good healthcare tends to vary inversely with the need for it: the people who most need care are the least likely to get it (named by the GP Julian Tudor Hart). Resources are more easily available to the more affluent in society. This reinforces the inequity (unfairness) that already exists in the healthcare system.
Inequality Paradox - A population-wide intervention (one aimed at everyone) can widen health inequalities, because people who are more affluent are better able to take it up and benefit from it. The most needy can therefore miss out, e.g. they might find it harder to take time off work to use a service if they are on inflexible shift work.
Proportionate Universalism - providing services to everyone while increasing their scale or intensity according to need or disadvantage. Universal provision alone, such as the same child benefit or school-meal entitlement for everyone, does not establish proportionality. Additional support for those facing greater barriers is needed to make provision proportionate. Simple access arrangements can reduce barriers, but universal availability does not guarantee equal uptake or benefit.
First Order Problem Solving - Immediate solving of the problem with a quick fix that won’t solve the problem long term.
Second Order Problem Solving - Slower forms of problem solving that find and remove the root cause of the problem; this takes longer initially, but the problem is less likely to come back.
Moral Individualism - A self-centred approach to problems that doesn’t help the greater good. An example of this is to say that a person who smokes is self-centred, because they care more about the five minutes they get to themselves when they have a cigarette than the effects it would have on their family if they got lung cancer.
James Reason's Framework of Error
- Active Failures - Unsafe acts by people in direct contact with the patient or system, which have a direct and usually short-lived effect on the safeguards (defences) that protect patients, e.g. slips, lapses, mistakes and procedural violations.
- Latent Failures - Any aspect of context that makes active failures more likely, e.g. poor supervision, lack of checks, poor training.
Screening Test Terms
Positive Predictive Value - The probability that someone who tested positive actually has the disease, but it also varies with the condition’s prevalence: when prevalence is low, many positive results are false positives.
Negative Predictive Value - the probability that someone with a negative test result does not have the target condition. Its denominator (the number you divide by) is all people who test negative. It concerns the condition tested for, not general health, and varies with the condition’s prevalence as well as test performance.
Sensitivity - The proportion of people with the disease who test positive (proportion of true positives).
Specificity - The proportion of people without the disease who test negative (proportion of true negatives).
Case Control
Cases versus control, using past exposure.
E.g. Asthma versus not asthma, using past mouldy house as the past exposure.

Table - Cases vs Controls in exposed and unexposed circumstances
SimpleMed original by Dr. Maddie Swannack
Odds of exposure in cases = a/c (exposed cases divided by unexposed cases)
Odds of exposure in controls = b/d (exposed controls divided by unexposed controls)
Odds ratio = a/c divided by b/d = ad/bc
Issues: selection bias (cases or controls are chosen in a way that distorts the comparison), recall bias (cases and controls remember past exposures differently, see Recall error above), confounding, random error.
Cohort
Exposed versus unexposed now, investigate future cases - prospective.
Exposed versus unexposed in the past, with outcomes that have already happened found from existing records - retrospective.
Person years at risk = years that each person in a population has been at risk all added together.
Incidence rate (IR) of exposed = number of new cases of the outcome in the exposed / person years at risk.
Incidence rate ratio = IR exposed / IR unexposed = how much more likely the disease is to occur with the exposure.
Issues: loss to follow up (people drop out, and if those who leave differ from those who stay the results are distorted: attrition bias), observer bias (the person recording outcomes is influenced by what they expect, see Observer error above), confounding, random error.
Cross Sectional
Find cases right now in the population - this is a snapshot.
An example is a survey in 2001 that found 250,000 cases of asthma and a separate survey in 2011 that found 300,000 cases (fictitious figures). Each survey is its own snapshot, and a prevalence needs the total population surveyed as well as the number of cases.
Prevalence = number of people with disease / total population. A cross sectional study counts existing cases at one point in time, so it gives prevalence, not absolute risk.
Issues: sampling bias (the sample is not representative of the population), participant bias (people who take part differ from those who do not), random error.
Ecological
Look at whole population, separate by a characteristic (usually geographical), look at cases in each group.
E.g. difference in cases of asthma at different distances from a road.
Issues: the ecological fallacy (a pattern seen across groups may not hold for the individuals in them), characteristics may be unclear, confounding variables, lack of generalisability (depending on sample size), random error.
Confidence Intervals
For case control and cohort studies:

Figure - The equations used to work out the error factor and the confidence intervals of cohort and case control studies
SimpleMed original by Dr. Maddie Swannack
For cross sectional studies:
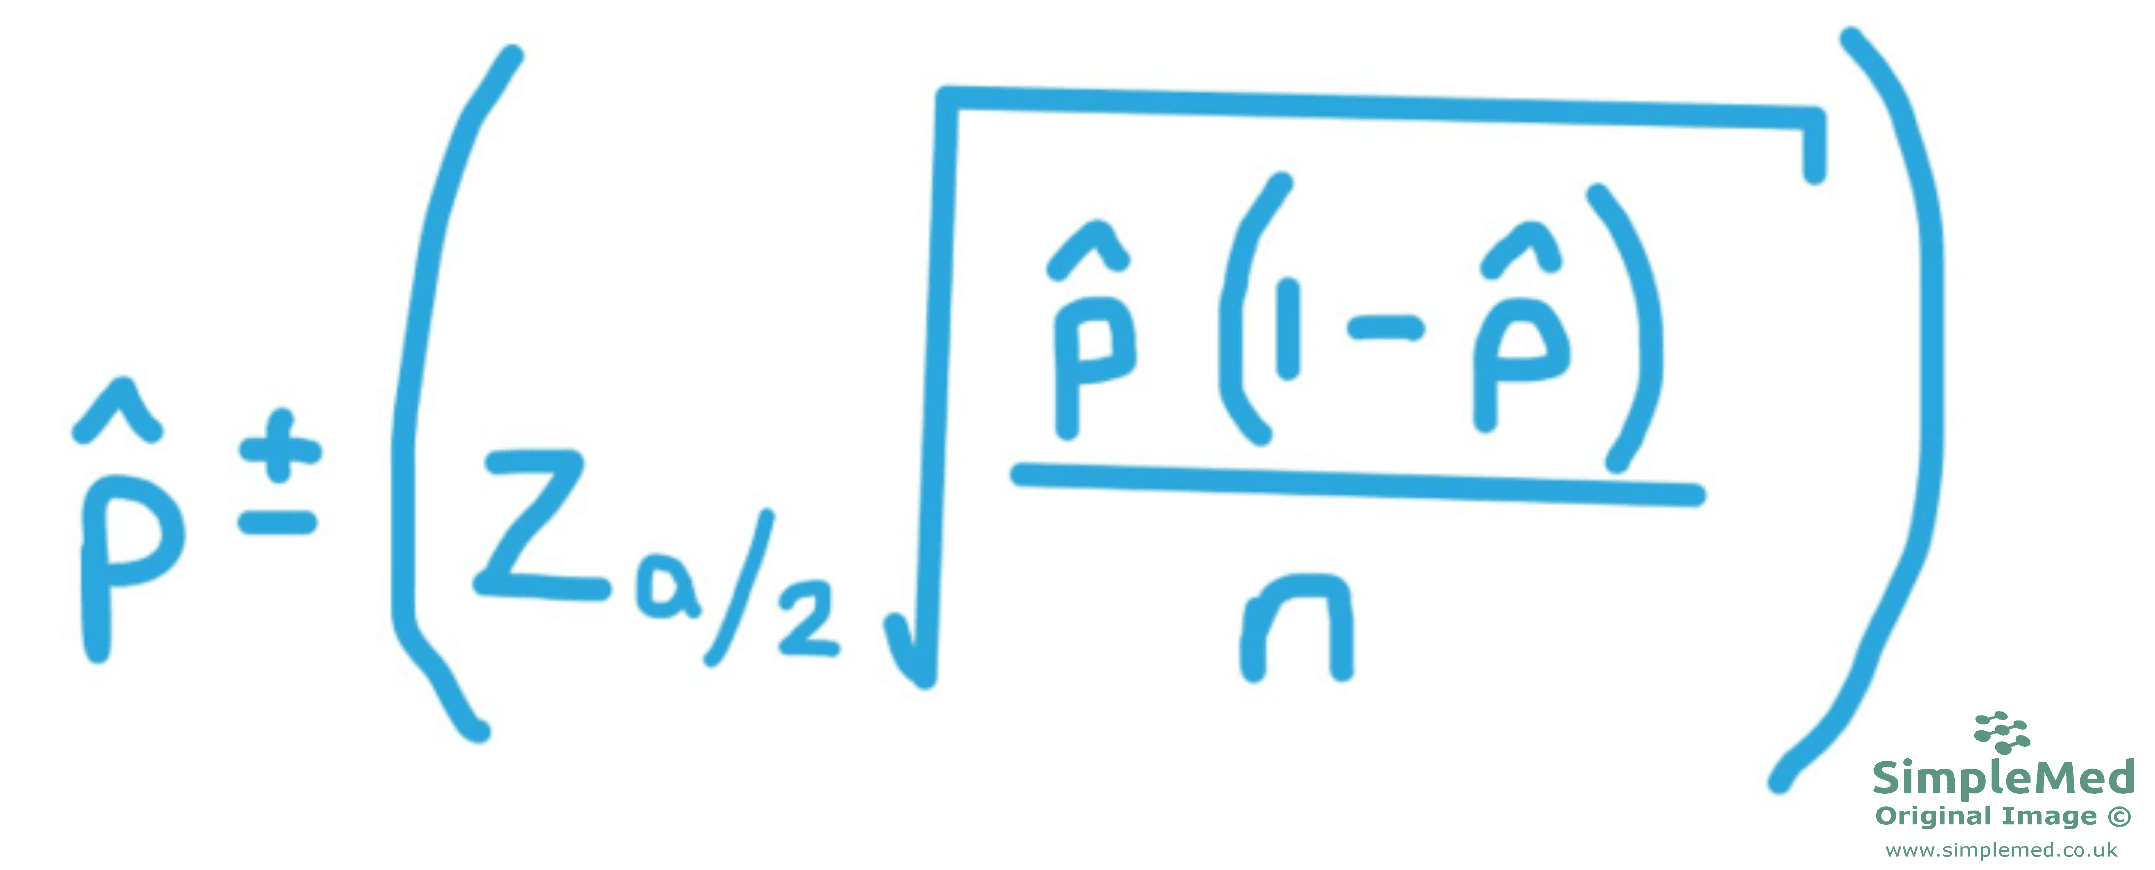
Figure - The equation used to find the confidence interval of a cross sectional study
SimpleMed original by Dr. Maddie Swannack
A 95% confidence interval is calculated by a method that, under its statistical assumptions, would include the true population parameter (the real value in the whole population, such as a mean or a ratio) in about 95% of intervals across repeated samples. For a particular calculated interval, the parameter is fixed; the 95% describes the method’s long-run coverage. The null value (the value that means no effect or no difference) is 1 for a ratio measure and 0 for a difference. If the 95% interval includes the relevant null value, the corresponding two-sided test (a test for a difference in either direction) at the 5% significance level does not reject the null hypothesis (the assumption that there is no effect), so the result is not statistically significant. A non-significant result does not prove that there is no association.
A confidence interval describes uncertainty in an estimated population parameter; it is not a range containing all individual observations. For the corresponding two-sided 5% test, an interval excluding the relevant null value indicates statistical significance. Interpret the estimated effect and the full interval as well as this threshold: statistical significance alone does not establish clinical importance or causation.
In practice, check whether the interval includes the null value (1 for ratios, 0 for differences).
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 5792
