

Next Lesson - Travel-related Infections
Core
An immunocompromised host is a patient whose immune system is unable to respond appropriately and effectively to infectious microorganisms. This is due to a defect in one or more components of the immune system.
A congenital defect in the immune system (one due to an intrinsic gene defect) is called primary immunodeficiency. An acquired defect (one that results from an underlying disease or treatment) is called secondary immunodeficiency.
Many different genetic defects can cause primary immunodeficiency: over 500 genes are now linked to inborn errors of immunity (the current name for these conditions). For this reason, primary immunodeficiency is often poorly recognised and diagnosed. Diagnosis is often delayed, sometimes for several years after the first symptoms, and a significant proportion of patients are diagnosed in adulthood. Delayed diagnosis can leave patients with permanent tissue and organ damage. Clinicians therefore need to be aware of primary immunodeficiency, so that they identify it early, prevent damage and improve the patient's prognosis and quality of life.
When should we suspect an Immunodeficiency?
The following mnemonic is often used as an initial guide when suspecting an immunodeficiency: SPUR
S- Severe: can the presenting complaint (the main problem the patient comes with) or the recurring infection be life-threatening if untreated?
P- Persistent: does not respond appropriately to conventional treatment?
U- Unusual: is the site of infection and type of microbe unusual? E.g. deep tissue infection, or an opportunistic microbe (one that rarely harms people with a healthy immune system)
R- Recurrent: does the patient have more infections than is usual for a healthy person of the same age?
If the history and features of infections a patient presents with show any of the features above, healthcare professionals should consider immunodeficiency.
Alternatively, the Jeffrey Modell Foundation Medical Advisory Board developed a series of 10 warning signs to recognise PID (Primary Immunodeficiency):
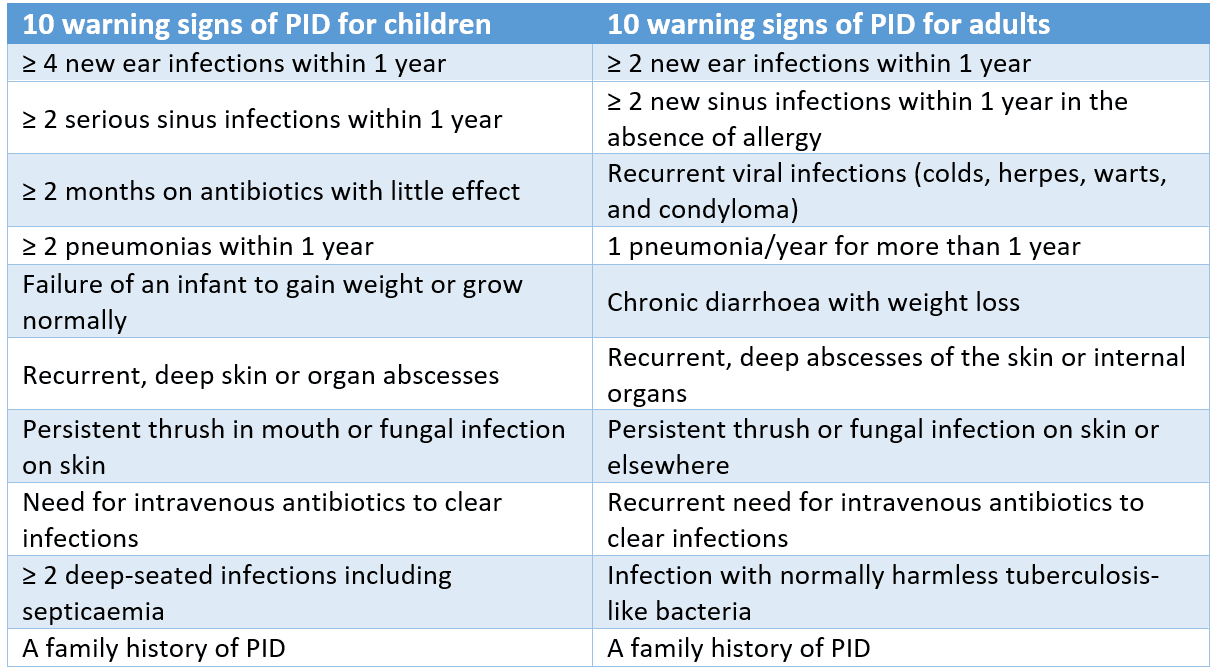
Figure: The 10 warning signs for PID in adults and children
SimpleMed original by Dr. Elena Perez
The 10 warning signs have a few limitations. They were developed by experts in the field of PIDs, but population-level evidence to support them is limited. A 2024 study of US electronic health records found that 33% of patients with an inborn error of immunity had two or more warning signs. Among matched controls (similar people without the condition), the figure was 3.1%. So about two thirds of the patients with an inborn error of immunity had fewer than two warning signs. It is also worth noting that some PID patients might have non-infectious manifestations such as autoimmunity, malignancy (cancer) or inflammatory responses to be aware of. Different types of PID carry different risks of particular cancers.
If immunodeficiency is suspected, the next step is to carry out some laboratory investigations to confirm the type of immunodeficiency:
- It is important to review the past medical history for any potential cause of secondary immunodeficiency, and to offer an HIV test (HIV is part of the differential diagnosis)
- Carry out a full blood count (FBC)
- Test humoral (antibody) immunity
- IgG, IgA, IgM (+/- IgE): the main classes of immunoglobulin (antibody)
- IgG1-4 subclasses, if total immunoglobulin levels are normal but an antibody deficiency is still suspected
- IgG levels to specific previous vaccines e.g. tetanus toxoid (the inactivated toxin used in the tetanus vaccine), measles, mumps, rubella
- Measure antibody in response to ‘test’ immunisation
- Test for cell-mediated immunity (immunity carried out by T cells rather than antibodies; T cells are lymphocytes, a type of white blood cell, that mature in the thymus)
- Lymphocyte count
- Lymphocyte subset analysis: counts of total T cells, helper T cells (CD4+), cytotoxic T cells (CD8+), natural killer (NK) cells and B cells (the lymphocytes that make antibodies), using an extended marker panel (a wider set of cell-surface markers)
- In vitro tests of T cell function (tests done in the laboratory, on cells in a dish or tube)
- Test for phagocytic cells (cells that engulf and destroy microbes, such as neutrophils and macrophages)
- Neutrophil count
- Neutrophil function tests e.g. oxidative burst (the release of reactive oxygen compounds that neutrophils use to kill microbes) for CGD (Chronic Granulomatous Disease)
- Adhesion molecule expression (testing for the surface proteins that let white cells stick to vessel walls and leave the blood), for LAD (Leukocyte Adhesion Deficiency)
- Test for complement (a group of blood proteins that help antibodies and phagocytes destroy microbes)
- Individual components
- Test of complement function (CH50 and AP50 measure the activity of the classical and alternative complement pathways)
- Definitive tests - molecular testing and gene mutations.
As mentioned above, the term primary immunodeficiency refers to congenital immunodeficiencies that are due to intrinsic gene defects. These can lead to a missing or non-functional protein, cell or other component of the immune system, making the immune system weak or dysfunctional.
The main immunodeficiencies that we will focus on are:
- Predominantly antibody deficiencies - account for roughly 50 to 65% of all PIDs, depending on the registry.
- Common variable immunodeficiency (CVID): the patient has B cells but they produce reduced or dysfunctional antibodies
- Bruton’s disease (X-linked agammaglobulinaemia, XLA): the gene is on the X chromosome, so almost all affected patients are boys (girls are usually carriers: they have the faulty gene but are usually well). The patients lack B cells so cannot produce antibodies
- IgA deficiency: the most common primary immunodeficiency. Most individuals are asymptomatic (have no symptoms). Prevalence is about 1 in 600 in white people, and estimates range from about 1 in 150 to 1 in 3000 depending on the population. These patients have an increased risk of autoimmune conditions.
- Hyper IgM: a defect in immunoglobulin class switching (B cells changing from making IgM to making IgG, IgA or IgE). IgG, IgA and IgE levels are low, while IgM is normal or raised. The X-linked form is caused by CD40 ligand deficiency (CD40 ligand is a protein on the surface of T cells that tells B cells to switch antibody class), a disorder of abnormal T- and B-cell function.
- Combined T and B cell deficiencies - represent around 15% of all PIDs and include severe combined immunodeficiency (SCID): as T cells are defective, B cells are not activated
- Phagocytic defects - responsible for about 10% of all PIDs. The most frequently diagnosed is chronic granulomatous disease (CGD), in which phagocytes lack killing machinery and are ineffective as a result
- Other cellular immunodeficiencies - make up 5-10% of all PIDs. The most common is DiGeorge syndrome (22q11.2 deletion syndrome: a deletion in a region on the long arm of chromosome 22). The thymus (the organ where T cells mature) is hypoplastic (underdeveloped) or, rarely, absent. T cell maturation may be incomplete (partial DiGeorge syndrome). It is absent only in complete DiGeorge syndrome, where there is no working thymus. This affects fewer than 1% of people with 22q11.2 deletion syndrome.
A way of differentiating between the different types of primary immunodeficiencies is by looking at the age of onset of first symptoms:
- Onset < 6 months old: most likely a T-cell or phagocyte defect.
- Onset between 6 months and 5 years old: suggests a B-cell/antibody or phagocyte defect (maternal antibodies have now cleared, so antibody defects become clear).
- Onset > 5 years old: most likely a B-cell/antibody/complement or a secondary immunodeficiency.
The type of microbe and the site of infection also help to identify the major immune defects, because specific presentations are associated with specific defects of the immune system:
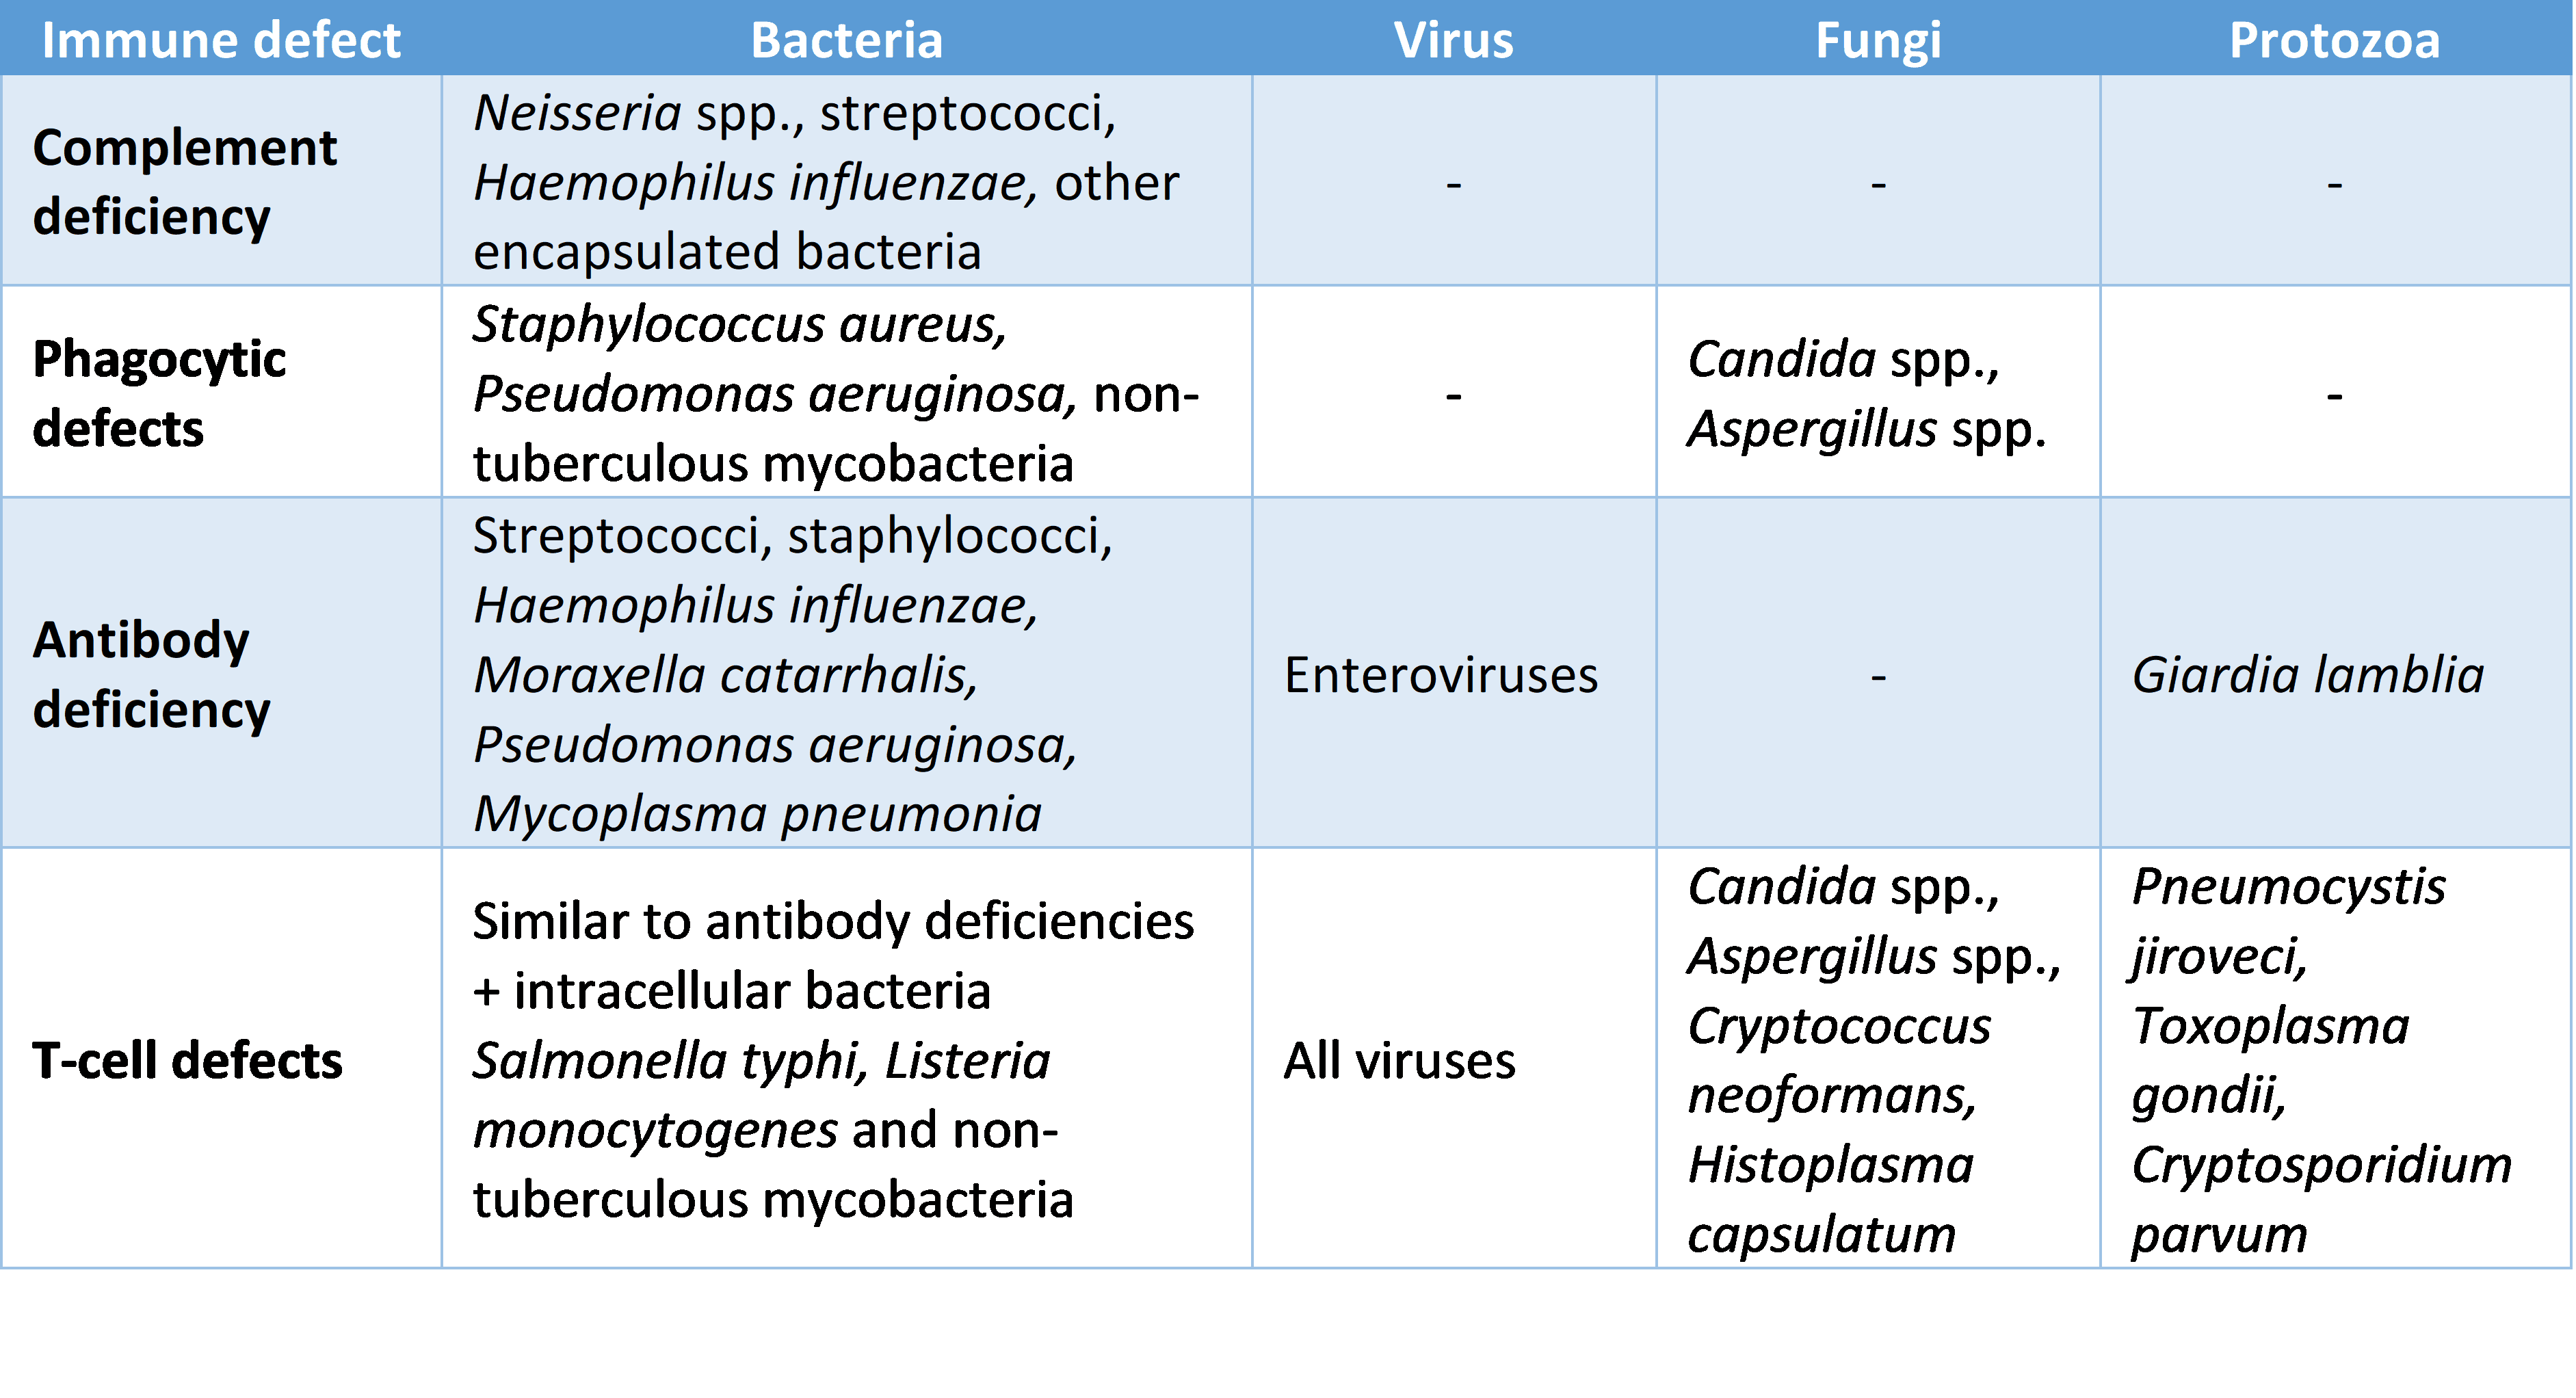
Figure: Infections associated with the different types of immune system defects
SimpleMed original by Dr. Elena Perez
Management of primary immunodeficiency diseases has three components: supportive treatment, specific treatment and management of any co-morbidities.
- Supportive treatment:
- Infection prevention: prophylactic antibiotics (antibiotics given to prevent infection)
- Treat infections promptly and aggressively, alongside immunoglobulin replacement where indicated
- Nutritional support: dietitian assessment of diet and growth, as these patients are at risk of malnutrition and of vitamin deficiencies, including low vitamin D
- In SCID, use irradiated and CMV-negative (cytomegalovirus-negative) blood products. Irradiation prevents graft-versus-host disease (donor T cells attacking the patient), and CMV-negative blood avoids passing on cytomegalovirus
- Avoid live attenuated vaccines (made from weakened living microbes, which can cause the disease they aim to prevent) in patients with severe PIDs (e.g. SCID)
- Specific treatment:
- Regular immunoglobulin therapy to replace missing antibodies: intravenous immunoglobulin (IVIg) or subcutaneous immunoglobulin (SCIg)
- SCID: haematopoietic (blood-forming) stem cell transplantation (HSCT). In a North American series of 240 infants transplanted from 2000 to 2009, five-year survival was 94% in infants transplanted at 3.5 months of age or younger, and 90% in older infants without prior infection
- Treat co-morbidities:
- Autoimmune and malignancy treatment if disease arises
- Assess organ damage (lung function assessment)
- Avoid non-essential exposure to radiation, especially in conditions with radiation sensitivity such as ataxia telangiectasia (an inherited condition that includes immunodeficiency and radiation sensitivity)
Secondary immune deficiencies are the result of extrinsic factors (factors outside the immune system) that decrease the production of immune components or increase their loss. A leading cause of secondary immunodeficiency worldwide is malnutrition. Other causes include infections (see article on HIV), liver diseases, lymphoproliferative diseases (conditions with excess lymphocytes, such as lymphoma) or asplenia (an absent or non-functioning spleen).
The spleen is an important organ of the immune system and by understanding its immune functions, one can easily understand how its removal or damage would contribute to secondary immunodeficiency. The spleen has an important role in:
- Removal of blood-borne pathogens: especially in dealing with encapsulated bacteria (bacteria with a protective capsule that makes them harder for phagocytes to engulf).
- Antibody production: during the acute phase response (the body's early reaction to infection) it produces IgM, and for long-term protection it produces IgG.
- Splenic macrophages: removal of opsonised microbes (microbes coated with antibody or complement so that phagocytes can ingest them) and of immune complexes (antibody bound to antigen).
Asplenic or splenectomised patients are therefore at risk of severe infection from encapsulated bacteria. These include Streptococcus pneumoniae, Haemophilus influenzae type b and Neisseria meningitidis. They are advised to take antibiotic prophylaxis, usually low-dose phenoxymethylpenicillin, for at least 2 years and often for life. They are also offered additional vaccines against pneumococcus and meningococcus (the pneumococcal, MenACWY and MenB vaccines) and an annual influenza vaccine. They should see a doctor as soon as possible if they have signs of infection, such as a high temperature. They are also advised to carry medical ID, such as a MedicAlert bracelet, to inform healthcare professionals in emergencies.
Similarly, patients with haematological malignancies (cancers of the blood and bone marrow) or who have undergone chemotherapy (drug treatment for cancer that also damages healthy dividing cells) are highly susceptible to infections. This susceptibility is due to chemotherapy-induced neutropenia (a low neutrophil count) and damage to mucosal barriers. Commonly used vascular catheters breach the skin and give bacteria a route into the body. Biofilms (layers of bacteria stuck to a surface and protected from antibiotics) can also form on them, which further increases the risk of infection. Any suspected neutropenic sepsis should be treated as a medical emergency and the patient should be given empirical (started before the cause is known) antibiotic therapy immediately.
Finally, any condition that results in an increased loss or catabolism (breakdown) of immune components can also cause secondary immunodeficiency. Some examples of such conditions include protein-losing diseases such as nephropathy (kidney disease that leaks protein into the urine) or enteropathy (bowel disease that leaks protein into the gut), and burns.
Examples of common manifestations of secondary immunodeficiency:
Shingles (herpes zoster) is caused by reactivation of the Varicella Zoster Virus (VZV) and is an example of a common infection in secondary immunodeficiency. Primary infection with VZV causes chickenpox, a vesicular (blistering) rash. The virus then remains latent (dormant) in sensory dorsal root ganglia (clusters of sensory nerve cells next to the spinal cord). Reactivation of latent VZV is more common in immunocompromised patients and causes shingles. Shingles is a painful, one-sided rash of vesicles (blisters) on red skin (erythema) that usually follows a dermatome (the area of skin supplied by one spinal nerve). It is treated with pain relief and antiviral drugs such as aciclovir, ideally started within 72 hours of the rash appearing. Patients who are severely immunocompromised need hospital admission (for intravenous aciclovir) or immediate specialist advice.
Candida albicans is known as an opportunistic pathogen: it is commonly found in the mouth and gut of healthy hosts, as part of the normal flora (the microbes that normally live there). However, in the immunocompromised, it can become pathogenic and overgrowth of the yeast can cause candidiasis. Oral candidiasis (thrush in the mouth) is common in HIV and is a recognised marker of immunosuppression, so it can be a sign that the infection is progressing towards AIDS.
Finally, Aspergillus is a group (genus) of fungi (moulds that spread by spores called conidia), with species that infect humans and crops. It is commonly found in samples taken from immunocompromised hosts. Aspergillus fumigatus is the most common organism causing aspergillosis. It primarily colonises paranasal sinuses and lungs, potentially leading to necrotising pneumonia. On high-resolution CT (HRCT) scans, the ‘halo’ sign (a ring of hazy, ground-glass change around a lung nodule) is highly suggestive of invasive pulmonary aspergillosis in the right clinical setting. It is not diagnostic on its own. Diagnosis also uses microbiological tests, such as galactomannan (a fungal antigen) and PCR (polymerase chain reaction, a test that detects the microbe’s DNA).
Edited by: Dr. Ben Appleby and Dr. Thomas Burnell
Reviewed by: Dr. Marcus Judge
- 10818
