

Next Lesson - Gastroenteritis and Enterocolitis
Core
Cancer of the oesophagus can be either squamous cell carcinoma (SCC, a cancer of the flat cells that line the oesophagus) or adenocarcinoma (a cancer of gland cells). In the UK, adenocarcinoma is the most common type and SCC is the second most common. SCC remains associated with smoking and alcohol exposure. Adenocarcinoma mainly affects the lower part of the oesophagus. It can develop from pre-malignant changes (changes that raise the risk of cancer) called Barrett’s Oesophagus. Barrett’s oesophagus occurs with chronic reflux disease (long-term backflow of stomach acid into the oesophagus). The stratified squamous epithelium (the normal lining, made of several layers of flat cells) undergoes metaplasia to simple columnar epithelium (a lining of a single layer of tall, column-shaped cells) to protect itself from the acid.
Risk factors for Barrett’s oesophagus matter because it increases the risk of oesophageal cancer. The risk is still small, and many people with Barrett’s oesophagus do not develop cancer. The risk factors include increasing age, male gender, abdominal obesity (extra fat around the waist) and acid reflux.
Smoking increases the risk of both main types of oesophageal cancer. Drinking alcohol increases the risk of SCC. Smoking and drinking together raise the risk of some oesophageal cancers more than either does alone.
The key presenting complaint of a patient with oesophageal cancer is dysphagia (difficulty swallowing).
Other red flag symptoms or signs (warning signs of serious disease, such as cancer) that may indicate oesophageal malignancy can be remembered by the acronym ALARM:
- A - Anaemia
- L - Loss of weight
- A - Anorexia (loss of appetite)
- R - Recent onset of progressive symptoms
- M - Melaena (black, tarry stools from bleeding higher in the gut) or Mass (a lump that can be felt)
NICE guideline NG12 advises a suspected cancer pathway referral (a referral for specialist assessment of possible cancer) for oesophageal cancer in people who have dysphagia. It also advises one for people aged 55 and over who have weight loss and any of upper abdominal pain, reflux or dyspepsia (indigestion).
Investigations for oesophageal cancer include blood tests (e.g. full blood count to check for anaemia) and endoscopy with biopsy (a camera test of the upper gut, with samples of abnormal-looking tissue taken and examined under a microscope). A CT scan of the chest, abdomen and pelvis is used to look for spread. Further staging tests (tests that show how far the cancer has spread) may include PET-CT (a CT scan combined with a scan that shows where cells are more active than normal), endoscopic ultrasound (an ultrasound probe on the end of an endoscope) and laparoscopy (a small operation to look inside the abdomen). NICE advises endoscopic ultrasound and laparoscopy only if they will help guide treatment.
Treatment may involve surgery if caught early, radiotherapy and/or chemotherapy. The prognosis for oesophageal is very poor.
Gastric cancer is most commonly an adenocarcinoma (a cancer that starts in gland cells). The stomach is lined by simple columnar epithelium, and its gland cells make mucus and stomach juices. Gastric cancer is described as cardia (in the top of the stomach, next to the oesophagus) or non-cardia (in the rest of the stomach, including the antrum, the lower part of the stomach next to the duodenum). It is also possible for the stomach to develop different sorts of cancers like gastric lymphoma or a gastric sarcoma, but these are rare.
Risk factors for stomach cancer include smoking, obesity, living in a region where the cancer is common (such as East Asia), high salt diet and family history. A family history means a parent, brother or sister with stomach cancer, or an inherited gene fault such as Lynch syndrome (also called hereditary non-polyposis colorectal cancer [HNPCC]). A history of gastritis (inflammation of the stomach lining) or stomach ulcers also increases the risk. Chronic infection with Helicobacter pylori (H. pylori, a bacterium that infects the stomach lining) is an established carcinogenic risk factor (a cause of cancer), particularly for non-cardia gastric adenocarcinoma (cancer in any part of the stomach except the cardia). A peptic ulcer (an ulcer in the stomach or duodenum) does not have to form first.
The typical presenting complaint of gastric cancer is epigastric pain (pain in the upper middle abdomen, just below the ribs) with an associated red flag symptom (a warning sign of serious disease). Examples are weight loss, a palpable epigastric mass (a lump in the upper abdomen that can be felt on examination), melaena (black, tarry stools from bleeding higher in the gut) and/or haematemesis (vomiting blood). This makes gastric cancer tricky to diagnose because the symptoms can be quite vague, and this often means that the diagnosis is made late. NICE guideline NG12 advises a suspected cancer pathway referral (a referral for specialist assessment of possible cancer) for stomach cancer in people who have dysphagia (difficulty swallowing). It also advises one for people aged 55 and over who have weight loss and any of upper abdominal pain, reflux or dyspepsia (indigestion). Diagnosis is made through endoscopy with biopsy (samples of tissue are taken and examined under a microscope). A whole-body CT scan is also done.
Treatment may involve surgery with chemotherapy (anti-cancer drugs) given before and after the operation. Radiotherapy (treatment using high-energy radiation) is usually given with chemotherapy, or to help with symptoms of advanced cancer. Targeted cancer drugs (drugs that act on particular features of cancer cells) or immunotherapy (drugs that help the immune system attack cancer cells) may be used for stomach cancer that has spread. As gastric cancer is often diagnosed late, these treatments may not be curative options.
The prognosis for gastric adenocarcinomas is poor because the cancer is usually not picked up until it has progressed to a later stage. The UK National Screening Committee does not recommend a national screening programme for stomach cancer. This is because there is no appropriate screening test, and it is not known how and when to treat suspicious signs of stomach cancer. Some countries where the cancer is more common, such as Japan, offer population-based screening using radiography (X-ray pictures) or endoscopy.
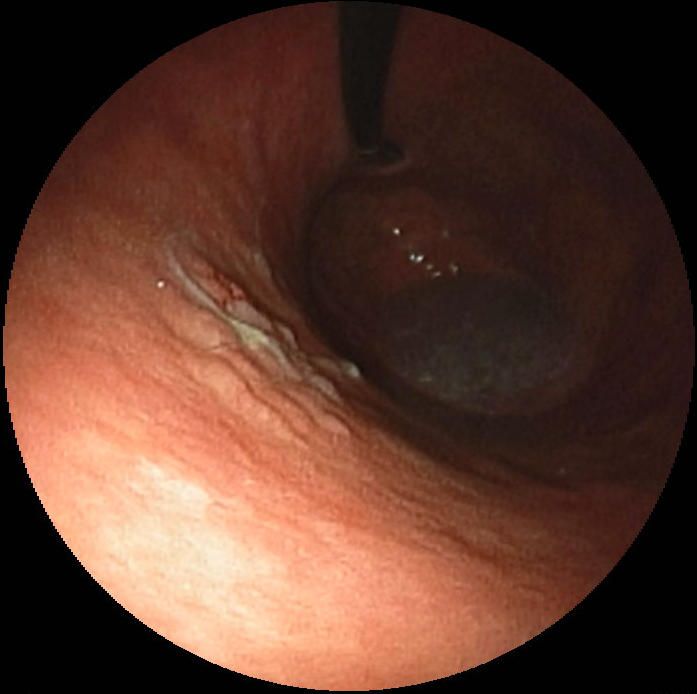
Image - Early gastric cancer in the body of the stomach
Public Domain Source by Med_Chaos [Public domain]
Hepatocellular carcinoma is the most common type of primary cancer of the liver (a cancer that starts in the liver). It is relatively uncommon in the general UK population but is common worldwide, particularly in patients with chronic liver disease and cirrhosis. However, it is relatively common for other cancers to metastasise (spread) to the liver. This is because most venous blood from the abdominal digestive tract reaches the liver through the portal circulation (the portal vein carries blood from the gut to the liver). Some drainage bypasses the liver. For example, the lower third of the rectum drains through the middle and inferior rectal veins into the systemic circulation (the general blood circulation), so blood from there does not pass through the liver first. In patients who present with jaundice, it is important to check for other red flag symptoms. These include weight loss, hepatomegaly (an enlarged liver) with irregular borders, and ascites (fluid in the abdomen). This is especially important if the jaundice is painless.
Risk factors for primary liver cancer include conditions that involve chronic inflammation of the liver, such as long-term hepatitis B, C or D infection and high alcohol consumption. These can lead to cirrhosis (scarring of the liver), which increases the risk of hepatocellular carcinoma. Fatty liver disease (non-alcoholic fatty liver disease, now also called MASLD), being overweight or obese, and diabetes also increase the risk.
Treatment depends on the stage of the cancer and how well the liver is working. It may involve surgery, liver transplantation, ablation (using heat to destroy the cancer), embolisation (blocking the blood supply to the cancer), radiotherapy, or targeted and immunotherapy drugs (drugs that act on cancer cells or help the immune system attack them). The prognosis is often poor, particularly when disease is advanced.
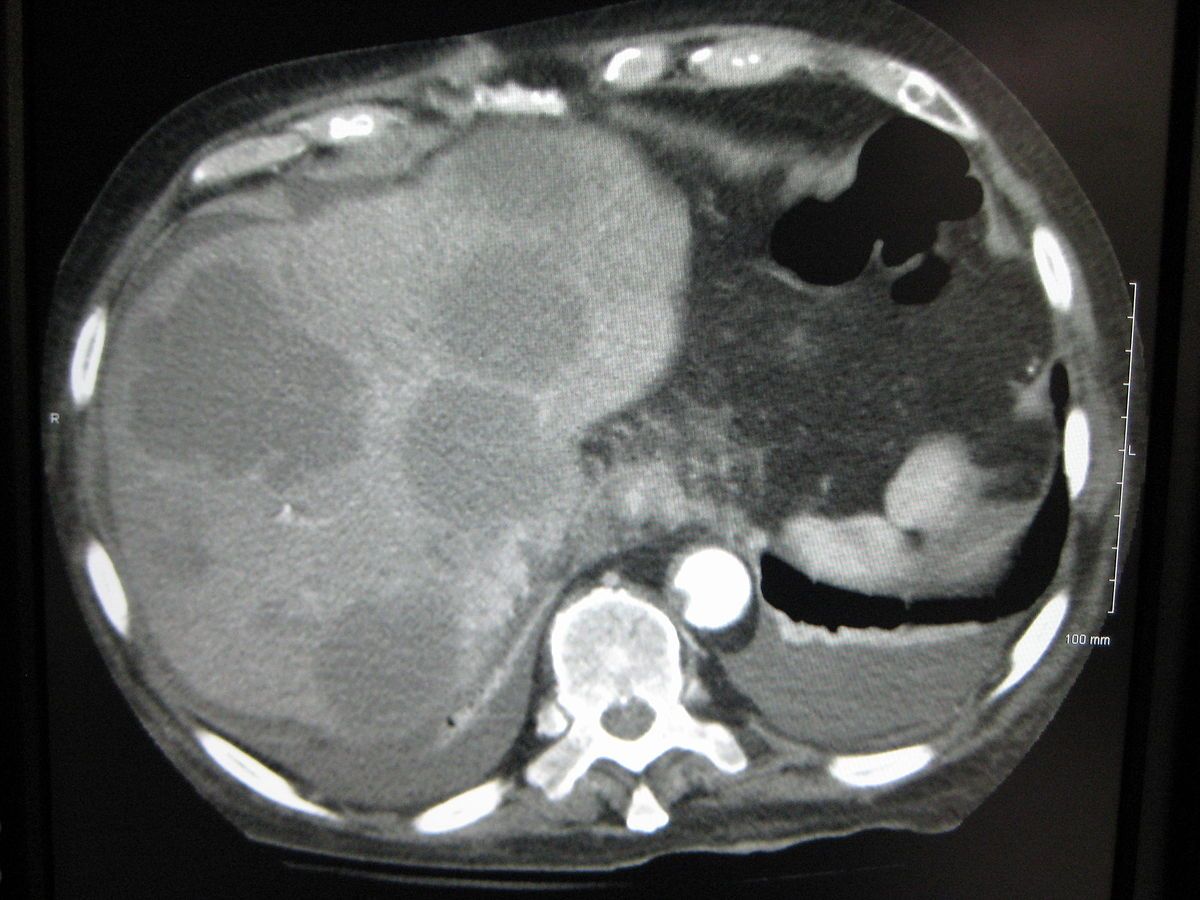
Image - Liver metastases on CT scan
Creative commons source by James Heilman, MD [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The vast majority of pancreatic cancers are ductal adenocarcinomas (cancers that start in gland cells of the pancreatic ducts, the small tubes that carry digestive juices).
Risk factors include increasing age, smoking, being overweight or obese, diabetes, family history, and recurrent or chronic pancreatitis (repeated or long-term inflammation of the pancreas). Pancreatic cancer is slightly more common in men than in women.
Pancreatic cancer can present with pain in the epigastric region that radiates to the back, jaundice and/or weight loss but symptoms do not usually arise until the cancer is at a later stage, making it difficult to diagnose early. As a result, it has a very poor prognosis. The ‘classical’, textbook presentation of pancreatic cancer is painless jaundice (i.e. jaundice with no other symptoms), but in reality, this is rare.
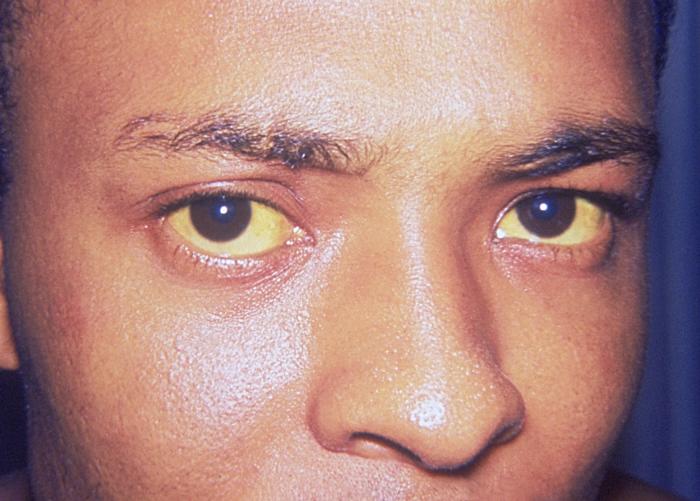
Image - Yellow sclera (the white of the eye) of jaundice
Public Domain Source by Centers for Disease Control and Prevention [Public domain]
Zollinger-Ellison Syndrome is a rare syndrome caused by a neuroendocrine tumour (a tumour of hormone-producing cells) called a gastrinoma. It can occur in the pancreas or the duodenum. This tumour secretes gastrin (a hormone that stimulates the stomach to make acid). This leads to the proliferation (growth in number) of parietal cells (the acid-making cells) in the stomach, which in turn increases acid production. Patients typically present with peptic ulcer disease (ulcers in the stomach or duodenum) and chronic diarrhoea.
Cancer of the small bowel is rare. Around 2,200 people are diagnosed in the UK each year. The main types are adenocarcinoma (a cancer of gland cells), neuroendocrine tumours (cancers of hormone-producing cells, formerly called carcinoid tumours), lymphoma and sarcoma. Gastrointestinal stromal tumours (GIST) are a rare type of sarcoma that can start in the connective tissue of the small bowel.
Risk factors include coeliac disease (an immune reaction to gluten that damages the lining of the small bowel), inflammatory bowel disease (long-term inflammation of the gut, such as Crohn’s disease), and genetic conditions such as familial adenomatous polyposis (FAP, a rare inherited condition in which many polyps develop on the bowel lining).
Small bowel cancer presents late, and its symptoms can be vague. It can cause small bowel obstruction (a blockage of the bowel), with colicky abdominal pain (pain that comes in waves), bloating and vomiting. Vomiting is more prominent when the blockage is higher up the small bowel. Severe constipation is a later development.
Management may involve surgery, chemotherapy and/or radiotherapy.
Colorectal cancer is a common cancer in the UK, with the most common type being adenocarcinoma.
Risk factors include increasing age, genetics (e.g. familial adenomatous polyposis [FAP] and Lynch syndrome, also called hereditary non-polyposis colorectal cancer [HNPCC]), inflammatory bowel disease (long-term inflammation of the gut, such as ulcerative colitis and Crohn’s disease), smoking, alcohol, obesity, a low fibre diet and eating a lot of red and processed meat.
A change in bowel habit from what is normal for the patient is a recognised presenting symptom of bowel cancer. Presentation varies with tumour site: right-sided cancers may present with iron-deficiency anaemia, left-sided cancers with altered bowel habit or obstruction, and rectal cancers with bleeding or tenesmus (a constant feeling of needing to open the bowels). Not every patient fits these patterns. NICE guideline NG12 advises offering a quantitative faecal immunochemical test (FIT, a stool test that looks for blood) to adults with an abdominal mass, a change in bowel habit or iron-deficiency anaemia, and to some adults with other unexplained symptoms depending on age. It advises a suspected cancer pathway referral (a referral for specialist assessment of possible cancer) if the result is at least 10 micrograms of haemoglobin per gram of faeces.
The table below summarises how presentation differs between right-sided colon, left-sided colon and rectal cancer:
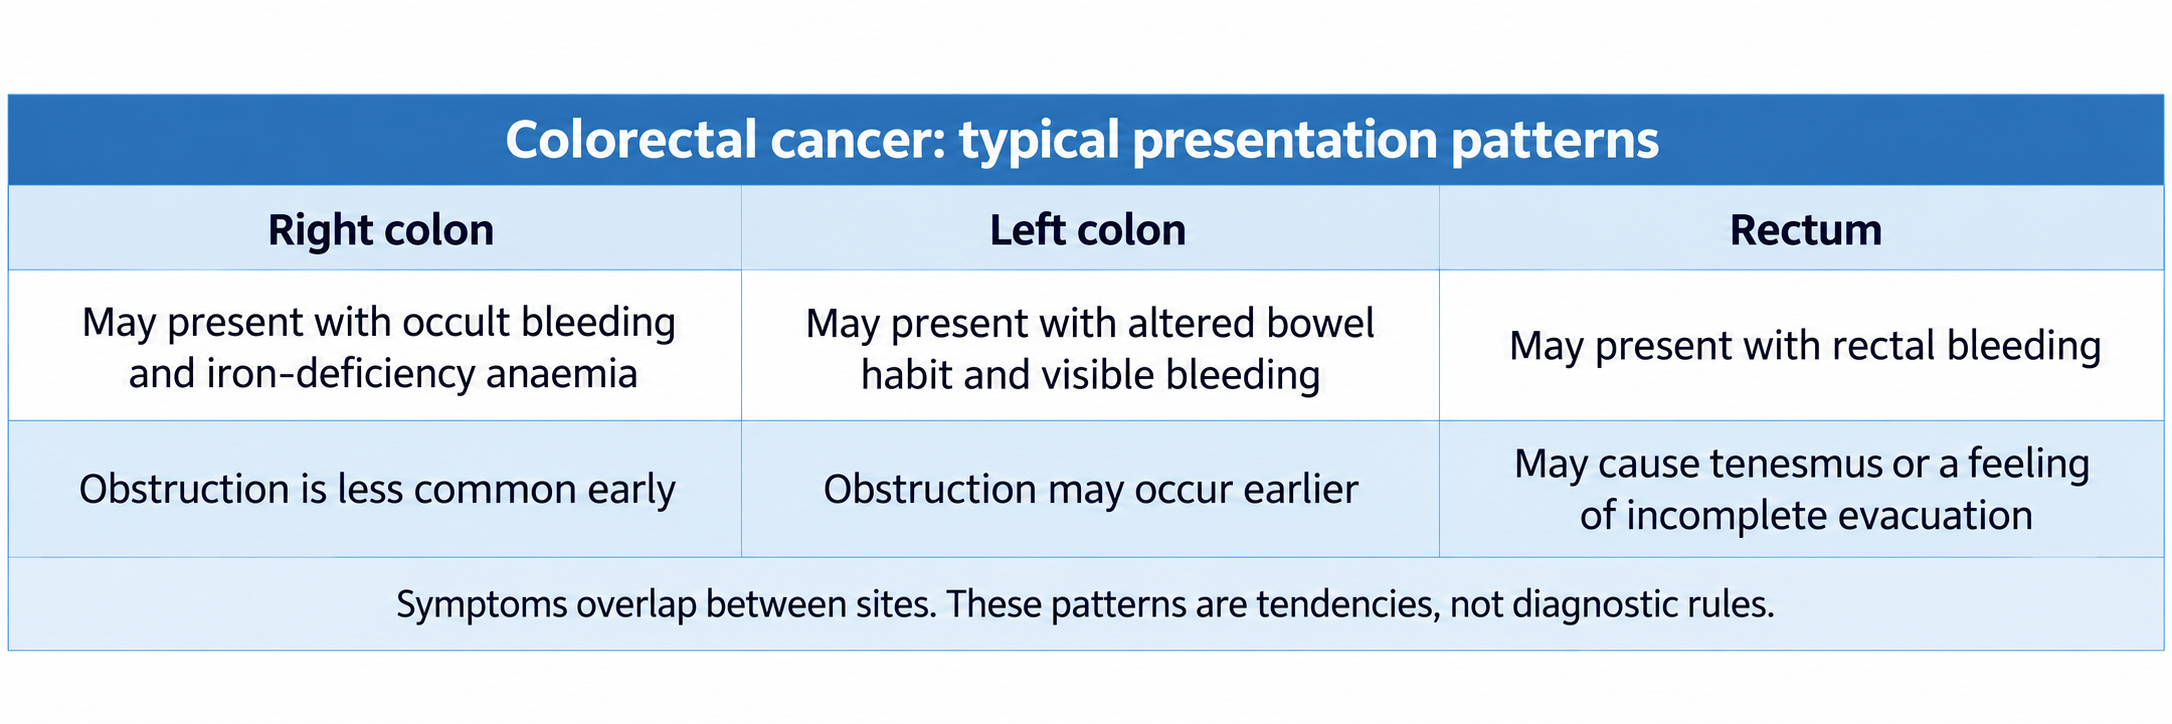
Table - Typical presentation patterns in right-colon, left-colon and rectal cancer. Symptoms overlap; these are tendencies rather than diagnostic rules.
SimpleMed original by Dr. Laura Hansell
Diagnosis is established by colonoscopy with biopsy (a camera test of the whole large bowel, with samples of tissue taken and examined under a microscope); CT/MRI scans help assess disease extent. Carcinoembryonic antigen (CEA, a protein in the blood that is raised in some cancers) may be measured at baseline and during follow-up. It cannot be used to screen for colorectal cancer or to rule it out, because it can miss some cancers and can be raised when there is no cancer.
Treatment often involves surgical resection of the affected bowel with adjuvant chemotherapy or radiotherapy. Radiotherapy in particular is used in rectal cancer as the rectum is relatively fixed within the pelvis, giving a predictable target; it is therefore less useful in colon cancer because the colon is more mobile.
The prognosis for colorectal cancer varies greatly depending on the stage at which the cancer is when it is first picked up.
In the UK, there is a screening programme that provides faecal immunochemical tests (FIT) every 2 years. A FIT looks for blood in a sample of stool. In England, it is offered to people aged 50 to 74. The age range varies across the UK nations. For example, in Northern Ireland it is offered to people aged 60 to 74. The test involves sending a stool sample in the post to be analysed.
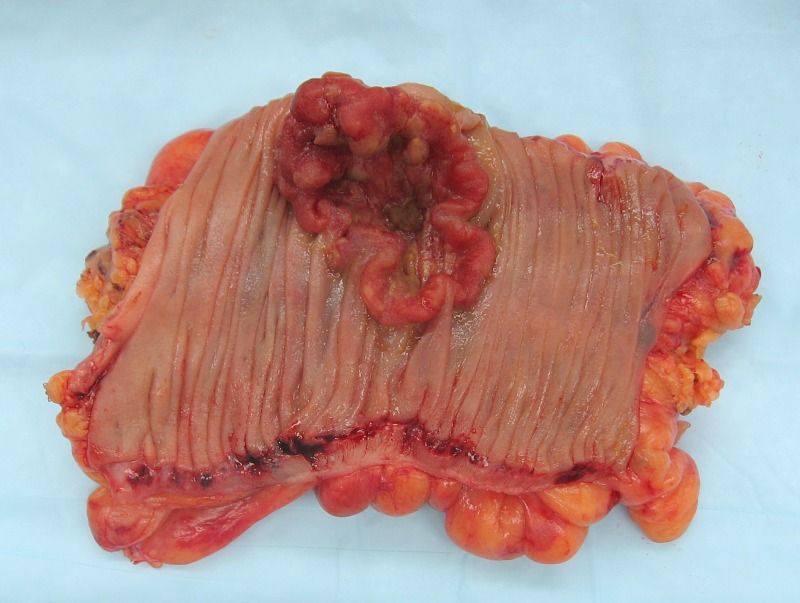
Image - Colorectal cancer
Creative commons source by Emmanuelm [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 928



