

Next Lesson - Anatomy and Physiology of the Midgut
Core
The mouth is the first part of the gastrointestinal system (GI system). It has two main functions: mechanical disruption of food by mastication (chewing) and chemical disruption of food through digestive enzymes found in saliva.
The muscles involved in mastication are:
- Temporalis (on the side of the skull)
- Masseter (in the cheek, from the cheekbone to the angle of the jaw)
- Medial pterygoid (jaw elevators)
- Lateral pterygoid (jaw depressor; it also pulls the jaw forwards, and one side on its own moves the jaw sideways)
Together, these muscles close the jaw, open it, and move it forwards and from side to side. All of them are innervated by the mandibular branch (the third branch) of the trigeminal nerve (CN V, the fifth cranial nerve). For more information, please see our article Fascial Planes, Muscles and Triangles in our Head and Neck section.
Saliva is composed of water, potassium, bicarbonate, mucins (the slippery proteins that make up mucus), amylase (an enzyme that starts to break down starch), lingual lipase (an enzyme that starts to break down fats) and immune proteins (such as immunoglobulin A, or IgA, an antibody). These components of saliva work together to perform functions such as lubricating the oral cavity, maintaining oral hygiene and the initial chemical disruption of food.
Saliva is released into the oral cavity via three pairs of salivary glands: parotid (in front of the ear), submandibular (under the jaw) and sublingual (under the tongue), all shown on the image below. Control of salivation is primarily driven by the autonomic nervous system.
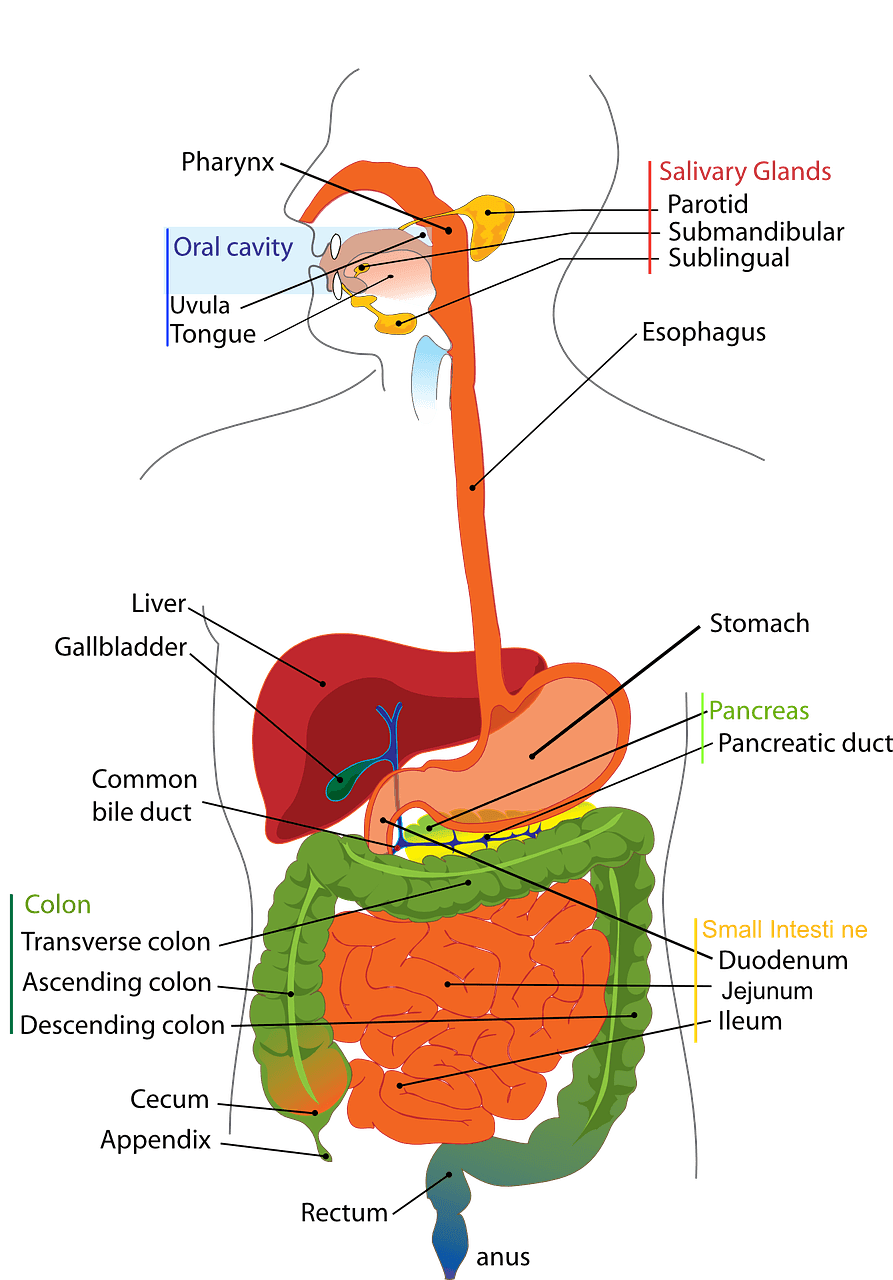
Diagram - Anatomy of the digestive system. The salivary glands are located in the head and all drain into the mouth
Creative commons source by Clker-Free-Vector-Images [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The oesophagus is the muscular tube that allows food transportation from the mouth to the stomach. It sits posterior to the trachea in the neck.
The oesophagus undergoes rapid peristalsis in order to transport the food bolus (the chewed ball of food) from the mouth to the stomach. The upper oesophageal sphincter prevents air from entering the GI tract and the lower oesophageal sphincter prevents reflux of acidic stomach contents back into the oesophagus.
The stomach is the J-shaped organ that receives food from the oesophagus to further the digestion started by the mouth.
The stomach is anatomically divided into regions:
- Cardia - the cardia is the region that surrounds the lower oesophageal sphincter.
- Fundus - the fundus sits superior to the cardia; the stomach’s shape means there is a region superior to the lower oesophageal sphincter.
- Pylorus - the pylorus is the region at the bottom of the stomach, surrounding the pyloric sphincter which connects the stomach to the duodenum.
- Body - the body of the stomach is the largest portion of the stomach and makes up the region between the pylorus and the fundus.
The stomach’s unusual shape also means that its two edges have curves of different lengths. These are known as the greater curve of the stomach and the lesser curve of the stomach. They are shown in red on the diagram below.

Diagram - The different regions of the stomach. The pyloric region (shown in pink) includes the wider pyloric antrum and the narrower pyloric canal, ending at the pyloric sphincter. The antrum is only part of the pyloric region
SimpleMed original by Dr. Maddie Swannack
The stomach also acts as an attachment point for the greater and lesser omenta (folds of peritoneum, the thin lining of the abdomen, that attach to the stomach). For more information on these, and the peritoneal cavity as a whole (the space inside the abdomen, lined by peritoneum), please see our article Development of the Gastrointestinal Tract.
The stomach has three main functions:
- Storage of food
- Disruption of the food bolus to form chyme (the semi-liquid mixture of food and gastric juice), through mechanical disruption and chemical disruption (by acid and pepsin, a protein-digesting enzyme)
- Secretion of intrinsic factor (a protein needed to absorb vitamin B12)
Mechanical disruption of the food bolus is aided by the stomach’s three layers of muscle that allow it to mix and grind its contents. These layers are the outer longitudinal layer (running along the length of the stomach), the central circular layer (running around it), and the inner oblique layer (running diagonally). By having fibres that run in three different directions, the stomach is able to contract against the food very well.

Diagram - Anatomy of the stomach with the three muscle layers shown
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The stomach wall is lined by a mucosa that is ridged, meaning it can expand as food enters the stomach. These folds of mucosa are called rugae. This mucosa is an important part of the stomach, because it contains many specialised cells that help with digestion. The surface of the mucosa is dotted with gastric pits (small dips in the epithelium), and each pit opens into a gastric gland (a tube-shaped gland in the stomach wall) that contains these cells.
G Cells - These are found within the pylorus. They are stimulated by gastrin-releasing peptide (GRP), acetylcholine release from neurones, and the presence of amino acids in the stomach to secrete gastrin (a hormone) to increase gastric acid secretion.
Parietal Cells - These are found within the body and fundus. They are stimulated by gastrin, histamine (made by cells in the stomach wall) and acetylcholine to secrete hydrochloric acid (HCl) to digest proteins, activate proteases (protein-digesting enzymes such as pepsin) and disinfect stomach contents. They also release intrinsic factor to aid Vitamin B12 absorption in the terminal ileum.
Mucous Cells - These are found throughout the stomach: in the cardia, body, fundus and pylorus. They secrete mucus and bicarbonate (HCO3-) ions to form a thick alkaline layer that adheres to the epithelium of the stomach to protect it from acidic damage.
Chief Cells - These are found within the fundus and body. They secrete pepsinogen (the inactive form of pepsin, a protein-digesting enzyme) to chemically disrupt proteins.
D Cells - These are found mainly within the pylorus, although some are scattered through the rest of the stomach lining. They are stimulated by the pH decreasing to secrete somatostatin (a hormone that switches off acid release) to inhibit G cells. This fall in pH occurs when the digested food leaves the stomach. The food had been mopping up hydrogen ions (buffering the acid), so once it has gone, any acid that is still being secreted makes the stomach more acidic.
As well as mucus and HCO3- ion secretion, the stomach has other defences including a high turnover of epithelial cells and an increased blood flow to the mucosa. This blood flow is maintained by prostaglandins (local chemical signals that protect the stomach lining).

Diagram - Histology of the stomach with the cells found within the gastric glands, which open into the gastric pits
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The duodenum is the most proximal part of the small intestine. It is the section of the gut between the pylorus of the stomach and the start of the jejunum, and it is split into 4 parts.
The function of the duodenum is to neutralise the acidic chyme from the stomach with bicarbonate-rich secretions before the chyme enters the jejunum. This is achieved mainly through bicarbonate-rich pancreatic secretions released into the duodenum, helped by alkaline mucus from the duodenal glands (Brunner’s glands) in the wall of the duodenum. Bile (made by the liver) helps the digestion of fats by emulsifying them, which means breaking large fat globules into tiny droplets. It is also where iron is absorbed from the chyme.
The duodenum has a dual blood supply from the gastroduodenal artery (a branch of the common hepatic artery, which comes from the coeliac trunk; it supplies the duodenum above the major duodenal papilla) and the inferior pancreaticoduodenal artery (a branch of the superior mesenteric artery; it supplies the duodenum below the papilla). Its venous drainage is into the veins of the same name, which drain into the superior mesenteric vein or the portal vein (the vein that carries blood from the gut to the liver). Lymphatic drainage is into the pancreaticoduodenal and superior mesenteric nodes.
I Cells - stimulated by the presence of fats and proteins, I cells release cholecystokinin (CCK, a hormone) to increase pancreatic enzyme secretion and to make the gallbladder contract, releasing bile.
S Cells - stimulated by H+ (hydrogen ions, which make the chyme acidic) and fatty acids to secrete secretin (a hormone). This increases HCO3- secretion and decreases gastric acid secretion from the stomach.
K Cells - stimulated by sugars, fatty acids and amino acids to secrete glucose-dependent insulinotropic polypeptide (GIP, a hormone that used to be called gastric inhibitory polypeptide). This acts mainly to increase insulin secretion after a meal (GIP is an incretin, a gut hormone that boosts insulin release), and has only a weak effect in decreasing gastric acid secretion.
Connect this region to the integrated physiology: use Gastrointestinal Motility and the Enteric Nervous System for gastric emptying, enteric (gut) reflexes and coordinated movement. Use Gastrointestinal Secretion, Digestion and Absorption for acid, enzyme action and nutrient uptake. Use Liver, Biliary and Exocrine Pancreatic Physiology for the bile and pancreatic secretions delivered to the duodenum.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 9098


