

Next Lesson - Auditory and Vestibular Systems
Core
To understand the visual pathway, the first thing to understand is the anatomy of the eye. For more information about the anatomy of the eyeball, please see the article 'The Eye' in our Head and Neck series.
The outermost layer of the eyeball is the fibrous layer. It consists of the sclera (the white of the eye) and the cornea (the transparent front of the eye), which are continuous with each other. Posteriorly, the sclera is continuous with the dural sheath (the dura mater, the tough outer membrane that also covers the brain) of the optic nerve (CNII). Next is the middle layer or vascular layer, known as the uvea. It comprises the iris (the circular structure around the pupil, which controls the size of the pupil) and the ciliary body (which controls the shape of the lens) anteriorly, and the choroid (a layer of blood vessels and connective tissue behind the retina) posteriorly.
Finally, the innermost layer is the retina, the light-detecting layer of the eye. It has two layers. The outer layer is the retinal pigment epithelium, a single layer of pigmented cells. The inner layer is the neural layer, which contains photoreceptor cells (rods and cones, which detect light), bipolar cells (which pass signals from the photoreceptor cells on to the ganglion cells), and ganglion cells (whose fibres form the optic nerve).
Optical coherence tomography (OCT) is an imaging technique (a scan) that shows the layers of the retina, so it can be used to show damage to the retina.
Understanding where light falls on the retina makes the visual pathway much easier to follow. The eye is like a pinhole camera, although in the real eye the cornea and lens bend (refract) the light to focus it. Light from the lateral visual field is directed towards the medial retina and light from an upper visual field is directed towards the lower retina. To help prevent confusion surrounding words like medial and lateral between the two eyes, medial is more often described as nasal (nearest the nose) and lateral as temporal (nearest the temple).
All of this means that the projection of what the eye sees is basically flipped upside down and flipped left to right on our retina. This spatial organisation is preserved as the information is mapped retinotopically (each point on the retina has a matching point in the cortex) in the visual cortex.
The basic optic pathway is as follows: retina -> optic nerve -> optic chiasm -> optic tracts -> lateral geniculate nucleus -> optic radiations -> visual cortex of the occipital lobe.
From the retina, the optic nerve leaves the orbit (eye socket) via the optic canal. This is a passage through the sphenoid bone (a bone at the base of the skull) into the middle cranial fossa (the central hollow in the floor of the skull). The optic nerves from both eyes meet in the centre of the skull to form the optic chiasm; this occurs just above the pituitary gland.
Within the optic chiasm, fibres from the nasal half of each retina cross over (decussate) to the contralateral optic tract, whereas the fibres from the temporal half of each retina remain ipsilateral (on their original side). So, the left optic tract comprises fibres from the left temporal half of the retina and fibres from the right nasal half of the retina. This means that the same half of the visual field from both eyes is transferred within the same optic tract. For example, something positioned to the patient’s right side will be perceived by the right nasal retina and the left temporal retina, and both will send the information down the left optic tract. The right optic tract carries the left half of the visual field in the same way.
The optic tracts project from the optic chiasm to a part of the thalamus known as the lateral geniculate nuclei (relay stations for visual information). There is a left and a right lateral geniculate nucleus. The fibres of the optic tract synapse here (pass the signal on to new neurones). The axons of these new neurones leave the nucleus as the superior and inferior optic radiations. Fibres from the superior half of the retina (inferior visual field) travel as the superior optic radiation through the parietal lobe to the visual cortex. Fibres from the inferior half of the retina (superior visual field) travel as the inferior optic radiation, also referred to as Meyer’s loop (named for the forward loop that its front part makes), through the temporal lobe to the visual cortex.
The names of the radiations are easy to mix up, so here is a summary:
- Inferior visual field - superior optic radiation - parietal lobe
- Superior visual field - inferior optic radiation - temporal lobe
Some people find this mnemonic helpful - PITS can be used to remember that the Parietal lobe has the Inferior visual field, and the Temporal lobe has the Superior visual field. PITS works for the lobes and the visual fields, but not for the names of the radiations, because the superior radiation carries the inferior visual field.
The optic radiations travel into the primary visual cortex in the occipital lobe.
Here is a diagrammatic representation of the pathway to help visualise it all:

Diagram - The path that information from all four quadrants of both eyes takes between the retina and the visual cortex
SimpleMed original by Dr. Elena Perez
Now, let’s apply the understanding of the visual pathway to localise lesions based on visual field defects. Damage to the optic fibres at different levels of the pathway causes particular patterns of visual field loss. These defects often develop slowly, so patients may not notice them, and they can be picked up during a routine eye test. This can lead to the diagnosis of a lesion in the brain.
Visual pathway defects are always described by referring to the lost visual field (not the position of the damage in the retina or the pathway). The visual field of each eye is divided into quadrants (quarters) when describing these.
There are some terms that are important to understand when describing visual field defects:
- Hemianopia - loss of one-half of the visual field (hemi means half). It is usually described across both eyes as a binocular (both eyes together) visual field defect (for example, loss of the left half of the visual field).
- Quadrantanopia - loss of one quadrant (one quarter) of the visual field.
- Homonymous - homonymous means the same, so a homonymous hemianopia would be a loss of the same half of the visual field in both eyes. However, it is important to understand that the same half is the nasal field of one eye and the temporal field of the other. For example, the right half of the visual field is the nasal field of the left eye and the temporal field of the right eye.
A scotoma is a localised defect in the visual field: an area of reduced or lost vision (a blind spot) that does not conform to quadrants like visual field defects normally do. Some scotomas are caused by retinopathies (diseases of the retina), for example those caused by diabetes and hypertension. Others come from damage to the visual pathway itself. For example, multiple sclerosis (an inflammatory condition of the brain, optic nerves and spinal cord) is not a retinopathy, but it can cause optic neuritis (inflammation of the optic nerve), which can produce a scotoma. Lesions at the optic chiasm or in the visual cortex can also cause scotomas.
Complete damage to one optic nerve causes monocular blindness (blindness in one eye), where vision from the whole visual field of the eye involved is lost. Partial damage to the optic nerve causes a less complete loss of vision in that eye, for example a scotoma or a general reduction in vision.
Damage to the optic chiasm (most commonly caused by pituitary tumours as the pituitary gland sits below the chiasm) causes bitemporal hemianopia, where patients lose the lateral halves of the visual field in both eyes (bitemporal means both temporal fields). This is because the nasal retinal regions (the temporal visual fields) decussate through the optic chiasm, and it is these fibres that are damaged. Bitemporal hemianopia is different from tunnel vision, which is narrowing of the whole peripheral visual field, as in retinitis pigmentosa (an inherited disease of the retina).
Damage to the optic tract will result in a contralateral homonymous hemianopia where patients lose vision on the opposite side of the visual field to where the lesion is. For example, if the lesion is on the left optic tract, it causes a right homonymous hemianopia, where the right half of the visual field is lost in each eye. This is a nasal hemianopia in the left eye and a temporal hemianopia in the right eye, which together are called ‘homonymous’.
Damage to the superior optic radiations (in the parietal lobe) will result in contralateral homonymous inferior quadrantanopia. For example, if the lesion is on the left parietal (superior) radiation, it causes right homonymous inferior quadrantanopia. Similarly, damage to an inferior optic radiation causes a superior quadrantanopia on the opposite side to the lesion. For example, if the lesion is on the left temporal (inferior) radiation, also called the left Meyer’s loop, it causes right homonymous superior quadrantanopia.
Infarction of the occipital visual cortex after posterior cerebral artery occlusion (blockage) can cause a contralateral homonymous hemianopia. Macular sparing may occur: central vision (from the macula, the central part of the retina) is preserved. This happens when the occipital pole (the tip of the occipital lobe), which represents central vision, remains intact, for example through collateral flow (blood supply from a neighbouring artery) from the middle cerebral artery. This collateral supply varies between individuals, so central vision is not always spared.
Here is a diagrammatic representation of visual field defects from lesions at different levels of the visual pathway to help visualise it all:
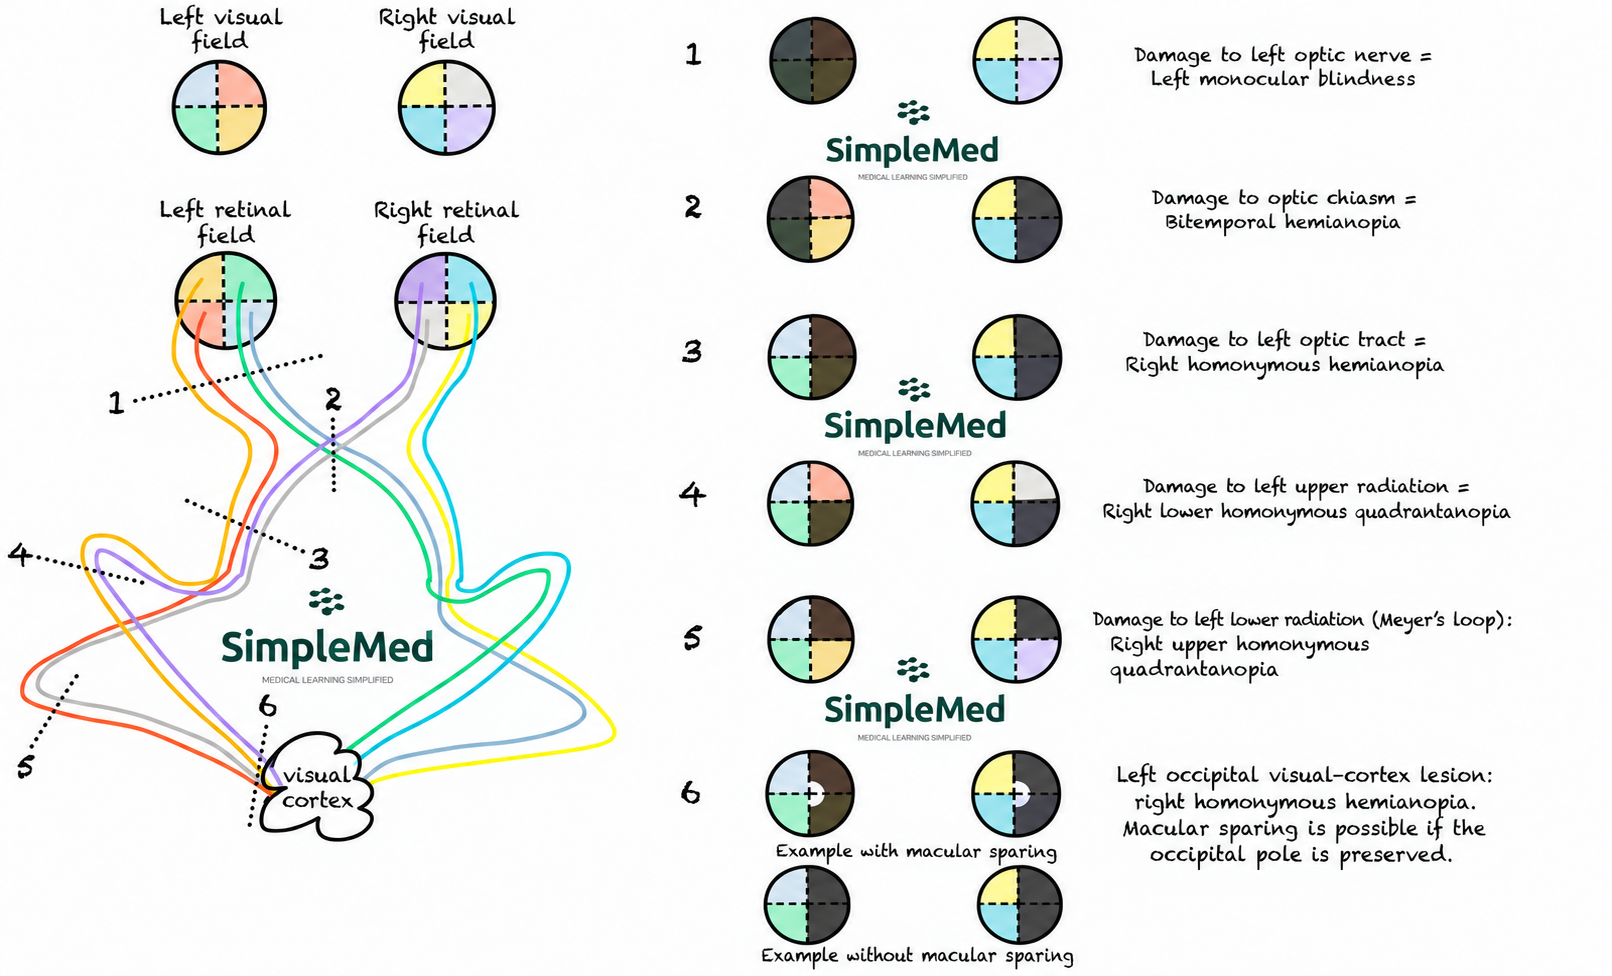
Diagram - Schematic examples of visual-field loss from left-sided pathway lesions. Paired circles represent the left and right eyes; dark shading marks field loss. A left occipital lesion may cause right homonymous hemianopia with or without macular sparing, depending on preservation of the occipital pole.
SimpleMed original by Dr. Elena Perez
In Summary
- The pathway goes retina -> optic nerve -> optic chiasm -> optic tract -> lateral geniculate nucleus -> radiations -> primary visual cortex.
- Visual fields and retinal positions are opposite: the upper temporal visual field falls on the lower nasal retina.
- The right half of each retina uses the right optic tract, because nasal fibres cross at the chiasm and temporal fibres do not.
- Nasal fibres decussate (cross) at the optic chiasm, so damage to the chiasm causes bitemporal hemianopia.
- Fibres from the inferior retina use the inferior radiation, which carries the superior portion of the visual field.
- PITS - Parietal radiation is Inferior visual field (superior radiation) and Temporal radiation is Superior visual field (inferior radiation).
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 1706
