

Next Lesson - Glomerular Filtration Rate and the Measurement of Kidney Function
Core
A diuretic is a substance that promotes diuresis, i.e. increases urine production. There are many types of diuretics, ranging from everyday substances that cause diuresis to medications that are prescribed to patients if they become fluid overloaded.
- Some examples of substances that cause diuresis but are not used as diuretic medicines include alcohol, coffee and tea.
- Alcohol inhibits anti-diuretic hormone release and this causes diuresis. See our article on anti-diuretic hormone for more information on how it functions.
- Caffeine causes mild diuresis. It blocks adenosine receptors in the kidney (adenosine receptor antagonism), which reduces sodium reabsorption and therefore water reabsorption.
- Some examples of diuretics include furosemide, bendroflumethiazide, spironolactone and amiloride.
Diuretics act by reducing the reabsorption of sodium (Na) and water in the kidney nephrons. By blocking Na reabsorption, water will not be reabsorbed from the tubules and so will be excreted. Diuretics can either increase or decrease potassium (K) excretion, meaning a patient can become hyper or hypokalaemic (have a high or low blood potassium level) depending on the diuretic given.
- Diuretics that cause hyperkalaemia include spironolactone and amiloride.
- Diuretics that cause hypokalaemia include loop and thiazide diuretics.
There are different ways that diuretics work and this depends on the type of diuretic. Diuretics mainly act in the following ways:
- Block Na transporters in the kidney nephron to decrease reabsorption of Na. Diuretics in this category include loop diuretics, thiazide diuretics and potassium sparing diuretics.
- Antagonise aldosterone (block its action) to reduce its effects and decrease Na reabsorption. Diuretics in this category include spironolactone and eplerenone.
- Osmotic diuretics act by increasing the osmolality of the filtrate in the nephron tubules to stop water being absorbed. The main diuretic in this category is mannitol.
- Inhibition of carbonic anhydrase in the kidney tubules which interferes with the reabsorption of Na and bicarbonate to increase water loss. The main diuretic in this category is acetazolamide.
As diuretics act by increasing water loss, they can cause two problems from the fluid loss alone (electrolyte disturbances are also common, and are covered for each type of diuretic below):
- Hypovolaemia (low circulating blood volume)
- Hypotension (low blood pressure, which can follow hypovolaemia)
When patients are reviewed, these side effects should be looked out for, especially if the patient is on a high dose of a diuretic, as this increases the risk of side effects.
Loop diuretics are the most potent diuretic as they work directly on the loop of Henle (the U-shaped section of the nephron) where large amounts of Na are reabsorbed.
Loop diuretics work by blocking apical Na-K-Cl2 (NKCC2) transporters in the thick ascending limb of the loop of Henle. By blocking this transporter less Na and chloride (Cl) ions are reabsorbed which decreases the osmolality in the medulla interstitium (the tissue around the tubules in the inner kidney), and therefore decreases water reabsorption from the descending limb of the loop of Henle. This results in increased water and Na loss from the body.
By blocking NKCC2 transporters, loop diuretics increase the loss of calcium and magnesium in the urine. This can cause hypocalcaemia (low blood calcium) and hypomagnesaemia (low blood magnesium), but blood levels do not always fall. Low magnesium is linked more clearly to thiazide diuretics. You should still check a patient's electrolyte levels to make sure they do not become too low. Calcium and magnesium are lost in the urine because of the following steps in the nephron tubules:
- Usually the NKCC2 transporter shifts 2 Cl-, 1 Na+ and 1 K+ into the tubule cell from the nephron lumen. The Na is pumped into the blood using the sodium-potassium pump (Na-K-ATPase) while the Cl drifts back into the blood through its own channel. While this is happening the K drifts back into the lumen through ROMK channels (potassium channels) in the apical membrane.
- This movement of K+ ions back into the lumen creates a positive luminal potential (the lumen becomes electrically positive compared with the blood) that drives the reabsorption of other positively charged ions, like Ca2+ and Mg2+, back into the tubule cells where they can then be moved into the blood.
- When the NKCC2 transporter is blocked this movement of K+ ions stops, and so there is no longer a positive luminal potential which then decreases the reabsorption of the other positively charged ions, so more calcium and magnesium are lost in the urine, which can lower blood levels.
Some examples of loop diuretics are furosemide and bumetanide. These two are commonly used in practice for a range of treatments. They have similar side effects and reactions with other drugs.
- Symptoms of Heart Failure - loop diuretics mainly decrease preload (the amount of blood filling the heart before it contracts), which relieves the symptoms of heart failure, such as breathlessness and swollen ankles. Their effect on survival is unclear.
- Acute Pulmonary Oedema (fluid in the lungs, usually due to left heart failure) - given intravenously, loop diuretics relieve breathlessness.
- Fluid Retention - loop diuretics can be used in conditions such as nephrotic syndrome, renal failure and decompensated liver disease if the patient becomes oedematous or is fluid retained.
- Hypertension
- Hypercalcaemia (high blood calcium) - loop diuretics increase calcium loss in the urine, but they are not effective at lowering blood calcium. They are now used only if IV fluids, e.g. normal saline, cause fluid overload.
Side Effects and Drug-Drug Interactions
The side effects that a patient may experience with different loop diuretics are very similar, but there are still some side effects that are different.
Potent loop diuresis can cause excessive salt and water loss, leading to hypovolaemia and electrolyte disturbances. Hyponatraemia (low blood sodium) can occur, but is less commonly caused by loop diuretics than by thiazides. Monitor fluid status, blood pressure, renal function and electrolytes, particularly after dose changes and during prolonged or high-dose treatment.
This article will cover the main side effects of furosemide and bumetanide.
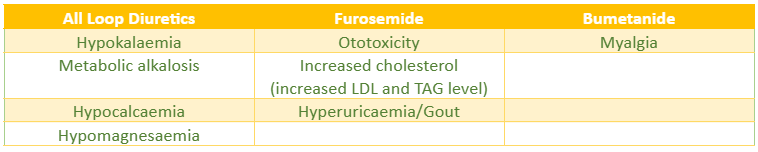
Table - The Side Effects of Loop Diuretics. Calcium and magnesium losses can lower blood levels, but this does not always happen.
SimpleMed original by Dr. Thomas Burnell
Drug-drug interactions occur when a patient is taking two or more drugs that interact with each other or have similar effects on the body, resulting in the patient experiencing the side effects of these drugs to a worse severity or making the side effects more likely to occur. The following table demonstrates the main drug interactions that may occur with loop diuretics.
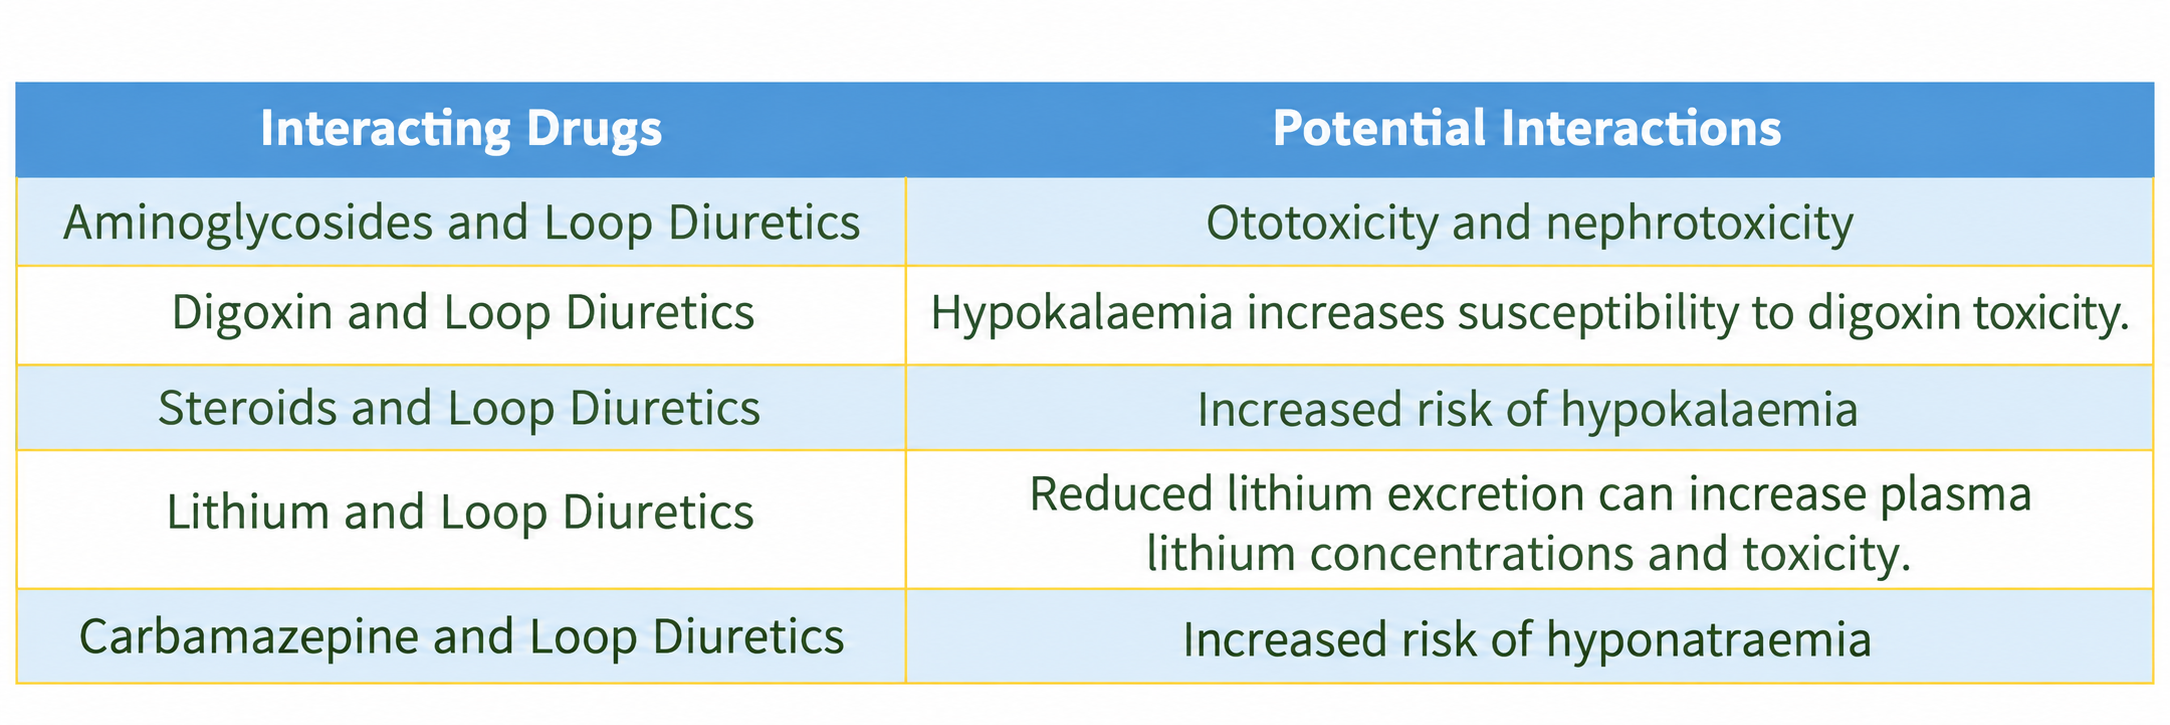
Table - Potential interactions with loop diuretics. Effects depend on the medicines and the patient; consult individual product information.
SimpleMed original by Dr. Thomas Burnell
Thiazide diuretics act to increase sodium and water loss by blocking sodium reabsorption in the early distal convoluted tubule (DCT, the part of the nephron after the loop of Henle), though they are less potent than loop diuretics.
Thiazide diuretics work by blocking the Na-Cl transporter in the DCT to increase the amount of Na in the nephron lumen. This decreases water reabsorption as there is a higher osmolality in the lumen, so water stays in the lumen and is lost as urine (diuresis).
As thiazide diuretics do not block NKCC2 transporters, calcium handling differs from loop diuretics. Thiazides reduce urinary calcium loss and can increase serum calcium, but they can still cause hypomagnesaemia, so magnesium levels may fall with treatment.
Some examples of thiazide diuretics include bendroflumethiazide, metolazone and indapamide, though indapamide and metolazone are classified as thiazide-like diuretics. Thiazide-like diuretics act at the beginning of the distal convoluted tubule, as thiazides do.
- Hypertension - when a diuretic is needed for hypertension, NICE advises a thiazide-like diuretic, such as indapamide, in preference to a conventional thiazide such as bendroflumethiazide. It is usually added to an ACE inhibitor, an angiotensin-II receptor blocker (ARB) or a calcium-channel blocker rather than started first, unless a calcium-channel blocker is not tolerated or there is heart failure
- Resistant oedema, e.g. in nephrotic syndrome (a kidney condition with heavy protein loss in the urine, causing swelling) - a thiazide-like diuretic, such as metolazone, can be added to a loop diuretic when the loop diuretic alone does not clear the oedema.
Side Effects and Drug-Drug Interactions
Thiazide diuretics typically all have the same main side effects and there is not much difference between them. The side effects can be seen in the table below.

Table - The Common Side Effects of Thiazide Diuretics. Hyponatraemia (low blood sodium) and hypomagnesaemia (low blood magnesium) can also occur.
SimpleMed original by Dr. Thomas Burnell
The common drug-drug interactions involving thiazide diuretics can be seen in the table below.
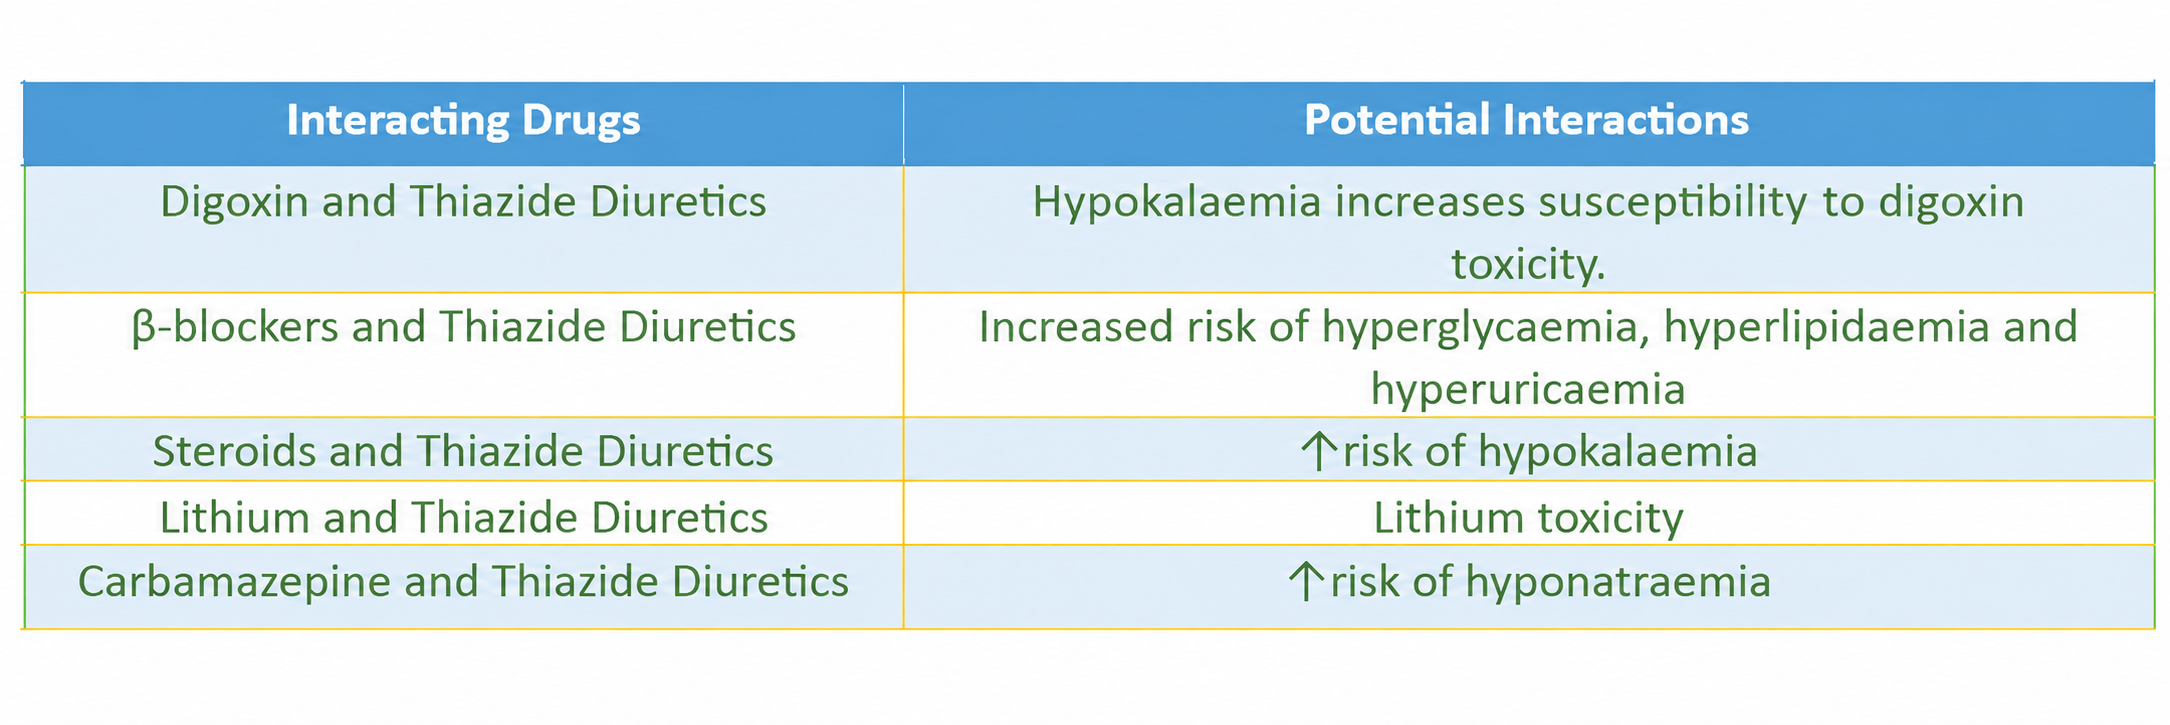
Table - Potential interactions with thiazide diuretics. The metabolic cautions shown with beta-blocker therapy can also occur with thiazides alone, so these cautions do not apply to every thiazide or every patient. Consult individual product information.
SimpleMed original by Dr. Thomas Burnell
Hypokalaemia in Loop Diuretics and Thiazide Diuretics
Both loop and thiazide diuretics have a risk of hypokalaemia because of how they increase the delivery of Na and water to the late distal convoluted tubule and collecting duct (the final part of the tubule). By increasing the delivery of these two substances, more potassium is secreted into the tubule and lost in the urine. There are two reasons for this:
- The increased Na reabsorption by the principal cells (the cells that reabsorb sodium and secrete potassium) of the collecting duct creates a favourable electrical gradient for potassium excretion via apical potassium channels on principal cells.
- The increased amount of sodium and water within the lumen causes there to be a faster flow rate within the tubule. The faster flow rate of the filtrate means K+ ions secreted into the lumen are washed away faster, lowering the K+ ion concentration in the lumen, creating a favourable chemical gradient for K+ ion secretion.
The effect of both of these is increased potassium loss in the urine leading to hypokalaemia.
Aldosterone antagonists work by inhibiting the effects of aldosterone and preventing its action on the kidneys. Aldosterone production is stimulated by the Renin-Angiotensin-Aldosterone System and is released from the adrenal cortex. Check out our article on blood pressure for more information about the renin-angiotensin-aldosterone system.
Aldosterone has many effects on the body but mainly acts on the kidneys to increase sodium and water reabsorption. Aldosterone’s functions include:
- Acts on cells in the DCT and collecting duct to upregulate the Na/K pump in the basolateral membrane (the side of the cell facing the blood) to create a Na gradient in the cell.
- Upregulates Epithelial Na channels (ENaC) in the collecting duct and colon to increase Na reabsorption and therefore increase water reabsorption.
- Stimulates secretion of K+ ions into the tubule to secrete the excess K brought into the cell by the Na/K pump. The secretion of K also helps to create and maintain the positive luminal potential.
- Upregulates Na/Cl co-transporters in the DCT to increase Na reabsorption.
- Stimulates Na and water retention in the gut, salivary glands and sweat glands to decrease water and Na loss.
Aldosterone antagonists work by inhibiting the functions of aldosterone. They do this by blocking the mineralocorticoid receptor (the receptor that aldosterone acts on), so aldosterone cannot increase the number of epithelial Na channels and Na/K pumps in the DCT and collecting duct. As a result, there is a reduction in Na reabsorption resulting in a loss of Na and diuresis.
One of the major side effects of aldosterone antagonists is hyperkalaemia. This happens because the kidneys lose the stimulation to secrete K+ ions into the tubule as aldosterone is being inhibited. Potassium excretion is also decreased because the electrical gradient that promotes K+ ion excretion is reduced because there is a higher concentration of Na+ ions in the tubule, increasing the tubule’s positive charge. The potassium level in the body will then rise as the kidneys are no longer removing excess K from the body, resulting in hyperkalaemia.
Potassium sparing diuretics, such as aldosterone antagonists, are often used in combination with potassium losing diuretics, such as loop diuretics, to reduce the loss of potassium from the body. They can cause dangerous hyperkalaemia if given with an ACE inhibitor or an angiotensin-II receptor blocker (ARB), or in kidney impairment, so potassium and kidney function must be monitored.
The main aldosterone antagonist drug is spironolactone. This article will be using spironolactone for its uses and side effects of aldosterone antagonists.
- Hypertension - as an add-on for resistant hypertension (NICE step 4), if blood potassium is 4.5 mmol/L or less
- Heart Failure - in heart failure with reduced ejection fraction (the heart pumps out less blood than it should), spironolactone reduces the risk of death
- Decompensated Liver Disease (advanced liver disease with complications such as ascites)
- Hyperaldosteronism (too much aldosterone)
- Ascites (fluid in the abdomen)
- Oedema
Side Effects of Spironolactone
All aldosterone antagonists can cause hyperkalaemia (high blood potassium) because they reduce the excretion of K from the body, so the level builds up. The other main side effects of spironolactone are:
- Impotence
- Painful gynaecomastia (breast tissue growth in men)
Amiloride is a potassium-sparing diuretic that inhibits epithelial Na-channels in the late distal convoluted tubule and collecting duct of the renal nephron to reduce Na reabsorption late on in the tubule, resulting in a small increase in diuresis. On its own, amiloride is a weak diuretic and causes only a small decrease in sodium reabsorption.
Amiloride is known as a potassium-sparing diuretic because it reduces potassium loss from the body. Reduced sodium reabsorption via epithelial Na-channels increases the positive charge in the nephron tubule, resulting in a less favourable electrical gradient for K+ ion secretion into the tubule. Spironolactone is also a potassium-sparing diuretic, but it works by blocking aldosterone, which reduces K+ ion secretion into the tubule, so less potassium is lost in the urine.
Amiloride is mainly used alongside a potassium-losing diuretic, e.g. loop or thiazide diuretics, to reduce the risk of hypokalaemia.
- Hypertension
- Oedema
- Congestive heart failure
- Ascites due to hepatic cirrhosis
The main side effect of amiloride is hyperkalaemia (high blood potassium), so plasma potassium must be monitored, especially in renal impairment. Other side effects include:
- Arthralgia (joint pain)
- Decreased appetite
- Nausea and vomiting
- Dysuria (painful urination)
- Dry mouth
Osmotic diuretics function by increasing the osmolality of the blood and the filtrate in the nephron tubule. They are freely filtered at the glomerulus but are not reabsorbed by the nephron. This means they can increase the osmolality of the renal filtrate, drawing water into the filtrate to decrease water reabsorption and increase water loss from the body. As osmotic diuretics also affect the osmolality of the blood they can be used to draw water out from other parts of the body, such as the brain.
An example of an osmotic diuretic is mannitol. The rest of this article will cover the uses and side effects of mannitol as an example of osmotic diuretics.
Mannitol is used to treat raised intracranial pressure and cerebral oedema. This is because the rise in blood osmolality draws water out of brain tissue and into the blood, which lowers the intracranial pressure and relieves pressure on the brain. It acts by a similar mechanism to draw water out of the brain in cerebral oedema to reduce brain swelling.
Side Effects of Osmotic Diuretics
- Dehydration
- Electrolyte disturbances (e.g. hyponatraemia, low blood sodium, or hypernatraemia, high blood sodium)
- Fluid overload, because mannitol first expands the blood volume. This can cause pulmonary oedema (fluid in the lungs), especially in patients with heart failure
- A rebound rise in intracranial pressure
- Headache
- Vomiting
- Skin reactions
Carbonic anhydrase inhibitors act by inhibiting carbonic anhydrase, an enzyme found on the apical surface of the tubule cells of the proximal convoluted tubule. The inhibition of this enzyme interferes with the reabsorption of bicarbonate from the filtrate, which inhibits the function of the Na-H exchanger on the apical surface of the tubule cells, reducing sodium reabsorption and therefore reducing water reabsorption causing diuresis.
Examples of carbonic anhydrase inhibitors include dorzolamide and acetazolamide. Dorzolamide is given as eye drops to treat glaucoma (raised pressure in the eye). Acetazolamide is used for glaucoma and to prevent altitude sickness (an unlicensed use). It is a weak diuretic and is little used for its diuretic effect.
Side Effects of Carbonic Anhydrase Inhibitors
- Renal stones (with acetazolamide)
- Headache
- Eye inflammation (with dorzolamide eye drops)
- Vision disorders (with dorzolamide eye drops)
- Nausea
As carbonic anhydrase inhibitors inhibit bicarbonate reabsorption, there is an increased risk of acidosis (too much acid in the blood) as there are less bicarbonate ions in the blood to react with acid. Metabolic acidosis is a common side effect of acetazolamide, so blood electrolytes should be checked with prolonged use. If acidosis occurs, it can be corrected with bicarbonate.
The following table is a simplified overview of when diuretics are used and which diuretics are used in each case. Some ticks need qualifying. A loop diuretic can be added to blood pressure treatment in resistant hypertension (blood pressure that stays high despite three other blood pressure drugs), impaired kidney function or heart failure. Loop diuretics are not effective at lowering blood calcium, so in hypercalcaemia (high blood calcium) they are used only if fluid overload develops. In nephrotic syndrome (a kidney condition with heavy protein loss in the urine), a thiazide-type diuretic may be added if a loop diuretic alone does not work well enough. Spironolactone is used for hypertension as an add-on in resistant hypertension.
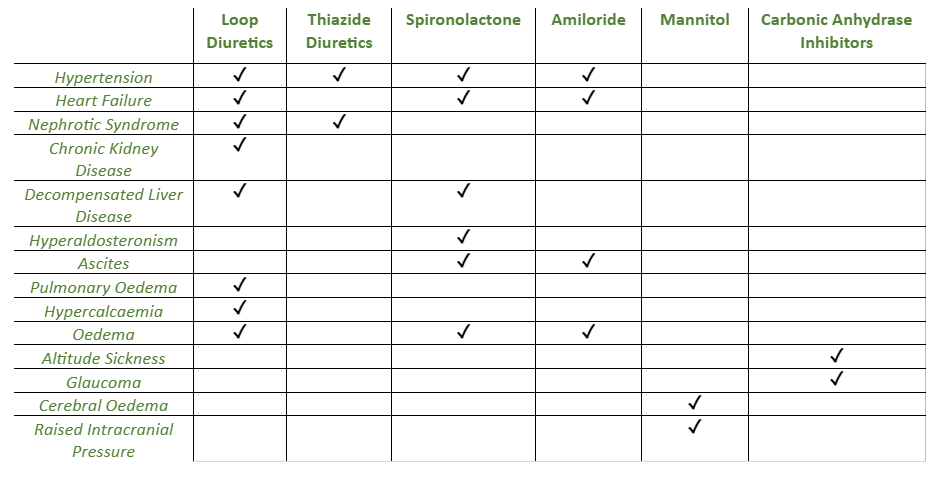
Table - The Main Uses of Diuretics
SimpleMed original by Dr. Thomas Burnell
Edited by: Dr. Maddie Swannack
Reviewed by: Adrian Judge and Dr. Marcus Judge
- 808
