

By Dr. Sachin Sudhakaran and Dr. Maddie Swannack
Next Lesson - Cranial Nerves VII-XII
Core
Introduction to Cranial Nerves
The cranial nerves are 12 pairs of nerves with various motor, sensory, special sensory and autonomic functions. Most are connected with the brain or brainstem, but the spinal component of the accessory nerve arises in the upper cervical spinal cord.
For clarity, a special sensory function is the carrying of one of the special senses: vision, taste, smell, hearing and balance. General sensory functions carry other sensations, such as touch, pain and temperature.
The 12 cranial nerves and their functions are as follows. Helpful tips for remembering these are shown in the blue columns:
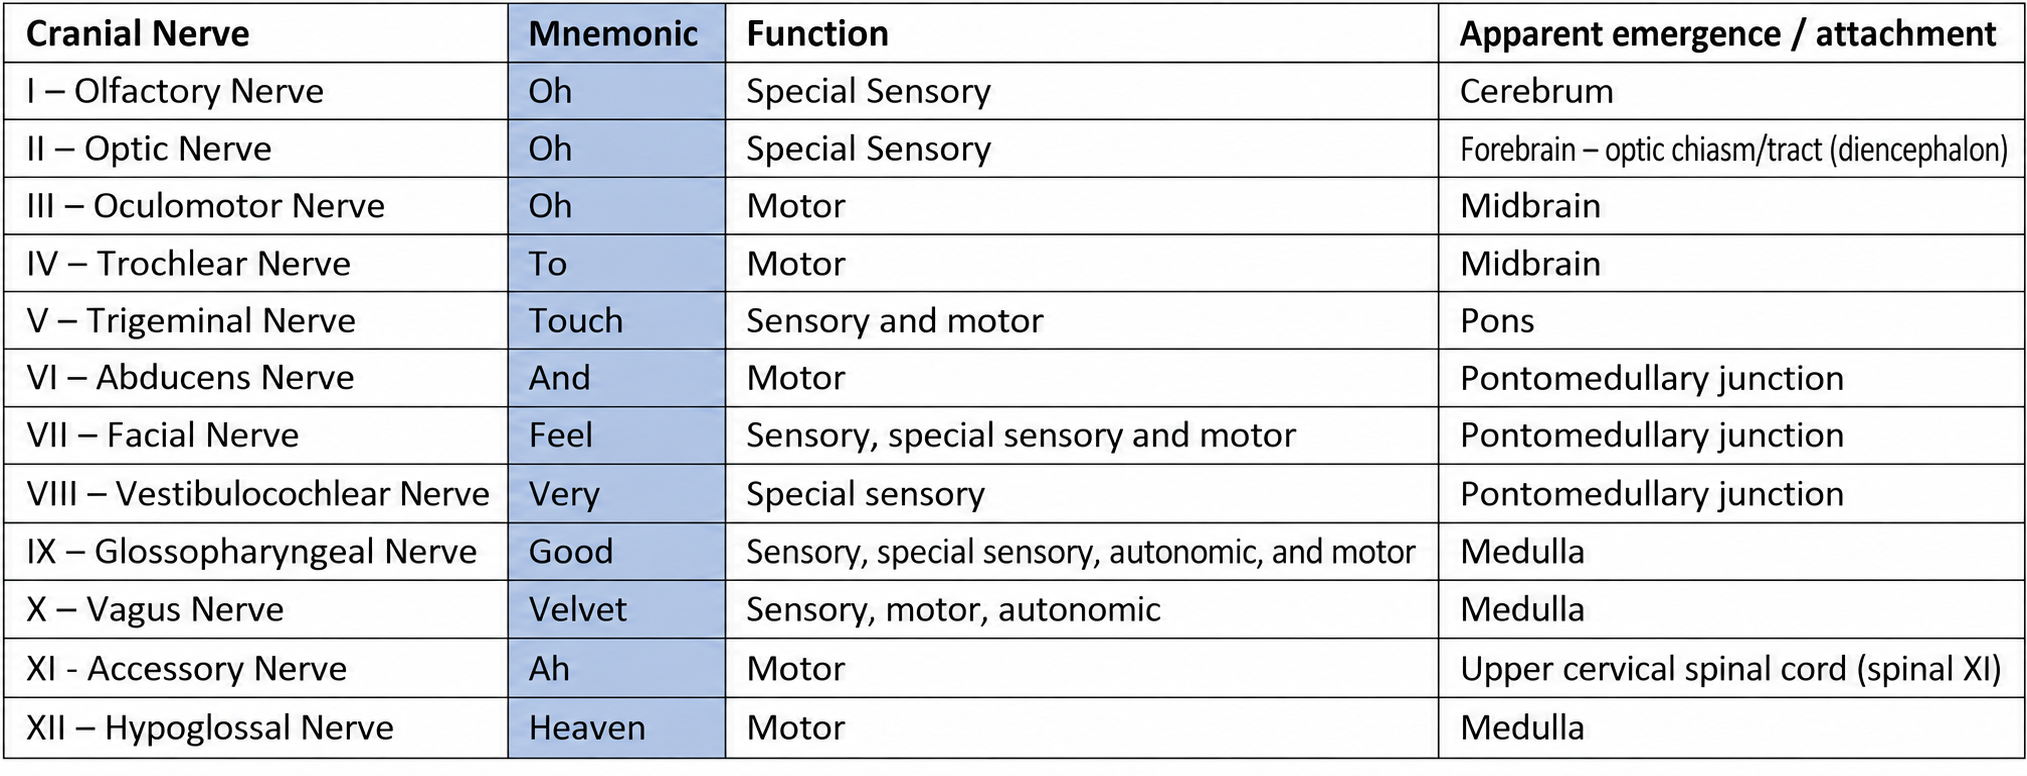
Table - Cranial nerve functions and apparent emergence or attachment. V emerges from the pons; VI, VII and VIII emerge at the pontomedullary junction. Spinal XI arises in the upper cervical spinal cord. The functional categories are broad summaries; III, VII, IX and X also carry parasympathetic fibres.
SimpleMed Original by Dr. Sachin Sudhakaran
The image below shows the anatomical origins of the cranial nerves.
The first 2 nerves, the olfactory and optic nerves, arise from the forebrain (the front part of the brain), not the brainstem.
The next 2 nerves emerge from the midbrain - oculomotor and trochlear.
The trigeminal nerve (V) emerges from the pons itself. The abducens (VI), facial (VII) and vestibulocochlear (VIII) nerves emerge at the pontomedullary junction, where the pons meets the medulla.
The glossopharyngeal (IX), vagus (X) and hypoglossal (XII) nerves emerge from the medulla. The spinal accessory nerve (XI) arises from the upper cervical spinal cord and ascends through the foramen magnum (the large opening at the base of the skull). It then leaves the skull through the jugular foramen (another opening in the skull base). The traditionally described cranial component arises from the medulla and joins the vagus nerve; this does not make spinal XI a medullary nerve.

Diagram - Inferior view showing cranial nerve attachments. VI, VII and VIII attach at the pontomedullary junction; the ascending spinal roots of XI arise in the cervical spinal cord. The traditional cranial component of XI joins X (the vagus nerve).
Creative commons source by OpenStax [CC BY 4.0]
This article will cover the path and function of the first six cranial nerves.
Function
These nerves are used in providing the sense of smell (olfaction).
Pathway
Found at the roof of the nasal cavity, fibres from the olfactory nerve pass through the cribriform foramina (literally ‘sieve holes’) of the cribriform plate. This plate is a feature of the ethmoid bone of the skull, a thin bone between the nose and the brain.
Once inside the skull, these nerve fibres enter the olfactory bulb, an oval structure where they synapse (connect) with the next nerve cells in the pathway. From the olfactory bulb, a bundle of fibres called the olfactory tract runs backwards to the primary olfactory cortex (the area that first receives smell signals), which lies in the temporal lobe of the brain.
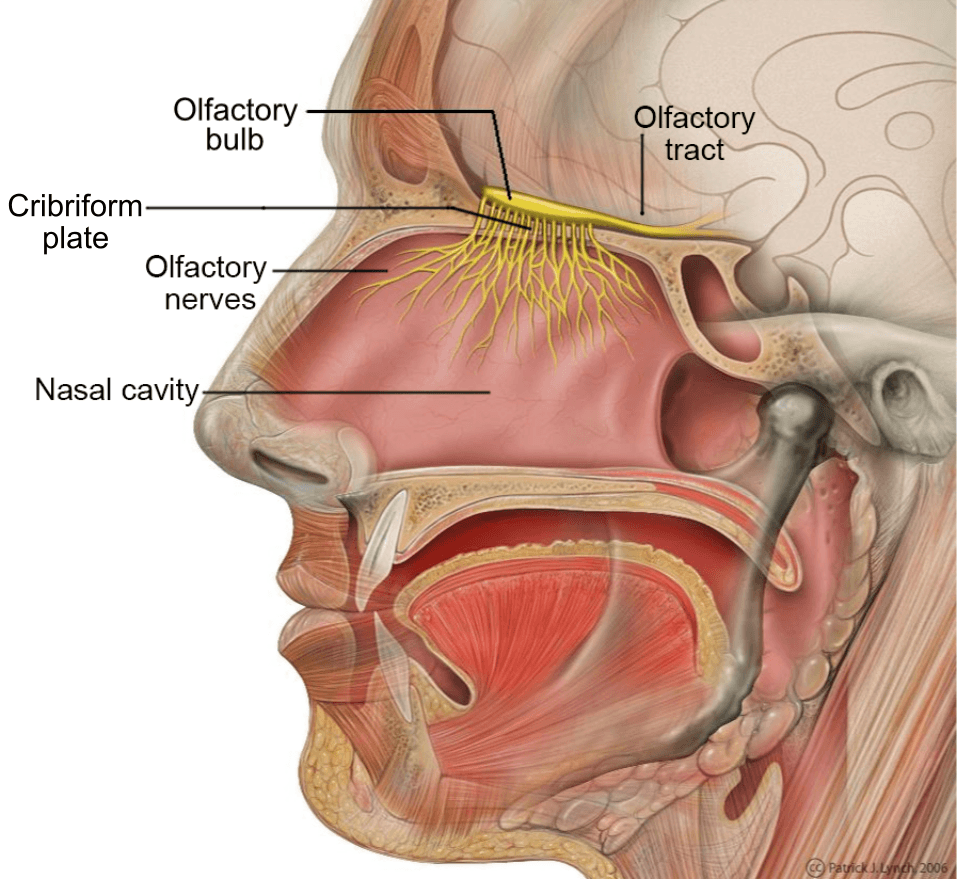
Diagram - Illustration showcasing the path of the olfactory nerve from the roof of the nasal cavity. Remember that the olfactory tract extends posteriorly to the temporal lobe
Creative commons source by Patrick J. Lynch [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Pathology
Pathology of this nerve has several causes. Anything that blocks odours from reaching the nerve can cause loss of smell, for example inflammation, infection or nasal polyps (soft swellings in the lining of the nose). When the nose and sinuses are not involved, infection and head injury are the most common causes. Sudden trauma to the nerve, such as a fracture of the ethmoid bone in a road traffic accident, is one example. External compression, for example by a tumour near the olfactory bulb, can also damage the nerve. Affected patients will report a loss of smell (anosmia).
Testing
To test this nerve, ask the patient about any change in their sense of smell and, where appropriate, test each nostril separately using a familiar, non-irritant odour.
Function
These nerves are used in providing the sense of vision.
Pathway
Very simply put, light enters the eye and hits the photoreceptor cells (the light-detecting cells) of the retina (the light-sensitive layer at the back of the eye). This generates graded electrical signals, which ultimately lead to action potentials in the retinal ganglion cells (the nerve cells whose axons form the optic nerve). The action potentials travel along the optic nerve and then along the rest of the visual pathway (described below) to the visual cortex of the brain. There they are interpreted as vision. The optic nerve leaves the orbit (the eye socket) through the optic canal, a passage in the sphenoid bone (the butterfly-shaped bone at the base of the skull).
To properly understand how the optic nerves of a patient are functioning it is important to understand the concept of visual fields.
Visual Fields
When describing the eye, the terms temporal (closer to the temporal bone, on the outer side) and nasal (closer to the nose, on the inner side) are used in place of lateral and medial. The visual fields are also divided into 4 quadrants. A visual field is the area of the world that a person can see. Each part of the visual field is detected by a matching part of the retina.
When light enters the eye, it will strike the contralateral side of the retina, meaning the side opposite to where the light came from. As shown in the diagram below, light from an object to the side of the patient (temporal vision) will hit the nasal surface of the retina, and vice versa.
To further complicate things the same occurs with light coming from above or below the patient. Light coming from above the patient will hit the inferior surface of the retina, and vice versa.
In summary, light from an object in the inferior temporal visual field (below and towards the temple) will hit the superior nasal part of the retina.
We do not perceive the world upside down or back to front, because the brain corrects for this effect. Nevertheless, the way light lands on the retina is an important fact to keep in mind when assessing for lesions (areas of damage) along the visual pathways.
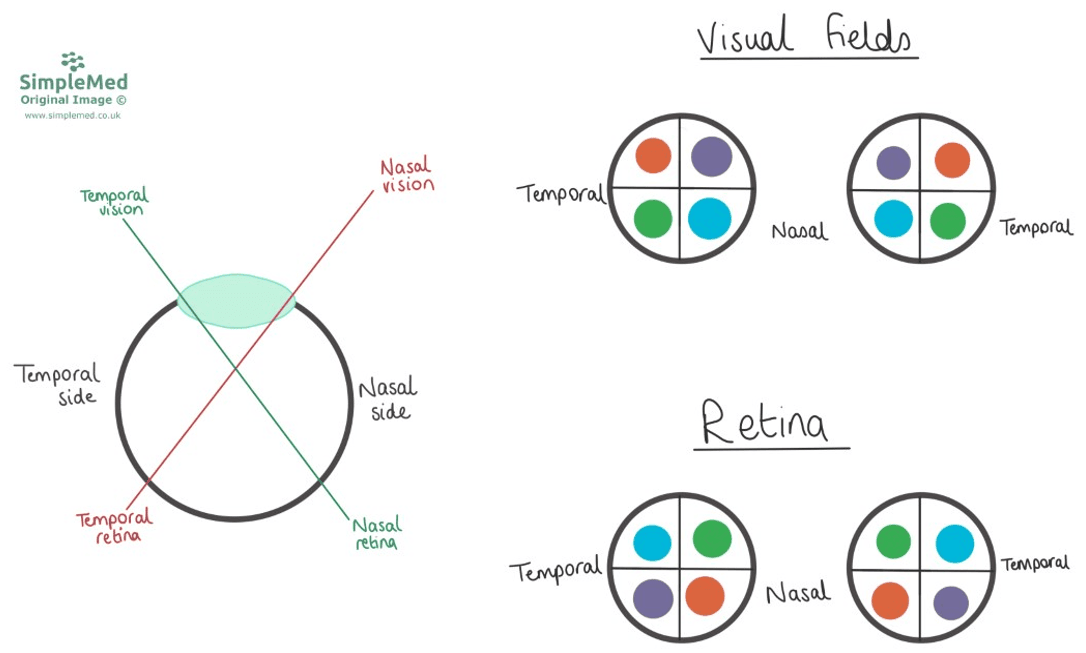
Diagram - How light enters the eye and hits the contralateral side of the retina, and how this leads to the visual fields corresponding to the retinal areas (with the same areas shown in the same colours), e.g. the orange object is above and lateral to the patient, but the image is seen on the inferior nasal quadrant
SimpleMed original by Dr. Maddie Swannack
The optic nerve fibres on the surface of the retina converge to form the optic nerve. The two optic nerves then travel posteriorly to the optic chiasm (the point where they meet). At this chiasm, fibres from the nasal retina decussate (swap sides) and fibres from the temporal retina remain on the same side. Exiting this chiasm are the optic tracts. Each tract carries information from the ipsilateral temporal retina (on the same side as the tract) and the contralateral nasal retina (in the opposite eye). For example, the left optic tract carries the information from the left half of both retinas. Together these detect the right visual field (the right-hand half of what both eyes see). This is shown in the image below.
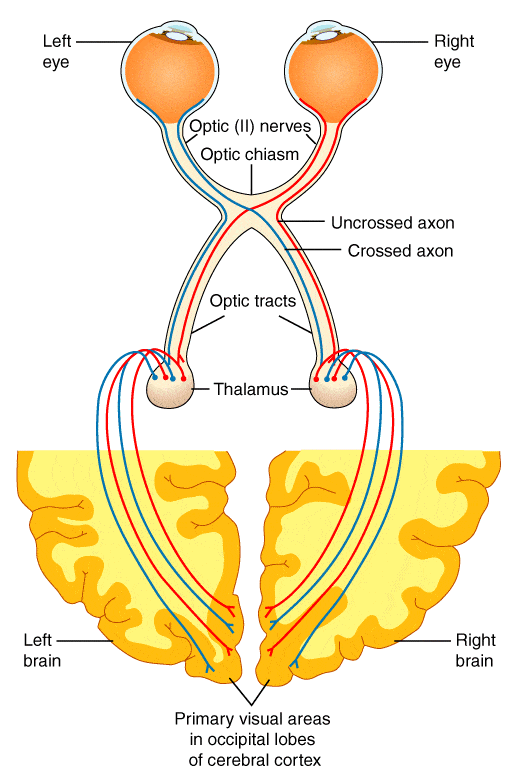
Diagram - The pathway of the visual system
Creative commons source by Wiley [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
The optic tracts extend to the lateral geniculate nuclei (the relay stations for vision, one on each side) in the thalamus. From each lateral geniculate nucleus, two bundles of fibres called optic radiations run to the primary visual cortex in the occipital lobe (at the back of the brain).
There are two radiations - the superior optic radiations which travel through the parietal lobes and the inferior optic radiations which travel through the temporal lobes. The superior radiations carry fibres from the superior retina, and so from the inferior half of the visual field.
Likewise the inferior radiations carry fibres from the inferior retina, and so from the superior half of the visual field.
Pathology
Lesions (areas of damage) along the visual pathway give different patterns of visual loss depending on the site. For example, direct compression of the optic chiasm by a pituitary tumour could cause bitemporal hemianopia, which is loss of the outer half of the visual field in both eyes. This will be covered more in the Neuroanatomy Unit.
Testing
The optic nerve is tested in several ways: visual acuity, colour vision, pupillary responses to light, and the visual fields. Visual acuity means how sharp the vision is, for example with Snellen charts (which are letter charts).
It is equally important to look at the retina through fundoscopy (examining the back of the eye), using an ophthalmoscope (a handheld instrument with a light and lenses).
Movement of the Eyeball - Cranial Nerves III, IV and VI
Primary Functions
There are six muscles that control movement of the eyeball. The four easiest to understand are called superior rectus, inferior rectus, medial rectus and lateral rectus. When they contract, they pull the eyeball in the direction of their name e.g. the superior rectus moves the eye superiorly (looking upwards).
The two remaining muscles are called the superior oblique and inferior oblique. These muscles attach to the eye at an oblique angle. As a result, when they contract, they rotate the eyeball. This means that superior oblique is responsible for the intorsion (internal rotation) of the eyeball, and inferior oblique is responsible for the extorsion (external rotation) of the eyeball. This movement is key in keeping the visual image stable when the head is tilted to the side.
All the muscles work antagonistically to each other to keep the eye in position. If a muscle loses its tone, the other muscles will pull away from it and move the eye out of position. For example, if the superior rectus is weak, the eye will be pulled inferiorly.
These are all shown in the diagram below:
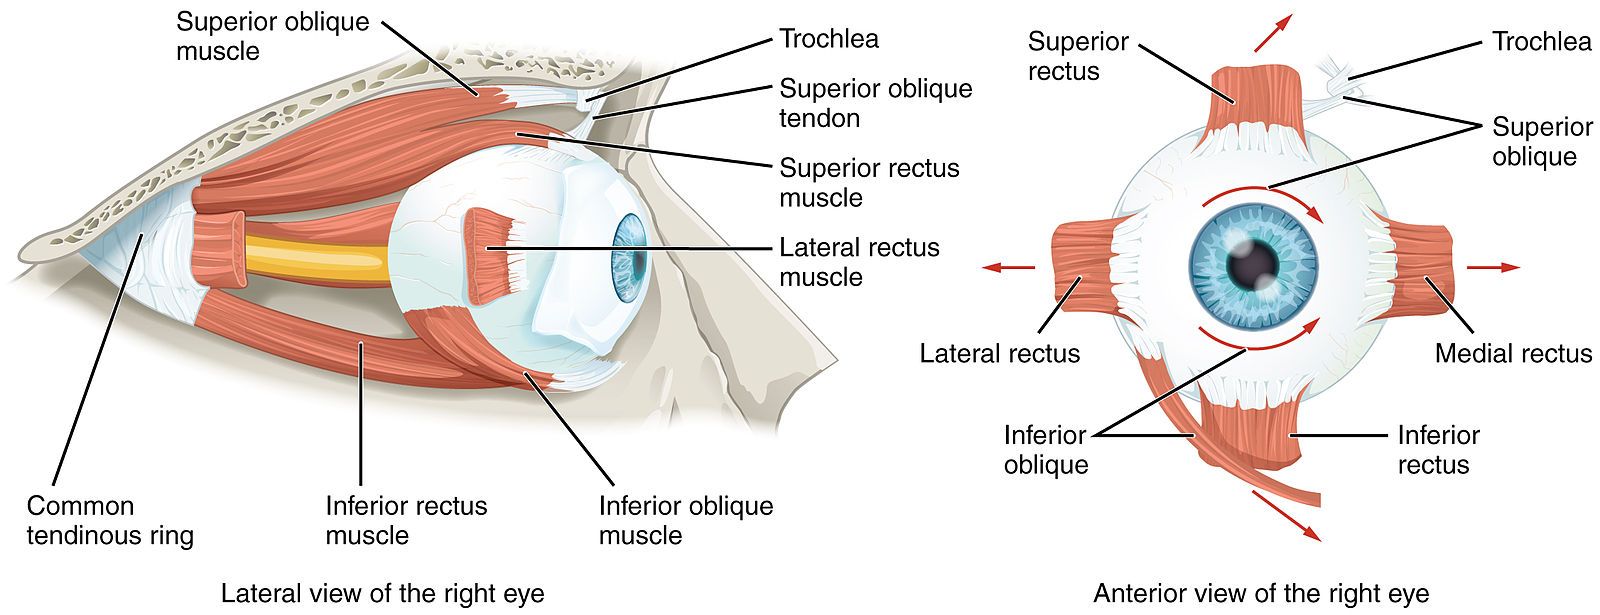
Diagram - The extra-ocular (eye-moving) muscles of the right eye. Note the oblique paths of the superior and inferior oblique muscles
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Secondary Functions
Some of the muscles also have secondary directions of pull, shown in the table below:
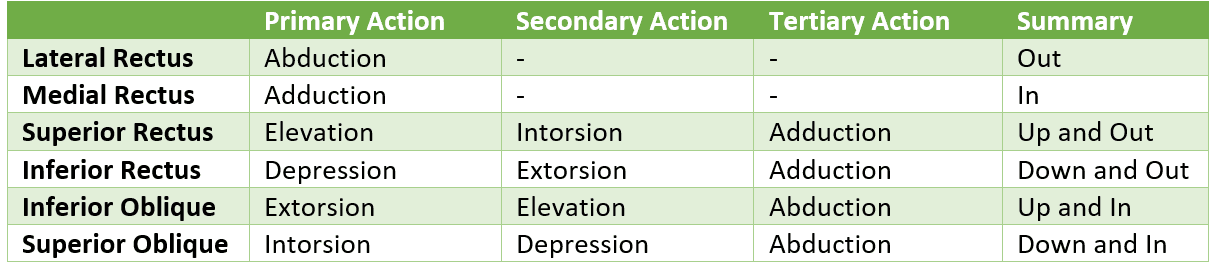
Table - The secondary functions of the extraocular muscles
This table can be quite complicated - the important thing to remember is the primary function.
Also remember that if the function of a muscle is lost, the eye will move in the opposite direction because the pull of the other muscles is unopposed.
Innervations
The six muscles which move the eye are innervated by one of three cranial nerves.
- Superior Rectus - Oculomotor (III)
- Superior Oblique - Trochlear (IV)
- Medial Rectus - Oculomotor (III)
- Inferior Rectus - Oculomotor (III)
- Inferior Oblique - Oculomotor (III)
- Lateral Rectus - Abducens (VI), so called as the lateral rectus abducts the eye
Which nerve supplies which muscle is difficult to remember. The mnemonic ‘LR6 SO4’ may act as an aid. This will help with knowing that the lateral rectus is innervated by cranial nerve VI (abducens) and that superior oblique is innervated by cranial nerve IV (trochlear). The rest are innervated by cranial nerve III (oculomotor).
Cranial Nerve III - Oculomotor
Function
The oculomotor nerve innervates four of the extra-ocular muscles (listed above and shown in image below). In addition, it innervates levator palpebrae superioris (responsible for elevating the eyelid) and sphincter pupillae (constricts the pupil). It also carries autonomic parasympathetic fibres.

Diagram - The extraocular muscles of the eye. The highlighted muscles are innervated by the oculomotor nerve
Creative commons source by OpenStax College, edited by Dr. Sachin Sudhakaran [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Pathway
Originating from the midbrain, fibres from the oculomotor nerve travel through the cavernous sinus (a blood-filled channel beside the pituitary gland). They then pass through the superior orbital fissure (a gap at the back of the orbit) to reach the muscles that the nerve supplies.
Pathology
Pathology of this nerve has several causes. In a population-based study from the USA, the most common cause was presumed microvascular disease, at 42% of cases. This means damage to the small blood vessels that supply the nerve, for example in diabetes or high blood pressure. Next came trauma (12%), external compression by a tumour (11%), brain surgery (10%) and compression by an aneurysm (a bulge in an artery wall, 6%). Raised intracranial pressure (pressure inside the skull) and cavernous sinus thrombosis (a blood clot in the cavernous sinus) can also affect the nerve.
Patients with pathology of this nerve usually have diplopia (double vision) and severe ptosis (drooping of the upper eyelid), due to loss of innervation to the levator palpebrae superioris muscle. They may also have a dilated (blown) pupil, due to loss of parasympathetic impulses to the sphincter pupillae muscle. A dilated pupil is more likely when the nerve is compressed (for example by an aneurysm) than in microvascular disease, but a normal pupil does not rule out compression. A new third nerve palsy needs urgent medical assessment, especially if the pupil is dilated.
The patient will present with the affected eye in a ‘down and out’ position (lateral and inferior) due to the paralysis of four of the extra-ocular muscles. This leaves only lateral rectus and superior oblique functioning, pulling the eye laterally and inferiorly.

Image - Patient presenting with a ‘down and out’ position of the left eye. Notice that the eyelids have to be retracted (pulled open); this is most likely because of ptosis of the left eye secondary to an oculomotor nerve lesion (damage to the nerve)
Creative commons source by Wang Y, Wang XH, Tian MM, Xie CJ, Liu Y, Pan QQ, Lu YN [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Testing
To test this nerve:
- Inspect the eyelids and pupils (check for asymmetry)
- Test the eye movements (using the H test - see below)
- Test the pupillary reflexes
Function
A nerve with purely motor function, this nerve innervates the superior oblique muscle, which primarily intorts and depresses the eye, particularly when the eye is adducted.
Pathway
Originating from the dorsal aspect of the midbrain, this nerve passes through the cavernous sinus and superior orbital fissure before innervating the superior oblique muscle. This nerve has the longest intracranial length of the cranial nerves.
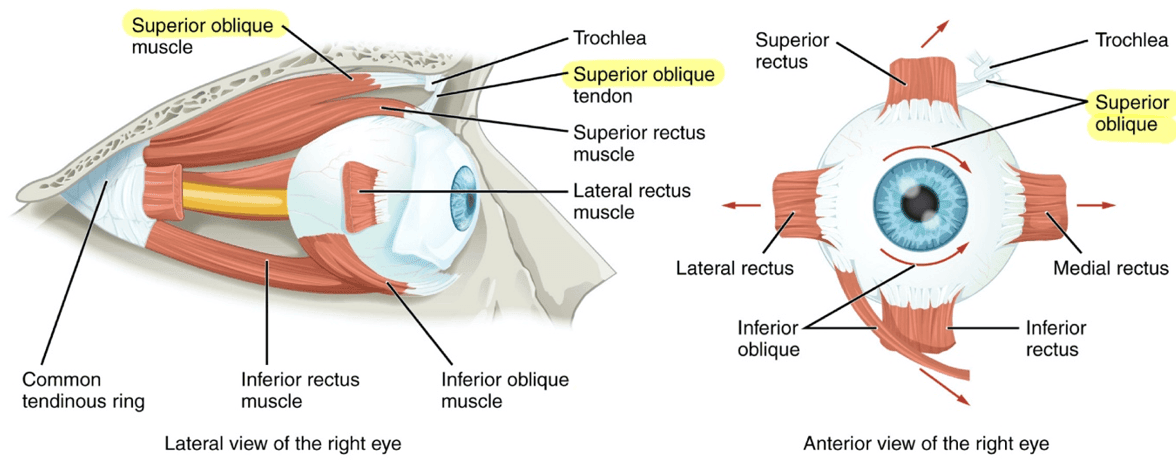
Diagram - The extra-ocular muscles of the eye. The highlighted muscles are innervated by the trochlear nerve
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Pathology
In a population-based study from the USA of isolated trochlear nerve palsy (palsy of this nerve on its own), the most common cause was presumed congenital (present from birth), at 49% of cases. High blood pressure (18%) and trauma (injury, 18%) came next, and a tumour was the cause in only 1%. Raised intracranial pressure (pressure inside the skull) can also affect the nerve. The nerve has a long course inside the skull, which makes it more vulnerable to injury.
Patients with trochlear nerve palsies (weakness or paralysis of the nerve) commonly complain of a downward gaze diplopia. This means vertical double vision that is worse when looking down and inwards, for example when reading or walking downstairs. This is because the affected eye has a weakness in looking down, so will not be able to follow the normal eye to the inferior position. Patients can also develop a head tilt away from the affected side.
The affected eye may appear slightly elevated and extorted (rotated outwards) because the depression and intorsion actions of the superior oblique are lost. This is most marked when the eye is adducted (turned towards the nose).
Testing
Test this nerve by testing eye movements (using the H test - see later).
Function
Like the trochlear nerve, this nerve has only one function, which is motor: it innervates the lateral rectus of the eye, which is involved in abducting the eye.
Pathway
Emerging at the pontomedullary junction, the abducens nerve passes through the cavernous sinus and the superior orbital fissure before innervating the lateral rectus muscle.
Pathology
Patients with pathology of the abducens present with diplopia (double vision). The affected eye cannot abduct and rests turned inwards (adducted), because the medial rectus is unopposed. In one population-based study the most common associations were high blood pressure and diabetes, which can damage the small blood vessels supplying the nerve. Trauma, multiple sclerosis (an autoimmune disease that damages the insulating coat of nerves in the brain and spinal cord) and tumours were less common, and in many cases no cause was found. A space-occupying lesion (such as a tumour) or raised intracranial pressure (pressure inside the skull) can push the brainstem downwards. This stretches the nerve where it leaves the brainstem at the pontomedullary junction.
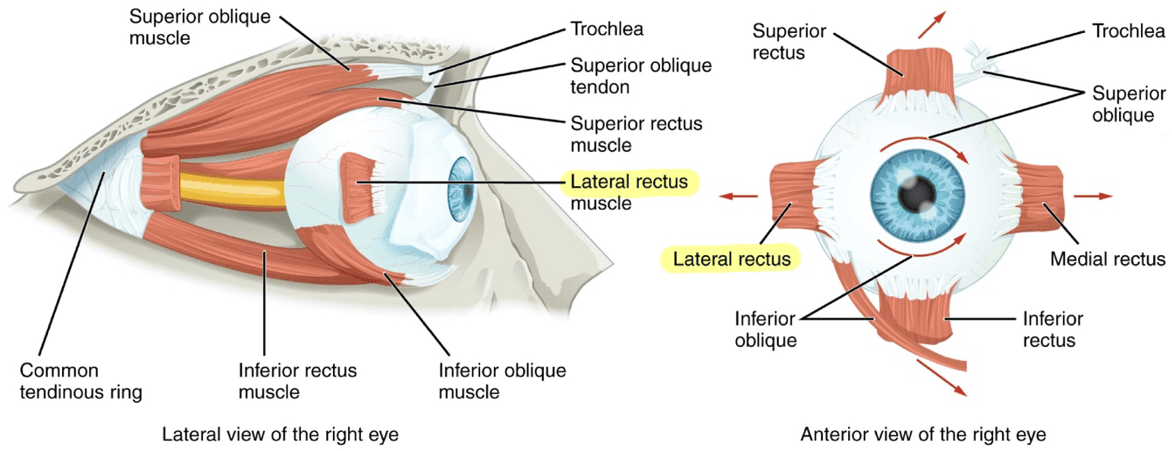
Diagram - Extra-ocular muscles of the eye. Highlighted muscles are innervated by the abducens
Creative commons source by OpenStax College [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Testing
To test this nerve, test the eye movements (using the H test).
All three nerves that control eye movement can be tested through one test, called the H test.
The test is conducted by having the patient keep their head still and follow the movements of a finger or pen. The aim is to evaluate the activity of specific eye muscles by performing movements which isolate their action.
Performing the H Test
First, set the patient up with their eyes in a neutral position. Ask the patient to follow your finger or pen with their eyes whilst keeping their head still to isolate the movements of the muscles of the eye. Ask the patient to report if they see double at any point. If the patient normally wears spectacles, make sure they wear them for the test.
For clarity, this example details the muscles of the left eye during the test (see diagram below); however, when carrying out the test both eyes are observed simultaneously.
Move the pen to the left side of the patient’s head (lateral to the left eye) to abduct the left eye. This tests the function of the lateral rectus muscle, and therefore the abducens nerve (VI).
Next move the pen superiorly. This tests the function of the superior rectus muscle and therefore the oculomotor (III) nerve.
Still on the left side of the patient’s head, move inferiorly. This tests the function of the inferior rectus and therefore the oculomotor (III) nerve.
Return the pen to the centre (the midline of the patient’s vision). Slowly move the pen across the centre of the vision to the right side of the patient’s head, medial to the left eye, to adduct the left eye. This tests the function of the medial rectus and therefore the oculomotor (III) nerve.
Still on the right side, move superiorly. This tests the function of the inferior oblique muscle and therefore the oculomotor (III) nerve.
Still on the right side, move inferiorly. This tests the function of the superior oblique muscle and therefore the trochlear (IV) nerve.
By the end of the test your pen should have traced an ‘H’ in the air in front of the patient’s face.
This test can be difficult to describe in words, so refer to the diagram below for clarification.
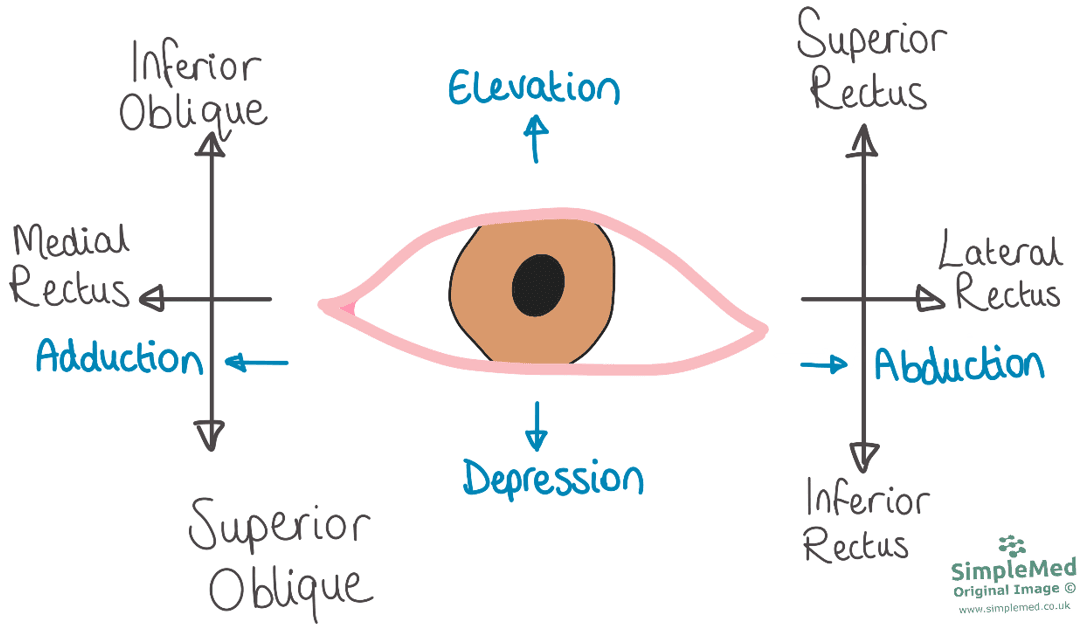
Diagram - The muscles involved in the ‘H Test’ when performed on the left eye. Eye movements tested are listed in blue, and the muscles that are isolated by performing that movement are shown on the ends of the ‘H’
SimpleMed original by Dr. Maddie Swannack
Function
The trigeminal nerve supplies sensory function to the face. It also supplies the muscles of mastication (chewing).
Pathway
Arising from the pons, this nerve splits into 3 branches at the trigeminal ganglion:
Ophthalmic Branch (Cranial Nerve V1)
Passing through the cavernous sinus and the superior orbital fissure, this nerve provides general sensation to the forehead, eye and nose.
This nerve also provides the afferent (sensory) fibres for the corneal reflex, the involuntary blink reflex that occurs when the cornea (the clear front surface of the eye) is touched. The efferent (motor) limb of the reflex is carried by the facial nerve (VII), which makes the orbicularis oculi muscle (the ring of muscle around the eye) close the eyelids.
Maxillary Branch (Cranial Nerve V2)
Passing through foramen rotundum (a round opening in the base of the skull) via the cavernous sinus, this nerve gives rise to many branches, including these two:
- Superior Alveolar - provides sensation to the upper teeth and gums.
- Infraorbital - provides sensation to the cheeks, lower eyelid and upper lip.
Mandibular Branch (Cranial Nerve V3)
Unlike the previous two branches, this nerve does not pass through the cavernous sinus. Rather, it passes through the foramen ovale (an oval opening in the base of the skull). It then enters the infratemporal fossa (a space at the side of the skull base, deep to the jaw), where it splits into several branches. This is the only division of the trigeminal nerve that also carries motor fibres, which supply the muscles of mastication. Three of its branches are:
- Inferior Alveolar - this branch enters the mandibular canal (a channel in the lower jaw bone). It emerges through the mental foramen (an opening on the front of the lower jaw) as the mental nerve, providing sensation to the lower lip and chin.
- Lingual - providing general sensation to the anterior 2/3 of the tongue.
- Auriculotemporal - providing general sensation to the temple, lateral side of the head and scalp, and the temporomandibular joint (the jaw joint, just in front of the ear).
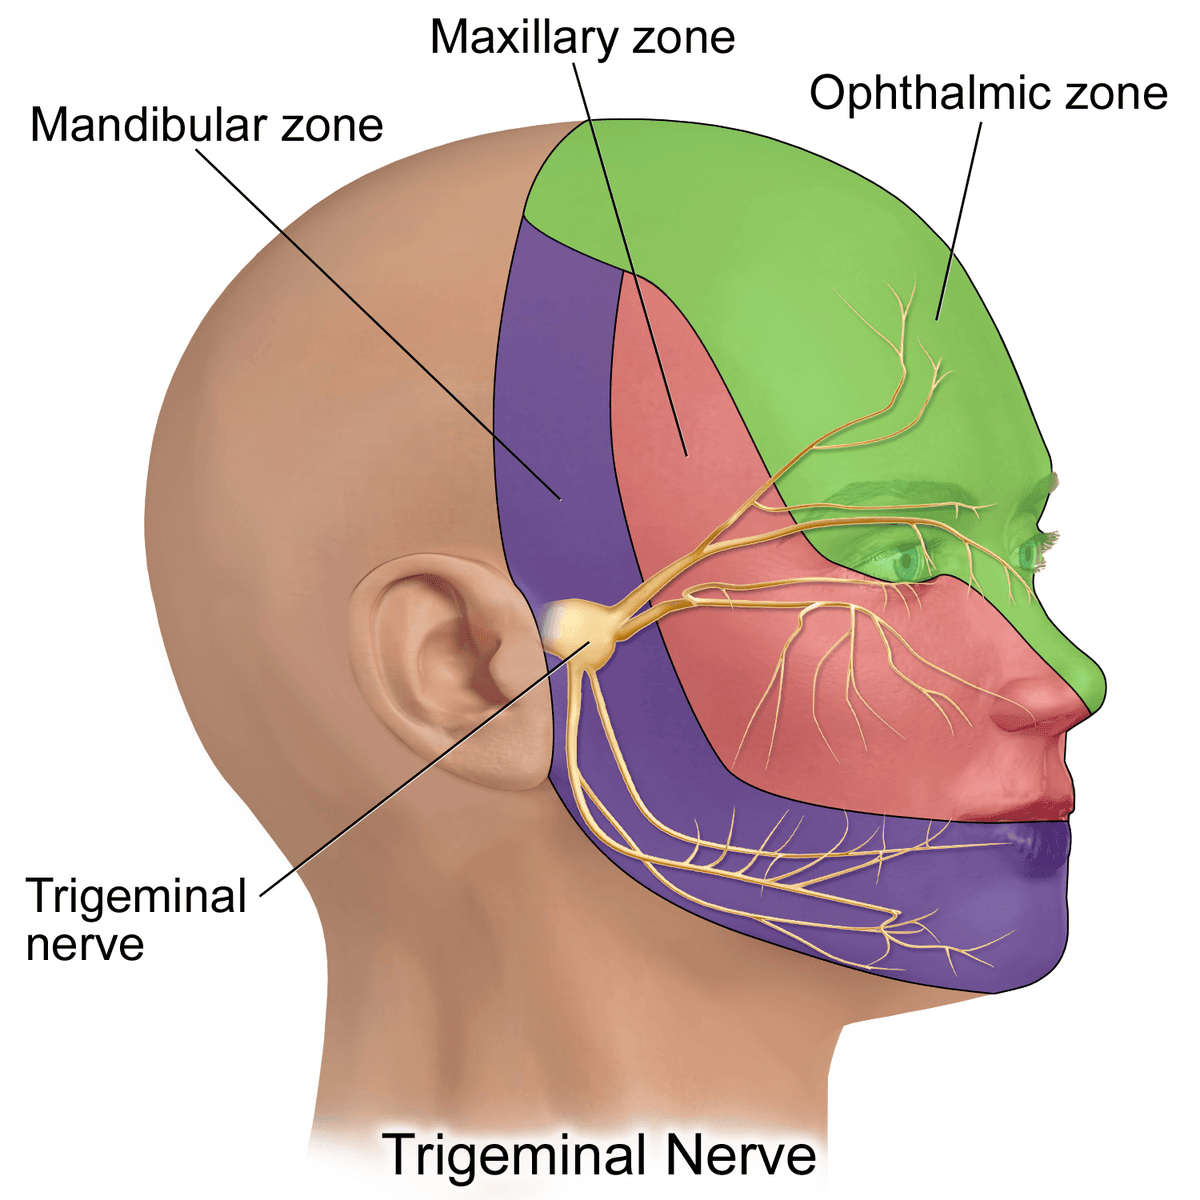
Diagram - The different areas of sensation provided by the different branches of the trigeminal nerve
Creative commons source by BruceBlaus [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Pathology
Trigeminal neuralgia causes severe, sudden attacks of pain in the area supplied by one or more branches of the trigeminal nerve, usually on one side of the face. The pain is excruciating, often described as electrical shocks, and can be triggered by very light contact with the face, for example when washing or brushing the teeth. In most cases the cause is compression of the nerve root by a blood vessel. This compression can lead to loss of the nerve’s insulating myelin coat (demyelination). Less often it is caused by another condition, such as multiple sclerosis or a tumour. Carbamazepine (an anticonvulsant drug that prevents seizures and also slows pain signals in the nerves) is the usual first treatment, and specialist advice is needed if it does not work or is not tolerated.
Testing
This nerve is tested by examination of sensation to touch in areas innervated by each of its branches. Testing the corneal reflex is also possible: a wisp of cotton wool is touched lightly to the cornea and the patient should blink. It is also used to assess patients who are unconscious.
The motor function of the nerve is tested by palpation of the muscles of mastication whilst the jaw is clenched. The patient is then asked to move their jaw from side to side.
Edited by: Dr. Ben Appleby
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 22951



