

Next Lesson - Urinary Tract Infections
Core
Causes of Urinary Tract Obstruction
A urinary tract obstruction is any obstruction that occurs to the outflow of urine. This can happen at any level in the urinary tract, from the kidneys to the urethral opening.
The causes of urinary tract obstruction can be categorised into supra-vesical (above the bladder, i.e. ureteric) or infra-vesical (below the bladder i.e. urinary retention) pathologies. The causes are outlined below and will be discussed in more detail later.
Supra-vesical obstruction can be caused by either an extraluminal (external compression of the ureter) or intraluminal (pathology within the ureter or ureteric walls) abnormality.
- Retroperitoneal malignancy - cancer in the retroperitoneum (the space behind the peritoneum, the lining of the abdomen, where the kidneys and ureters lie). It may start there, or it may spread to the lymph nodes there (metastases), most commonly from breast, gynaecological and prostate cancer.
- Direct obstruction by a tumour - bladder cancer can obstruct the ureters at the vesicoureteric junction (VUJ). Locally advanced prostate cancer can also obstruct the urethra, but that is a lower tract (infra-vesical) cause, covered under urinary retention below.
- Retroperitoneal fibrosis - excess connective tissue around the ureters compresses them (see below).
The most common intraluminal cause of ureteric obstruction is a stone within the urinary tract. The blockage causes renal colic (severe pain that comes in waves). Obstruction can also be caused by blood clots (clot colic) or sloughed papilla (necrosis of the renal papillae in which dead cells are discarded into the lumen of the ureter).
This is a rare condition in which excess connective tissue forms in the retroperitoneal space of the abdomen.
There are many causes:
- Idiopathic (no known cause)
- Malignancy - breast, lung, stomach, lymphoma, and others
- Autoimmune
- Drugs
- Abdominal Aortic Aneurysm (AAA)
This fibrosis can cause compression of the ureters as they (along with the kidneys) are retroperitoneal structures. This is therefore a cause of extra-luminal, supra-vesical obstruction.
Treatment of retroperitoneal fibrosis usually includes draining the blocked ureters, using a ureteric stent (a thin tube placed inside the ureter) or a nephrostomy (a tube placed through the skin into the kidney). A possible underlying malignancy is excluded (this may require biopsies). Steroids are the main medical treatment, sometimes with other immunosuppression (drugs that dampen the immune system). Surgery to free the ureters from the fibrous tissue (ureterolysis) is usually kept for patients who do not respond to this.
Renal colic is a very common cause of acute ureteric obstruction. Classically, it presents with colicky pain (pain which comes on in waves) that spreads from the loin (the side of the back between the ribs and the hip bone) to the groin, and with haematuria (blood in the urine), which may be non-visible (apparent only on urinalysis, a test of the urine such as a dipstick).
By far the most common cause of renal colic is kidney stones - though it may be caused by blood clots, and sloughed papillae. Renal colic usually occurs unilaterally (on one side), although it can be bilateral. Pyonephrosis (pus in an obstructed kidney, covered below) can develop if there is an infection of the collecting system (the part of the kidney that collects urine and drains it into the ureter) proximal to the obstruction.
Risk Factors for Kidney Stones
The following are risk factors for the development of kidney stones:
- Male Gender - men have a greater incidence of kidney stones compared to women (about 2 to 3 times higher), although the difference is narrowing
- Age - the incidence of kidney stones peaks between the ages of 40 and 50 years, and is lower in children and elderly people
- Metabolic - hypercalcaemia (a high level of calcium in the blood) can predispose a patient to develop kidney stones
- Family History
- Dehydration
- Hypertension
- Increased BMI
- Anatomical Abnormalities - for example: polycystic kidney disease (many fluid-filled cysts in the kidneys), horseshoe kidney (the two kidneys are joined together), and pelviureteric junction (PUJ) stenosis (a narrowing where the kidney meets the ureter)
Kidney stones can be differentiated based on their chemical make-up:
- Calcium Oxalate - the most common type of stone
- Calcium Phosphate - includes the minerals apatite and brushite (two forms of calcium phosphate)
- Struvite Stones - magnesium ammonium phosphate stones associated with urease-producing bacteria (bacteria that make urease, an enzyme that breaks down urea) and alkaline urine
- Uric Acid Stones - favoured by persistently acidic urine; ammonium urate stones form under different biochemical conditions
- Hydroxyapatite - a calcium phosphate mineral, so this overlaps with the calcium phosphate category above
- Cystine Stones - occur in cystinuria, an inherited transport disorder causing excessive urinary cystine; cystine is less soluble in acidic urine
One imaging technique is KUB Radiography (x-ray of the kidneys, ureters, and bladder). This will allow for the identification of calcium containing stones as these are radiopaque (so will appear white on x-ray). On plain KUB radiography, uric acid stones are radiolucent (they do not show up on x-ray), whereas cystine stones have poor radiopacity and may be difficult to see. A negative KUB does not exclude a stone. Non-contrast CT KUB is more sensitive for stone detection. NICE advises urgent (within 24 hours) low-dose non-contrast CT KUB for adults with suspected renal colic. Ultrasound is offered instead in pregnancy. Children and young people have ultrasound first, and low-dose CT is only considered if the diagnosis is still uncertain.
Kidney stones are likely to obstruct the ureter in three places, where the renal tract is the narrowest:
- Pelviureteric Junction (PUJ) - the junction between the renal pelvis and the ureter. The ureter is significantly smaller in diameter than the renal pelvis so stones can become stuck here.
- Pelvic Brim - this is where the ureters cross over the top of the common iliac arteries (the large arteries supplying the pelvis and legs). This is an area of narrowing so again stones can become lodged here.
- Vesicoureteric Junction (VUJ) - the junction between the ureters and the bladder. The acute angle of entry of the ureters into the bladder causes a ‘u-bend’ which is a common site for stones to become lodged.
Some kidney stones will pass through the urinary tract without significant problems due to their small size, and the only management needed may be adequate analgesia (pain relief) and good hydration. NICE advises a non-steroidal anti-inflammatory drug (NSAID) as the first-line pain relief for suspected renal colic.
Surgical management may be needed in some cases:
- Stone is unlikely to pass by itself. There is no single size cut-off: the chance of passing falls as the stone gets larger. In one study of ureteric stones, 65% of 5mm stones passed within 20 weeks, compared with 9% of stones 6.5mm or wider
- The kidney is obstructed by a stone and infected (an emergency: see Pyonephrosis below)
- Patient is in uncontrolled pain
- Bilateral kidney stones causing obstruction
- The patient only has one kidney which is obstructed by a stone
Stones can be treated surgically via laser lithotripsy (using a laser inside the ureters to break up the stone), extracorporeal shockwave lithotripsy (ESWL; extracorporeal means outside the body, so this is a non-invasive procedure aiming shockwaves at the location of the kidney stone), or percutaneous nephrolithotomy (a thin tube is passed through the skin of the back into the kidney to break up and remove the stone). The choice depends on the size and site of the stone. For adults, NICE advises ESWL as the first choice for kidney and ureteric stones under 10mm, ureteroscopy (a thin telescope passed up the ureter, which is how laser lithotripsy is done) for ureteric stones of 10 to 20mm, and percutaneous nephrolithotomy for kidney stones larger than 20mm. ESWL has a number of risks, and is contraindicated in acute urinary tract infection or urosepsis (sepsis from a urinary source), uncorrected bleeding disorders or coagulopathies (problems with blood clotting), pregnancy, and abdominal aortic aneurysm.
Pyonephrosis is the accumulation of pus within an obstructed renal collecting system, and this is a urological emergency. Failure to decompress (drain and relieve the pressure of) the obstruction may lead to death from sepsis or a permanent loss of renal function. Pyonephrosis should be suspected in patients with an obstructed kidney who develop signs of sepsis.
Pyonephrosis requires urgent drainage of the obstructed collecting system by a ureteric stent (a thin tube placed inside the ureter to keep it open) or percutaneous nephrostomy (a tube placed through the skin into the kidney), alongside immediate antibiotics and sepsis management. Obtain urgent senior urological input to arrange source control (drainage of the infected urine); antibiotics alone do not relieve the infected obstruction.
Pelviureteric Junction (PUJ) Obstruction
PUJ obstruction is impaired drainage from the renal pelvis into the ureter at their junction. It may result from anatomical narrowing or external compression, or functional impairment of peristalsis in the junctional segment. It is usually present from birth, but may appear or be recognised later. PUJ obstruction can present with antenatal hydronephrosis (swelling of the kidney from backed-up urine, seen before birth) which is picked up on an ultrasound scan, but it can also present at any stage of life. It can be asymptomatic, so only found incidentally on imaging, but the classical presentation is loin pain that is worse after heavy fluid intake or alcohol consumption.
When surgical correction is needed, pyeloplasty can be performed using a laparoscopic (keyhole) or open approach. This is the surgical reconstruction of the renal pelvis in an attempt to relieve the PUJ obstruction.
Infra-vesical Obstruction - Urinary Retention
Urinary retention can be classified as acute or chronic, with chronic urinary retention further split into high-pressure and low-pressure retention.
Some causes of urinary retention are specific to male and female anatomy, and some causes are common to both.
Causes of urinary retention in men:
- Benign prostatic hyperplasia (BPH)
- Prostate cancer
- Urethral strictures (narrowing of the urethra)
- Urinary tract infection
- Constipation
- Neurological dysfunction
- Recent surgery
- Drugs
Causes of urinary retention in women:
- Urethral stenosis (narrowing of the urethra)
- Pelvic organ prolapse (the womb, bladder or bowel bulges into the vagina)
- Pelvic masses
- Urinary tract infection
- Constipation
- Neurological dysfunction
- Recent surgery
- Drugs
Acute urinary retention presents with a painful inability to void (pass urine) and a painful, palpable bladder (one that can be felt through the abdomen). Acute retention is usually very painful for patients, so catheterisation is essential both to relieve pain and to prevent complications resulting from the backing up of urine.
Causes of acute urinary retention include:
- BPH - most common cause in men
- Urethral strictures
- Prostate cancer
- Urinary tract infection
- Constipation
- Severe pain
- Medication - antimuscarinic medications (drugs that block the nerve signals that make the bladder muscle contract) and spinal anaesthesia can affect the innervation (nerve supply) of the bladder, which can cause retention
- Neurological - several nerve problems can cause acute urinary retention. Examples are iatrogenic damage (damage caused by treatment) during pelvic surgery, peripheral neuropathy (damage to nerves outside the brain and spinal cord), diseases of the brain and spinal cord such as multiple sclerosis (MS) and, less commonly, Parkinson’s disease, and Bladder-Sphincter Dyssynergia (a disturbance in the co-ordination of the contraction of the detrusor muscle, the muscle of the bladder wall, and the relaxation of the urethral sphincter). Cauda equina syndrome (compression of the nerve roots at the base of the spinal cord) is a rare emergency that can also cause retention, which may be painless. It is usually diagnosed with an MRI scan.
Treatment of acute urinary retention involves:
- Catheterising and recording the volume of urine drained on catheterisation.
- A full examination including abdominal exam, external genitalia exam, and a digital rectal examination (DRE).
- Urine Dip.
- Urea and Electrolytes (U&Es).
- Treat any obvious underlying causes - conditions like constipation can cause acute urinary retention. Not treating the underlying cause can result in another episode of retention.
- Alpha-blockers (drugs that relax the prostate) are offered to men before the catheter is removed, to improve the chance of passing urine afterwards. After the catheter is removed, check over several hours that the man can pass urine freely.
Patients with chronic urinary retention have a long-standing reduced ability to void their bladders. This stretches the detrusor muscle over time and desensitises it, which means that this type of retention is painless. Patients may still be able to void small amounts of urine but are likely to suffer from weak stream and hesitancy. Larger volumes of urine can be retained, from 300-4000ml.
In men, chronic retention is commonly caused by BPH, urethral strictures, or prostate cancer. In women, common causes include pelvic prolapse (the womb, bladder or bowel bulges into the vagina) or pelvic masses. Neurological causes can affect both men and women and include peripheral neuropathy (damage to nerves outside the brain and spinal cord) as well as diseases of the brain and spinal cord, like MS and, less commonly, Parkinson's disease.
Chronic urinary retention can be categorised into high-pressure or low-pressure retention.
In high-pressure retention, the pressure of the retained fluid is so high that it can cause damage to the kidneys, resulting in hydronephrosis and abnormal urea and electrolytes (U&Es). Low-pressure retention will not impact renal function and does not cause hydronephrosis.
The management of chronic urinary retention depends on whether the kidneys are affected. NICE advises checking kidney function (serum creatinine) and imaging the upper urinary tract in men with chronic retention, and catheterisation for men with impaired kidney function or hydronephrosis (high-pressure retention). Surgery on the bladder outlet is another option, and a long-term catheter is used when surgery is unsuitable. Intermittent self-catheterisation (where patients are taught to pass a catheter into the bladder themselves, drain the urine and remove the catheter each time) is considered before an indwelling catheter (one that stays in place).
After treatment, patients with urinary retention should be monitored for complications resulting from post-obstructive diuresis (a large rise in urine output once the blockage is relieved). It starts as a normal physiological response: the body gets rid of the accumulated salt and water that built up during the retention. In a few cases, this can become excessive and severe, leading to dehydration and electrolyte imbalance.
Careful monitoring of fluid input and output and of blood electrolytes (U&Es), together with oral fluid replacement, is usually enough to manage post-obstructive diuresis. Some patients need intravenous fluids, for example if their blood pressure falls significantly.
Patients with chronic urinary retention can develop acute retention. This can be caused by an acute deterioration in the condition causing the chronic retention, or a new condition on top of the previous one. These patients will have very large residual volumes (the volume of urine left in the bladder after passing urine) but still have minimal discomfort due to the desensitisation of the bladder. They should be treated as per the acute retention guidelines, but these patients are more at risk of post-obstructive diuresis so will need careful monitoring.
Obstructive uropathy (a disease of the urinary tract) is a structural or functional hindrance to normal urine flow. The kidneys do not have to be damaged for it to be called obstructive uropathy. Kidney dysfunction resulting from the obstruction is termed obstructive nephropathy. Situations in which obstruction can impair overall kidney function include:
- Bilateral ureteric obstruction
- Unilateral ureteric obstruction in a patient with one kidney
- High-pressure chronic retention
Obstruction complicated by infection, anuria (passing no urine) or acute kidney injury (AKI) needs urgent assessment and urgent relief of the obstruction. NICE advises referring everyone with upper tract obstruction to a urologist, and referring immediately if there is pyonephrosis, an obstructed single kidney, obstruction of both kidneys, or complications of AKI caused by the obstruction. Obstructive nephropathy can cause post-renal AKI (AKI caused by a blockage after the kidney) and hyperkalaemia (high blood potassium).
Treatment involves relieving the obstruction, correcting the underlying cause, and monitoring for the complications of AKI and hyperkalaemia. Upper tract obstructions can be drained using a JJ-stent (a tube going from the renal pelvis to the bladder) or a nephrostomy (a tube from the renal pelvis that comes out through a port in the skin). When AKI is present, NICE advises doing this as soon as possible and within 12 hours of diagnosis.
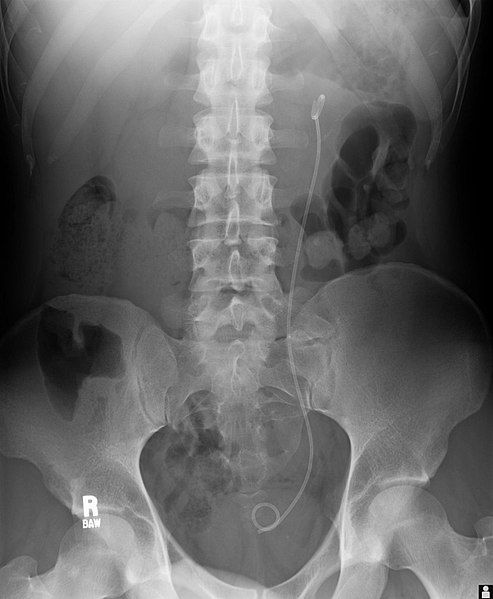
Image - An abdominal x-ray with a left JJ stent
Public Domain Source by Lucid Smog [Public domain]
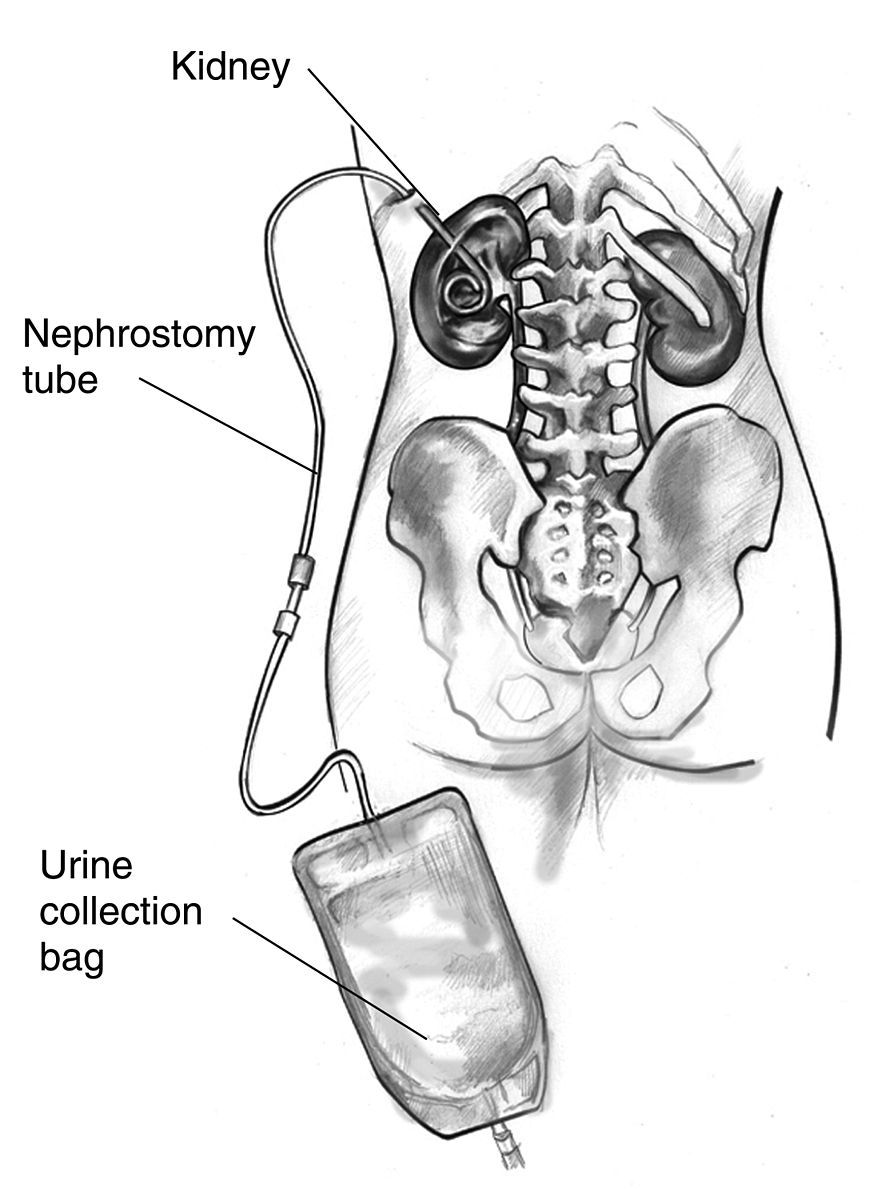
Diagram - A nephrostomy tube in the left kidney, connected to a urine collection bag
Public Domain Source by United States Department of Health and Human Services [Public domain]
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 5455


