

Next Lesson - Hyponatraemia
Core
There are a number of ways in which kidney function can be measured. One of these methods is through measurement of compounds filtered by the kidneys. The constituents of urine can also be analysed to check for underlying renal pathology. Urodynamic tests (tests of how the bladder and urethra work) can also be used to look at how the bladder, sphincter, and urethra store and release urine.
Kidney function is measured in terms of glomerular filtration rate (GFR). GFR is defined as the volume of plasma that is filtered by the glomeruli per unit time. The normal range of GFR is 90-120 mL/min/1.73m2. For a person with a body surface area of 1.73 m2, this corresponds to 129.6-172.8 L of glomerular filtrate per day (filtrate is the fluid filtered out of the blood; 90-120 mL/min multiplied by 1,440 minutes/day). Because the quoted GFR is indexed to body surface area (adjusted to a standard body size of 1.73 m2), the absolute volume filtered also depends on body size. GFR can be measured using the clearance (the volume of plasma cleared of a substance each minute) of a suitable filtration marker (a substance that can be measured in blood and urine). In routine practice, estimated GFR (eGFR) is usually calculated from serum creatinine using a validated equation; measured marker clearance and creatinine-based eGFR are different methods.
There are many factors which can cause temporary or permanent changes in GFR.
Men typically have a higher GFR than women.
In utero (in the womb), nephron development is typically finished by 34 to 36 weeks of gestation (length of pregnancy). Premature babies (born early) and low birth weight infants therefore have fewer nephrons, so their GFR is lower. At birth, GFR is approximately 20 mL/min/1.73 m2, but normal (adult) GFR is reached by around 1 to 2 years of age.
GFR starts to decline again after the age of 30 to 40. The rate of decline after this point is roughly 8 mL/min/1.73 m2 per decade (10 years), with wide variation between people. This is due to the loss of functioning nephrons (more glomeruli become scarred with age) and to a fall in filtration within the nephrons that remain. In order to try and offset this decline, there is some compensatory hypertrophy of the remaining nephrons, but the capacity for hypertrophy also declines with age.
Larger people tend to have larger kidneys than smaller people, and larger kidneys contain more nephrons. Therefore, GFR in larger people is higher.
In pregnancy, GFR increases by around 40-50%, helped by an increase in plasma volume. This is associated with an increase in kidney size of about 1-1.5cm. The growth is attributed to a larger volume of blood vessels and of the supporting (interstitial) tissue, not to new nephrons, so the total nephron number stays the same. GFR returns to its pre-pregnancy level by about 1 month post-partum (after childbirth). Kidney size returns to normal over about 6 months.
Due to the above factors, there is huge variability in the GFR between individuals. If the GFR declines it may be due to the decline in the number of nephrons, or the decline in the filtration ability within individual nephrons. When kidney function declines slowly, individual nephrons may hypertrophy so overall GFR may not fall until significant kidney damage has occurred.
GFR can be measured indirectly by the clearance of a marker that is freely filtered and has no tubular reabsorption or secretion (the tubules are the small tubes that lead on from the glomerulus, so none is taken back into the blood or added to the urine). This differs from estimating GFR using a serum-creatinine equation.
Renal clearance can be calculated with the following equation:
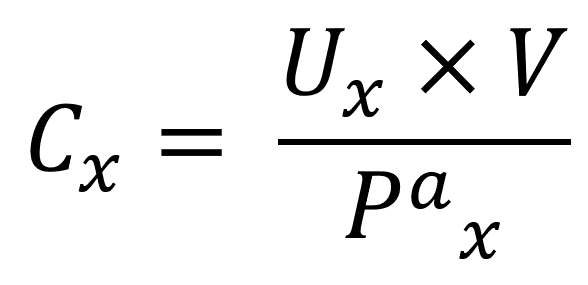
Where C = clearance, U = concentration of the marker in urine, V = urine flow rate, Pa = plasma concentration of the marker, and x = the substance whose clearance is being measured. Urinary and plasma concentrations must use consistent units.
In order to best measure GFR, the substance needs to have these four properties:
- Have an appropriately measured plasma concentration. An endogenous marker (one made inside the body) should have stable generation. An exogenous marker (one given from outside the body) must be administered using a suitable measurement protocol.
- Be freely filtered across the glomerulus.
- Not be reabsorbed in the nephron.
- Not be secreted into the nephron.
If all four of these conditions are true, then the clearance rate will be equal to GFR.
Inulin is an exogenous polysaccharide that is freely filtered and neither reabsorbed nor secreted. Its urinary clearance provides a reference measurement of GFR. The conventional method uses a continuous intravenous infusion to maintain a steady plasma concentration, with timed blood sampling and urine collections. It is cumbersome and is not routinely used for everyday kidney-function assessment. At least one inulin preparation made for this test (Inutest 25%) is no longer marketed. Inulin should not be confused with insulin.
Creatinine is an endogenous substance produced mainly by creatine metabolism in muscle (creatine is an energy store in muscle cells). It is freely filtered across the glomerulus and is not reabsorbed along the nephron. However, it is secreted into the nephron and the rate of production can change dependent on diet and exercise. For this reason it does not measure true GFR - but it is an estimate. Because of tubular secretion (the tubules add extra creatinine to the urine), measured creatinine clearance tends to overestimate GFR. Creatinine clearance is measured by collecting urine over 24 hours - this is cumbersome and frequently inaccurate but it can be used in pregnancy.
51Cr-EDTA (chromium-51 attached to EDTA, ethylenediaminetetraacetic acid) is a radioactively labelled marker which is cleared exclusively by renal filtration. Its clearance is slightly lower than that of inulin (a small amount binds to proteins in the blood), meaning it slightly underestimates GFR. It has been used clinically to measure GFR in children or where a better indication of renal function is required, e.g. in a kidney transplant or in a work-up (the tests done beforehand) to donate a kidney for transplant. Production of 51Cr-EDTA by GE Healthcare ceased in 2020. Other markers can be used instead, such as iohexol (a contrast dye that contains iodine) or 99mTc-DTPA (technetium-99m attached to DTPA, another radioactively labelled marker).
In routine clinical practice, estimated GFR (eGFR) is usually derived from measurements of serum creatinine. Serum creatinine is very easy to measure but can vary greatly between individuals. Equations are used to take other patient factors, such as age and sex, into account. Two have been widely used: MDRD (Modification of Diet in Renal Disease) and CKD-EPI (Chronic Kidney Disease Epidemiology Collaboration), which are described below. NICE recommends the CKD-EPI creatinine equation for adults.
The MDRD calculation takes into account serum creatinine, age, and sex. NICE recommends the CKD-EPI creatinine equation for adults instead. In the past, both equations included an ethnicity adjustment. In 2021 NICE removed its advice to adjust the CKD-EPI creatinine equation for ethnicity.
This calculation is inaccurate in:
- People without kidney disease - for example transplant donors
- Children
- Pregnancy
- Old age
- Bodybuilders or other patients with unusually high muscle mass
- Amputees or other patients with significantly reduced muscle mass
- Patients with kidney function above 60 mL/min
- When true GFR changes quickly - like in AKI (acute kidney injury, a sudden fall in kidney function)
These limitations do not all produce the same direction of error. During recovery from AKI, serum creatinine may remain elevated while filtration improves, so creatinine-based eGFR can underestimate current GFR. During worsening AKI, creatinine may not yet have risen to its new steady-state level, so eGFR can overestimate current GFR. Low muscle mass can also cause overestimation because creatinine generation is reduced; unusually high muscle mass can cause underestimation. Creatinine-based equations assume a steady state and should not be used to diagnose chronic kidney disease from a single result during AKI.
The CKD-EPI equation uses the same variables as MDRD, however, the calculation is slightly different. It is the equation that NICE recommends for adults. It is equally as accurate as MDRD when GFR is below 60 mL/min/1.73 m2 but more accurate when GFR is above 60 mL/min/1.73 m2. It is still not a perfect calculation.
eGFR measurement is less accurate in patients with mild kidney disease. There are three reasons for this:
- A reduction in overall nephron number leads to compensatory hyperfiltration in the remaining nephrons (each one filters more than normal), which can temporarily preserve measured GFR.
- A reduced number of nephrons leads to nephron hypertrophy, which would increase filtration.
- Reduced filtration of creatinine due to reduced GFR results in increased serum creatinine. More creatinine is then actively secreted by the tubules into the nephron, so the serum creatinine rises less than expected and stays closer to its normal level.
These three factors mean that eGFR remains normal, despite there being some mild kidney damage.
Urinalysis is the term given to examining a urine sample. It is most often done with a dipstick test (a thin plastic strip with pads that change colour when they meet certain chemicals in the urine). The urine can also be looked at under a microscope. Urinalysis allows practitioners to screen for common abnormalities in a patient’s urine using chemical markers.
A urinalysis dipstick will give information on the following:
- Specific gravity (density)
- pH
- Leukocytes (white blood cells)
- Blood/Haemoglobin
- Nitrites (chemicals made when some bacteria break down nitrates in the urine)
- Ketones
- Bilirubin
- Urobilinogen (a substance made from bilirubin in the gut, a small amount of which reaches the urine)
- Protein
- Glucose
Some common conditions can cause typical findings on a urinalysis strip, which help to point towards the diagnosis:
- Urinary Tract Infection (UTI) - blood, nitrites, or leukocytes.
- Uncontrolled Diabetes - glucose and ketones.
- Nephrotic Syndrome (a condition in which the kidneys leak large amounts of protein into the urine) - protein (with potentially small amounts of blood).
- Jaundice (yellowing of the skin and eyes) - bilirubin in the urine suggests liver disease or a blocked bile duct. Urobilinogen can be raised in haemolysis (breakdown of red blood cells) and liver disease, and lowered when a bile duct is blocked.
These are just some of the conditions in which urinalysis can help to point towards a diagnosis. Dipstick results can be falsely positive or falsely negative, so they should be interpreted together with the patient’s symptoms and examination, and sometimes with further tests. For example, NICE advises against using standard reagent strips to identify proteinuria (protein in the urine) in adults, and recommends a urine albumin:creatinine ratio (ACR) instead.
There are many advantages to performing a urinalysis. It is very cheap, requires little training to be able to do, can be done at the patient’s bedside or in clinic, and all results are back within two minutes. However, the dipstick is not advised for diagnosing UTI in every adult. In England, the UK Health Security Agency (UKHSA) advises against urine dipsticks for adults over 65 years with suspected UTI and for adults with a urinary catheter. Bacteria can be present in the urine without infection (asymptomatic bacteriuria). This is more common with age, and most adults with a catheter in place for more than one month have bacteria in the bladder or urine without infection. It can make a dipstick positive, so symptoms and signs guide management instead. A urinalysis also only shows a practitioner what is present in the urine and does not give any information as to the filtration function (GFR) of the kidney.
Urodynamics is an umbrella term for a group of more invasive tests which look directly at the function of the bladder, sphincters, and urethra.
Urodynamic tests include:
- Uroflowmetry - the measurement of urine speed and volume.
- Postvoid Residual Measurement - a measurement of the amount of urine left in the bladder after urination.
- Cystometric Testing - a measurement of how much the bladder can hold, how much pressure builds up inside the bladder as it stores urine, and how full the bladder is when the urge to void (pass urine) is felt.
- Leak Point Pressure Measurement - a measurement of the pressure at which leakage occurs in a patient with urinary incontinence during a cystometric test.
- Pressure Flow Studies - a study which looks at the pressure required in the bladder to void and the flow rate that a given pressure generates.
- Electromyography (recording the electrical activity of muscles) - sensors which are used to measure the electrical activity of the muscles around the bladder and sphincters. This is used when a neuromuscular cause (a problem with the nerves or muscles) of a urinary tract problem is suspected.
- Video Urodynamic Tests - taking live X-ray images of the bladder during filling and voiding, using a contrast dye (a liquid that shows up on X-ray) that is put into the bladder as it fills.
These tests provide a direct look at the inner workings of the bladder, sphincters, and urethra. However, they can cause discomfort, and video urodynamics involves exposure to radiation. There is also a small risk of developing a UTI. The results of some tests are available instantly, while others like electromyography may take some days to come back.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 7520
