

Next Lesson - Lung Cancer
Core
The pleural space is defined as the potential space between the visceral and parietal pleura (the visceral pleura covers the lung and the parietal pleura lines the chest wall). It is called a potential space because the two layers normally lie almost touching. The space holds only a tiny amount of fluid. Its pressure is negative because the lungs recoil inwards while the chest wall pulls outwards. A pneumothorax is defined as the presence of air in the pleural space.
Pneumothoraces can be defined by their cause:
A primary spontaneous pneumothorax is, as the name suggests, a pneumothorax that occurs seemingly spontaneously, and not due to any underlying pulmonary pathology. Primary spontaneous pneumothoraces most commonly occur in young, tall, thin males, with no predisposing lung disease or history of trauma. It isn’t fully understood how primary spontaneous pneumothoraces occur. The most common line of thinking is that some people have small blebs (bubble-like structures) on the lung surface which can rupture due to microtrauma (tiny, unnoticed injury), for example in exercise. Smoking greatly increases the risk: in one Swedish study it raised the relative risk of a first spontaneous pneumothorax about ninefold in women and 22-fold in men.
A secondary spontaneous pneumothorax occurs spontaneously as a consequence of underlying lung pathology. This is due to underlying conditions such as COPD (chronic obstructive pulmonary disease), asthma, cystic fibrosis (an inherited condition that makes lung mucus thick and sticky) or interstitial lung disease (scarring of the lung tissue). Pneumothoraces caused by trauma (for example a fractured rib or blunt chest trauma) or that are iatrogenic (caused by a medical procedure or treatment, for example following central venous line insertion, where a long drip is placed in a large vein in the neck, chest or groin) are classified separately.
A tension pneumothorax occurs when a one-way valve system is created at the place where the pleural membrane has been breached. Air can enter the pleural space on inspiration, but can’t leave during expiration. This is because the change in pressure on expiration causes the newly created valve to close.
The trapped air causes an increase in intrapleural pressure (the pressure inside the pleural space), to the point where it exceeds atmospheric pressure, and starts to collapse the lung. This is a medical emergency because the rising intrapleural pressure severely compromises ventilation and venous return (the flow of blood back to the heart), leading to rapid cardiorespiratory collapse.
A person with a pneumothorax will typically present with a sudden onset of pleuritic chest pain, a cough and breathlessness. Pleuritic chest pain is pain that gets worse with deep breathing, sneezing or coughing.
On examination the patient will be dyspnoeic (short of breath) and tachycardic (with a fast heart rate), with reduced chest movements, hyper-resonance (a hollow, drum-like note) on percussion and reduced breath sounds on auscultation. These signs will be found on the affected side. Low blood pressure (hypotension) points to a tension pneumothorax rather than a simple one (see below).
Additional signs and symptoms suggesting a tension pneumothorax include severe respiratory distress, tracheal deviation (the windpipe pushed to one side) away from the pneumothorax, fatigue, a raised JVP (jugular venous pressure) and hypotension. These need to be checked for in any case of suspected pneumothorax because a tension pneumothorax is a medical emergency. Tracheal deviation is described as a late finding and is often absent: in published reports of tension pneumothorax it was recorded in only about 15 to 30% of patients who were breathing unaided. Its absence does not rule out a tension pneumothorax.
Diagnosis of a pneumothorax is usually confirmed with a chest x-ray, which will show an area without lung markings (the fine branching lines of the blood vessels in the lung) where the lung is usually seen. A tension pneumothorax is a clinical diagnosis and should be treated immediately without waiting for imaging; chest x-ray findings such as tracheal deviation may be seen if imaging is obtained.
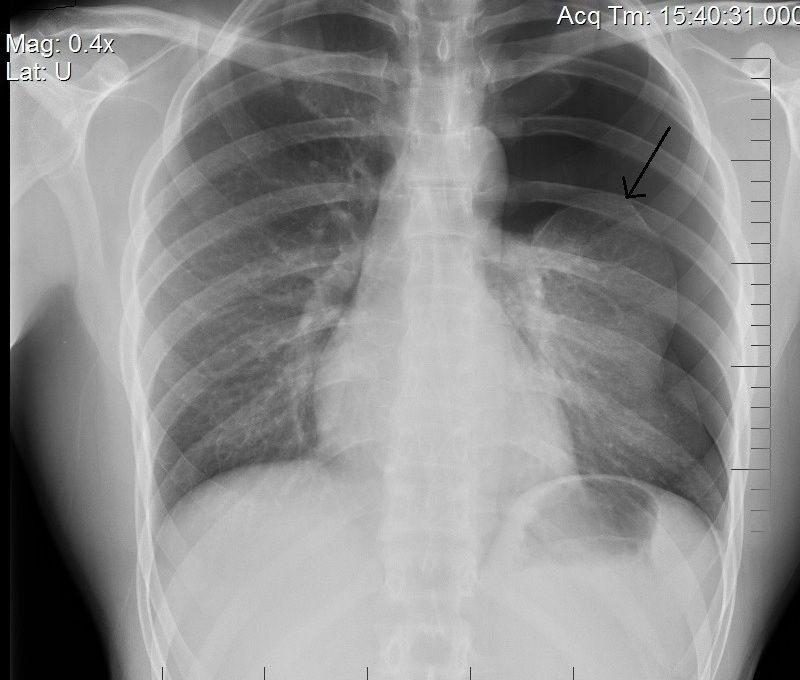
Image - A chest radiograph (x-ray) showing a left-sided pneumothorax, which can be seen by the absent lung markings in the left lung field. The arrow points to the outer edge of the collapsed left lung
Public Domain Source by Mynameisderek [Public domain]
Management of a pneumothorax depends on the type, size and clinical stability of the patient. Options range from observation and oxygen therapy to aspiration or insertion of a chest drain. When a drain is needed, it is inserted through the triangle of safety (the safe area on the side of the chest wall), directly above a rib so that the nerve and blood vessels running below each rib are not damaged. A common site is the fifth intercostal space (the gap between two ribs) at the mid-axillary line (the vertical line down the side of the chest from the middle of the armpit).
In comparison, a tension pneumothorax is a medical emergency and should be treated as soon as possible with the insertion of a wide-bore cannula in the second intercostal space, mid-clavicular line until a chest drain can be inserted.
A pleural effusion is a collection of fluid in the pleural space. Fluid accumulates when formation exceeds clearance. Transudates (watery, low-protein fluid) usually arise from systemic changes in hydrostatic pressure (the pressure pushing fluid out of vessels) or oncotic pressure (the protein pull that keeps fluid in), whereas exudates (protein-rich fluid) arise from local disease that increases permeability or impairs lymphatic drainage. Transudates and exudates are not defined by whether fluid is produced too fast or absorbed too slowly.
Classify an effusion using paired pleural-fluid and serum protein and LDH (lactate dehydrogenase, an enzyme released by damaged cells) measurements with Light’s criteria (listed below), interpreted in the clinical context.
A transudate often has relatively low protein, but a pleural-fluid protein concentration <30 g/L alone is not definitive. Common transudative causes include heart failure, with raised hydrostatic pressure, and nephrotic syndrome (a kidney condition in which protein is lost in the urine), with reduced plasma oncotic pressure. In cirrhosis (scarring of the liver), the most widely accepted explanation is that ascitic fluid (fluid in the abdomen) passes through small defects in the diaphragm into the pleural space, which is called hepatic hydrothorax.
An exudate usually contains more protein because of local inflammation, increased permeability or impaired lymphatic drainage. Causes include malignancy, infection and pulmonary embolism. Protein concentration alone is insufficient to classify an effusion reliably.
Light’s criteria classify pleural fluid as an exudate if any of the following apply:
- Pleural fluid protein to serum protein ratio > 0.5
- Pleural fluid LDH to serum LDH ratio > 0.6
- Pleural fluid LDH greater than two thirds of the upper limit of normal serum LDH
Bilateral effusions often have a systemic transudative cause, such as raised hydrostatic pressure in heart failure or reduced oncotic pressure in hypoalbuminaemia (low blood albumin). A unilateral effusion may suggest a local exudative process, but either type can be unilateral or bilateral. Distribution is a clinical clue, not a substitute for determining the cause and analysing the fluid when indicated.
Symptoms of pleural effusion usually come on gradually, and include breathlessness, chest pain, a cough and symptoms of the underlying cause.
On examination, there may be ‘stony dullness’ on percussion, reduced breath sounds, reduced vocal resonance (the voice sounds quieter through the chest wall) over the effusion, reduced lung expansion. In a large effusion there may also be tracheal deviation away from the site of the effusion. ‘Stony dullness’ is characteristic of an effusion, but is not pathognomonic (it is not found only in effusion): pleural thickening can produce similar findings. Chest imaging, particularly ultrasound, confirms whether pleural fluid is present.
Pleural effusions can be imaged using a chest x-ray, which will show blunting (a sharp corner becoming rounded or filled in) of the costophrenic and cardiophrenic angles (the sharp corners where the diaphragm meets the ribs and the heart), and a meniscal line (a curved upper edge to the fluid, higher at the sides) where the fluid ends.
Ultrasound-guided fluid aspiration (drawing fluid out with a needle, using ultrasound to find a safe site) is advised for an undiagnosed one-sided effusion. The fluid is sent for tests such as cytology (examination of the cells), protein, LDH, glucose, pH and culture, which show whether it is a transudate or an exudate and help to find the cause. Fluid can also be removed to relieve breathlessness (therapeutic aspiration), but unless the underlying cause is treated the effusion is likely to recur.
Large pleural effusions that cause symptoms can be drained. One way is therapeutic aspiration, and BTS advises removing no more than about 1.5 L in one attempt, because very rapid re-expansion of the lung can cause re-expansion pulmonary oedema (fluid in the lung). A chest drain may be used in some cases, for example a small tube to drain pleural infection (infected fluid or pus in the pleural space). For recurrent malignant (cancer-related) effusions, an indwelling pleural catheter (a thin tube left in place so that fluid can be drained at home) or talc pleurodesis (using talc to make the two pleural layers stick together) can be offered. However, definitive management is through treating the underlying cause.
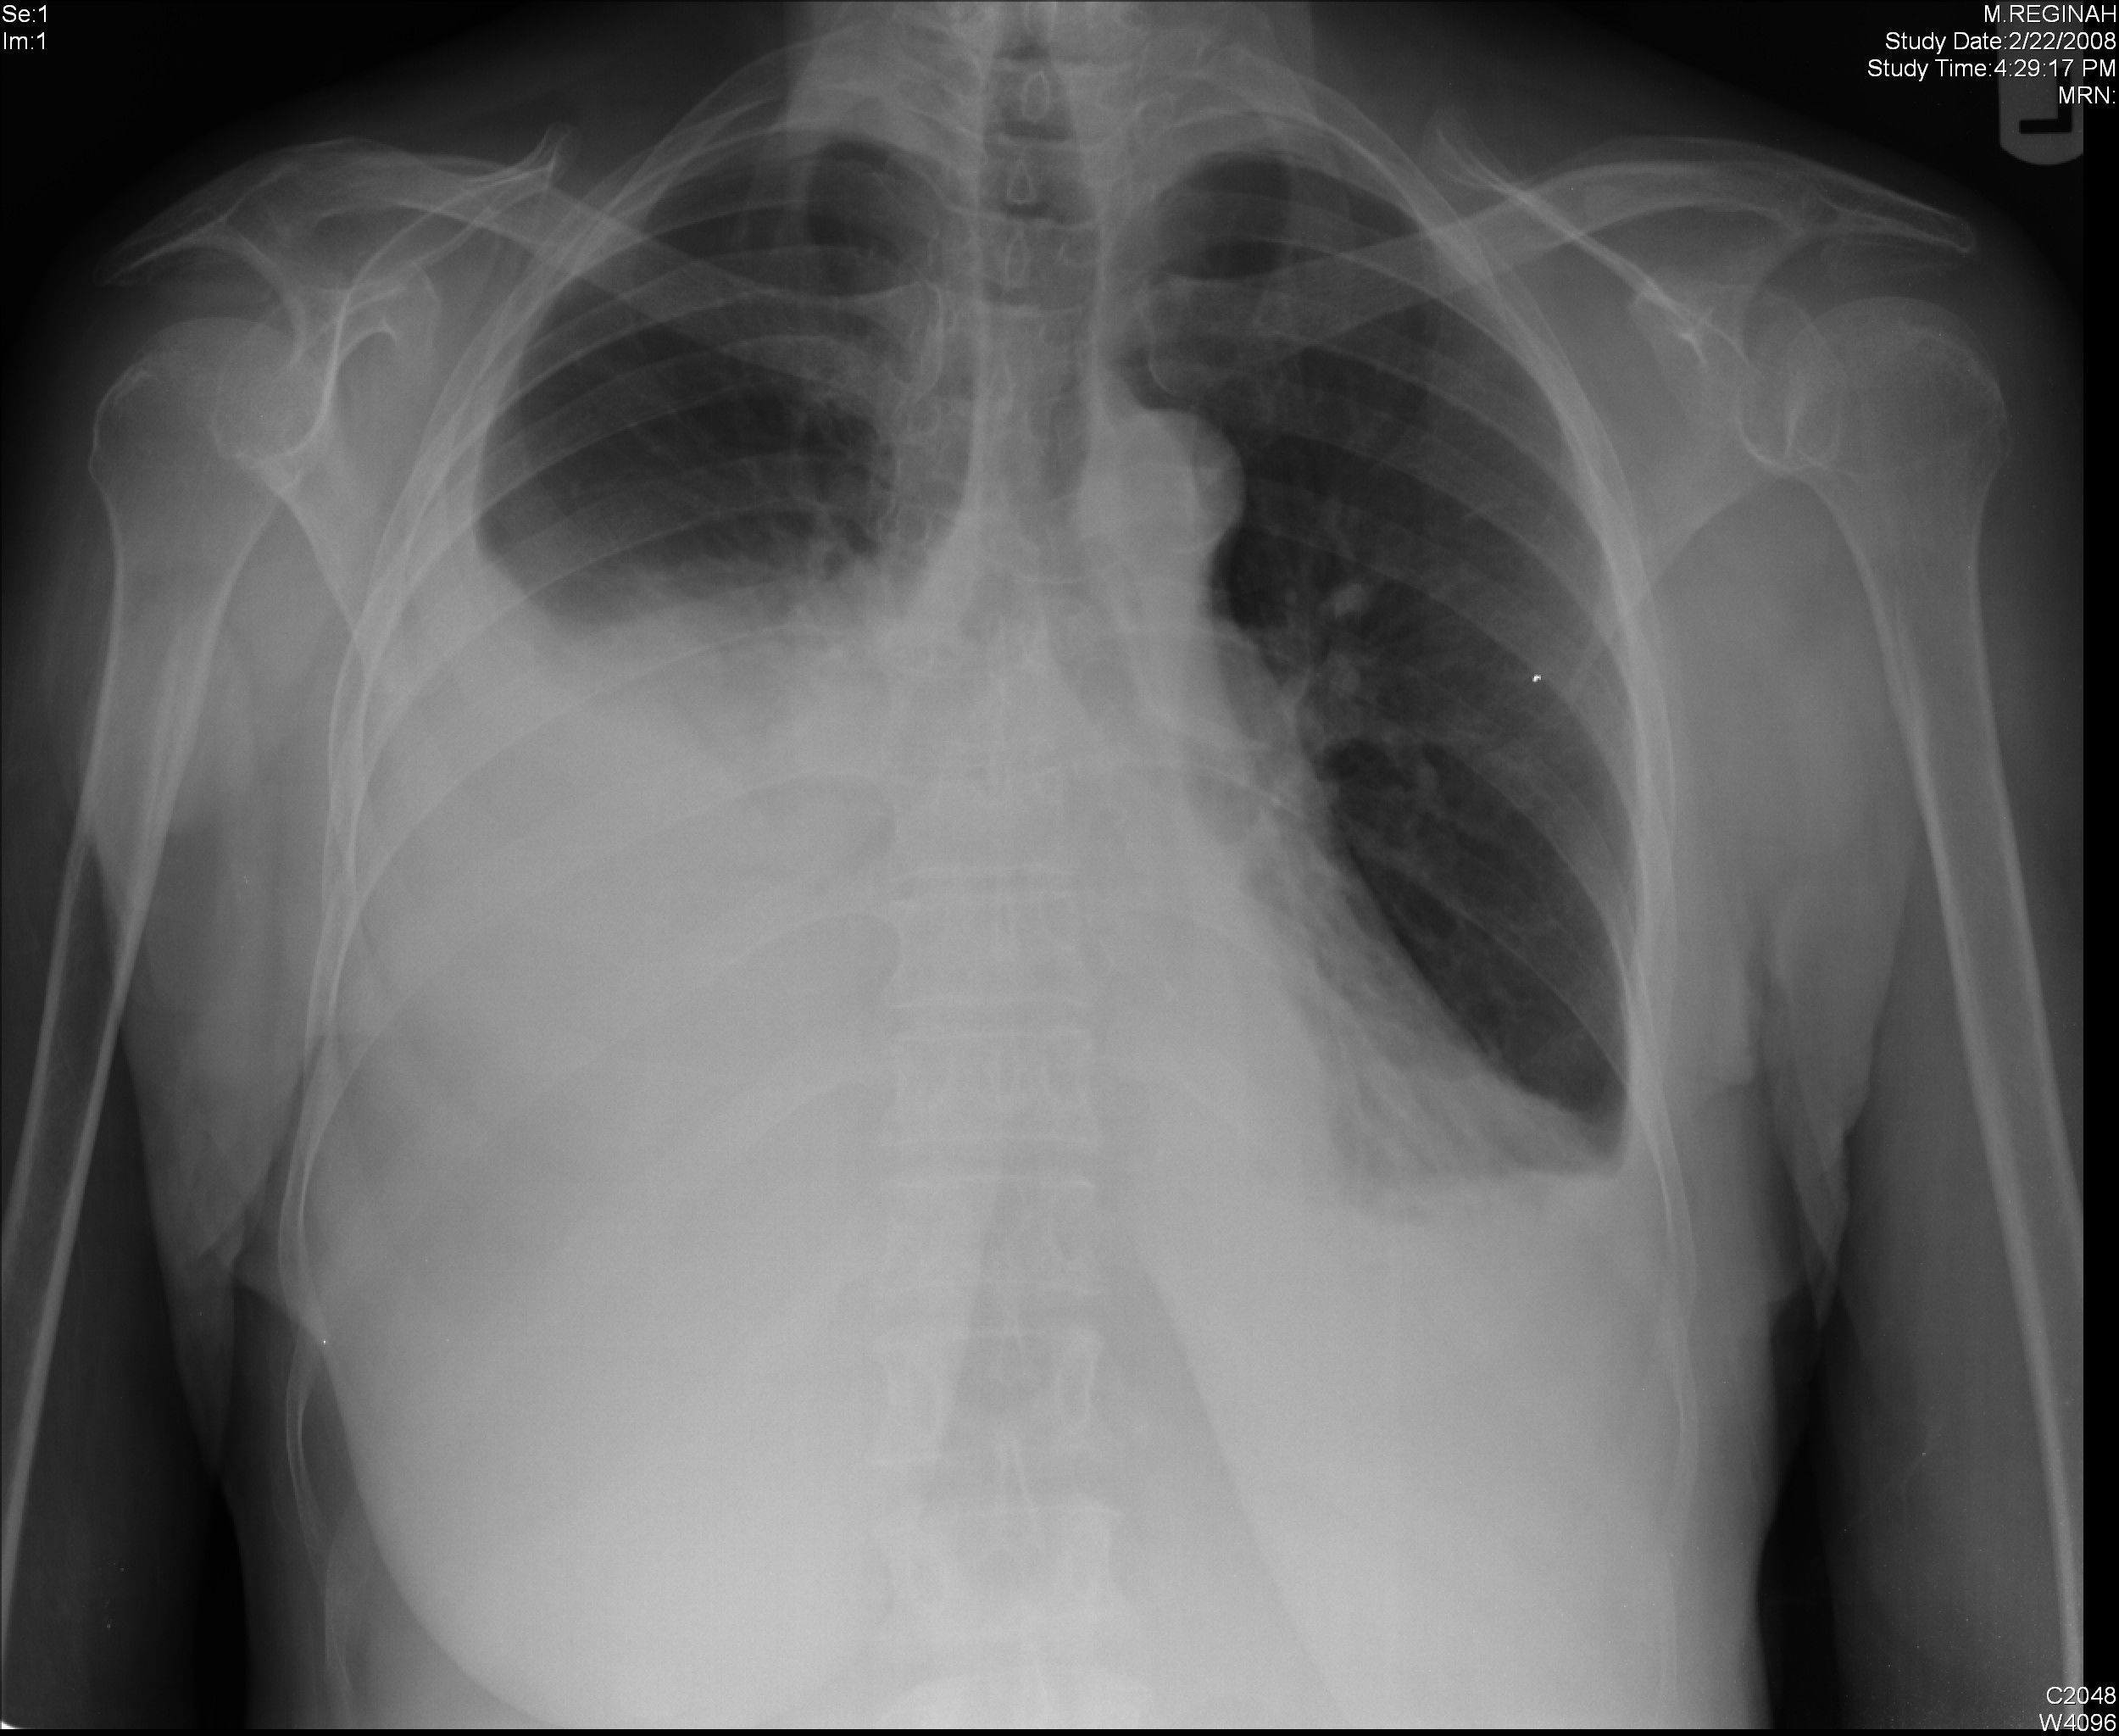
Image - A chest radiograph (x-ray) showing a right-sided pleural effusion. The cardiophrenic and costophrenic angles are completely lost, and a meniscus can be seen at the superior margin of the effusion
Creative commons source by Yale Rosen [CC BY-SA 4.0 (https://creativecommons.org/licenses/by-sa/4.0)]
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 17681

