

By Dr. Thomas Burnell and Dr. Bethany Turner
Next Lesson - Cardiac Conduction and Contraction
Core
If total peripheral resistance (TPR) changes, the heart usually has to change its output (cardiac output = CO) as well, or blood pressure (BP) will change.
Mean arterial BP (the average pressure in the arteries over a heartbeat) ≈ TPR x CO
For example, when metabolism in the muscles increases during exercise, blood vessels dilate to supply muscles with more blood. This causes a fall in TPR. As the equation above shows, arterial pressure would fall too unless cardiac output rises to compensate. The autonomic nervous system brings about this rise through withdrawal of parasympathetic activity and an increase in sympathetic activity. In real exercise, cardiac output rises by more than is needed to offset the fall in TPR, so blood pressure rises somewhat rather than staying the same. Blood pressure stays high enough to perfuse the vital organs.
CO = stroke volume x heart rate
The equation shows how CO is worked out. CO is then combined with TPR to give mean arterial BP.
- Stroke Volume (SV) - determined by:
- The Afterload - the load the ventricles must overcome to eject blood (arterial pressure and resistance in the arteries are often used to estimate it).
- The Preload - how much the ventricles are stretched at the end of diastole (the phase when they relax and fill with blood).
- The Contractility - the strength of the ventricles' contraction at a given filling.
- Heart Rate (HR) - determined by:
- The autonomic nervous system (ANS), which speeds up or slows the heart's own pacemaker (the sinoatrial node). Circulating hormones such as adrenaline also affect heart rate.
The Frank-Starling law describes how greater ventricular filling produces a stronger contraction and a larger stroke volume within the physiological range (the heart's normal working range). This helps the healthy heart match its output to venous return (the blood returning to the heart through the veins).
The link between end-diastolic volume (EDV, the volume of blood in the ventricle at the end of filling) and stroke volume (SV) is not fixed. It depends on contractility and afterload. At a given contractile state and afterload, increasing EDV usually increases SV within the physiological range. The first figure below uses end-diastolic pressure (EDP, the pressure in the ventricle at the end of filling) as a stand-in measure of how full the ventricle is.
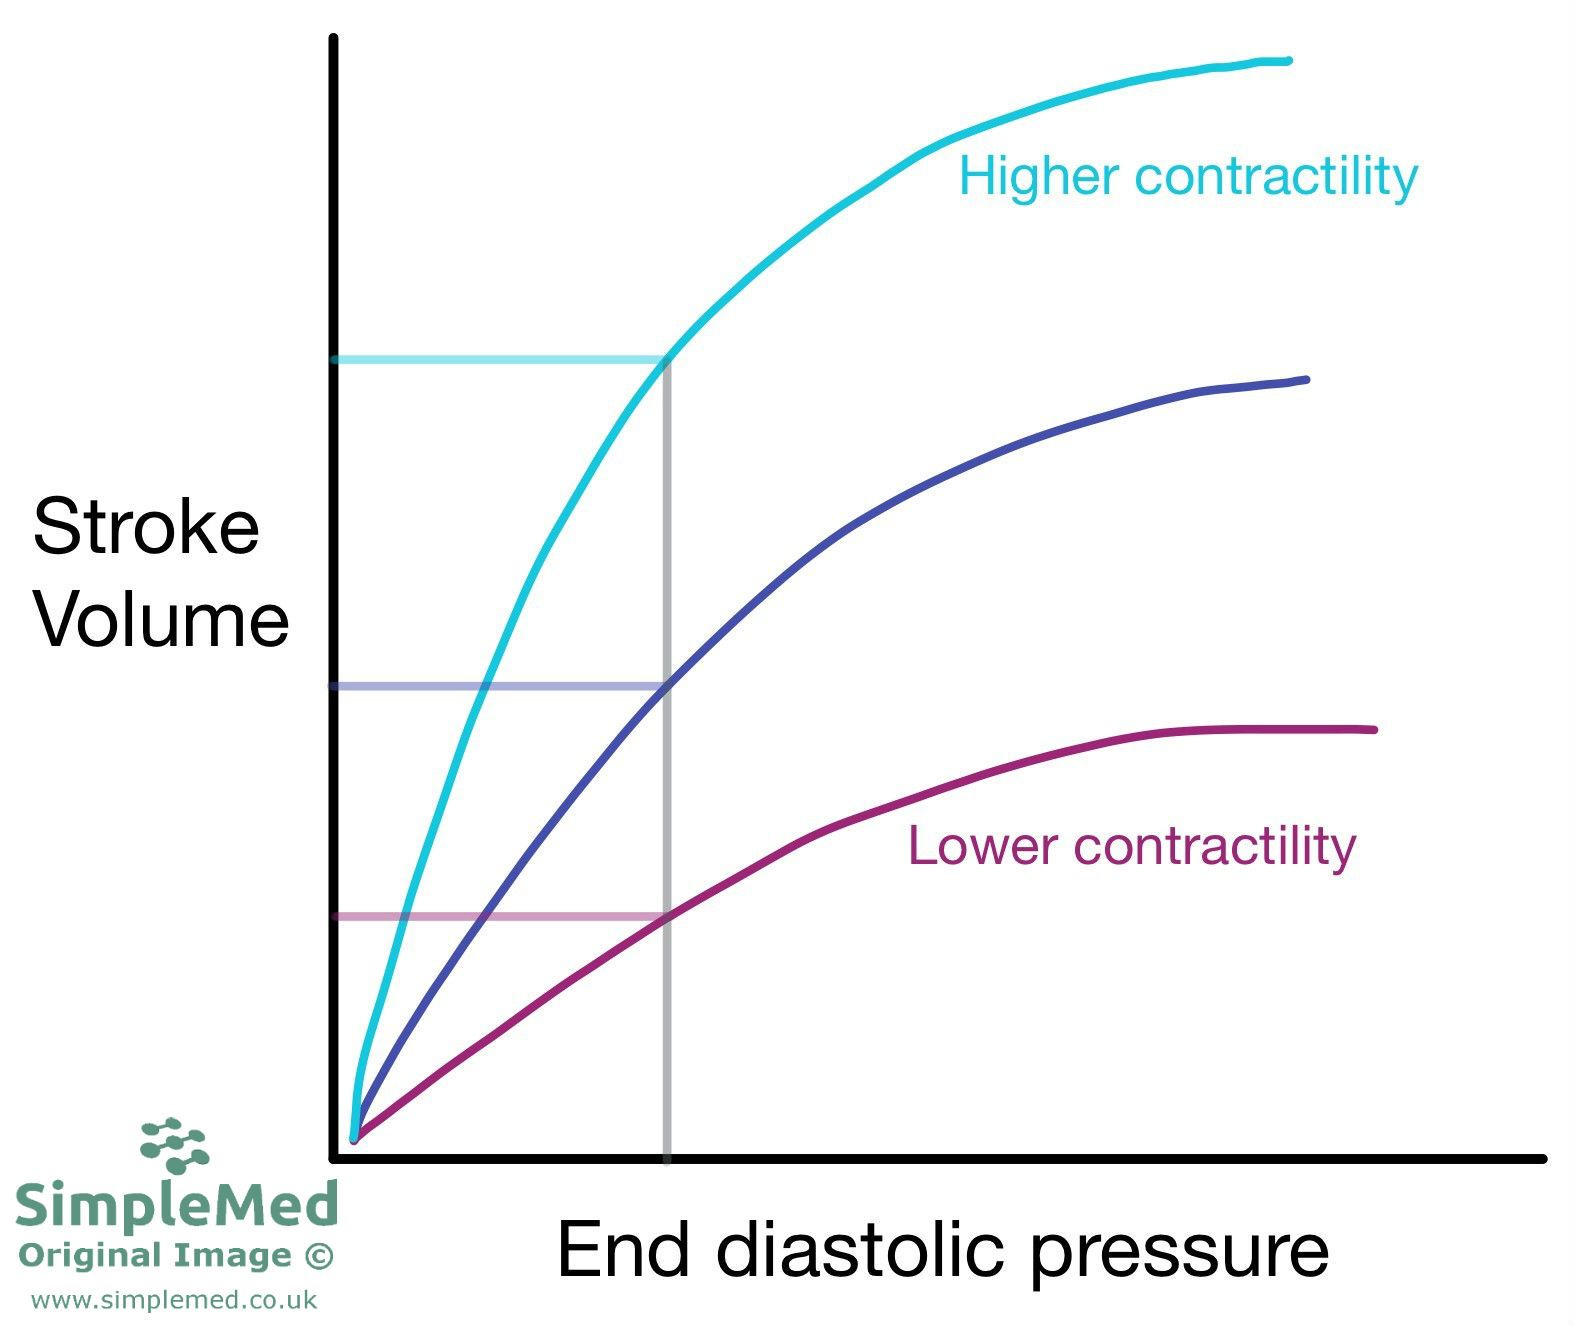
Diagram - How the stroke volume changes with the end diastolic pressure
SimpleMed original by Dr. Bethany Turner
Stimulation from the sympathetic nervous system can increase heart contractility. Sympathetic stimulation makes the ventricles pump harder, leading to an increased SV at a given filling (in the diagram above, the curve for higher contractility lies higher).
Filling stretches the sarcomeres (the contractile units of muscle fibres) before contraction. Within the physiological range, a longer sarcomere produces more force. This is called length-dependent activation (the muscle responds more strongly the further it is stretched). It includes increased calcium sensitivity (a stronger response to the same amount of calcium) of the contractile proteins (actin and myosin, the filaments that slide past each other to shorten the muscle). A failing ventricle may gain little extra stroke volume from further filling. One reason is that length-dependent activation is depressed in failing heart muscle. It is not simply that actin and myosin lose contact.
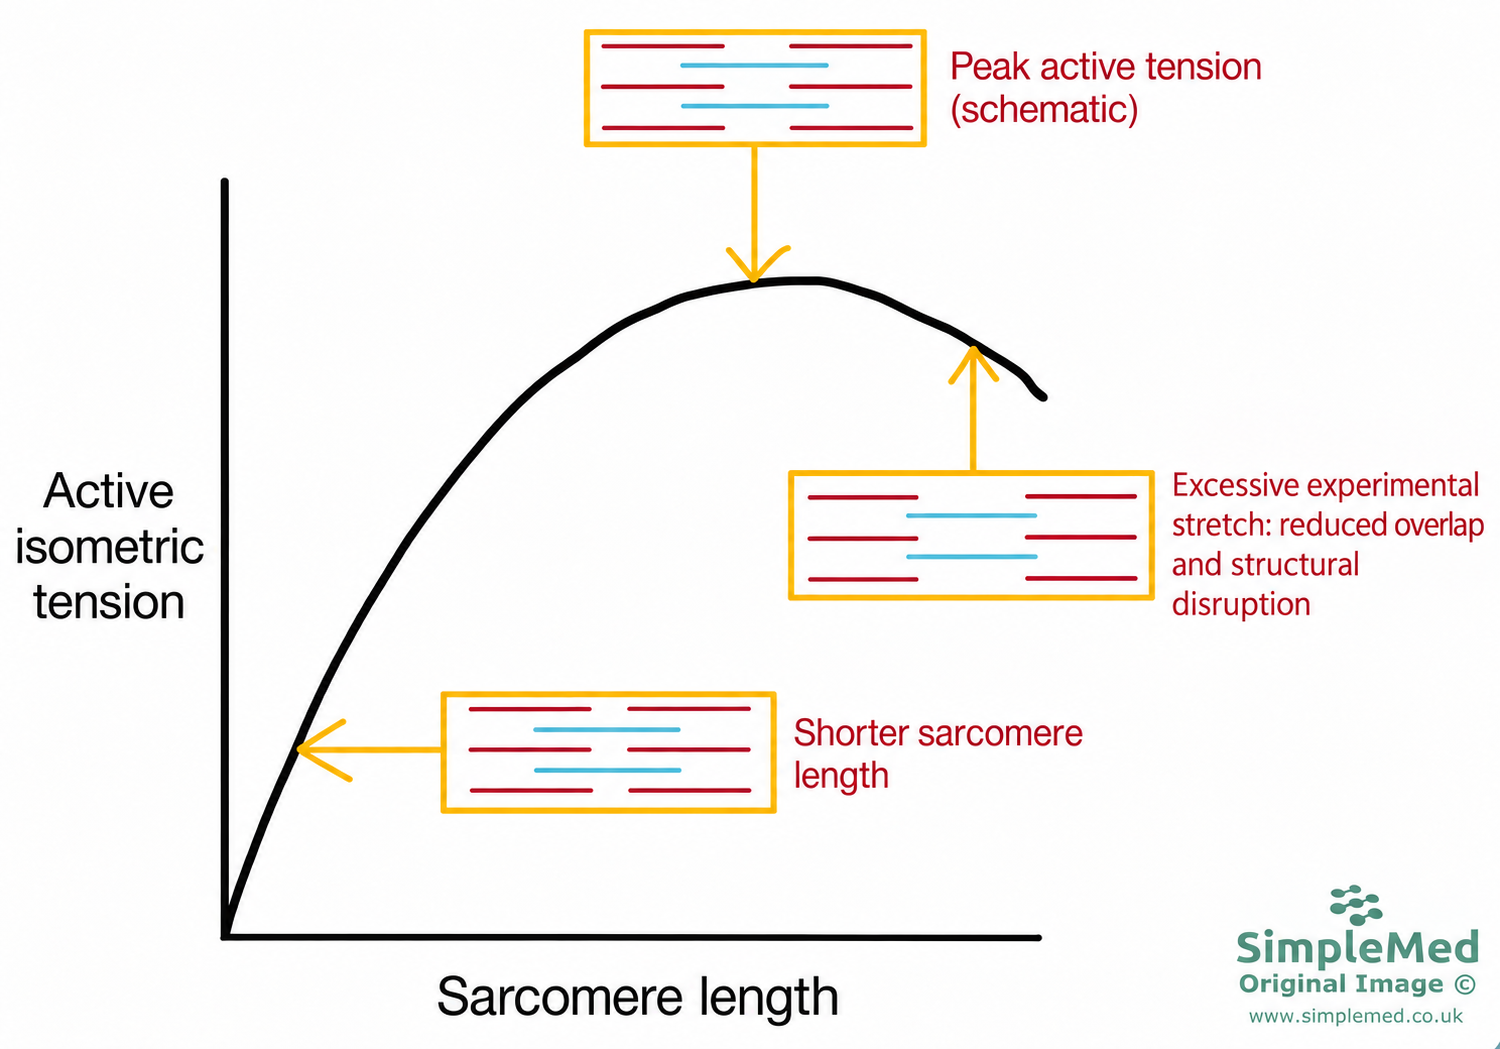
Diagram - Schematic muscle length-tension relationship. Active tension can fall with excessive experimental stretch through reduced filament overlap (less overlap between the actin and myosin filaments) and structural changes. This diagram is not a ventricular stroke-volume curve or an explanation of ordinary congestion (fluid backing up in the circulation). Physiological cardiac length-dependent activation includes increased calcium sensitivity.
SimpleMed original by Dr. Bethany Turner
Autonomic Control of the Heart
The autonomic nervous system is important for many physiological functions and for control of the body systems. In the cardiovascular system (CVS) it controls the heart rate, force of contraction, and peripheral resistance of blood vessels.
The parasympathetic nervous system (PNS) control of the heart is via the vagus nerve. The vagus has pre-ganglionic fibres (running from the brainstem to a ganglion, a cluster of nerve cell bodies). These synapse with the post-ganglionic fibres (running from the ganglion to the heart) on the epicardial surface (the outer surface of the heart) or within the heart walls, at the sinoatrial (SA) node (the heart's pacemaker) and the atrioventricular (AV) node. The post-ganglionic fibres release acetylcholine (ACh), which acts on M2 muscarinic receptors (the acetylcholine receptors that slow the heart), causing a negative chronotropic effect (slowing of the heart rate).
- PNS causes a negative chronotropic effect by decreasing the slope of the pacemaker potential (the slow rise in membrane voltage in SA node cells that triggers each beat). It does this by increasing potassium ion conductance (how easily potassium ions flow out of the cell) and decreasing cAMP (cyclic AMP, a signalling molecule inside the cell).
The sympathetic nervous system (SNS) control of the heart is via post-ganglionic fibres from the sympathetic trunk (the chain of sympathetic ganglia beside the spine). These sympathetic fibres supply the SA node, AV node and myocardium (heart muscle). The post-ganglionic fibres release noradrenaline (NA), which acts on β1-adrenoceptors (beta-1 receptors on the heart). This has a positive chronotropic effect (the heart beats faster) and a positive inotropic effect (the heart beats with more force).
Sympathetic stimulation increases cyclic AMP (cAMP) in SA node cells. cAMP binds directly to hyperpolarisation-activated, cyclic nucleotide-gated (HCN) channels. These channels carry the mixed Na+/K+ funny current (If, the inward current that drives the pacemaker potential), and cAMP shifts their activation towards more positive voltages. Greater inward pacemaker current helps the cells reach threshold sooner, increasing the rate at which they fire.
cAMP also activates protein kinase A (PKA), an enzyme that adds phosphate groups to other proteins. In ventricular myocytes (ventricular muscle cells), this enhances calcium entry and calcium release from the sarcoplasmic reticulum (the calcium store inside muscle cells), increasing the force of contraction.
Sympathetic stimulation also speeds calcium reuptake (calcium being pumped back into the sarcoplasmic reticulum) and so speeds ventricular relaxation. Faster relaxation helps the ventricles fill when heart rate is higher. Faster relaxation is separate from the rise in heart rate. The pacemaker rhythm sets the heart rate, and faster ventricular relaxation does not make the SA node fire sooner.

Diagram - The nerve supply to the heart and the effects it has on the heart
Creative commons source by OpenStax College [CC BY 3.0 (https://creativecommons.org/licenses/by/3.0)]
Autonomic Control of Vasculature
The sympathetic nervous system constantly releases NA at low levels to cause a small amount of vasoconstriction of blood vessels. This is the normal vasomotor tone of the blood vessels. This slight sympathetic activity allows the blood vessels to contract or dilate depending on the needs of the tissue by increasing or decreasing the level of NA. The NA acts on α1-adrenoceptors (alpha-1 receptors for noradrenaline on vessel muscle) present on most arteries and veins to cause some vasoconstriction to maintain the vasomotor tone.
Noradrenaline activates α1-adrenoceptors, stimulating calcium release from the sarcoplasmic reticulum (the calcium store inside muscle cells) through inositol trisphosphate (IP3, a signalling molecule that triggers the release). Calcium binds calmodulin (a calcium-binding protein), which activates myosin light chain kinase (MLCK). MLCK adds phosphate groups to myosin light chains, enabling smooth muscle contraction and vasoconstriction.
The same receptor pathway produces diacylglycerol (DAG, a second signalling molecule made alongside IP3), which activates protein kinase C (PKC, an enzyme that adds phosphate groups to proteins). PKC can phosphorylate (add a phosphate group to) the inhibitory protein CPI-17, and CPI-17 then reduces myosin light chain phosphatase (MLCP) activity. MLCP normally removes phosphate groups from myosin light chains; it does not directly inhibit MLCK. Reducing MLCP activity helps sustain myosin phosphorylation and contraction at a given calcium concentration, a process called calcium sensitisation (the muscle contracts more strongly at the same calcium level).
Adrenaline stimulates both α- and β-adrenoceptors. At low concentrations, relaxation produced by β2 receptors can predominate in vascular beds (the networks of small vessels in a tissue) with these receptors. As concentration rises, vasoconstriction produced by α receptors becomes more prominent and can dominate the overall vascular response. The rise in concentration shifts the balance of effects; it does not switch off β-receptor activity.
In anaphylaxis, intramuscular adrenaline is the first-line treatment (the treatment given first). Its α effects help reverse peripheral vasodilation and reduce tissue oedema, while its β effects support cardiac contraction and dilate the airways. Through β2 receptors on mast cells (immune cells that release histamine), adrenaline also reduces the release of histamine and other chemicals that drive the allergic reaction. Together, these alpha and beta actions help explain why adrenaline works; α1 stimulation alone would not do all of this.
Baroreceptors (stretch-sensitive pressure sensors) are located in the aortic arch (the curve of the aorta above the heart) and the carotid sinus. The carotid sinus is a small widening of the carotid artery where the common carotid artery divides in two.
When blood pressure is increased, the baroreceptor nerve endings are stretched, which makes them fire more often. This information is sent to the medullary control centre (the cardiovascular control centre in the medulla oblongata, part of the brainstem). The centre sends out signals via the ANS to decrease heart rate and contractility. It also lowers vascular resistance (TPR) by reducing sympathetic activity to the blood vessels. Together, these changes decrease BP.
With sustained hypertension, baroreceptors can adapt so that their response range shifts towards higher blood pressures. This is called resetting: it changes the relationship between blood pressure and the rate at which the receptors send nerve impulses, rather than switching the receptors off. They still fire and respond to short-term rises and falls in pressure, helping to limit sudden fluctuations. However, the reflex does not by itself restore persistently raised blood pressure to its previous level.
Reviewed by: Dr. Marcus Judge
- 19532

