

All done here! Check out our other subjects!
Core
Antibodies (also known as immunoglobulins, Ig) are Y-shaped proteins. They are made by plasma cells, which develop from B-cells (a type of lymphocyte). B-cells become plasma cells when the adaptive immune system is exposed to antigens (see article on adaptive immunity).
The antibody population produced in the body is polyclonal. This means that there are multiple B cells producing multiple different types of antibodies all simultaneously, creating a population of antibodies that are all different. They bind to different parts of antigens (epitopes), and several may bind the same antigen.
Monoclonal antibodies (mAb) are antibodies made artificially by creating a population of identical cloned B-cells derived from a single parent B-cell. Every antibody in this monoclonal population will be identical. Early monoclonal antibodies were made with hybridoma technology (introduced in 1975). Many therapeutic antibodies are now made by genetic engineering (recombinant DNA technology) and produced in cultured cells, but the result is still a population of identical antibodies.
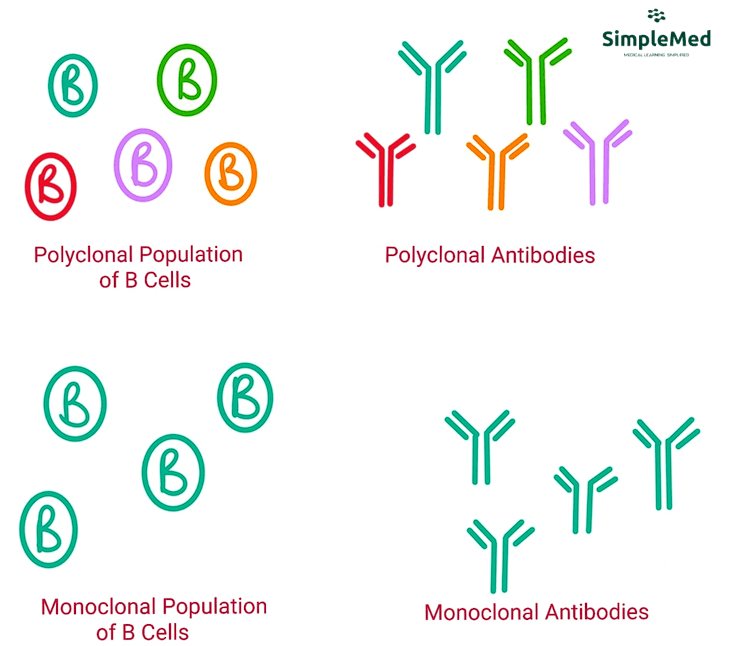
Diagram - Difference between a population of polyclonal antibodies produced by a variety of parent B cells, and a population of monoclonal antibodies produced by a single type of parent B cell
SimpleMed original by Dr. Maddie Swannack
Types of Monoclonal Antibodies
The historical source-based nomenclature (naming system) distinguishes murine (-omab), chimeric (-ximab), humanised (-zumab) and fully human (-umab) antibodies. These endings remain useful for established medicines. For newly named antibodies, WHO has replaced this scheme with categories based on structure: -tug (unmodified full-length antibodies), -bart (full-length antibodies with engineered changes), -ment (fragments) and -mig (bispecific or multispecific antibodies). The old source endings therefore no longer apply to every new antibody.
Murine antibodies (historically -omab) are entirely derived from a mouse source. Because they are foreign proteins, they have an increased potential for immunogenicity (provoking an unwanted immune response) in humans. This can cause infusion reactions and can reduce how well the medicine works. Some patients may also find an animal-derived medicine unacceptable, for example because of religious beliefs or vegetarianism.
Chimeric antibodies (historically -ximab) combine non-human variable domains (the parts of the antibody that differ between antibodies and bind the antigen) with human constant regions (the parts that are the same between antibodies of one class). The variable domains lie in the antigen-binding parts of both arms of the Y. The distinction is therefore not simply mouse arms on a human stem (the base of the Y). A fixed percentage of human sequence is also not the definition.
Humanised antibodies (historically -zumab) have predominantly human immunoglobulin sequences with a non-human contribution concentrated in the complementarity-determining regions, the antigen-binding loops. Additional non-human amino acids may be kept so that the antibody still binds well. This category is not defined by a fixed percentage of human sequence, or by an entirely non-human binding region.
Fully human antibodies (historically -umab) use human immunoglobulin sequences. This describes sequence origin and does not mean that the medicine must be harvested directly from a person.
Humanisation and human sequence reduce the contribution of foreign-species sequence to immunogenicity. However, humanised and fully human antibodies can still provoke anti-drug antibodies (the patient’s own antibodies against the medicine), including responses against their distinctive binding regions. Actual risk depends on the product, patient and treatment conditions. Human sequence does not guarantee immune tolerance, and some infusion reactions have other causes.
Clinical Use of Monoclonal Antibodies
Monoclonal antibodies are used in clinical practice and in research, for both therapeutic and diagnostic purposes. Understanding which antigens are associated with specific cancer cells and which are found on normal tissue cells helps choose antigen targets for developing appropriate monoclonal antibodies.
When used for therapeutics, they can work in multiple ways:
- Bind to cell surface receptors (antigens) to activate or inhibit signalling pathways within the cell.
- Induce cell death by binding to antigens and activating antibody-dependent cell-mediated cytotoxicity (ADCC, where immune cells destroy the antibody-coated cell) or complement-dependent cytotoxicity (CDC, where complement proteins of the innate immune system destroy it).
- Bind to antigens prompting internalisation (the cell takes the antibody inside by endocytosis). This allows an antibody that carries a toxin (a conjugated antibody, described below) to release the toxin directly inside the target cancer cells.
- Block inhibitory immune checkpoints (signals that act as brakes on T-cells), thereby enhancing T-cell-mediated immune responses against cancer cells.
- Neutralise a cytokine (a signalling protein of the immune system), such as tumour necrosis factor alpha, which infliximab blocks, or destroy a type of immune cell, as rituximab does to B-cells. These actions treat immune-mediated conditions such as Crohn’s disease and rheumatoid arthritis.
Conjugated monoclonal antibodies are monoclonal antibodies that have been tagged with either a cytotoxic (chemotherapy) drug or a radioactive substance (a radionuclide, an atom that gives off radiation, such as iodine-131 or yttrium-90). This delivers treatment to cells that carry the target antigen. The effect is more localised and can reduce systemic side effects, although some binding to normal tissues may still occur if the antigen is also expressed on healthy cells.
Monoclonal antibodies are also used in routine laboratory techniques, because each one binds a single target very specifically. Examples are enzyme-linked immunosorbent assay (ELISA, which detects a protein in a sample), immunohistochemistry (which shows where a protein sits in a tissue sample) and Western blotting (which detects a protein after it has been separated by size).
Side Effects of Monoclonal Antibodies
Foreign-species sequence is one contributor to an immune response against a therapeutic antibody. Responses vary with the product, patient and treatment; antibody origin alone cannot reliably rank the clinical risk of every medicine.
Some patients will experience no symptoms or mild symptoms such as fatigue during treatment with monoclonal antibodies.
Others will have a mild reaction following the initial infusion and tolerate subsequent infusions better.
Finally, a few people develop severe infusion-related reactions. These include anaphylaxis and cytokine release syndrome (a widespread inflammatory reaction caused by the release of cytokines, the signalling proteins of the immune system). In some reactions the immune system recognises the antibody as foreign, but not in all of them.
To manage infusion-related reactions appropriately, patients need to be well informed about the red flags (warning signs) of a possible reaction to the infusion. They should contact clinical staff immediately if they experience unexpected side effects. Precautionary measures can also be taken: depending on the medicine, doctors may prescribe prophylactic (preventive) steroids, antihistamines or paracetamol before the infusion to reduce the risk or severity of an infusion-related reaction. Premedication does not prevent every reaction, and the regimen for each medicine is set out in its product literature. Many monoclonal antibody infusions are started at a slow rate and later increased in a stepwise manner if well tolerated. The exact schedule is set out in the product literature, and some monoclonal antibodies are given by subcutaneous injection instead.
Finally, appropriate emergency drugs to treat infusion-related reactions should always be readily available, or prescribed according to local protocol, prior to initiating patient treatment.
Edited by: Dr. Maddie Swannack
Reviewed by: Dr. Thomas Burnell and Dr. Marcus Judge
- 756
